


Summary of Product Characteristics (SmPC) - Akizza 75 mcg /20 mcg tablets
1 NAME OF THE MEDICINAL PRODUCT
Akizza 75 mcg /20 mcg tablets
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each film coated tablet contains 75 micrograms gestodene and 20 micrograms
Ethinylestradiol
Excipient with known effect contains 68.97 mg lactose (as lactose monohydrate).
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Film coated tablets
Round, white to off white, biconvex tablet debossed ‘A’ on one side and other side plain.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Oral contraception and the recognised gynaecological indications for such oestrogen-progestogen combinations.
The decision to prescribe Akizza should take into consideration the individual woman's current risk factors, particularly those for venous thromboembolism (VTE), and how the risk of VTE with Akizza compares with other combined hormonal contraceptives (CHCs) (see sections 4.3 and 4.4).
4.2 Posology and method of administration
First treatment cycle: 1 tablet daily for 21 days, starting on the first day of the menstrual cycle. Contraceptive protection begins immediately.
Subsequent cycles: Tablet taking from the next pack of Akizza is continued after a 7-day interval, beginning on the same day of the week as the first pack.
Changing from 21-day combined oral contraceptives: The first tablet of Akizza should be taken on the first day immediately after the end of the previous oral contraceptive course. Additional contraceptive precautions are not required.
Changing from a combined Every Day pill (28 day tablets):
Akizza should be started after taking the last active tablet from the Every Day Pill pack. The first Akizza tablet is taken the next day. Additional contraceptive precautions are not then required.
Changing from a progestogen-only pill (POP):
The first tablet of Akizza should be taken on the first day of bleeding, even if a POP has already been taken on that day. Additional contraceptive precautions are not then required. The remaining progestogen-only pills should be discarded.
Post-partum and post-abortum use: After pregnancy, oral contraception can be started 21 days after a vaginal delivery, provided that the patient is fully ambulant and there are no puerperal complications. Additional contraceptive precautions will be required for the first 7 days of tablet taking. Since the first post-partum ovulation may precede the first bleeding, another method of contraception should be used in the interval between childbirth and the first course of tablets. After a first-trimester abortion, oral contraception may be started immediately in which case no additional contraceptive precautions are required.
Special circumstances requiring additional contraception
Incorrect administration: A single delayed tablet should be taken as soon as possible, and if this can be done within 12 hours of the correct time, contraceptive protection is maintained. With longer delays, additional contraception is needed. Only the most recently delayed tablet should be taken, earlier missed tablets being omitted, and additional non-hormonal methods of contraception (except the rhythm or temperature methods) should be used for the next 7 days, while the next 7 tablets are being taken. Additionally, therefore, if tablet(s) have been missed during the last days of a pack, there should be no break before the next pack is started. In this situation, a withdrawal bleed should not be expected until the end of the second pack. Some breakthrough bleeding may occur on tablet taking days but this is not clinically significant. If the patient does not have a withdrawal bleed during the tablet-free interval following the end of the second pack, the possibility of pregnancy must be ruled out before starting the next pack.
Gastro-intestinal upset: Vomiting or diarrhoea may reduce the efficacy of oral contraceptives by preventing full absorption. If vomiting or diarrhoea occurs within 4 hours of taking an Akizza tablet-taking from the current pack should be continued. Additional non-hormonal methods of contraception (except the rhythm or temperature methods) should be used during the gastro-intestinal upset and for 7 days following the upset. If these 7 days overrun the end of a pack, the next pack should be started without a break. In this situation, a withdrawal bleed should not be expected until the end of the second pack. If the patient does not have a withdrawal bleed during the tablet-free interval following the end of the second pack, the possibility of pregnancy must be ruled out before starting the next pack. Other methods of contraception should be considered if the gastro-intestinal disorder is likely to be prolonged.
Children: Not applicable.
Elderly: Not applicable.
4.3 Contraindications
Combined hormonal contraceptives (CHCs) should not be used in the following conditions. Should any of the conditions appear for the first time during CHC use, the product should be stopped immediately.
Presence or risk of venous thromboembolism (VTE)
Venous thromboembolism – current VTE (on anticoagulants) or history of
(e.g. deep venous thrombosis [DVT] or pulmonary embolism [PE])
- Known hereditary or acquired predisposition for venous thromboembolism, such as APC-resistance, (including Factor V Leiden), antithrombin-III-deficiency, protein C deficiency, protein S deficiency
- Major surgery with prolonged immobilisation (see section 4.4)
- A high risk of venous thromboembolism due to the presence of multiple risk factors (see section 4.4)
Presence or risk of arterial thromboembolism (ATE)
- Arterial thromboembolism – current arterial thromboembolism, history of arterial thromboembolism (e.g. myocardial infarction) or prodromal condition (e.g. angina pectoris)
- Cerebrovascular disease – current stroke, history of stroke or prodromal condition (e.g. transient ischaemic attack, TIA)
- Known hereditary or acquired predisposition for arterial thromboembolism, such as hyperhomocysteinaemia and anti-phospholipid antibodies (anticardiolipin-antibodies, lupus anticoagulant)
- History of migraine with focal neurological symptoms
A high risk of arterial thromboembolism due to multiple risk factors (see section 4.4) or to the presence of one serious risk factor such as:
- diabetes mellitus with vascular symptoms
- severe hypertension
- severe dyslipoproteinaemia
- Presence or history of severe hepatic disease, e.g. active viral hepatitis and severe cirrhosis, as long as liver function values have not returned to normal.
- Presence or history of liver tumours (benign or malignant).
- Current or history of breast cancer.
- Hypersensitivity to the active substance(s) or to any of the excipients.
Relevant UK clinical guidance should also be consulted.
Akizza is contraindicated for concomitant use with the medicinal products containing ombitasvir/paritaprevir/ritonavir or dasabuvir or medicinal products containing glecaprevir/pibrentasvir (see sections 4.4 and section 4.5).
4.4 Special warnings and precautions for use
Warnings
- If any of the conditions or risk factors mentioned below is present, the suitability of Akizza should be discussed with the woman.
- In the event of aggravation, or first appearance of any of these conditions or risk factors, the woman should be advised to contact her doctor to determine whether the use of Akizza should be discontinued.
Risk of venous thromboembolism (VTE)
The use of any combined hormonal contraceptive (CHC) increases the risk of venous thromboembolism (VTE) compared with no use. Products that contain levonorgestrel, norgestimate or norethisterone are associated with the lowest risk of VTE. Other products such as Akizza may have up to twice this level of risk. The decision to use any product other than one with the lowest VTE risk should be taken only after a discussion with the woman to ensure she understands the risk of VTE with Akizza, how her current risk factors influence this risk, and that her VTE risk is highest in the first ever year of use. There is also some evidence that the risk is increased when a CHC is re-started after a break in use of 4 weeks or more.
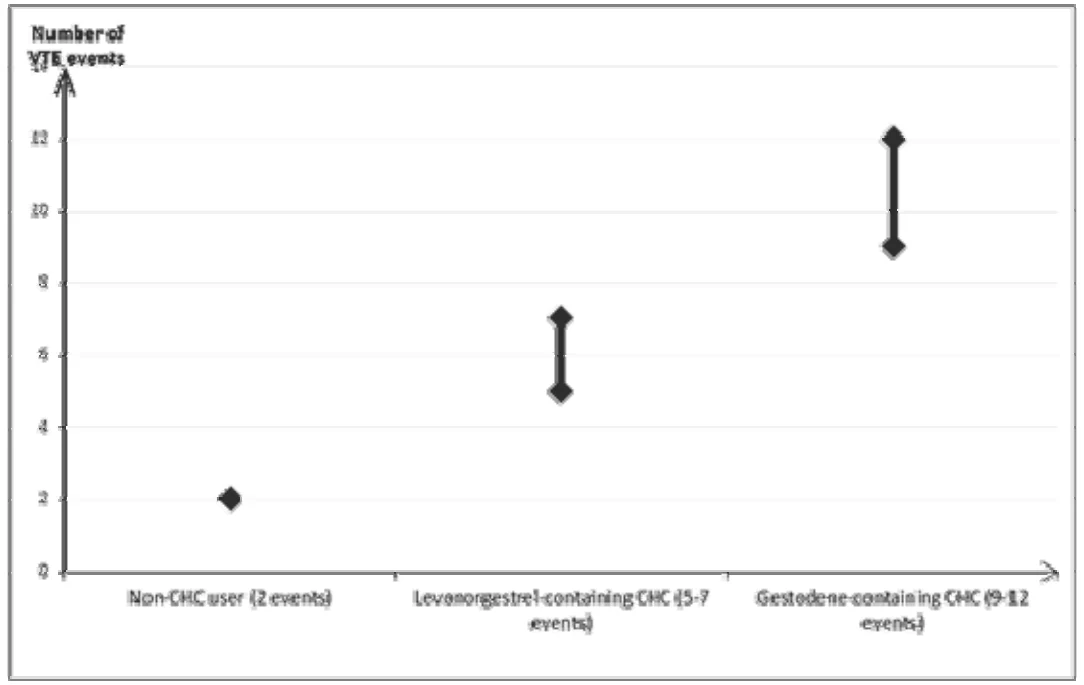
In women who do not use a CHC and are not pregnant, about 2 out of 10,000 will develop a VTE over the period of one year. However, in any individual woman the risk may be far higher, depending on her underlying risk factors (see below).
It is estimated1 that out of 10,000 women who use a CHC containing gestodene between 9 and 12 women will develop a VTE in one year; this compares with about 62 in women who use a levonorgestrel-containing CHC.
In both cases, the number of VTEs per year is fewer than the number expected during pregnancy or in the postpartum period.
VTE may be fatal in 1-2% of cases.
Number of VTE events per 10,000 women in one year
| Extremely rarely, thrombosis has been reported to occur in CHC users in other blood vessels, | |
| e.g. hepatic, mesenteric, renal, cerebral or retinal veins and arteries. | |
| 1 These incidences were estimated from the totality of the epidemiological study data, using relative risks for the different | |
| products compared with levonorgestrel-containing CHCs. | |
| 2 Mid-point of range of 5-7 per 10,000 WY, based on a relative risk for CHCs containing levonorgestrel versus non-use of | |
| approximately 2.3 to 3.6. | |
| Risk factors for VTE | |
| The risk for venous thromboembolic complications in CHC users may increase substantially | |
| in a woman with additional risk factors, particularly if there are multiple risk factors (see | |
| table). | |
| Akizza is contraindicated if a woman has multiple risk factors that put her at high risk of | |
| venous thrombosis (see section 4.3). If a woman has more than one risk factor, it is possible | |
| that the increase in risk is greater than the sum of the individual factors – in this case her total | |
| risk of VTE should be considered. If the balance of benefits and risks is considered to be | |
| negative a CHC should not be prescribed (see section 4.3). | |
| Table: Risk factors for VTE | |
| Risk factor | Comment |
| Obesity (body mass index over 30 | Risk increases substantially as BMI rises. |
| kg/m2) | Particularly important to consider if other risk factors |
| also present. | |
| Prolonged immobilisation, major | In these situations it is advisable to discontinue use of |
| surgery, any surgery to the legs or | the pill (in the case of elective surgery at least four |
| pelvis, neurosurgery, or major trauma | weeks in advance) and not resume until two weeks |
| Note: temporary immobilisation | after complete remobilisation. Another method of |
| including air travel >4 hours can also | contraception should be used to avoid unintentional |
| be a risk factor for VTE, particularly | pregnancy. |
| in women with other risk factors | Antithrombotic treatment should be considered if |
| Akizza has not been discontinued in advance. | |
| Positive family history (venous | If a hereditary predisposition is suspected, the woman |
| thromboembolism ever in a sibling or | should be referred to a specialist for advice before |
| parent especially at a relatively early | deciding about any CHC use. |
| age e.g. before 50). | |
| Other medical conditions associated | Cancer, systemic lupus erythematosus, haemolytic |
| with VTE | uraemic syndrome, chronic inflammatory bowel |
| disease (Crohn's disease or ulcerative colitis) and sickle | |
| cell disease. | |
| Increasing age | Particularly above 35 years. |
| There is no consensus about the possible role of varicose veins and superficial | |
| thrombophlebitis in the onset or progression of venous thrombosis. | |
| The increased risk of thromboembolism in pregnancy, and particularly the 6 week period of | |
| the puerperium, must be considered (for information on “Pregnancy and lactation” see | |
| Section 4.6). | |
| Symptoms of VTE (deep vein thrombosis and pulmonary embolism) | |
| In the event of symptoms women should be advised to seek urgent medical attention and to | |
| inform the healthcare professional that she is taking a CHC. | |
| Symptoms of deep vein thrombosis (DVT) can include: | |
| |
| |
| |
| Symptoms of pulmonary embolism (PE) can include: | |
| |
| |
| |
| |
| |
| Some of these symptoms (e.g. “shortness of breath”, “coughing”) are non-specific and might | |
| be misinterpreted as more common or less severe events (e.g. respiratory tract infections). | |
| Other signs of vascular occlusion can include: sudden pain, swelling and slight blue | |
| discoloration of an extremity. | |
| If the occlusion occurs in the eye symptoms can range from painless blurring of vision which | |
| can progress to loss of vision. Sometimes loss of vision can occur almost immediately. | |
| Risk of arterial thromboembolism (ATE) | |
| Epidemiological studies have associated the use of CHCs with an increased risk for arterial | |
| thromboembolism (myocardial infarction) or for cerebrovascular accident (e.g. transient | |
| ischaemic attack, stroke). Arterial thromboembolic events may be fatal. | |
| Risk factors for ATE | |
| The risk of arterial thromboembolic complications or of a cerebrovascular accident in CHC | |
| users increases in women with risk factors (see table). Akizza is contraindicated if a woman | |
| has one serious or multiple risk factors for ATE that puts her at high risk of arterial | |
| thrombosis (see section 4.3). If a woman has more than one risk factor, it is possible that the | |
| increase in risk is greater than the sum of the individual factors - in this case her total risk | |
| should be considered. If the balance of benefits and risks is considered to be negative a CHC | |
| should not be prescribed (see section 4.3). | |
| Table: Risk factors for ATE | |
| Risk factor | Comment |
| Increasing age | Particularly above 35 years |
| Smoking | Women should be advised not to smoke if they wish |
| to use a CHC. Women over 35 who continue to smoke | |
| should be strongly advised to use a different method | |
| of contraception. | |
| Hypertension | |
| Obesity (body mass index over 30 | Risk increases substantially as BMI increases. |
| kg/m2) | Particularly important in women with additional risk |
| factors | |
| Positive family history (arterial | If a hereditary predisposition is suspected, the woman |
| thromboembolism ever in a sibling or | should be referred to a specialist for advice before |
| parent especially at relatively early | deciding about any CHC use |
| age e.g. below 50). | |
| Migraine | An increase in frequency or severity of migraine |
| during CHC use (which may be prodromal of a | |
| cerebrovascular event) may be a reason for immediate | |
| discontinuation | |
| Other medical conditions associated | Diabetes mellitus, hyperhomocysteinaemia, valvular |
| with adverse vascular events | heart disease and atrial fibrillation, |
| dyslipoproteinaemia and systemic lupus | |
| erythematosus. | |
| Symptoms of ATE | |
| In the event of symptoms women should be advised to seek urgent medical attention and to | |
| inform the healthcare professional that she is taking a CHC. | |
| Symptoms of a cerebrovascular accident can include:- sudden numbness or weakness of the | |
| face, arm or leg, especially on one side of the body; | |
| |
| |
| |
| |
| |
| Temporary symptoms suggest the event is a transient ischaemic attack (TIA). | |
| Symptoms of myocardial infarction (MI) can include: | |
| |
| below the breastbone; | |
| |
| |
| |
| |
| |
Medical Examination/Consultation Prior to the initiation or reinstitution of Akizza a complete medical history (including family history) should be taken and pregnancy must be ruled out. Blood pressure should be measured and a physical examination should be performed, guided by the contra-indications (see section 4.3) and warnings (see section 4.4). It is important to draw a woman's attention to the information on venous and arterial thrombosis, including the risk of Akizza compared with other CHCs, the symptoms of VTE and ATE, the known risk factors and what to do in the event of a suspected thrombosis.
The woman should also be instructed to carefully read the user leaflet and to adhere to the advice given. The frequency and nature of examinations should be based on established practice guidelines and be adapted to the individual woman.
Women should be advised that hormonal contraceptives do not protect against HIV infections (AIDS) and other sexually transmitted diseases.
Undiagnosed vaginal bleeding that is suspicious for underlying conditions should be investigated.
Conditions which require strict medical supervision
The decision to prescribe the COC must be made using clinical judgement and in consultation with the woman.
Exacerbation or first appearance of any of these conditions may indicate that use of the oral contraceptive should be discontinued:
- Diabetes mellitus with mild vascular disease or mild nephropathy, retinopathy or neuropathy
Hypertension that is adequately controlled, i.e. systolic >140 to159 mm Hg or diastolic >
90 to 94mmHg (see also Section 4.4 'Reasons for stopping oral contraception immediately')
- porphyria
- obesity
- migraine
- cardiovascular diseases
Reasons for stopping oral contraception immediately:
When stopping oral contraception non-hormonal contraception should be used to ensure contraceptive protection is maintained.
- 1. Occurrence for the first time, or exacerbation, of migrainous headaches or unusually frequent or unusually severe headaches
- 2. Sudden disturbances of vision, of hearing or other perceptual disorders
- 3. First signs of thrombosis or blood clots (e.g. unusual pains in or swelling of the leg(s), stabbing pains on breathing or coughing for no apparent reason). Feeling of pain and tightness in the chest
- 4. At least four weeks before an elective major operation (e.g. abdominal, orthopaedic), any surgery to the legs, medical treatment for varicose veins or prolonged immobilisation, e.g. after accidents or surgery. Do not restart until 2 weeks after full ambulation. In case of emergency surgery, thrombotic prophylaxis is usually indicated e.g. subcutaneous heparin
- 5. Onset of jaundice, hepatitis, itching of the whole body
- 6. Significant rise in blood pressure
- 7. Severe upper abdominal pain or liver enlargement
- 8. Clear exacerbation of conditions known to be capable of deteriorating during oral contraception or pregnancy (see section 4.4 'Conditions which deteriorate in pregnancy or during previous COC use' under 'Other conditions').
Tumours
Numerous epidemiological studies have been reported on the risks of ovarian, endometrial, cervical and breast cancer in women using combined oral contraceptives. The evidence is clear that high dose combined oral contraceptives offer substantial protection against both ovarian and endometrial cancer. However, it is not clear whether low dose COCs confer protective effects to the same level.
- Breast cancer
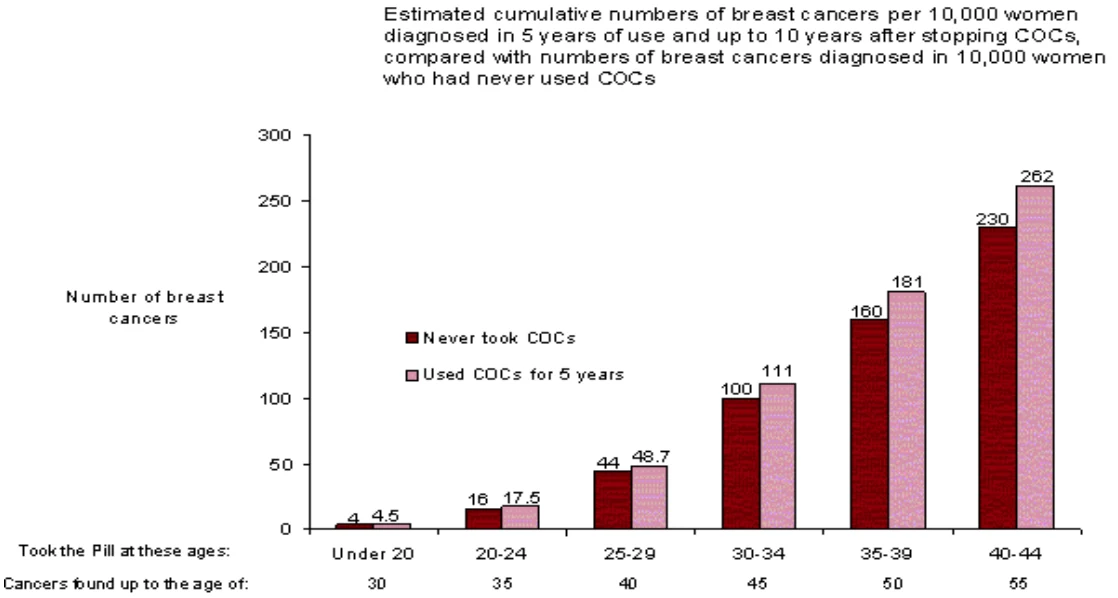
A meta-analysis from 54 epidemiological studies reported that there is a slightly increased relative risk (RR = 1.24) of having breast cancer diagnosed in women who are currently using combined oral contraceptives (COCs). The observed pattern of increased risk may be due to an earlier diagnosis of breast cancer in COC users, the biological effects of COCs or a combination of both. The additional breast cancers diagnosed in current users of COCs or in women who have used COCs in the last ten years are more likely to be localised to the breast than those in women who never used COCs.
Breast cancer is rare among women under 40 years of age whether or not they take COCs. Whilst this background risk increases with age, the excess number of breast cancer diagnoses in current and recent COC users is small in relation to the overall risk of breast cancer (see bar chart).
The most important risk factor for breast cancer in COC users is the age women discontinue the COC; the older the age at stopping, the more breast cancers are diagnosed. Duration of use is less important and the excess risk gradually disappears during the course of the 10 years after stopping COC use such that by 10 years there appears to be no excess.
The possible increase in risk of breast cancer should be discussed with the user and weighed against the benefits of COCs taking into account the evidence that they offer substantial protection against the risk of developing certain other cancers (e.g. ovarian and endometrial cancer).
- Cervical Cancer
The most important risk factor for cervical cancer is persistent HPV infection. Some epidemiological studies have indicated that long-term use of COCs may further contribute to this increased risk but there continues to be controversy about the extent to which this finding is attributable to confounding effects, e.g., cervical screening and sexual behaviour including use of barrier contraceptives.
- Liver Cancer
In rare cases benign and, in even rarer cases, malignant liver tumours leading in isolated cases to life-threatening intra-abdominal haemorrhage have been observed after the use of hormonal substances such as those contained in Akizza. If severe upper abdominal complaints, liver enlargement or signs of intra-abdominal haemorrhage occur, the possibility of a liver tumour should be included in the differential diagnosis.
Other conditions
The possibility cannot be ruled out that certain chronic diseases may occasionally deteriorate during the use of combined oral contraceptives
- Known hyperlipidaemias
Women with hypertriglyceridemia, or a family history thereof, may be at an increased risk of pancreatitis when using COCs.
Women with hyperlipidaemias are at an increased risk of arterial disease (see section 4.4 'Circulatory disorders'). However routine screening of women on COCs is not appropriate.
- Blood pressure
Hypertension is a risk factor for stroke and myocardial infarction (see section 4.4 'Arterial thromboembolic-related conditions'). Although small increases in blood pressure have been reported in many women taking COCs, clinically relevant increases are rare. However, if sustained hypertension develops during the use of a COC, antihypertensive treatment should normally be instigated at a level of 160/100 mm Hg in uncomplicated patients or at 140/90 mm Hg in those with target organ damage, established cardiovascular disease, diabetes or with increased cardiovascular risk factors. Decisions about the continued use of the COC should be made at lower BP levels, and alternative contraception may be advised.
- Conditions which deteriorate in pregnancy or during previous COC use
The following conditions have been reported to occur or deteriorate with both pregnancy and COC use. Consideration should be given to stopping Akizza if any of the following occur during use:
- jaundice and/or pruritus related to cholestasis
- COCs may increase the risk of gallstone formation and may worsen existing disease
- systemic lupus erythematosus
- herpes gestationis
- otosclerosis-related hearing loss
- sickle cell anaemia
- renal dysfunction
- hereditary angioedema. Exogenous estrogens may induce or exacerbate symptoms of hereditary and acquired angioedema.
- any other condition an individual woman has experienced worsening of during pregnancy or previous use of COCs.
- Disturbances of liver function
Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal.
- Diabetes (without vascular involvement)
Insulin-dependent diabetics without vascular disease can use COCs. However it should be remembered that all diabetics are at an increased risk of arterial disease and this should be considered when prescribing COCs. Diabetics with existing vascular disease are contraindicated from using COCs (see section 4.3 Contraindications).
Although COCs may have an effect on peripheral insulin resistance and glucose tolerance, there is no evidence for a need to alter the therapeutic regimen in diabetics using low-dose COCs (containing < 0.05 mg ethinylestradiol).
However, diabetic women should be carefully observed while taking COCs.
- Psychiatric Disorders
Depressed mood and depression are well-known undesirable effects of hormonal contraceptive use (see section 4.8). Depression can be serious and is a well-known risk factor for suicidal behaviour and suicide. Women should be advised to contact their physician in case of mood changes and depressive symptoms, including shortly after initiating the treatment.
- Chloasma
Chloasma may occasionally occur, especially in women with a history of chloasma gravidarum. Women with a tendency to chloasma should avoid exposure to the sun or ultraviolet radiation whilst taking COCs.
- Menstrual Changes
Reduction of menstrual flow: This is not abnormal and it is to be expected in some patients. Indeed, it may be beneficial where heavy periods were previously experienced.
Missed menstruation: Occasionally, withdrawal bleeding may not occur at all. If the tablets have been taken correctly, pregnancy is very unlikely. If withdrawal bleeding fails to occur at the end of a second pack, the possibility of pregnancy must be ruled out before resuming with the next pack.
Intermenstrual bleeding: Irregular bleeding (spotting or breakthrough bleeding) may occur especially during the first months of use. Therefore, the evaluation of any irregular bleeding is only meaningful after an adaptation interval of about three cycles. If bleeding irregularities persist or occur after previously regular cycles, then non-hormonal causes should be considered and adequate diagnostic measures are indicated to exclude malignancy or pregnancy. This may include curettage.
Some women may experience amenorrhoea or oligomenorrhoea after discontinuation of oral contraceptives, especially when these conditions existed prior to use. Women should be informed of this possibility.
- Lactose Intolerance
This product contains lactose. Patients with rare hereditary problems of galactose intolerance, the total lactase deficiency, fructose intolerance or glucose-galactose malabsorption or sucrase-isomaltase should not take this medicine.
- ALT elevations
During clinical trials with patients treated for hepatitis C virus infections (HCV) with the medicinal products containing ombitasvir/paritaprevir/ritonavir and dasabuvir with or without ribavirin, transaminase (ALT) elevations higher than 5 times the upper limit of normal (ULN) occurred significantly more frequent in women using ethinylestradiol-containing medications such as combined hormonal contraceptives (CHCs). Additionally, also in patients treated with glecaprevir/pibrentasvir, ALT elevations were observed in women using ethinylestradiol-containing medications such as CHCs (see sections 4.3 and 4.5).
4.5 Interaction with other medicinal products and other forms of interaction
- Interactions
Hepatic enzyme inducers
Drugs which induce hepatic enzymes (especially cytochrome P450 3A4) increase the metabolism of contraceptive
steroids and hence may result in breakthrough bleeding and pregnancy. The following have been shown to have clinically important interactions with COCs:
Antiretroviral agents
- ritonavir;
- nelfinavir;
- nevirapine
Anticonvulsants
- barbiturates (including phenobarbitone);
- primidone;
- phenytoin;
- carbamazepine;
- oxcarbazepine;
- topiramate.
Antibiotics/antifungals
- griseofulvin;
- rifampacin.
Herbal remedies
- St John's wort ( Hypericum perforatum)
Note: There are other antiretroviral agents that may increase plasma concentration of sex hormones.
Substances decreasing the clearance of COCs (enzyme inhibitors)
Strong and moderate CYP3A4 inhibitors such as azole antifungals (e.g. itraconazole, voriconazole, fluconazole) and macrolides (e.g. erythromycin) can increase plasma concentrations of the estrogen or the progestin or both.
Etoricoxib doses of 60 to 120 mg/day have been shown to increase plasma concentrations of ethinylestradiol 1.4 to 1.6- fold, respectively when taken concomitantly with a combined hormonal contraceptive containing 0.035 mg ethinylestradiol.
Managing interactions with hepatic enzyme inducers
Interactions can occur with drugs that induce microsomal enzymes (especially cytochrome P450 3A4) which can result in increased clearance of sex hormones and which may lead to breakthrough bleeding and/or contraceptive failure.
Enzyme induction can already be observed after a few days of treatment. Maximal enzyme induction is generally seen within a few weeks. After the cessation of drug therapy enzyme induction may be sustained for about 4 weeks.
Women on short term treatment with any of these drugs should temporarily use a barrier method in addition to the COC or choose another method of contraception. The barrier method should be used during the time of concomitant drug administration and for 28 days after their discontinuation. If the period during which the barrier method is used runs beyond the end of a pack, the next pack should be started without a break. In this situation, a withdrawal bleed should not be expected until the end of the second pack. If the patient does not have a withdrawal bleed during the tablet-free interval following the end of the second pack, the possibility of pregnancy must be ruled out before resuming with the next pack.
For women receiving long-term therapy with hepatic enzyme inducers, another method of contraception should be used.
Substances increasing the clearance of COCs (diminished efficacy of COCs by enzyme-induction), e.g.:
Phenytoin, barbiturates, primidone, carbamazepine, rifampicin, and possibly also oxcarbazepine, topiramate, felbamate, griseofulvin and products containing St. John's wort.
Substances with variable effects on the clearance of COCs, e.g.:
When co-administered with COCs, many HIV/HCV protease inhibitors and non-nucleoside reverse transcriptase inhibitors can increase or decrease plasma concentrations of estrogen or progestin. These changes may be clinically relevant in some cases.
Effects on other drugs
Oral contraceptives may affect the metabolism of certain other drugs. Accordingly, plasma and tissue concentrations may either increase (e.g. cyclosporin, tizanidine, theophylline) or decrease (e.g. lamotrigine).
Note: The prescribing information of concomitant medications should be consulted to identify potential interactions.
Pharmacodynamic interactions
Concomitant use with the medicinal products containing ombitasvir/ paritaprevir/ ritonavir and dasabuvir, with or without ribavirin, or glecaprevir / pibrentasvir may increase the risk of ALT elevations (see sections 4.3 and 4.4).
Therefore, Akizza-users must switch to an alternative method of contraception (e.g., progestagen-only contraception or non-hormonal methods) prior to starting therapy with this combination drug regimen. Akizza can be restarted 2 weeks following completion of treatment with this combination drug regimen.
Other forms of interactions
- Laboratory tests
The use of oral contraceptives may influence the results of certain laboratory tests including biochemical parameters of liver, thyroid, adrenal and renal function, plasma levels of carrier proteins and lipid/lipoprotein fractions, parameters of carbohydrate metabolism and parameters of coagulation and fibrinolysis. Laboratory staff should therefore be informed about oral contraceptive use when laboratory tests are requested.
4.6 Fertility, pregnancy and lactation
Akizza is not indicated during pregnancy. If pregnancy occurs during treatment with Akizza, further intake must be stopped. However, extensive epidemiological studies have revealed neither an increased risk of birth defects in children born to women who used COCs prior to pregnancy, nor a teratogenic effect when COCs were taken inadvertently during early pregnancy.
The increased risk of VTE during the postpartum period should be considered when re-starting Akizza (see section 4.2 and 4.4).
The use of Akizza during lactation may lead to a reduction in the volume of milk produced and to a change in its composition. Minute amounts of the active substances are excreted with the milk. These amounts may affect the child particularly in the first 6 weeks post-partum. Mothers who are breast-feeding may be advised instead to use another method of contraception.
4.7 Effects on ability to drive and use machines
None known.
4.8 Undesirable effects
Summary of the safety profile
The most commonly reported adverse reactions with Akizza are nausea, abdominal pain, increased weight, headache, depressed mood, altered mood, breast pain, breast tenderness. They occur in ≥1% of users.
Serious adverse reactions are arterial and venous thromboembolism.
| System Organ | Adverse events reported in clinical trials | Adverse | |||
| Class | Commo | Uncommon | Rare | Unknown | events |
| reported post | |||||
| n | (≥ 1/1000, | (< 1/1000) | |||
| marketing | |||||
| (≥ 1/100) | <1/100) | ||||
| Eye disorders | contact lens | ||||
| intolerance | |||||
| Gastrointestinal | nausea, | vomiting, | |||
| disorders | abdomin | diarrhea | |||
| al pain | |||||
| Immune | hypersensitivit | Exogenous | |||
| system | y | estrogens | |||
| disorders | may induce | ||||
| or exacerbate | |||||
| symptoms of | |||||
| hereditary | |||||
| and acquired | |||||
| angioedema | |||||
| Investigations | weight | weight | |||
| increased | decreased | ||||
| Metabolism | fluid | Hypertriglycer | |||
| and nutrition | retention | idemia, | |||
| disorders | changes in | ||||
| glucose | |||||
| tolerance or | |||||
| effect on | |||||
| peripheral | |||||
| insulin | |||||
| resistance | |||||
| Nervous | headache | migraine | |||
| system | |||||
| disorders | |||||
| Vascular | Venous | ||||
| system | thromboembol | ||||
| ism (VTE), | |||||
| Arterial | |||||
| thromboembol | |||||
| ism (ATE) | |||||
| Hepatobiliary | liver function | ||||
| disorders | disturbances | ||||
| Psychiatric | depresse | libido | libido | ||
| disorders | d mood, | decreased | increased | ||
| mood | |||||
| altered | |||||
| Reproductive | breast | breast | vaginal | reduced | |
| system and | pain, | hypertrophy | discharge, | menstrual | |
| breast disorders | breast | breast | flow, spotting, | ||
| tendernes | discharge | breakthrough | |||
| s | bleeding and | ||||
| missed | |||||
| withdrawal | |||||
| bleeding, post | |||||
| pill | |||||
| amenorrhoea | |||||
| Skin and | rash, | erythema | chloasma | ||
| subcutaneous | urticaria | nodosum, |
| tissue disorders | erythema | ||||
| multiforme |
Description of selected adverse reactions
An increased risk of arterial and venous thrombotic and thrombo-embolic events, including myocardial infarction, stroke, transient ischemic attacks, venous thrombosis and pulmonary embolism has been observed in women using CHCs, which are discussed in more detail in section 4.4.
The following serious adverse events have been reported in women using COCs, which are discussed in section 4.4 'Special warnings and precautions for use':
- Venous thromboembolic disorders
- Arterial thromboembolic disorders
- Strokes (e.g. transient ischemic attack, ischemic stroke, haemorrhagic stroke)
- Hypertension
- Liver tumours (benign and malignant)
The frequency of diagnosis of breast cancer is very slightly increased among COC users. As breast cancer is rare in women under 40 years of age the excess number is small in relation to the overall risk of breast cancer. Causation with COC use is unknown. For further information, see sections 4.3 'Contraindications' and 4.4 'Special warnings and precautions for use'.
Conditions reported to deteriorate with pregnancy or previous COC use
- Jaundice and/or pruritus related to cholestasis; gallstone formation; systemic lupus erythematosus; exacerbation of chorea, herpes gestationis; otosclerosis-related hearing loss; Crohn's disease, ulcerative colitis, sickle cell anaemia; renal dysfunction; hereditary angioedema; porphyria; cervical cancer.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Overdosage may cause nausea, vomiting and, in females, withdrawal bleeding. Withdrawal bleeding may even occur in girls before their menarche, if they accidentally take the medicinal product.
There are no specific antidotes and treatment should be symptomatic.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Sex hormones and modulators of the genital
system, fixed combinations of oestrogen-progestogen.
ATC code: G03AA10
The contraceptive effect of Akizza is based on the interaction of various
factors, the most important of which are seen as the inhibition of ovulation and the changes in the cervical secretion. Furthermore, the endometrium is rendered unreceptive to implantation.
5.2 Pharmacokinetic properties
- Gestodene
Orally administered gestodene is rapidly and completely absorbed. Following single ingestion of Akizza, maximum drug serum levels of about 3.5ng/ml are reached at about 1.0 hour. Thereafter, gestodene serum levels decrease in two phases. The terminal disposition phase is characterized by a half-life of about 12hours. For gestodene, an apparent volume of distribution of 0.7 l/kg and a metabolic clearance rate from serum of about 0.8 ml/min/kg were determined.
Gestodene is not excreted in unchanged form but as metabolites, which are eliminated with a half-life of about 1 day. Gestodene metabolites are excreted at a urinary to biliary ratio of about 6:4. The biotransformation follows the known pathways of steroid metabolism. No pharmacologically active metabolites are known.
Gestodene is bound to serum albumin and to SHBG (sex hormone binding globulin). Only about 1.3% of the total serum drug levels are present as free steroid, about 69% are specifically bound to SHBG. The relative distribution (free, albumin-bound, SHBG-bound) depends on the SHBG concentrations in the serum. Following induction of the binding protein, the SHBG-bound fraction increases to ca. 80 % while the unbound and the albumin-bound fractions decrease.
Following daily repeated administration of Akizza, an accumulation of gestodene concentrations in the serum is observed. Mean serum levels are about fivefold higher at steady-state, which is generally reached during the second half of a treatment cycle. The pharmacokinetics of gestodene are influenced by SHBG serum levels. Under treatment with Akizza, a twofold increase in the serum SHBG levels has been observed for the first treatment cycle. Due to the specific binding of gestodene to SHBG, the increase in SHBG levels is accompanied by an almost parallel increase in gestodene serum levels. After three treatment cycles, the extent of SHBG induction per cycle does not seem to change further. The absolute bioavailability of gestodene was determined to be 99% of the dose administered.
- Ethinylestradiol
Orally administered ethinylestradiol is rapidly and completely absorbed. Following ingestion of Akizza, maximum drug serum levels of 65pg/ml are reached at 1.7 hours. Thereafter, ethinylestradiol serum levels decrease in disposition two phases characterized by half-lives of about 2 hours and about 21 hours, respectively. The terminal half-life of ethinylestradiol is subject to a large interindividual variation and a range of 5 to 30h has been reported in the literature. Due to analytical reasons, these parameters can only be calculated following the administration of higher doses. For ethinylestradiol, an apparent volume of distribution of about 5 l/kg and a metabolic clearance rate from serum of about 5ml/min/kg were determined. Ethinylestradiol is highly but non-specifically bound to albumin. About 2% of drug levels are present unbound. During absorption and first liver passage, ethinylestradiol is metabolized extensively, resulting in a mean oral bioavailability of about 45% with a large interindividual variation of about 20-65%. Unchanged drug is not excreted. Ethinylestradiol metabolites are excreted at a urinary to biliary ratio of 4:6 with a half-life of about 1 day.
According to the half-life of the terminal disposition phase from serum and the daily ingestion, steady-state serum levels of ethinylestradiol can be expected to be reached after 5 - 6 days. At the end of a treatment cycle, they were found to be higher by about 40 - 60% as compared to a single dose administration.
During established lactation, 0.02% of the daily maternal dose could be transferred to the newborn via milk.
The systemic availability of ethinylestradiol might be influenced in both directions by other drugs. There is, however, no interaction with high doses of vitamin C. Ethinylestradiol induces the hepatic synthesis of SHBG and CBG (corticoid binding globulin) during continuous use. The extent of SHBG induction, however, depends on the chemical structure and the dose of the co-administered progestogen. During treatment with Akizza, SHBG concentrations in the serum increased from 107nmol/l to 216nmol/l in the first and to 223nmol/l in the third cycle. Serum concentrations of CBG were increased from 42μg/ml to 77μg/ml in the first cycle and remained constant thereafter.
5.3 Preclinical safety data
The combination of ethinylestradiol and gestodene, like other contraceptive steroids, is associated with an increased incidence of neoplastic nodules in the rat liver, the relevance of which to man is unknown. Malignant liver tumours have been reported on rare occasions in long-term users of oral contraceptives.
There are no other preclinical safety data which could be of relevance to the prescriber and which are not already included in other relevant sections of the SPC.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Tablet core:
Lactose monohydrate
Maize Starch
Povidone 25
Magnesium stearate
Tablet film-coating:
Composition of Opadry white 03F58750
HPMC 2910/Hypromellose (E464)
Titanium dioxide (E171)
Macrogol 6000
Talc (E553b)
6.2 Incompatibilities
Not known.
6.3 Shelf life
36 months.
6.4 Special precautions for storage
This medicinal product does not require any special storage conditions. Store in the original package.
6.5 Nature and contents of container
Tablets are packed in PVC/PVDC/Aluminium blisters inside a sealed tri-laminated pouch.
Pack sizes: 1 x 21 tablets; 3 x 21 tablets, 6 x 21 tablets, 13 x 21 tablets.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Morningside Healthcare Ltd.
Unit C, Harcourt Way
Leicester
LE19 1WP
United Kingdom
8 MARKETING AUTHORISATION NUMBER(S)
PL 20117/0252
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
24/08/2015
10 DATE OF REVISION OF THE TEXT
27/10/2021