


Summary of Product Characteristics (SmPC) - Qinlock 50 mg tablets
1 NAME OF THE MEDICINAL PRODUCT
QINLOCK 50 mg tablets
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each tablet contains 50 mg of ripretinib.
Excipient with known effect
Each tablet contains 179 mg of lactose monohydrate.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Tablet.
White to off-white, approximately 9 × 17 mm, oval shaped tablet, debossed with ‘DC1' on one side.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
QINLOCK is indicated for the treatment of adult patients with advanced gastrointestinal stromal tumour (GIST) who have received prior treatment with three or more kinase inhibitors, including imatinib.
4.2 Posology and method of administration
QINLOCK should be prescribed by physicians experienced in the administration of anticancer agents.
Posology
The recommended dose is 150 mg ripretinib (three 50 mg tablets) taken once daily at the same time each day with or without food.
If the patient misses a dose of QINLOCK within 8 hours of the time it is usually taken, the patient should be instructed to take it as soon as possible and then take the next dose at the regularly scheduled time. If a patient misses a dose by more than 8 hours of the time it is usually taken, the patient should be instructed not to take the missed dose and simply resume the usual dosing schedule on the following day.
In case of vomiting after QINLOCK administration, the patient should not take a replacement dose and should resume the dosing schedule the next day at the usual time.
Treatment with QINLOCK should continue as long as benefit is observed or until unacceptable toxicity (see section 4.4).
Posology adjustments
Dose interruptions or dose reductions may be required based on individual safety and tolerability. The recommended dose reduction for adverse reactions is 100 mg orally, once daily.
QINLOCK should be permanently discontinued in patients who are unable to tolerate 100 mg orally once daily. The recommended dose modifications for QINLOCK for adverse reactions are provided in Table 1.
Table 1: Recommended dose modifications for adverse reactions
| Adverse reaction | Severitya | QINLOCK dose modifications |
| Palmar-Plantar Erythrodysaesthesia Syndrome (PPES) (see sections 4.4 and 4.8) | Grade 2 |
|
| Grade 3 |
|
| Adverse reaction | Severitya | QINLOCK dose modifications |
| Hypertension (see sections 4.4 and 4.8) | Grade 3 |
|
| Grade 4 | Permanently discontinue. | |
Left ventricular systolic dysfunction (see sections 4.4 and 4.8) | Grade 3 or 4 | Permanently discontinue. |
| Arthralgia or myalgia (see section 4.8) | Grade 2 |
|
| Grade 3 |
| |
| Other adverse reactions (see section 4.8) | Grade 3 or 4 |
|
a Graded per National Cancer Institute Common Terminology Criteria for Adverse Events version 4.03 (NCI CTCAE v4.03).
Concomitant medicinal products
Concomitant medicinal products that are strong or moderate inducers of CYP3A should be avoided (see sections 4.4 and 4.5). If a strong or moderate CYP3A inducer must be co-administered, the QINLOCK dosing frequency may be increased during the co-administration period. For strong inducers, the dose may be increased from 150 mg once daily to 150 mg twice daily. For patients taking QINLOCK twice daily, if the patient misses a dose within 4 hours of the time it is usually taken, the patient should be instructed to take the missed dose as soon as possible and then take the next dose at the regularly scheduled time. If a patient misses a dose by more than 4 hours of the time it is usually taken, the patient should be instructed not to take the missed dose and simply resume the usual dosing schedule. Close monitoring of overall efficacy and safety is recommended in these patients.
Special populations
Renal impairment
No dose adjustment is recommended in patients with mild and moderate renal impairment (see section 5.2). Only limited clinical data are available in patients with severe renal impairment [creatinine clearance (CLcr) <30 mL/min]. A recommended dose of QINLOCK has not been established in patients with severe renal impairment (see section 5.2).
Hepatic impairment
No dose adjustment is recommended in patients with mild hepatic impairment. A recommended dose of QINLOCK has not been established in patients with moderate or severe hepatic impairment. Close monitoring of overall safety is recommended in these patients (see section 5.2).
Elderly
In clinical studies, no clinically relevant differences were observed between elderly (aged >65 years) and younger patients (aged ≤ 65 and ≥ 18 years) (see section 5.1).
Paediatric population
The safety and efficacy of QINLOCK in children below 18 years of age have not been established (see section 5.1). No data are available.
Method of administration
QINLOCK is for oral use.
The tablets should be taken at the same time each day with or without food (see section 5.2).
Prescribers should instruct patients to swallow the tablets whole and not to chew, split, or crush them. Patients should not ingest the tablets if they are broken, cracked, or otherwise not intact as the potential effects of these alterations have not been evaluated.
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
4.4 Special warnings and precautions for use
Palmar-Plantar Erythrodysaesthesia Syndrome (PPES)
PPES occurred in patients treated with ripretinib (see section 4.8). Based on severity, ripretinib should be withheld and then resumed at the same or reduced dose (see section 4.2).
Hypertension
Hypertension was observed with ripretinib (see section 4.8). Ripretinib must not be initiated unless blood pressure is adequately controlled. Blood pressure is to be monitored as clinically indicated. Based on severity, ripretinib should be withheld and then resumed at same or reduced dose or permanently discontinue (see section 4.2).
Cardiac failure
Cardiac failure (including cardiac failure, cardiac failure acute, acute left ventricular failure, and diastolic dysfunction) was observed with ripretinib (see section 4.8). Ejection fraction should be assessed by echocardiogram or multiple-gated acquisition (MUGA) scan prior to initiating ripretinib and during treatment, as clinically indicated. Ripretinib should be permanently discontinued for Grade 3 or 4 left ventricular systolic dysfunction (see section 4.2). The safety of ripretinib has not been assessed in patients with a baseline left ventricular ejection fraction below 50%.
Cutaneous squamous cell carcinoma (CuSCC)
CuSCC was reported in patients receiving ripretinib (see section 4.8). Dermatological evaluations should be performed when initiating ripretinib and routinely during treatment. Suspicious skin lesions should be managed with excision and dermatopathological evaluation. Ripretinib should be continued at the same dose.
Wound healing complications
No formal studies to evaluate the effect of ripretinib on wound healing have been conducted. Impaired wound healing complications may occur in patients who receive medicinal products that inhibit the vascular endothelial growth factor (VEGF) signalling pathway. Therefore, ripretinib has the potential to adversely affect wound healing.
Treatment with ripretinib is to be withheld for at least 3 days prior to and after minor surgery and at least 5 days prior to and after major surgery. Ripretinib may then be resumed after surgery based on clinical judgement of adequate wound healing.
Embryo-foetal toxicity
Based on findings from animal studies, ripretinib can cause foetal harm when administered to pregnant women (see sections 4.6 and 5.3). It is recommended to advise women to avoid pregnancy while taking ripretinib. The pregnancy status of females of reproductive potential must be verified prior to initiating ripretinib and during treatment. Females of reproductive potential and males with female partners of reproductive potential must use effective contraception during treatment and for at least 1 week after the final dose of ripretinib (see sections 4.6 and 5.3). Effects of ripretinib on contraceptive steroids have not been studied. A barrier method contraception should be added if systemic contraceptive steroids are used.
Phototoxicity
Ripretinib exhibits a potential for phototoxicity (see section 5.3). It is recommended to advise patients to avoid or minimise exposure to direct sunlight, sunlamps, and other sources of ultraviolet radiation due to the risk of phototoxicity associated with ripretinib. Patients should be instructed to use measures such as protective clothing (long sleeves and hat) and sunscreen with high sun protection factor (SPF).
CYP3A inhibitors and inducers
Ripretinib is a CYP3A substrate. Concurrent administration of ripretinib with the strong CYP3A and P-glycoprotein (P-gp) inhibitor itraconazole resulted in an increase in ripretinib plasma exposure (see section 4.5). Caution is required when administering ripretinib with agents that are strong CYP3A and P-gp inhibitors.
Concurrent administration of ripretinib with the strong CYP3A inducer rifampicin resulted in a decrease in ripretinib plasma exposure. Therefore, chronic administration of agents that are strong or moderate CYP3A inducers with ripretinib should be avoided (see sections 4.2 and 4.5).
Important information about some excipients
QINLOCK contains lactose.
Patients with rare hereditary problems of galactose intolerance, total lactase deficiency or glucose-galactose malabsorption should not take this medicinal product.
4.5 Interaction with other medicinal products and other forms of interaction
Both ripretinib and its active metabolite DP-5439 are mainly cleared by CYP3A4/5 and are substrates of P-gp and Breast Cancer Resistance Protein (BCRP).
Effect of other medicinal products on ripretinib
Effect of strong CYP3A/P-gp inhibitors
Co-administration of itraconazole (a strong CYP3A inhibitor) and also a P-gp inhibitor increased ripretinib Cmax by 36% and AUC0-∞ by 99%. DP-5439 Cmax was unchanged; AUC0-∞ increased by 99%. Strong inhibitors of CYP3A/P-gp (e.g. ketoconazole, erythromycin, clarithromycin, itraconazole, ritonavir, posaconazole, and voriconazole) are to be used with caution and patients should be monitored. Ingestion of grapefruit juice is not recommended.
Effect of CYP3A inducers
Co-administration of QINLOCK with the strong CYP3A inducer rifampicin decreased ripretinib Cmax by 18% and AUC0-∞ by 61%, decreased DP-5439 AUC0-∞ by 57%, and increased DP-5439 Cmax by 37%.
Concomitant use of QINLOCK with strong CYP3A inducers (e.g. carbamazepine, phenytoin, rifampicin, phenobarbital and St. John’s wort) and moderate CYP3A inducers (e.g. efavirenz and etravirine) must therefore be avoided. If a strong or moderate CYP3A inducer must be co-administered, the QINLOCK dosing frequency may be increased during the co-administration period. For strong inducers, the dose may be increased from 150 mg once daily to 150 mg twice daily. For patients taking QINLOCK twice daily, if the patient misses a dose within 4 hours of the time it is usually taken, the patient should be instructed to take the missed dose as soon as possible and then take the next dose at the regularly scheduled time. If a patient misses a dose by more than 4 hours of the time it is usually taken, the patient should be instructed not to take the missed dose and simply resume the usual dosing schedule. Monitor for clinical response and tolerability.
Effect of acid-reducing agents
No clinically significant differences in the plasma exposure to ripretinib and DP-5439 were observed when QINLOCK was co-administered with pantoprazole (a proton pump inhibitor).
Drug transporter systems
Based on in vitro data, medicinal products that are inhibitors of BCRP (e.g. cyclosporine A, eltrombopag) should be used with caution in combination with QINLOCK, as increased plasma concentrations of ripretinib or DP-5439 may be possible.
Effect of ripretinib on other medicinal products
CYP isoform-selective substrates
In vitro studies suggested ripretinib may inhibit CYP2C8. QINLOCK is to be used with caution in combination with substrates of CYP2C8 (e.g. repaglinide, paclitaxel), as co-administration may lead to increased exposure of CYP2C8 substrates.
The in vivo net effect of inhibition of CYP3A4 in the intestine and systemic CYP3A4 induction is unknown. Caution is recommended when co-administering ripretinib with sensitive CYP3A4 substrates with a narrow therapeutic window (e.g. cyclosporine, tacrolimus) or that are mostly metabolised in the intestine (e.g. midazolam).
Ripretinib and DP-5439 induced CYP2B6 in vitro. Co-administration of ripretinib with CYP2B6 substrates with narrow therapeutic index (e.g. efavirenz) may lead to loss of their efficacy.
Ripretinib and DP-5439 down-regulated CYP1A2 in vitro. Co-administration of ripretinib with CYP1A2 substrates with narrow therapeutic index (e.g. tizanidine) may lead to increased concentrations and monitoring is recommended.
It is unknown whether ripretinib may reduce the effectiveness of systemically acting hormonal contraceptives, and therefore women using systemically acting hormonal contraceptives should add a barrier method.
Drug transporter systems
In vitro studies suggested ripretinib is an inhibitor of P-gp and BCRP. DP-5439 is a substrate for P-gp and BCRP. DP-5439 is an inhibitor of BCRP and Multidrug And Toxin Protein 1 (MATE-1).
Medicinal products that are P-gp substrates with narrow therapeutic indices (e.g. digoxin, dabigatran etexilate) should be used with caution in combination with QINLOCK due to the likelihood of increased plasma concentrations of these substrates.
QINLOCK is to be used with caution in combination with BCRP substrates (e.g. rosuvastatin, sulfasalazine and irinotecan) and MATE-1 substrates (e.g. metformin) as co-administration of QINLOCK with BCRP and MATE-1 substrates may lead to an increase of their exposure. Clinical studies with BCRP or MATE-1 substrates have not been conducted.
4.6 Fertility, pregnancy and lactation
Women of childbearing potential/Contraception in males and females
Women of childbearing potential and men with female partners of reproductive potential must be informed that QINLOCK may cause foetal harm and must ensure effective contraception during treatment and for at least 1 week after the final dose of QINLOCK (see section 4.4)
The pregnancy status of females of reproductive potential is to be verified prior to initiating QINLOCK and during treatment.
Effects of QINLOCK on contraceptive steroids have not been studied. Add a barrier method if systemic steroids are used for contraception.
Pregnancy
There are no data on the use of ripretinib in pregnant women.
Based on its mechanism of action, ripretinib is suspected to cause foetal harm when administered during pregnancy and animal studies have shown reproductive toxicity (see sections 4.4 and 5.3). QINLOCK should not be used during pregnancy unless the clinical condition of the woman requires treatment with ripretinib.
Breast-feeding
It is unknown whether ripretinib/metabolites are excreted in human milk. A risk to the breast-fed child cannot be excluded. Breast-feeding should be discontinued during treatment with QINLOCK and for at least 1 week after the final dose.
Fertility
There are no data on the effect of ripretinib on human fertility. Based on findings from animal studies, male and female fertility may be compromised by treatment with QINLOCK (see section 5.3).
4.7 Effects on ability to drive and use machines
QINLOCK has no influence on the ability to drive and use machines. In some patients, fatigue has been reported following administration of QINLOCK. If a patient experiences fatigue, this may influence their ability to drive or use machines.
4.8 Undesirable effects
Summary of the safety profile
In the Phase 3 double-blind, randomised (2:1), placebo-controlled study (INVICTUS), 129 participants with a diagnosis of advanced GIST who had failed at least 3 approved prior lines of treatment were randomised to QINLOCK (n=85) or placebo (n=44) (see section5.1). In the Phase 1 Study DCC-2618-01-001, a total of 277 patients with advanced malignancies were enrolled, and 218 patients were treated at the recommended Phase 2 dose of 150 mg QINLOCK once daily.
The median duration of treatment for QINLOCK in the double-blind period of the INVICTUS study was 5.49 months.
The most frequently observed adverse reactions (≥25%) in patients treated with QINLOCK in the pooled safety population (n=392) were fatigue (51.0%), alopecia (50.8%), nausea (39.8%), myalgia (37.8%), constipation (37.2%), diarrhoea (32.7%), PPES (29.8%), weight decreased (26.5%) and vomiting (25.8%).
The adverse reactions (≥10 to <25%) observed in patients treated with QINLOCK in the pooled safety population (n=392) were lipase increased (23.7%), muscle spasms (23.7%), arthralgia (21.2%), headache (20.7%), dyspnoea (20.2%), hypertension (19.4%), dry skin (17.6%), back pain (15.6%), cough (15.6%), blood bilirubin increased (14.0%), oedema peripheral (13.8%), hypophosphataemia (12.2%), pain in extremity (12.0%), pruritus (11.0%) and seborrhoeic keratosis (11.0%).
Grade 3/4 adverse reactions (≥2%) observed in patients treated with QINLOCK in the pooled safety population (n=392) were lipase increased (14.8%), anaemia (14.0%), abdominal pain (8.2%), hypertension (6.9%), fatigue (4.1%), hypophosphataemia (4.1%), vomiting (2.6%), dyspnoea (2.0%), diarrhoea (2.0%) and blood bilirubin increased (2.0%). Serious adverse reactions (≥1%) observed in patients treated with QINLOCK were anaemia (3.8%), dyspnoea (2.3%), vomiting (2.0%), nausea (1.8%), fatigue (1.5%), blood bilirubin increased (1.3%), constipation (1.0%), and muscular weakness (1.0%).
Tabulated list of adverse reactions
The overall safety profile of QINLOCK is based on pooled data from 392 patients (pooled safety population) who received at least 1 dose of QINLOCK. Two clinical studies with QINLOCK in adult patients with advanced malignancies were conducted and form the primary basis of the overall evaluation of safety: a pivotal phase 3 study in adult patients with GIST, Study DCC-2618-03-001 (INVICTUS) (see section 5.1) and an open-label, first-in-human study in adult patients with advanced malignancies (Study DCC-2618-01-001).
The double-blind period of the INVICTUS study formed the primary basis of the determination of adverse reactions. The treatment emergent adverse events that were at least 5% higher in QINLOCK arm as compared to the placebo arm and those that were at least 1.5 times greater in the QINLOCK arm than those compared to placebo arm in INVICTUS were considered adverse drug reactions. Treatment emergent adverse events identified within the INVICTUS study were also evaluated across the pooled safety population (n=392). These events were considered adverse drug reactions per the Sponsor assessment. They are classified according to System Organ Class and the most appropriate MedDRA term is used to describe a certain reaction and its synonyms and related conditions.
The severity of adverse drug reactions was assessed based on the Common Terminology Criteria for Adverse Events (CTCAE), defining Grade 1 = mild, Grade 2 = moderate, Grade 3 = severe, Grade 4=life threatening, and Grade 5=death.
Frequencies are defined as: very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1,000 to <1/100), rare (≥1/10,000 to <1/1,000), very rare (<1/10,000), not known (cannot be estimated from the available data) and are shown in Table 2. Within each frequency grouping, adverse reactions are presented in order of decreasing seriousness.
Table 2: Adverse drug reactions reported in INVICTUS and study DCC-2618-01-001
| Neoplasms benign, malignant and unspecified (including cysts and polyps) | |
| Very common | Seborrhoeic keratosis |
| Common | Melanocytic naevus, skin papilloma, squamous cell carcinoma of skina, fibrous histiocytoma |
| Endocrine disorders | |
| Common | Hypothyroidism |
| Metabolism and nutrition disorders | |
| Very common | Hypophosphataemia |
| Psychiatric disorders | |
| Common | Depression |
| Nervous system disorders | |
| Very common | Headache |
| Common | Peripheral sensory neuropathy |
| Cardiac disorders | |
| Common | Cardiac failureb, tachycardia |
| Vascular disorders | |
| Very common | Hypertensionc |
| Respiratory, thoracic and mediastinal disorders | |
| Very Common | Dyspnoea, cough |
| Gastrointestinal disorders | |
| Very common | Nausea, constipation, diarrhoea, vomiting |
| Common | Stomatitis, abdominal pain upper |
| Skin and subcutaneous tissue disorders | |
| Very common | Alopecia, PPES, dry skin, pruritus |
| Common | Hyperkeratosis, rash maculopapular, pruritus generalised, dermatitis acneiform |
| Musculoskeletal and connective tissue disorders | |
| Very common | Myalgia, muscle spasms, arthralgia, back pain, pain in extremity |
| Common | Muscular weakness, musculoskeletal chest pain |
| General disorders and administration site conditions | |
| Very common | Fatigue, oedema peripheral |
| Investigations | |
| Very common | Weight decreased, lipase increased, blood bilirubin increased |
| Common | Alanine aminotransferase increased |
aSquamous cell carcinoma of skin (Squamous cell carcinoma of skin, Keratoacanthoma, Squamous cell carcinoma of head and neck) bCardiac Failure (Cardiac failure, Acute left ventricular failure, Cardiac failure acute, Diastolic dysfunction)
cHypertension (Hypertension, Blood pressure increased)
Description of selected adverse drug reactions
Palmar-plantar erythrodysaesthesia syndrome (PPES)
In the double-blind period of the INVICTUS study, PPES was reported in 19 of 85 (22.4%) patients in the QINLOCK arm and no patients in the placebo arm. PPES led to dose discontinuation in 1.2% of patients, dose interruption in 3.5% of patients, and dose reduction in 2.4% of patients. All events were mild or moderate in severity (58% Grade 1 and 42% Grade 2).
In the pooled safety population, PPES occurred in 29.8% of 392 patients, including Grade 3 adverse reactions in 0.5%. The median time to onset and duration of the first event was 8.1 weeks (range: 0.3 week to 112.1 weeks) and 24.3 weeks (range: 0.9 week to 191.7 weeks), respectively. See sections 4.2 and 4.4 for additional information.
Hypertension
In the double-blind period of the INVICTUS study, there was a higher incidence of hypertension (all events regardless of causality) in patients treated with QINLOCK (15.3%) vs. 4.7% of patients who received placebo.
In the pooled safety population, hypertension occurred in 19.4% of 392 patients, including Grade 3 adverse reactions in 6.9%. See sections 4.2 and 4.4 for additional information.
Cardiac failure
In the double-blind period of the INVICTUS study, cardiac failure (all events regardless of causality) occurred in 1.2% of the 85 patients who received QINLOCK. Cardiac failure led to dose discontinuation in 1.2% of the 85 patients who received QINLOCK.
In the pooled safety population, cardiac failure occurred in 1.5% of 392 patients, including Grade 3 adverse reactions in 1.0%.
In the pooled safety population, 299 of 392 patients had a baseline and at least one post-baseline echocardiogram. Grade 3 decreased left ventricular ejection fraction occurred in 4.0% of the 299 patients.
See section 4.4 for additional information.
Cutaneous malignancies
In the double-blind period of the INVICTUS study, CuSCC (all events regardless of causality) was reported in 5.9% of the 85 patients receiving QINLOCK. CuSCC of the skin was not reported in placebo-treated patients. See sections 4.2 and 4.4 for additional information.
In the pooled safety population, CuSCC occurred in 8.7% of 392 patients including Grade 3 adverse reactions in 0.5%. Melanoma (all events regardless of causality) occurred in 0.3% of 392 patients.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
There is no known specific antidote for overdose with QINLOCK.
In the event of suspected overdose, QINLOCK must be discontinued immediately, best supportive care should be initiated by a medical professional, and the patient must be observed until clinical stabilisation.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Antineoplastic agents, other protein kinase inhibitors; ATC Code: L01EX19
Mechanism of action
Ripretinib is a novel tyrosine kinase inhibitor that inhibits KIT proto-oncogene receptor tyrosine kinase and PDGFRA kinase, including wild type, primary, and secondary mutations. Ripretinib also inhibits other kinases in vitro, such as PDGFRB, TIE2, VEGFR2, and BRAF.
Clinical efficacy and safety
INVICTUS (DCC-2618-03-001 study)
The efficacy and safety of QINLOCK were evaluated in a randomised (2:1), double-blind, placebo-controlled study (INVICTUS study) in patients with unresectable, locally advanced or metastatic GIST who had been previously treated with or are intolerant to at least 3 prior anticancer therapies including treatment with imatinib, sunitinib, and regorafenib. Randomisation was stratified by prior lines of therapy (3 versus ≥4) and Eastern Cooperative Oncology Group (ECOG) performance status (0 versus 1 or 2).
The primary efficacy outcome measure was progression-free survival (PFS) based on disease assessment by blinded independent central review (BICR) using modified RECIST 1.1 criteria, in which lymph nodes and bone lesions were not target lesions and a progressively growing new tumour nodule within a pre-existing tumour mass must meet specific criteria to be considered unequivocal evidence of progression. Secondary efficacy endpoints included objective response rate (ORR) by BICR, overall survival (OS), and patient-reported health state, physical function (PF), and role function (RF).
Participants were randomised to receive 150 mg QINLOCK (n=85) or placebo (n=44) orally once daily administered in continuous 28-day cycles. Treatment continued until disease progression or unacceptable toxicity. Individual treatment arms were unblinded at the time of disease progression as assessed by BICR review and all patients on placebo arm were offered to cross-over to QINLOCK.
The demographic characteristics were median age of 60 years (29 to 83 years) with 79 (61.2%) of patients aged 18-64 years, 32 (24.8%) of patients aged 65-74 years, and 18 (13.9%) patients aged ≥ 75 years (no patients ≥ 85 years old were randomised); male (56.6%); white (75.2%); and ECOG performance status of 0 (41.9%), 1 (49.6%), or 2 (8.5%). Sixty-three percent (63%) of patients received 3 prior therapies and approximately 37% received 4 or more prior therapies. Sixty-six percent (66%) of patients randomised to placebo crossed over to QINLOCK during the open-label period.
At the primary analysis (data cut-off date 31 May 2019) QINLOCK was compared to placebo in the INVICTUS study. QINLOCK demonstrated benefit in all assessed patient subgroups for PFS. Median PFS as determined by BICR (months) (95% CI) was 6.3 (4.6, 6.9) for QINLOCK versus 1.0 (0.9, 1.7) for placebo, HR (95% CI) 0.15 (0.09, 0.25) p-value < 0.0001. The secondary endpoint ORR (%) was 9.4 (4.2, 18) for QINLOCK versus 0 (0, 8) for placebo, p-value 0.0504 and not statistically significant. Median OS (months) (95% CI) was 15.1 (12.3, 15.1) for QINLOCK versus 6.6 (4.1, 11.6) for placebo, nominal p-value 0.0004. OS was not evaluated for statistical significance as a result of the sequential testing procedure for the secondary endpoints of ORR and OS.
PFS, ORR and OS results from a more recent data cut-off (10 August 2020) are shown in Table 3 and Figures 1 and 2. PFS results were similar across subgroups based on age, sex, region, ECOG status and number of previous lines of therapy.
Table 3: INVICTUS efficacy results (as of 10 August 2020)
QINLOCK (n = 85) | Placebo (n = 44) | |
| PFSa | ||
| Number of events (%) | 68 (80) | 37 (84) |
| Progressive disease | 62 (73) | 32 (73) |
| Deaths | 6 (7) | 5 (11) |
| Median PFS (months) (95% CI) | 6.3 (4.6, 8.1) | 1.0 (0.9, 1.7) |
| HR (95% CI)b | 0.16 (0.10, 0.27) | |
| ORRa | ||
| ORR (%) | 11.8 | 0 |
| (95% CI) | (5.8, 20.6) | (0, 8) |
| OS | ||
| Number of deaths (%) | 44 (52) | 35 (80) |
| Median OS (months) (95% CI) | 18.2 (13.1, NE) | 6.3 (4.1, 10.0) |
| HR (95% CI)b | 0.42 (0.27, 0.67) | |
BICR = Blinded Independent Central Review; CI = Confidence Interval; HR = Hazard Ratio; ORR = Objective Response Rate; NE = not estimable; PFS = Progression Free Survival; OS = Overall Survival a Assessed per BICR. b Hazard ratio is based on Cox proportional regression model. This model includes treatment and randomisation stratification factors as fixed factors. | ||
Figure 1: INVICTUS Kaplan-Meier curve of progression-free survivala
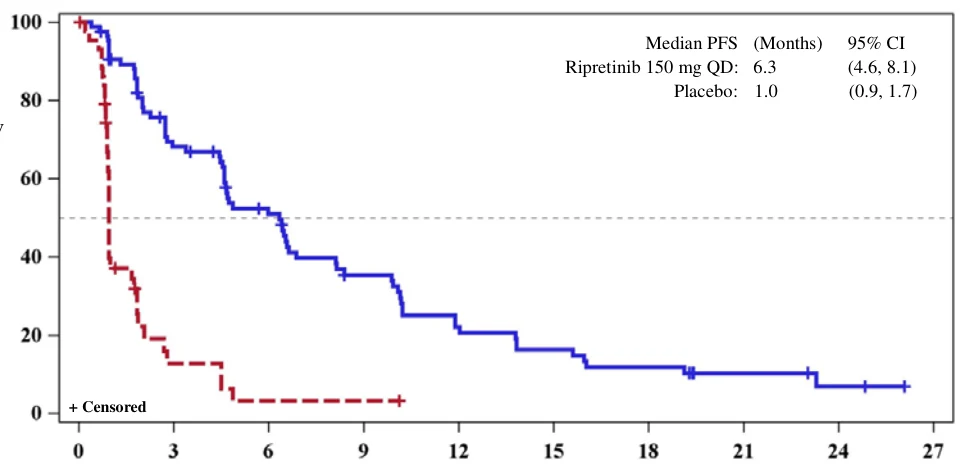
a Data cut off 10 August 2020
Figure 2: INVICTUS Kaplan-Meier curve of overall survivala 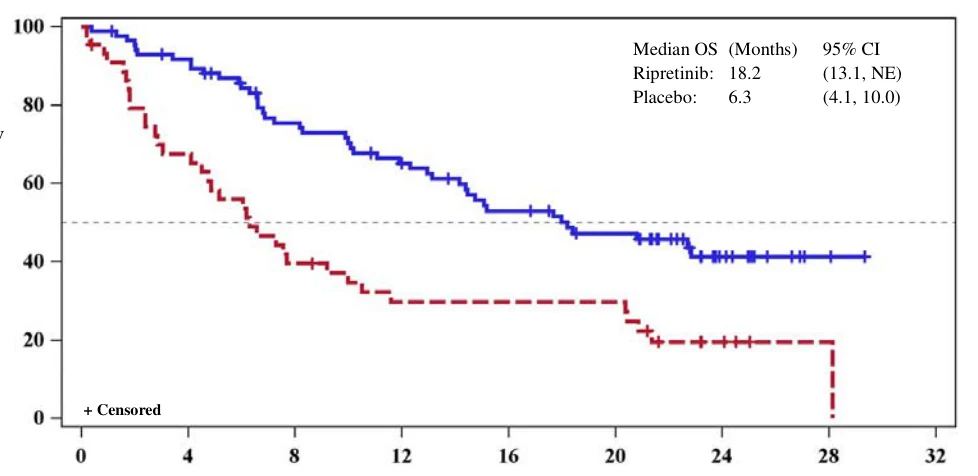
a Data cut off 10 August 2020
Paediatric population
The European Medicines Agency has waived the obligation to submit the results of studies with QINLOCK in all subsets of the paediatric population in the treatment of GIST (see section 4.2 for information on paediatric use).
Survival Probability (%)
Progression Free Survival (Months)
Ripretinib 150 mg QD
+ Censored
Placebo
Number of Patients at Risk
Ripretinib 150 mg QD 85 54 37 24 15 11 8 4 2 0
Placebo 44 4 1 1 0
Median PFS (Months) 95% CI Ripretinib 150 mg QD: 6.3 (4.6, 8.1)
Placebo: 1.0 (0.9, 1.7)
Survival Probability (%)
Overall Survival (Months)
Ripretinib
+ Censored
Placebo
Patients at Risk:
Ripretinib 85 76 59 49 39 32 12 2 0 Placebo 44 29 17 12 12 12 4 1 0
Median OS (Months) 95% CI Ripretinib: 18.2 (13.1, NE) Placebo: 6.3 (4.1, 10.0)
5.2 Pharmacokinetic properties
Absorption
Ripretinib reaches peak plasma concentrations at a median of 4 hours after oral administration of single dose ripretinib 150 mg (given as three tablets each containing 50 mg). The mean (CV%) AUC0-∞ after a single dose of 150 mg of ripretinib was 9,856 (39%) and 8,146 (56%) ng•h/mL for ripretinib and DP-5439, respectively.
Administration with a high-fat meal increased ripretinib AUC0-24 and Cmax by 30% and 22%, respectively. DP-5439 AUC0-24 and Cmax were higher by 47% and 66%, respectively.
Distribution
Both ripretinib and its active metabolite DP-5439 bind to plasma proteins at ≥ 99%. The mean (CV%) apparent volume of distribution (Vss/F) is approximately 302 (35%) L for ripretinib and 491 (38%) L for DP-5439.
Biotransformation
CYP3A4/5 is the major metaboliser of ripretinib and its active metabolite DP-5439, while CYP2C8 and CYP2D6 are minor metabolisers.
Elimination
Following oral administration of single dose ripretinib 150 mg in humans, mean (CV%) apparent oral clearance (CL/F) was 15.2 (39%) and 17.9 (56%) L/hr for ripretinib and DP-5439, respectively. Mean (CV%) half-life (t½) was 12.6 (17%) and 15.6 (23%) hours for ripretinib and DP-5439, respectively.
Systemic elimination of ripretinib was not primarily attributed to the kidney with 0.02% and 0.1% of the ripretinib dose excreted as ripretinib and DP-5439, respectively, in urine and 34% and 6% of the ripretinib dose excreted as ripretinib and DP-5439, respectively, in faeces.
Dose proportionality
Across the dose range of 20-250 mg, ripretinib and DP-5439 PK appeared to be less than dose proportional, especially at ripretinib doses higher than 150 mg.
Time dependency
Steady-state conditions are achieved within 14 days.
Specific populations
No clinically significant differences in the pharmacokinetics of QINLOCK were observed based on age (19 to 87 years), sex, race (White, Black, and Asian), body weight (39 to 138 kg), and tumour (GIST or other solid tumours).
Patients with renal impairment
In clinical studies, no relevant differences in exposure were observed between patients with mild and moderate renal impairment (CLcr 30 to 89 mL/min estimated by Cockcroft-Gault) and patients with normal renal function. Based on a population pharmacokinetic analysis, no dose adjustment is recommended in patients with mild and moderate renal impairment. The pharmacokinetics and safety of QINLOCK in patients with severe renal impairment (CLcr 15 to 29 mL/min estimated by Cockcroft-Gault) is limited. No dosing recommendation can be made in patients with severe renal impairment (see section 4.2).
Patients with hepatic impairment
In clinical studies, no relevant differences in exposure were observed between patients with mild (total bilirubin ≤ upper limit of normal (ULN) and AST > ULN, or total bilirubin > ULN to ≤1.5 × ULN and any AST) hepatic impairment and normal hepatic function. Based on a population pharmacokinetic analysis, no dose adjustment is recommended in patients with mild hepatic impairment. The pharmacokinetics and safety of QINLOCK in patients with moderate or severe hepatic impairment have not been studied; no dosing recommendation can be made in this subgroup (see section 4.2).
5.3 Preclinical safety data
The preclinical safety profile of ripretinib was assessed in rats and dogs for up to 13 weeks duration. Inflammation responses correlated with skin changes (discoloured, lesions) were recorded in rats (approximately 1.12 times the human exposure at 150 mg once daily). Elevated hepatic enzyme activity was reported in both species (approximately 1.12 and 1.3 times the human exposure at 150 mg once daily for rats and dogs, respectively). Dogs presented gastrointestinal effects (emesis and/or abnormal faeces) (approximately 1.3 times the human exposure at 150 mg once daily), and inflammatory responses illustrated by adverse skin lesions (approximately 0.14 times the human exposure at 150 mg once daily).
Carcinogenicity
Carcinogenicity studies have not been conducted with ripretinib.
Genotoxicity
Ripretinib was found to be positive in an in vitro micronucleus assay. Ripretinib was not mutagenic in in vitro bacterial reverse mutation (Ames) assay nor in an in vivo rat bone marrow micronucleus assay, demonstrating the absence of significant genotoxic risk.
Reproductive and developmental toxicity
Dedicated fertility studies in male and female animals were not conducted with ripretinib. However, in a 13-week repeat-dose toxicity study in male rats, there were findings of degeneration in the seminiferous epithelium of the testes, and cellular debris of the epididymis in males administered 30 or 300 mg/kg/day but were considered of sufficient severity to affect reproduction at dose 300 mg/kg/day only (approximately 1.4 times the human exposure at 150 mg once daily).
In a pivotal embryofoetal development study, ripretinib was teratogenic in rats, inducing dose-related malformations primarily associated with the visceral and skeletal systems at a maternal dose of 20 mg/kg/day (approximately 1.0 times the human exposure at 150 mg once daily). Additionally, skeletal variations were already observed at 5 mg/kg/day. The developmental NOAEL for ripretinib was therefore established at 1 mg/kg/day (approximately 0.02 times the human exposure at 150 mg once daily).
A study investigating effects of ripretinib on the pre-/postnatal development was not performed.
Phototoxicity
Ripretinib indicates a potential for photoirritation/phototoxicity based on absorption in the UV visible range (above 290 nm). In vitro phototoxicity assessment in 3T3 mouse fibroblast cells suggest that ripretinib exhibits a potential for phototoxicity at clinically relevant concentrations following exposure to UVA and UVB radiation.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Crospovidone (E1202)
Hypromellose acetate succinate
Lactose monohydrate
Magnesium stearate (E470b)
Microcrystalline cellulose (E460)
Silica, colloidal hydrated (E551)
6.2 Incompatibilities
Not applicable.
6.3 Shelf life
3 years.
6.4 Special precautions for storage
This medicinal product does not require any special temperature storage conditions.
Store in the original package and keep bottle tightly closed in order to protect from light and moisture.
6.5 Nature and contents of container
White high-density polyethylene (HDPE) bottle with an aluminium foil/polyethylene (PE) tamper evident seal and a white polypropylene (PP) child-resistant closure, together with one PE desiccant canister containing silica gel. Each bottle contains 30 or 90 tablets.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Deciphera Pharmaceuticals (Netherlands) B.V.
Atrium Building Floor 4th
Strawinskylaan 3051
1077ZX, Amsterdam
Netherlands
8 MARKETING AUTHORISATION NUMBER(S)
PLGB 55295/0004
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
20/12/2021
10 DATE OF REVISION OF THE TEXT
20/12/2021