

Summary of Product Characteristics (SmPC) - Amikacin 250 mg / ml solution for injection/infusion
1 NAME OF THE MEDICINAL PRODUCT
Amikacin 250mg/ml Solution for Injection/Infusion
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
1ml of solution for injection contains 250mg of amikacin (as sulfate). 1 ampoule of 2ml of solution for injection contains 500mg of amikacin (as sulfate).
Excipients with known effect:
Sodium 6.5 mg / 0.14 mmol per ml
Sodium metabisulfite (E 223) 2.475 mg per ml
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Solution for injection.
Colourless to yellowish liquid, practically free of particles
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Amikacin is indicated in the treatment of following infections in adults and pediatric patients including neonates (see section 5.1)
Hospital-acquired pneumonia (HAP) including ventilator-associated pneumonia
(VAP) - Complicated Urogenital tract infections including pyelonephritis
Complicated Intraabdominal infections
- Endocarditis (only in combination with other antibiotics)
- Infected burns
Treatment of patients with bacteraemia that occurs in association with, or is suspected to be associated with, any of the infections listed above.
Amikacin may be used in the management of neutropenic patients with fever that is suspected to be due to a bacterial infection.
Consideration should be given to official guidance on the appropriate use of antibacterial agents.
4.2 Posology and method of administration
Posology
Adults and children over 12 years
The recommended intramuscular or intravenous dosage for adults and adolescents with normal renal function (creatinine clearance ≥50 mg/min) is 15 mg/kg/day which may be administered as a single daily dose or several equal doses (e.g. 7.5 mg/kg every 12 hours, or 5mg/kg every 8 hours).
The total daily dose should not exceed 1.5 g. For endocarditis and in febrile neutropenic patients dosing should be twice daily, as there is not enough data to support once daily dosing.
Children 4 weeks to 12 years
The recommended intramuscular or intravenous (slow intravenous infusion) dose in children with normal renal function is 15-20 mg/kg/day, given either as a single daily dose of 15-20 mg/kg, or divided into two doses of 7.5 mg/kg every 12 hours.
In endocarditis and in febrile neutropenic patients, dosing should be twice daily, as there is not enough data to support once daily dosing.
Neonates
An initial loading dose of 10 mg/kg followed by 7.5 mg/kg every 12 hours (see sections 4.4 and 5.2).
Premature infants
The recommended dose in premature infants is 7.5 mg/kg every 12 hours (see sections 4.4 and 5.2).
Dosage in elderly patients (≥65 years):
Renal function should be taken into account in elderly patients (see section 5.2).
Life-threatening infections and/or those caused by Pseudomonas
The adult dose may be increased to 500 mg every eight hours but should neither exceed 1.5 g/day nor be administered for a period longer than 10 days. A maximum total adult dose of 15 g should not be exceeded.
Urinary tract infections (other than pseudomonal infections):
7.5 mg/kg/day in two equally divided doses (equivalent to 250 mg twice daily in adults). As the activity of amikacin is enhanced by increasing the pH, a urinary alkalising agent may be administered concurrently.
Other routes of administration
Amikacin in concentrations of 0.25% (2.5 mg/mL) may be used satisfactorily as an irrigating solution in abscess cavities, the pleural space, the peritoneum and the cerebral ventricles.
Intraperitoneal use
Following exploration for established peritonitis, or after peritoneal contamination due to faecal spill during surgery, amikacin may be used as an irrigant after recovery from anaesthesia in concentrations of 0.25% (2.5 mg/mL). If instillation is desired in adults, a single dose of 500 mg is diluted in 20 mL of sterile distilled water and may be instilled through a polyethylene catheter sutured into the wound at closure. If possible, instillation should be postponed until the patient has fully recovered from the effects of anaesthesia and muscle-relaxing drugs.
Monitoring
The renal function status should be evaluated by measuring the serum creatinine concentration or preferably by estimation of creatinine clearance. Blood urea nitrogen (BUN) is far less reliable for this purpose. Assessment of renal function should be performed at the start of therapy and should be re-evaluated at regular intervals during treatment.
Amikacin concentrations in serum should be measured in all patients receiving parenteral amikacin and must be measured in obesity, if high doses are being given, the elderly and in cystic fibrosis. Both peak and trough serum concentrations should be measured intermittently during therapy to ensure adequate but not excessive serum levels. In patients receiving multiple daily dosing peak concentrations (30-90 minutes after injection) of above 35μg/ml and trough concentrations (just before the next dose) of above 10μg/ml should be avoided.
In patients receiving once daily (or extended interval) dosing pre-dose (‘trough’) concentration should be less than 5 mcg/ml. Peak concentrations (approximately 60 minutes after administration) may exceed 35 mcg/ml.
If the pre-dose (‘trough’) concentration is high, the interval between doses must be increased. If the post-dose (‘peak’) concentration is high, the dose must be decreased.
Auditory and vestibular function should also be monitored during treatment, in particular if longer treatment duration (>7-10 days) is considered.
Dosage in renal impairment
In patients with impaired renal function (creatinine clearance less than 50 mL/min) the recommended dose has to be decreased and adjusted to the renal function. This can be achieved by increasing the dose interval and/or reducing the dose.
In all patients with renal impairment, serum amikacin peak and trough concentration and renal function must be monitored regularly and the dose regimen altered as necessary (see below).
Once daily/extended interval dosing
Patients with renal impairment in whom once daily dosing would be considered appropriate if their renal function were normal may receive extended interval dosing. The initial dose may be the same as in normal renal function. The dose interval should be at least 24 hours and extended according to the degree of renal impairment and the results of serum amikacin level measurements (see Monitoring Advice).
In severe renal impairment, the initial dose may have to reduced in addition.
Once daily or extended interval dosing should be avoided in patients with a creatinine clearance less than 20 ml/minute.
A once daily/extended interval dose regimen should be avoided in children over 1 month of age with a creatinine clearance less than 20 ml/minute/1.73 m2.
Reduced Dose at Fixed Intervals:
If patients with renal impairment are given amikacin at fixed time intervals, the dose must be reduced. In these patients, the serum amikacin concentration should be measured to ensure accurate administration and to avoid excessive serum concentrations. If a determination of serum concentration is not possible and the patient's condition is stable, serum creatinine and creatinine clearance rates are the most readily available indicators of the extent of renal dysfunction and the consequent reduction in dose.
As renal function may alter appreciably during therapy, the serum creatinine should be checked frequently and the dosage regimen modified as necessary.
Multiple daily dosing
In patients with renal impairment in whom multiple daily dosing at fixed intervals would be considered appropriate if their renal function were normal, the dose must be reduced while the dose interval is maintained. Serum amikacin concentrations should be measured and creatinine clearance should be estimated regularly (see Monitoring Advice).
Treatment should be initiated by administering a normal dose, 7.5 mg/kg, as a loading dose. This dose is the same as the normally recommended dose which would be calculated for a patient with a normal renal function as described above.
To initially determine the size of maintenance doses administered every 12 hours, the loading dose should be reduced in proportion to the reduction in the patient’s creatinine clearance rate:
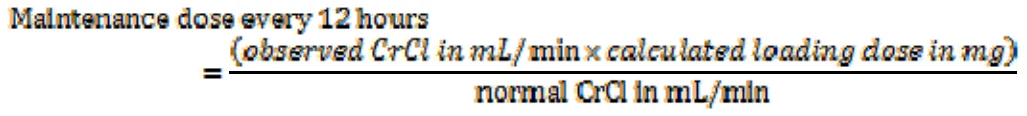
(CrCl = creatinine clearance rate)
Subsequent doses should be determined based on amikacin serum concentrations (see Monitoring Advice).
Treatment duration
At recommended dosages, infections caused by susceptible pathogens should respond to therapy within 24-48 hours. If clinical response does not occur within 3-5 days, therapy should be discontinued and the antibiotic susceptibility pattern of the invading organism should be rechecked. If necessary, alternative therapy should be considered. Failure of therapy may be due to the resistance of the organism or to septic locus requiring surgical drainage.
The average duration of treatment is 7-10 days. For all routes of administration, the maximum daily dose should not exceed 15-20mg/kg/day. If prolonged treatment is required, it should be carried out after reviewing the necessity of using amikacin, determination of serum amikacin concentrations and additionally monitoring of renal, auditory and vestibular functions as closely as possible daily.
Method of administration
IM use or IV use after dilution.
In paediatric patients the amount of diluents used will depend on the amount of amikacin tolerated by the patient. The solution should normally be infused over a 30 to 60-minute period. Infants should receive a 1 to 2-hour infusion.
Amikacin should not be physically premixed with other drugs, but should be administered separately according to the recommended dose and route.
For the dilution of Amikacin see section 6.6
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
Due to the known cross sensitivities in this class of drugs, a history of hypersensitivity or serious toxic reactions to aminoglycosides may be a contraindication to all aminoglycosides.
Because of its sulphite content, Amikacin must not be used in asthmatics with sulphite hypersensitivity.
4.4 Special warnings and precautions for use
Allergic reactions
Amikacin contains sodium metabisulfite
Sodium metabisulfite may rarely cause severe hypersensitivity reactions in susceptible individuals, including anaphylactic symptoms and life- threatening bronchial spasms (bronchospasm).
Sulphite hypersensitivity is generally uncommon and more common in asthmatics than non-asthmatics.
Neuro/Ototoxicity
Neurotoxicity manifesting as vestibular and/or bilateral auditory ototoxicity may occur in patients treated with aminoglycosides. The risk of aminoglycoside-induced ototoxicity is greater in patients with impaired renal function or in those where the duration of treatment is extended beyond 5-7 days, even in healthy patients. Often, deafness at high frequencies appears first and can only be detected by audiometric testing. Dizziness may occur and may be evidence of vestibular damage. Other signs of neurotoxicity may include numbness, skin tingling, muscle twitching, and convulsions. Patients who develop cochlear or vestibular damage do not need to have symptoms during treatment that alert them of eighth cranial nerve damage. Total or partially irreversible bilateral deafness or disabling vertigo may occur after discontinuation of the drug.
Aminoglycoside Induced ototoxicity is usually irreversible.
There is an increased risk of ototoxicity in patients with mitochondrial DNA mutations (particularly the nucleotide 1555 A to G substitution in the 12S rRNA gene), even if aminoglycoside serum levels are within the recommended range during treatment. Alternative treatment options should be considered in such patients.
In patients with a family history of relevant mutations or aminoglycoside induced deafness, alternative treatments or genetic testing prior to administration, should be considered.
Neuromuscular toxicity
Neuromuscular blockade and respiratory paralysis have been reported following parenteral injection, topical installation (as in orthopaedic flushing and abdominal lavage, or with local empyema treatment) and after oral administration of aminoglycosides. The risk of respiratory paralysis when administering aminoglycosides irrespective of the route of administration should be considered, especially in patients receiving anesthetics or neuromuscular blockers (see section 4.5 Interactions with other medications and other forms of interaction "). If neuromuscular blockade occurs, calcium salts may relieve respiratory paralysis but mechanical ventilation may be necessary.
In animal studies, neuromuscular blockade and muscular paralysis have been reported after administration of high doses of amikacin.
Aminoglycosides should be used with caution in patients with muscular disorders such as
myasthenia gravis or parkinsonism as these drugs may aggravate muscle weakness due to
their potential curare-like effect on the neuromuscular junction.
Renal toxicity:
Aminoglycosides are potentially nephrotoxic. Renal toxicity appears independent of plasma obtained at the peak (Cmax). The risk of nephrotoxicity is increased in patients with impaired renal function and in patients receiving high doses or prolonged drug therapy.
Patients should be well hydrated during treatment and renal function should be assessed by the usual methods prior to starting therapy and daily during the course of treatment. A reduction of dosage is required if evidence of renal dysfunction occurs, such as presence of urinary casts, white or red cells, albuminuria, decreased creatinine clearance, decreased urine specific gravity, increased BUN, serum creatinine, or oliguria. If azotemia increases, or if a progressive decrease in urinary output occurs, treatment should be stopped.
Elderly patients may have reduced renal function which may not be seen in the routine screening tests such as BUN (blood urea nitrogen) or serum creatinine, A crearinine clearance determination may be more helpful. Monitoring of renal function in elderly patients during treatment with aminoglycosides is particularly important.
Renal function and function of the eighth cranial nerve should be closely monitored, especially in patients with know or suspected renal impairment at the onset of treatment and also in those whose renal function us initially normal but who develop signs of renal impairment during treatment.
Serum concentrations of amikacin should be monitored (when possible) to ensure adequate levels and to avoid potential toxic levels. The urine should be examined for decreased density, increased excretion of proteins and the presence of cells or casts. BUN (blood urea nitrogen), serum creatinine, or creatinine clearance should be measured periodically. Repeat audiograms should be performed (if possible), especially in high-risk patients. Evidence of ototoxicity (dizziness, tinnitus, ringing in the ears and hearing loss) or nephrotoxicity require discontinuation of the drug or dose adjustment.
Aminoglycosides may be inactivated by betalactams. Inactivation may continue in samples (serum, cerebrospinal fluid, etc.) taken for laboratory testing and then interfere with aminoglycoside level assays. The samples should therefore be adequately treated after collection (immediate determination, storage in the freezer or addition of beta-lactamase).
Diarrhoea/pseudomembranous colitis caused by Clostridium difficile occurs. Patients with diarrhoea must therefore be monitored closely.
Concurrent and/or sequential systemic, oral, or topical use of other neurotoxic or nephrotoxic products, particularly bacitracin, cisplatin, amphotericin B, cephaloridine, paromomycin, viomycin, polymyxin B, colistin, vancomycin, or other aminoglycosides, should be avoided. Other factors that may increase risk of toxicity are advanced age and dehydration.
Other
Aminoglycosides are quickly and almost totally absorbed when they are applied topically, except to the urinary bladder, in association with surgical procedures. Irreversible deafness, renal failure and death due to neuromuscular blockade have been reported following irrigation of both small and large surgical fields with an aminoglycoside preparation.
Prolonged antibiotic use may occasionally lead to overgrowth of resistant pathogens. The patient should be constantly monitored in this regard. Should a superinfection occur during therapy, appropriate measures must be taken.
Macular infarction sometimes leading to permanent loss of vision has been reported following intravitreous administration (injection into the eye) of amikacin.
Paediatric use
Aminoglycosides should be used with caution in premature and neonatal infants because of the renal immaturity of these patients and the resulting prolongation of serum half-life of these drugs.
This medicinal product contains 38.8 mg sodium in the maximum daily dose of 6 ml, equivalent to 1.94% of the WHO recommended maximum daily intake of 2 g sodium for an adult.
4.5 Interaction with other medicinal products and other forms of interaction
Concurrent or serial use with other neurotoxic, ototoxic or nephrotoxic agents, particularly bacitracin, cisplatin, amphotericin B, cyclosporine, tacrolimus, cephaloridine, paromomycin, viomycin, polymyxin B, colistimethate/colistin, vancomycin, or other aminoglycosides should be avoided either systemically or topically because of the potential for additive effects. Increased nephrotoxicity has been reported following concomitant parenteral administration of aminoglycoside antibiotics and cephalosporins. Concomitant cephalosporin use may spuriously elevate creatinine serum level determinations.
The risk of ototoxicity is increased when amikacin is used in conjunction with rapidly acting diuretic drugs, particularly when the diuretic is administered intravenously. Diuretics may enhance aminoglycoside toxicity by altering antibiotic concentrations in serum and tissue. Such agents include furosemide and ethacrynic acid which is itself an ototoxic agent. Irreversible deafness may result.
A reduction in serum activity of aminoglycosides may occur with concomitant use of penicillin-type drugs.
There is an increased risk of hypocalcaemia when aminoglycosides are administered with bisphosphonates.
There is an increased risk of nephrotoxicity and possible ototoxicity when aminoglycosides are co-administered with platinum compounds.
The use of amikacin is not recommended in patients under the influence of anaesthetics or muscle-relaxing drugs (including ether, halothane, d-tubocurarine, succinylcholine decamethonium, atracurium, rocuronium, vecuronium or in patients receiving massive transfusions of citrate-anticoagulated blood) as neuromuscular blockade and consequent respiratory depression may occur. If blockade occurs, calcium salts may reverse this phenomenon.
Indomethacin may increase the plasma concentration of amikacin in neonates.
In patients with severely impaired renal function, a reduction in activity of aminoglycosides may occur with concomitant use of penicillin-type drugs.
In vitro admixture of aminoglycosides with beta-lactam antibiotics (penicillins or cephalosporins) may result in significant mutual inactivation. A reduction in serum activity may also occur when an aminoglycoside or penicillin-type drug is administered in vivo by separate routes. Inactivation of the aminoglycoside is clinically significant only in patients with severely impaired renal function. Inactivation may continue in specimens of body fluids collected for assay, resulting in inaccurate aminoglycoside readings. Such specimens should be properly handled (assayed promptly, frozen, or treated with beta-lactamase).
Some antibiotics could in rare cases, reduce the effectiveness of oral contraceptives by interfering with the bacterial hydrolysis of steroid conjugates in the gut and thus the reabsorption of unconjugated steroid. Thereby, the plasma levels of active steroid would decrease. This unusual interaction would occur in women with high biliary excretion of steroid conjugates. This interaction has not been reported for amikacin.
There is an increased risk of nephrotoxicity and possibly of ototoxicity when aminoglycosides are administered with platinum compounds.
Concomitantly administered thiamine (vitamin B1) may be destroyed by the reactive sodium metabisulfite component of the amikacin sulfate formulation.
Sulfite is a very reactive compound. Therefore, mixtures with other medicinal products (other than those indicated in section 6.6) should be avoided.
4.6 Fertility, pregnancy and lactation
Pregnancy
Amikacin should be administered to pregnant women and neonatal infants only when clearly needed and under medical supervision (see section 4.4).
There is limited data on the use of aminoglycosides in pregnancy. Aminoglycosides can cause foetal harm. Aminoglycosides cross the placenta and there have been reports of total, irreversible, bilateral congenital deafness in children whose mothers received streptomycin during pregnancy.
Although adverse reactions to the unborn or neonate in pregnant women who have been treated with other aminoglycosides have not been reported, there is potential for harm.
If a pregnant patient is to be treated or becomes pregnant during treatment, medical advice should be provided on the risk of the potential hazard to the fetus.
Breast-feeding
It is not known if amikacin passes into the breast milk. The decision should be made to either stop breastfeeding or stop the therapy.
Fertility
In reproduction toxicity studies in mice and rats, no effects on fertility or foetal toxicity were reported.
4.7 Effects on ability to drive and use machines
No studies on the effects on the ability to drive and use machines have been performed. However, the occurrence of some side effects (see section 4.8) may affect the ability to drive vehicles and operate machinery.
4.8 Undesirable effects
All aminoglycosides have oto-, nephro- and neurotoxic potential. The risk of these side effects is greater in patients with already impaired renal function, in patients receiving more than the recommended doses, prolonged therapy and in patients treated with other ototoxic or nephrotoxic drugs (see section 4.4).
Frequency is defined using the following convention:
Very common (≥1/10), common (≥1/100 to < 1/10), uncommon (≥1/1,000 to <1/100), rare (≥1/10,000 to <1/1,000), very rare (< 1/10,000) and not known (cannot be estimated from the available data).
| System organ class | Frequency | MedDRA Term |
| Infections and infestations | Uncommon | Superinfections or colonisation with resistant bacteria or yeasta |
| Blood and lymphatic system disorders | Rare | Anaemia, eosinophilia, granulocytopenia, leukopenia, thrombocytopenia |
| Immune system disorders | Not known | Anaphylactic response (anaphylactic reaction, anaphylactic shock and anaphylactoid reaction), hypersensitivity |
| Metabolism and nutrition disorders | Rare | Hypomagnesaemia |
| Nervous system disorders | Common | Dizziness |
| Not known | Acute muscular paralysisa | |
| Rare | Tremora, paraesthesiaa, headache, balance disordera | |
| Eye disorders | Rare | Blindnessb **, retinal infarctionb |
| Ear and labyrinth disorders | Common | Vestibular disorders with nausea, |
| Rare | Tinnitusa, hypoacusisa,, hearing loss | |
| Not known | Chochlear damage Deafnessa, deafness neurosensorya | |
| Cardiovascular disorders | Rare | Hypotonia, Hypotension, thrombophlebitis tachycardia, myocarditis |
| Respiratory, thoracic and mediastinal disorders | Not known | Apnoea, bronchospasm |
| Gastrointestinal disorders | Uncommon | Nausea, vomiting |
| Hepatobiliary disorders | Uncommon | Elevation of liver enzymes in plasma (SGOT, SGPT, LDH, alkaline phosphatase and bilirubin) |
| Skin and subcutaneous tissue disorders | Uncommon | Rash |
| Rare | Pruritus, urticaria | |
| Musculoskeletal and connective tissue disorders | Rare | Arthralgia, myokymiaa |
| Renal and urinary disorders | Common | Nephrotoxicity, Proteinuria, urea increase |
| Rare | oliguriaa , Increase in serum creatinineaalbuminuriaa, azotemiaa, red blood cells urinea, white blood cells urinea, cells in the urinea | |
| Not known | Acute renal failure, toxic nephropathy, cells in the urine | |
| General disorders and administration site conditions | Rare | Fever |
| Not known | Pain in the injection site ** |
a See section 4.4.
b Amikacin is not formulated for intavitreal use. Blindness and retinal infarction have been reported following intravitreous administration (injection into the eye) of amikacin. * Changes in renal function are usually reversible at the end of therapy. ** Amikacin is not intended for administration to the vitreous body. When amikacin was injected directly into the eye, maculopathies were observed, occasionally leading to complete loss of vision.
Description of selected adverse reactions
Cases of skin and mucosal reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported, however with an unclear connection.
Kidney and urinary tract disorders
Nephrotoxicity is manifested as increased excretion of tubule epithelia, cylindruria, increase in β2-microglobulin excretion, enzyme excretion via urine (e.g. alanine aminopeptidase, glutamine transferase, β-galactosidase, N-acetyl-glucosaminidase), azotemia, decrease in urine osmolarity, increase in blood urea nitrogen and serum creatinine, decrease in creatinine clearance. In case of minor irritations (albumin, erythrocytes, leukocytes or cylinders in urine) the fluid intake should be increased. After discontinuation of the drug, renal impairment is usually reversible.
As with all aminoglycosides, there have been reports of nephrotoxicity and acute renal failure following approval of amikacin.
Disorders of the ear and the labyrinth
Ototoxic reactions involving the 8th cranial nerve occur in approximately 0.5 - 5% of the treated patients. This may involve vestibular or cochlear function (see section 4.4).
When treating with amikacin, special attention should be paid to cochlear damage. These are manifested as tinnitus, pressure in the ears and initially merely as audiometrically detectable decrease of acoustic perceptions in the high frequency range (> 4000 Hertz) above the speech range. However, hearing loss can develop to complete, irreversible deafness despite discontinuation of the aminoglycoside. Vestibular disorders manifest in initial symptoms such as dizziness, nausea, and vomiting. In the clinical examination usually a nystagmus is detected. At the first sign of hearing or balance disorders, amikacin therapy should be discontinued.
Disorder of the nervous system
Neuromuscular blockades:
Specific risks are very rare when taking aminoglycosides. The occurrence of neuromuscular blockade, which can lead to respiratory arrest, can occur especially with intrapleural or intraperitoneal administration. The neuromuscular blocking properties of the aminoglycosides are enhanced by inhalation narcotics or muscle relaxants or curare-like drugs. Particularly at risk are patients with myasthenia gravis. Respiratory paresis requires artificial respiration. In addition, the application of potassium salts may be considered as a countermeasure.
Immune system disorders
Due to the content of sulfite it can lead to hypersensitivity reactions that may manifest as vomiting, diarrhoea, wheezing, acute asthma attack, disturbance of consciousness or shock in individual cases, especially in bronchial asthma. These reactions can vary widely individually and can lead to life-threatening conditions
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Significant risk of overdose is a potential nephro, oto and neurotoxic (neuromuscular blockade) effect. Respiratory neuromuscular blockade should be appropriately treated, including the administration of calcium in ionised form (for example as gluconate or lactobionate in 10-20% solution) (see section 4.4). In case of overdose or toxic reactions, amikacin can be removed by peritoneal or hemodialysis. Continuous arteriovenous hemofiltration also leads to a reduction of amikacin. In neonates an exchange transfusion may be considered.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Anti-infectives for systemic use, ATC code: J01GB06
Mechanism of action
The mechanism of action of amikacin is due to a disruption of protein biosynthesis on the bacterial ribosome by interaction with the rRNA and subsequent inhibition of translation. This results in a bactericidal effect.
Relationship between pharmacokinetics and pharmacodynamics
The efficacy depends essentially on the quotient of maximum serum concentration (Cmax) and minimal inhibitory concentration (MIC) of the pathogen.
Resistance mechanisms
Resistance to amikacin may be due to the following mechanisms:
- Enzymatic Inactivation: Enzymatic modification of aminoglycoside molecules is the most common mechanism of resistance. Acetyltransferases, phosphotransferases or nucleotidyltransferases are responsible for this, most of which are plasmid-encoded. Amikacin is highly stable to aminoglycoside-inactivating enzymes. It can therefore inhibit bacteria that are resistant to gentamicin and other aminoglycosides.
- Reduced penetration and active efflux: These resistance mechanisms are mainly found in Pseudomonas aeruginosa.
- Alteration of the target structure: Modifications within the ribosomes are the cause of resistance.
There is partial cross-resistance of amikacin with other aminoglycoside antibiotics.
Threshold values
The assay of amikacin is carried out using usual serial dilution. The following minimum inhibitory concentrations for sensitive and resistant pathogens have been established:
EUCAST Clinical MIC Breakpoints for amikacin (EUCAST Clinical Breakpoint table version 13.0, valid from 01-01-2023).
| Pathogen | Species-related breakpoints, mg / L of amikacin (S ≤ / R >) |
| Enterobacterales (systemic infections) | 8/81 |
| Enterobacterales (infections originating from the urinary tract) | 8/8 |
| Pseudomonas spp. (systemic infections) | 16/161 |
| Pseudomonas spp. (infections originating from the urinary tract) | 16/16 |
| Acinetobacter spp. (systemic infections) | 8/81 |
| Acinetobacter spp. (infections originating from the urinary tract) | 8/8 |
| Staphylococcus spp. (S.aureus) | 16/161 |
| Staphylococcus spp. (coagulase-negative staphylococci | 16/16 |
| Enterococcus spp. | Note2/ Note2 |
| Viridans group streptococci | Note2/ Note2 |
| Haemophilus influenzae | IE/IE |
| Moraxella catarrhalis | IE/IE |
| PK-PD (Non-species related) breakpoints | 1/1 |
1 For systemic infections, aminoglycosides should be used in combination with other active therapy. In this circumstance, the value in brackets can be used to distinguish between wild type organisms and organisms with acquired resistance mechanisms.
Note2 - Synergy with penicillins or glycopeptides can be expected if the isolate is susceptible to the penicillin or glycopeptide.
IE- Insufficient evidence
The prevalence of acquired resistance of individual species may vary over place and over time. Therefore, local information about the resistance situation is required, especially for the adequate treatment of severe infections. If the efficacy of amikacin is questionable due to the local resistance situation, expert therapy counselling should be sought. Particularly in the case of severe infections or treatment failures, a microbiological diagnosis with detection of the pathogen and its sensitivity to amikacin should be sought.
Sensitive Species
Aerobic gram-positive micro-organisms
Staphylococcus aureus
Staphylococcus haemolyticus
Staphylococcus hominis
Aerobic gram-negative micro-
organisms Coagulase negative
staphylococci Citrobacter freundii Enterobacter
aerogenes
Enterobacter cloacae
Escherichia coli
Haemophilus
influenzae Klebsiella
oxytoca Klebsiella
pneumoniae
Morganella morganii
Proteus mirabilis
Proteus vulgaris
Providencia
Pseudomonas aeruginosa 1)
Salmonella enterica (enteritis
salmonella) Serratia liquefaciens °
Serratia
marcescens
Shigella spp.
Species in which acquired resistance can be a problem Aerobic gram-positive micro-organisms
Staphylococcus epidermis
Aerobic gram-negative micro-organisms
Acinetobacter baumannii
Naturally resistant species
Aerobic gram-positive micro-organisms
Enterococcus
spp.
Streptococcus
spp.
Pneumococcus
Aerobic gram-negative micro-organisms
Burkholderia cepacia
Stenotrophomonas maltophilia
Meningococcus
oThere were no latest data when the tables were published. The primary literature, standard works and therapy recommendations presume sensitivity.
- 1) For isolates of particular patient groups, e.g. Patients with cystic fibrosis, the resistance rate
≥10%.
Resistance occurs (1-10%) in Pseudomonas aeruginosa and is common (>10%) in coagulase- negative staphylococci.
In combination with a beta-lactam antibiotic, a synergistic effect is often achieved against most bacteria including streptococci and enterococci.
5.2 Pharmacokinetic properties
After IM injection, amikacin is well tolerated locally and rapidly absorbed. After administration of 250 mg amikacin IM average serum peak concentrations of 11 μg / ml are achieved within one hour when amikacin 21 μg / ml is administered. I.V. short infusion of 500 mg amikacin results in an average serum concentration of 38 μg / ml (end of infusion). After 1 hour, 18 μg / ml were still detectable. In elderly patients (with mean creatinine clearance of 64 ml / min) the blood levels are 55 μg / ml after a 30-minute infusion of 15 mg / kg, 5.4 μg / ml after 12 hours and 1.3 μg/ ml after 24 hours.
Serum half-life in patients with normal renal function is 2.4 hours, with an average volume of distribution of 24 litres and about 28% of body weight. Plasma protein binding ranges from 0-11%. Amikacin passes into the cerebrospinal fluid in small amounts in intact meninges, while the blood-CSF barrier is penetrated more easily in Meningitis. There is no accumulation with repeated dosing. The average serum clearance rate is 100 ml / min; The renal clearance rate in normal renal function is 94 ml/min. Amikacin is not metabolized and excreted almost exclusively by glomerular filtration. In normal renal function, approximately 91% of the IM administered dose is excreted within the first 8 hours via urine in active form and 98% within 24 hours.
In case of impaired renal function, excretion is significantly delayed.
Intramuscular and intravenous administration:
Renal elimination of amikacin is reduced in newborns and especially in premature infants. Amikacin is removable by both peritoneal dialysis and hemodialysis. By peritoneal dialysis (patients without infection) about 20% of the administered amikacin dose could be removed within 8-12 hours. Hemodialysis is much more effective. Depending on the dialysis method, either 50% (range 29-81%) of the administered dose was removed within 4 hours or 40-80% was removed within 8 hours.
Experiences in children
Data from dosing studies on a daily basis show that levels in CSF in normal children are around 10 to 20% of serum concentrations and may reach 50% in meningitis. The elimination of amikacin was reduced in newborns and especially in preterm infants.
In a single study of newborns (1-6 days after birth) grouped by birth weight (<2000g, 2000-3000g and >3000g), Amikacin was given intramuscularly and/or intravenously at a dose of 7.5mg/kg. The neonatal clearance > 3000g was 0.84ml/min/kg and the terminal half-life was about 7 hours. In this group, the initial volume of distribution was 0.3ml/kg and the volume of distribution at steady state was 0.5ml/kg. In the lower birth weight groups, the clearance/kg was lower and the half-life longer. Repeated dosing every 12 hours in all the specified groups showed no accumulation after 5 days.
5.3 Preclinical safety data
No long-term studies have been performed to evaluate the carcinogenic or mutagenic potential. Studies in rats have shown that daily doses up to 10 times recommended dose for humans did not cause any adverse effects on male and female fertility.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Sodium metabisulfite (E223)
Sodium citrate
Sulfuric acid
Water for injection
6.2 Incompatibilities
Amikacin is incompatible with some penicillins and cephalosporins, amphotericin chlorothiazide sodium, erythromycin gluceptate, heparin, nitrofurantoin sodium, phenytoin sodium, thiopentone sodium and warfarin sodium, and depending on the composition and strength of the vehicle, tetracyclines, vitamins of the B group with vitamin C, and potassium chloride.
At times, amikacin may be indicated as concurrent therapy with other antibacterial agents in mixed or superinfections. In such instances, amikacin should not be physically mixed with other antibacterial agents in syringes, infusion bottles or any other equipment. Each agent should be administered separately.
6.3 Shelf life
24 months
Chemical and physical in-use stability has been demonstrated for 24 hours at room temperature.
From a microbiological point of view, the product should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2-8°C, unless dilution has taken place in controlled and validated aseptic conditions.
6.4 Special precautions for storage
This medicinal product does not require any special storage conditions.
6.5 Nature and contents of container
Amikacin 250 mg/ml Solution for Injection/Infusion consists of a 2 ml clear type I glass ampoule.
Amikacin 250 mg/ml Solution for Injection/Infusion is available in packs containing 5 ampoules.
6.6 Special precautions for disposal and other handling
For single use only, discard any unused solution.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration whenever the solution and container permit.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Kent Pharmaceuticals Limited
2nd floor, Connect 38 1 Dover Place
Ashford
Kent
England
TN23 1FB
8 MARKETING AUTHORISATION NUMBER(S)
PL 08215/0118
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
28/11/2022
10 DATE OF REVISION OF THE TEXT
23/01/2026