

Summary of Product Characteristics (SmPC) - Waylivra 285 mg solution for injection in Pre-filled syringe
1 NAME OF THE MEDICINAL PRODUCT
Waylivra 285 mg solution for injection in pre-filled syringe
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each ml contains 200 mg volanesorsen sodium, equivalent to 190 mg volanesorsen.
Each single-dose pre-filled syringe contains 285 mg of volanesorsen in 1.5 ml solution.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Solution for injection (injection).
Clear, colourless to slightly yellow solution with a pH of approximately 8 and osmolarity of 363-485 mOsm/kg.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Waylivra is indicated as an adjunct to diet in adult patients with genetically confirmed familial chylomicronemia syndrome (FCS) and at high risk for pancreatitis, in whom response to diet and triglyceride lowering therapy has been inadequate.
4.2 Posology and method of administration
Posology
Treatment should be initiated by and remain under the supervision of a physician experienced in the treatment of patients with FCS. Prior to initiating Waylivra, secondary causes of hypertriglyceridemia (e.g. uncontrolled diabetes, hypothyroidism) should be excluded or appropriately addressed.
The recommended starting dose is 285 mg in 1.5 ml injected subcutaneously once weekly for 3 months. Following 3 months, dose frequency should be reduced to 285 mg every 2 weeks.
However, treatment should be discontinued in patients with a reduction in serum triglycerides <25% or who fail to achieve serum triglycerides below 22.6 mmol/L after 3 months on volanesorsen 285 mg weekly.
After 6 months of treatment with volanesorsen, increase of dose frequency to 285 mg weekly should be considered if response has been inadequate in terms of serum triglyceride reduction as evaluated by the supervising experienced specialist and in the condition that platelet counts are in the normal range. Patients should be re-downtitrated to 285 mg every 2 weeks if the higher 285 mg once weekly dose does not provide significant additional triglyceride reduction after 9 months.
Patients should be instructed to give the injection on the same day of the week, according to medically determined frequency of administration.
If a dose is missed and noticed within 48 hours, the patient should be directed to give the missed dose as soon as possible. If not noticed within 48 hours, then the missed dose should be skipped and the next planned injection given.
Platelet monitoring and dose adjustments
Before initiation of treatment, platelet count should be measured. If the platelet count is below 140 x 109/L another measurement should be taken approximately a week later to reassess. If platelet count remains below 140 x 109/L upon a second measurement, Waylivra should not be initiated (see section 4.3).
After commencing treatment, patients should have platelet levels monitored at least every two weeks, depending on the platelet levels.
Treatment and monitoring should be adjusted according to laboratory values in line with Table 1.
For any patient dose paused or discontinued due to severe thrombocytopenia, the benefits and risks of returning to treatment once platelet count ≥100 x 109/L should be carefully considered. For discontinued patients, a haematologist should be consulted prior to resuming treatment.
Table 1. Waylivra monitoring and treatment recommendations
| Platelet count (x109/L) | Dose (285 mg prefilled syringe) | Monitoring frequency |
| Normal (≥140) | Starting dose: Weekly After 3 months: Every 2 weeks | Every 2 weeks |
| 100 to 139 | Every 2 weeks | Weekly |
| 75 to 99 | Pause treatment for ≥4 weeks and resume treatment after platelet levels ≥ 100 x 109/L | Weekly |
| 50 to 74a | Pause treatment for ≥4 weeks and resume treatment after platelet levels ≥ 100 x 109/L | Every 2-3 days |
| Less than 50a, b | Discontinue treatment Glucocorticoids recommended | Daily |
a See section 4.4 for recommendations regarding use of antiplatelet agents/non-steroidal anti-inflammatory drugs (NSAIDs)/anticoagulants
b Consultation of a haematologist is needed to reconsider the benefit/risk for possible further treatment with volanesorsen.
Special populations
Elderly population
No starting dose adjustment is necessary for elderly patients. There is limited clinical data for patients aged 65 and over (see sections 5.1 and 5.2).
Renal impairment
No starting dose adjustment is necessary in patients with mild to moderate renal impairment. The safety and efficacy in patients with severe renal impairment has not been established and these patients should be closely observed.
Hepatic impairment
This medicinal product has not been studied in patients with hepatic impairment. The medicinal product is not metabolised via the cytochrome P450 enzyme system in the liver, therefore dose adjustment is unlikely to be required in patients with hepatic impairment.
Paediatric population
The safety and efficacy of this medicinal product in children and adolescents below 18 years of age have not yet been established. No data are available.
Method of administration
This medicinal product is intended for subcutaneous use only. It should not be administered intramuscularly or intravenously.
Each pre-filled syringe is for single use only.
Waylivra should be inspected visually prior to administration. The solution should be clear and colourless to slightly yellow. If the solution is cloudy or contains visible particulate matter, the contents must not be injected and the medicinal product should be returned to the pharmacy.
The first injection administered by the patient or caregiver should be performed under the guidance of an appropriately qualified health care professional. Patients and/or caregivers should be trained in the administration of this medicinal product in accordance with the patient information leaflet.
The pre-filled syringe should be allowed to reach room temperature prior to injection. It should be removed from refrigerated storage (2 ° to 8 °C) at least 30 minutes before use. Other warming methods should not be used. It is normal to see a large air bubble. It should not be attempted to remove the air bubble.
It is important to rotate sites for injection. Sites for injection include the abdomen, upper thigh region, or outer area of the upper arm. If injected in the upper arm, the injection should be administered by another person. Injection should be avoided at the waistline and other sites where pressure or rubbing may occur from clothing. This medicinal product should not be injected into tattoos, moles, birthmarks, bruises, rashes, or areas where the skin is tender, red, hard, bruised, damaged, burned, or inflamed.
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
Chronic or unexplained thrombocytopenia. Treatment should not be initiated in patients with thrombocytopenia (platelet count <140 x 109/L).
4.4 Special warnings and precautions for use
Thrombocytopenia
Waylivra is very commonly associated with reductions in platelet count in patients with FCS, which may result in thrombocytopenia (see section 4.8). Patients with lower body weight (less than 70 kg) may be more prone to thrombocytopenia during treatment with this medicinal product. Careful monitoring for thrombocytopenia is important during treatment with this medicinal product in patients with FCS (see section 4.2). Recommendations for adjustments to monitoring frequency and dosing are specified in Table 1 (see section 4.2).
Discontinuation of antiplatelet medicinal products/NSAIDs/anticoagulants should be considered for platelet levels < 75 x 109/L. Treatment with these medicinal products must be discontinued at platelet levels < 50 x 109/L (see section 4.5).
Patients should be instructed to report to their physician immediately if they experience any signs of bleeding, which can include petechiae, spontaneous bruising, subconjunctival bleeding, or other unusual bleeding (including nosebleeds, bleeding from gums, stools, or unusually heavy menstrual bleeding), neck stiffness, atypical severe headache, or any prolonged bleeding.
LDL-C Levels
With treatment with Waylivra, LDL-C levels may rise but will usually remain within the normal range.
Renal toxicity
Renal toxicity has been observed after administration of volanesorsen and other subcutaneously and intravenously administered antisense oligonucleotides. Monitoring for evidence of nephrotoxicity by routine urine dipstick is recommended on a quarterly basis. In the case of a positive assessment, a broader assessment of renal function, including serum creatinine and a 24-hour collection to quantify the proteinuria and assess creatinine clearance, should be performed. Treatment should be discontinued if: proteinuria of ≥ 500 mg/24 hour is recorded, or an increase in serum creatinine ≥ 0.3 mg/dL (26.5 μmol/L) that is >ULN is recorded, or creatinine clearance estimated by the CKD-EPI equation is ≤ 30 mL/min/1.73m2. Treatment should also be discontinued for any clinical symptoms or signs of renal impairment pending the previous confirmatory assessments.
Hepatotoxicity
Elevations of liver enzymes have been observed after administration of other subcutaneously and intravenously administered antisense oligonucleotides. Monitoring for hepatotoxicity through serum liver enzymes and bilirubin should be assessed on a quarterly basis. Treatment should be discontinued if there is a single increase in ALT or AST > 8 x ULN, or an increase > 5 x ULN, which persists for ≥ 2 weeks, or lesser increases in ALT or AST that are associated with total bilirubin > 2 x ULN or INR > 1.5. Treatment should also be discontinued for any clinical symptoms or signs of hepatic impairment or hepatitis.
Immunogenicity and inflammation
No evidence of altered safety profile or clinical response was associated with presence of anti-drug antibodies. If formation of anti-drug antibodies with a clinically significant effect is suspected, contact the Marketing Authorisation Holder to discuss antibody testing.
Monitoring of inflammation should be assessed through quarterly assessment of erythrocyte sedimentation rate (ESR).
Sodium content
This medicinal product contains less than 1 mmol sodium (23 mg) per dose of 285 mg, that is to say essentially ‘sodium-free’.
4.5 Interaction with other medicinal products and other forms of interaction
No clinical drug interaction studies have been conducted.
Clinically relevant pharmacokinetic interactions are not expected between volanesorsen and substrates, inducers or inhibitors of cytochrome P450 (CYP) enzymes, and drug transporters. It is unknown whether triglyceride lowering by volanesorsen and the potentially ensuing decrease in inflammation leads to normalisation of CYP enzyme expression.
In clinical studies, this medicinal product has been used in combination with fibrates and fish oils with no impact on the medicinal product pharmacodynamics or pharmacokinetics. There were no adverse events related to drug-drug interactions reported during the clinical program, however this is based on limited data.
The effect of concomitant administration of this medicinal product with alcohol or medicinal products known to have potential for hepatotoxicity (e.g., paracetamol) is unknown. If signs and symptoms of hepatotoxicity develop, use of the hepatotoxic medicinal product should be discontinued.
Antithrombotic agents and medicinal products that may lower platelet count
It is not known whether the risk of bleeding is increased by concomitant use of volanesorsen and antithrombotic agents or medicinal products that may lower platelet count or affect platelet function. Discontinuation of antiplatelet medicinal products/NSAIDs/anticoagulants should be considered for
platelet levels <75 x 109/L and treatment with these medicinal products should be stopped at platelet
levels < 50 x 109/L (see section 4.4).
4.6 Fertility, pregnancy and lactation
Pregnancy
There are no data on the use of volanesorsen in pregnant women.
Animal studies do not indicate direct or indirect harmful effects with respect to reproductive toxicity (see section 5.3).
As a precautionary measure, it is preferable to avoid the use of this medicinal product during pregnancy.
Breastfeeding
In non-clinical studies, levels of volanesorsen in milk were very low in lactating mice. Available pharmacodynamic/toxicological data in animals have shown excretion of very low amounts of volanesorsen in milk (see section 5.3). Due to the poor oral bioavailability of this medicinal product, it is considered unlikely that these low milk concentrations would result in systemic exposure from nursing.
It is unknown whether volanesorsen or metabolites are excreted in human milk.
A risk to the newborn infant cannot be excluded.
A decision must be made whether to discontinue breast-feeding or to discontinue/abstain from therapy taking into account the benefit of breast feeding for the child and the benefit of therapy for the woman.
Fertility
No clinical data on the effect of this medicinal product on human fertility are available. Volanesorsen had no effect on fertility in mice.
4.7 Effects on ability to drive and use machines
Volanesorsen has no or negligible influence on the ability to drive and use machines.
4.8 Undesirable effects
Summary of the safety profile
In clinical studies in patients with FCS, the most commonly reported adverse reactions during treatment were platelet count decreased occurring in 29%, thrombocytopenia occurring in 21% (see section 4.4), and injection site reactions occurring in 82% of patients during the pivotal studies.
Tabulated list of adverse reactions
Table 2 presents the adverse reactions from the Phase 3 studies in patients with FCS in receiving volanesorsen subcutaneously.
The frequency of adverse reactions is defined using the following convention: very common (≥1/10); common (≥1/100 to <1/10); uncommon (≥1/1,000 to <1/100); rare (≥1/10,000 to <1/1,000); very rare (<1/10,000); and not known (cannot be estimated from available data). Within each frequency grouping, adverse reactions are presented in order of decreasing seriousness.
Table 2: Summary of adverse reactions in clinical studies in patients with FCS
(N=87)
| System Organ Class | Very common | Common |
| Blood and lymphatic system disorders | Thrombocytopenia | Leukopenia Lymphopenia Eosinophilia Immune thrombocytopenic purpura Spontaneous haematoma |
| Immune system disorders | Immunisation reaction Hypersensitivity Serum sickness-like reaction | |
| Metabolism and nutrition disorders | Diabetes mellitus | |
| Psychiatric disorders | Insomnia | |
| Nervous system disorders | Headache | Syncope Hypoaesthesia Presyncope Retinal migraine Dizziness Tremor |
| Eye disorders | Conjunctival haemorrhage Vision blurred | |
| Vascular disorders | Hypertension Haemorrhage Haematoma Hot flush | |
| Respiratory, thoracic and mediastinal disorders | Dyspnoea Pharyngeal oedema Wheezing Epistaxis |
| System Organ Class | Very common | Common |
Cough Nasal congestion | ||
| Gastrointestinal disorders | Nausea Diarrhoea Vomiting Abdominal distension Abdominal pain Dry mouth Gingival bleeding Mouth haemorrhage Parotid gland enlargement Dyspepsia Gingival swelling | |
| Skin and subcutaneous tissue disorders | Erythema Pruritus Rash Urticaria Hyperhidrosis Petechiae Ecchymosis Night sweats Papule Skin hypertrophy Swelling face | |
| Musculoskeletal and connective tissue disorders | Myalgia | Arthralgia Pain in extremity Arthritis Musculoskeletal pain Back pain Neck pain Pain in jaw Muscle spasms Joint stiffness Myositis Peripheral arthritis |
| Renal and urinary disorders | Haematuria Proteinuria |
| System Organ Class | Very common | Common |
| General disorders and administration site conditions | Injection site erythema Injection site pain Injection site swelling Injection site discolouration Injection site induration Injection site pruritus Injection site bruising Chills Injection site oedema | Injection site haematoma Asthenia Fatigue Injection site reaction Pyrexia Injection site hypoaesthesia Injection site haemorrhage Injection site warmth Injection site dryness Injection site pallor Injection site urticaria Injection site vesicles Malaise Feeling hot Influenza-like illness Injection site discomfort Injection site inflammation Injection site mass Oedema Pain Injection site paraesthesia Injection site scab Injection site papule Injection site rash Non-cardiac chest pain Vessel puncture site haemorrhage |
| Investigations | Platelet count decreased | Haemoglobin decreased White blood cell count decreased Blood creatinine increased Blood urea increased Creatinine renal clearance decreased Hepatic enzyme increased International normalised ratio increased Transaminases increased |
| Injury, poisoning and procedural | Contusion |
| System Organ Class | Very common | Common |
| complications |
Description of selected adverse reactions
Thrombocytopenia
In the pivotal Phase 3 study in patients with FCS (the APPROACH study), confirmed reductions in platelet counts to below normal (140 x 109/L) were observed in 75% of FCS patients treated with volanesorsen and 24% of placebo patients; confirmed reductions to below 100 x 109/L were observed in 47% of patients treated with volanesorsen compared with no placebo patients. In APPROACH 5 patients who discontinued therapy due to platelet levels included 2 patients with platelet counts <25 x 109/L and 3 with platelet counts between 50 x 109/L and 75 x 109/L. It was also reported in this study that platelet count decreased was reported in 11 (33%) patients versus 1 (3%), and thrombocytopenia was reported in 4 (12%) patients vs none for subjects treated with volanesorsen compared to placebo, respectively.
In the open-label extension (CS7), confirmed reductions in platelet counts to below normal (140 x 109/L) were observed in 52 (79%) patients overall, including 37 (74%) patients in the treatment-naïve group. Confirmed reductions to below 100 x 109/L were observed in 33 (50%) patients overall including 24 (48%) treatment naïve patients. In the open-label extension, 11 patients discontinued due to thrombocytopenia and platelet-related events. None of these patients had any major bleeding events and all recovered to normal platelet count following drug discontinuation and administration of glucocorticoids where medically indicated. In this open-label extension study, platelet count decreased was reported in 16 (24%) and thrombocytopenia was reported in 14 (21%) patients.
For pooled data with the APPROACH study and the CS7 study, platelet count decreased was reported in 25 (29%) patients, and thrombocytopenia was reported in 18 (21%).
Immunogenicity
In the Phase 3 clinical studies (CS16 and APPROACH), 16% and 33% of volanesorsen-treated patients tested positive for anti-drug antibodies during 6-month and 12-month treatment, respectively. No evidence of altered safety profile or clinical response was associated with presence of anti-drug antibodies; however this is based on the limited long-term data (see section 4.4).
Injection site reactions
Injection site reactions defined as any local cutaneous reaction at the injection site persisting more than 2 days occurred in 79% of volanesorsen-treated patients in the APPROACH study and 81% of patients in its open-label extension (CS7). Injection site reactions occurred in 80% of volanesorsen-treated patients across both studies. These local reactions were mostly mild and typically consisted of 1 or more of the following: erythema, pain, pruritus, or local swelling. Injection site reactions did not occur with all injections and resulted in discontinuation for 1 patient in the APPROACH study and 1 patient in the open label extension (CS7).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
There is no clinical experience with overdose of this medicinal product. In the case of overdose, patients should be carefully observed and supportive care administered, as appropriate. Symptoms of overdose are expected to be limited to constitutional symptoms and injection site reactions.
Haemodialysis is unlikely to be beneficial given that volanesorsen is rapidly distributed into cells.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: lipid modifying agents, other lipid modifying agents, ATC code: C10AX18
Mechanism of action
Volanesorsen is an antisense oligonucleotide designed to inhibit the formation of apoC-III, a protein that is recognised to regulate both triglyceride metabolism and hepatic clearance of chylomicrons and other triglyceride-rich lipoproteins. The selective binding of volanesorsen to the apoC-III messenger ribonucleic acid (mRNA) within the 3′ untranslated region at base position 489-508 causes the degradation of the mRNA. This binding prevents translation of the protein apoC-III, thus removing an inhibitor of triglyceride clearance and enabling metabolism through an LPL-independent pathway.
Pharmacodynamic effects
Effects of Waylivra on lipid parameters
In APPROACH, the Phase 3 clinical study in patients with FCS, Waylivra reduced fasting triglycerides, total cholesterol, non-HDL cholesterol, apoC-III, apoB-48, and chylomicron triglyceride levels and increased LDL-C, HDL-C, and apoB (see Table 3).
Table 3: Mean Baseline and Percent Change in Lipid Parameters from
Baseline to Month 3
Lipid Parameter (g/L for apoC-III, apoB, apoB-48; mmol/L for cholesterol, triglycerides) | Placebo (N=33) | Volanesorsen 285 mg (N=33) | ||
| Baseline | % Change | Baseline | % Change | |
| Triglycerides | 24.3 | +24% | 25.6 | -72% |
| Total Cholesterol | 7.3 | +13% | 7.6 | -39% |
| LDL-C | 0.72 | +7% | 0.73 | +139% |
| HDL-C | 0.43 | +5% | 0.44 | +45% |
| Non-HDL-C | 6.9 | +14% | 7.1 | -45% |
| ApoC-III | 0.29 | +6% | 0.31 | -84% |
| ApoB | 0.69 | +2% | 0.65 | +20% |
| ApoB-48 | 0.09 | +16% | 0.11 | -75% |
| Chylomicron Triglycerides | 20 | +38% | 22 | -77% |
Cardiac Electrophysiology
At a drug concentration 4.1 times the peak drug plasma concentrations (Cmax) of the maximum recommended dose (285 mg subcutaneous injection), volanesorsen did not prolong the heart-rate corrected QT (QTc) interval.
Clinical efficacy and safety
APPROACH study in patients with FCS
The APPROACH study is a randomised, double-blind placebo-controlled 52-week multicentre clinical study in 66 patients with FCS, evaluating volanesorsen 285 mg administered as a subcutaneous injection (33 treated with volanesorsen, 33 with placebo). Main inclusion criteria were a diagnosis of FCS (Type 1 hyperlipoproteinemia) in combination with a history of chylomicronemia evidenced by documentation of lactescent serum or documentation of fasting TG measurement ≥ 880 mg/dl.
Diagnosis of FCS required documentation of at least one of the following:
- a) Confirmed homozygote, compound heterozygote, or double heterozygote for known loss-of-function mutations in Type 1-causing genes (such as LPL, APOC2, GPIHBP1, or LMF1)
- b) Post heparin plasma LPL activity of ≤ 20% of normal.
Patients taking Glybera within 2 years prior to screening were excluded from the study.
Nineteen of the 33 patients in the volanesorsen group completed 12 months of study treatment. Thirteen of these patients had dose adjustment/pause on the study. Out of the 13, 5 had a dose pause, 5 had a dose adjustment and 3 had both a dose pause and dose adjustment.
Mean age was 46 years (range 20-75 years; 5 patients ≥65 years old); 45% were men; 80% were White, 17% were Asian, and 3% were of other races. Mean body mass index was 25 kg/m2. A history of documented acute pancreatitis was reported for 76% of patients and a history of diabetes was reported for 15% of patients; 21% of patients had a recorded history of lipaemia retinalis and 23% of patients had a recorded history of eruptive xanthomas. The median age at diagnosis was 27 years, with 23% shown to lack a known FCS genetic mutation.
At study entry, 55% of patients were on lipid lowering therapies (48% on fibrates, 29% on fish oils, 20% HMG-CoA reductase inhibitors), 27% were on pain medicinal products, 20% were on platelet aggregation inhibitors, and 14% were on nutritional supplements. Background lipid-lowering therapies remained consistent throughout the study. Patients were prohibited from receiving plasma apheresis within 4 weeks prior to screening or during the study; 11% of patients had previously received gene therapy for lipoprotein lipase deficiency (i.e., alipogene tiparvovec), on average 8 years prior to starting this study. After a 6-week diet run-in period, the mean fasting triglyceride level at baseline was 2,209 mg/dL (25.0 mmol/L). Compliance with diet and alcohol restriction was reinforced through periodic counselling sessions during the study.
Waylivra led to a statistically significant reduction in triglyceride levels as compared to placebo at the primary efficacy endpoint, defined as percent change from baseline to Month 3 in fasting triglycerides, in addition to a lower incidence of pancreatitis over the 52-week treatment period in a post-hoc analysis (Table 4).
At the primary efficacy endpoint, the treatment difference between volanesorsen and placebo in mean fasting triglyceride percent change was -94% (95% CI: -122% -67%; p < 0.0001, with a decrease of -77% from baseline (95% CI: -97, -56) in patients receiving volanesorsen and an increase of 18% from baseline (95% CI: -4, 39) in patients receiving placebo (Table 4).
Table 4: Mean Change from Baseline in Fasting Triglycerides in the Phase 3
Placebo-Controlled Study in Patients with FCS at Month 3 (APPROACH)
| Placebo (N=33) | Volanesorsen 285 mg (N = 33) | Relative Difference in Change vs Placebo | |
LS Mean Percent Change (95% CI) | +18% (-4, 39) | -77% (-97, -56) | -94%* (-122, -67) |
LS Mean Absolute Change (95% CI) mg/dL or mmol/L | +92 (-301, +486) mg/dL +1 (-3, +5) mmol/L | -1,712 (-2,094, -1,330) mg/dL -19 (-24, -15) mmol/L | -1,804 (-2,306, -1,302) mg/dL -20 (-26, -15) mmol/L |
*p-value < 0.0001 (primary efficacy endpoint)
Difference= LS Mean of [volanesorsen % Change – Placebo % Change] (ANCOVA model)
Onset of the reduction was rapid with separation from placebo seen as early as 4 weeks and maximum response seen at 12 weeks, with clinically and statistically significant triglyceride reduction maintained over 52 weeks (Figure 1). The mean fasting triglyceride percent change was significantly different between volanesorsen and placebo arms at 3, 6, and 12 months; the volanesorsen arm included patients who did not complete dosing but who returned for assessments over the 52-week study. There were no significant differences in treatment effect across the stratification factors of presence or absence of concurrent omega-3 fatty acids or fibrates.
Figure 1: LS Mean Percent Change in Fasting Triglycerides in Phase 3 Study in
Patients with FCS (APPROACH)
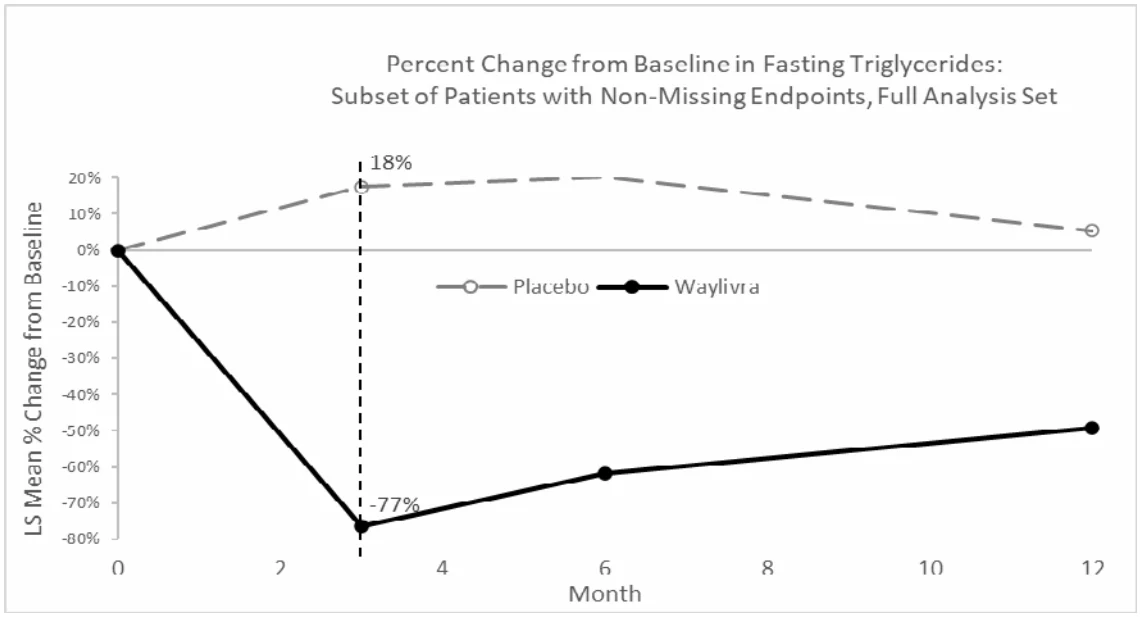
LS mean percent change from baseline in fasting triglycerides based on the observed data are displayed.
Difference= LS Mean of [volanesorsen % Change – Placebo % Change] (ANCOVA model)
p-value from ANCOVA model < 0.0001 at Month 3 (primary efficacy endpoint), Month 6 and Month 12
Additional efficacy results for changes in triglyceride are presented in Table 5. Most patients receiving volanesorsen experienced a clinically significant reduction in triglycerides.
Table 5: Additional Results for Changes in Triglycerides in the APPROACH study (Primary endpoint at Month 3)
| Parameter at Month 3a | Placebo (N=31) | Volanesorsen 285 mg (N=30) |
| Percent of patientsb with fasting plasma triglyceride < 750 mg/dL (8.5 mmol/L)* | 10% | 77% |
Percent of patientsc with ≥ 40% reduction in fasting triglycerides** | 9% | 88% |
a The Month 3 endpoint was defined as the average of Week 12 (Day 78) and Week 13 (Day 85) fasting assessments. If 1 visit was missing, then the other visit was used as the endpoint.
b The denominator for percentage calculation was the total number of patients in FAS with baseline fasting triglyceride ≥ 750 mg/dL (or 8.5 mmol/L) in each treatment group.
c The denominator for percentage calculation was the total number of patients in each treatment group.
* p-value =0.0001
**p-value < 0.0001
P-values from logistic regression model with treatment, presence of pancreatitis and presence of concurrent omega-3 fatty acids and/or fibrates as factors, and logarithm-transformed baseline fasting triglycerides as a covariate.
In the APPROACH study, the numerical incidence of pancreatitis in patients treated with volanesorsen was lower compared with placebo (3 patients 4 events in 33 placebo patients vs 1 patient 1 event in 33 volanesorsen patients).
An analysis of patients with a history of recurrent pancreatitis events (≥ 2 events in the 5 years prior to Study Day 1) showed a significant reduction in pancreatitis attacks in volanesorsen-treated patients compared to placebo treated patients (p=0.0242). In the volanesorsen group, of the 7 patients who had 24 adjudicated pancreatitis attacks in the prior 5 years, none of the patients experienced a pancreatitis attack during the 52 week treatment period. In the placebo group, of the 4 patients who had 17 adjudicated pancreatitis attacks in the prior 5 years, 3 patients experienced 4 pancreatitis attacks during the 52-week treatment period.
Open-label extension study in patients with FCS
CS7 is a multicentre, open-label extension Phase 3 study designed to evaluate the safety and efficacy of dosing and extended dosing with volanesorsen in patients with FCS. All patients enrolled either had participated in the APPROACH Study, in the CS16 Study, or were new FCS patients and had completed qualification assessments prior to receiving volanesorsen 285 mg once per week or a reduced frequency for safety or tolerability reasons determined in their index study. A total of 68 patients have been treated in this study including 51 treatment-naïve patients, 14 patients who had received volanesorsen in Study CS6, and 3 patients who had received volanesorsen in Study CS16. Fifty patients had a dose pause, 45 had a dose adjustment and 41 had both a dose pause and a dose adjustment.
Data from Study CS7 is provided in Table 6. The percent change in fasting TG from Index Study Baseline to Open-label Month 3 for the APPROACH- and CS16-volanesorsen patients was -49.2% and -64.9%, respectively. The percent change in fasting TG from index study baseline to open-label month 6, month 12 and month 24 for the APPROACH-volanesorsen patients was -54.8%, -35.1% and -50.2%, respectively.
Table 6: Summary of Fasting Triglycerides (Mean (SD, SEM), mg/dL) Over Time in Study CS7 (N=68)
| Time Point | Treatment-naïve Group (Open-label Study Baselinea, N=51) | APPROACH- volanesorsen (Index Study Baselinea, N=14) | CS16-volanesorsen (Index Study Baselinea, N=3) |
| n | Observe d Value | % change from Baselin e | n | Observe d Value | % change from Baselin e | n | Observe d Value | % change from Baselin e | |
| Baseli nea | 51 | 2341 (1193, 167) | - | 14 | 2641 (1228, 328) | - | 3 | 2288 (1524, 880) | - |
| Month 3 | 47 | 804 (564, 82) | -59.8 (37.0, 5.4) | 14 | 1266 (812, 217) | -49.2 (34.8, 9.3) | 3 | 855 (651, 376) | -64.9 (9.1, 5.3) |
| Month 6 | 49 | 1032 (695, 99) | -45.5 (42.9, 6.1) | 13 | 1248 (927, 257) | -54.8 (23.8, 6.6) | 3 | 1215 (610, 352) | -43.0 (19.7, 11.4) |
| Month 12 | 45 | 1332 (962, 143) | -36.3 (44.2, 6.6) | 12 | 1670 (1198, 346) | -35.1 (45.6, 13.2) | 3 | 1351 (929, 536) | -41.6 (36.3, 21.0) |
| Month 15 | 34 | 1328 (976, 167) | -35.6 (48.1, 8.2) | 10 | 1886 (1219, 386) | -26.5 (57.4, 18.1) | 2 | 1422 (190, 135) | 3.4 (23.3, 16.5) |
| Month 18 | 27 | 1367 (938, 181) | -37.5 (45.6, 8.8) | 7 | 1713 (1122, 424) | -38.4 (32.2, 12.2) | 2 | 1170 (843, 596) | -24.0 (31.9, 22.6) |
| Month 24 | 21 | 1331 (873, 190) | -40.5 (47.4, 10.3) | 5 | 1826 (1743, 780) | -50.2 (32.2, 14.4) | 2 | 1198 (1177, 832) | -26.3 (56.0, 39.6) |
a Baseline values for treatment-naïve group were taken from the open-label study CS7 and baseline for APPROACH-volanesorsen and CS16-volanesorsen groups were taken from the respective index study.
Elderly population
Clinical studies included 4 patients with FCS aged 65 treated with volanesorsen in randomised control studies (phase II study CS2, 1 patient; APPROACH 3 patients), and 6 patients aged 65 and over in the open-label extension study (CS7). No overall differences in safety or effectiveness were observed between these patients and younger patients, however data are limited in this subpopulation.
Paediatric population
The European Medicines Agency has deferred the obligation to submit the results of studies with volanesorsen in one or more subsets of the paediatric population in the treatment of familial chylomicronemia syndrome (see section 4.2 for information on paediatric use).
This medicinal product has been authorised under a so-called ‘conditional approval’ scheme. This means that further evidence on this medicinal product is awaited. The MHRA will review new information on this medicinal product at least every year and this SmPC will be updated as necessary.
5.2 Pharmacokinetic properties
Absorption
Following subcutaneous injection, peak plasma concentrations of volanesorsen are typically reached in 2 to 4 hours. The absolute bioavailability of volanesorsen following a single subcutaneous administration is approximately 80% (most likely higher because an AUC of 0 to 24 hours was used and volanesorsen has a half-life of >2 weeks).
Following a dose of 285 mg once weekly in patients with FCS, the estimated geometric mean (coefficient of variation % of geometric mean) steady-state Cmax is 8.92 µg/ml (35%), AUC0-168h is 136 µg*h/ml (38%), and Ctrough is 127 ng/ml (58%) in patients who remain negative for anti-drug antibody. An alternative dosing regimen of 285 mg volanesorsen every two weeks results in a Ctrough,ss of approximately 58.0 ng/ml with Cmax and AUC similar compared to the once weekly dosing regimen.
Distribution
Volanesorsen was rapidly and widely distributed to tissues following subcutaneous or intravenous administration in all species evaluated. The estimated steady-state volume of distribution (Vss) in patients with FCS is 330 L. Volanesorsen is highly bound to human plasma proteins (>98%) and the binding is concentration independent.
In vitro studies show that volanesorsen is not a substrate or inhibitor of P-glycoprotein (P-gp), breast cancer resistance protein (BCRP), organic anion transporting polypeptides (OATP1B1, OATP1B3), bile salt export pump (BSEP), organic cation transporters (OCT1, OCT2), or organic anion transporters (OAT1, OAT3).
Biotransformation
Volanesorsen is not a substrate for CYP metabolism, and is metabolised in tissues by endonucleases to form shorter oligonucleotides that are then substrates for additional metabolism by exonucleases. Unchanged volanesorsen is the predominant circulating component.
In vitro studies indicate that volanesorsen is not an inhibitor of CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP2E1, or CYP3A4 or inducer of CYP1A2, CYP2B6, or CYP3A4.
Elimination
Elimination involves both metabolism in tissues and excretion in urine. Urinary recovery of the parent drug was limited in humans with < 3% of administered subcutaneous dose recovered within 24 hours post dose. The parent drug and 5- to 7-mer chain-shortened metabolites accounted for approximately 26% and 55% of oligonucleotides recovered in urine, respectively. Following subcutaneous administration, terminal elimination half-life is approximately 2 to 5 weeks.
In animals, elimination of volanesorsen was slow and occurred mainly via urinary excretion, reflecting rapid plasma clearance principally to tissues. Both volanesorsen and shorter oligonucleotide metabolites (predominantly 7-mer metabolites (generated either from 3′-deletions or 5′-deletions)) were identified in human urine.
Linearity/non-linearity
Single- and multiple-dose pharmacokinetics of volanesorsen in healthy volunteers and patients with hypertriglyceridemia have shown that the Cmax of volanesorsen is dose-proportional over a dose range of 100 to 400 mg and the AUC is slightly more than dose-proportional over the same dose range. Steady-state was reached approximately 3 months after starting volanesorsen. Accumulation in Ctrough was observed (7- to 14-fold) and little or no increase in Cmax or AUC was observed following weekly SC administration over a dose of 200 to 400 mg. Some accumulation in AUC and Cmax was observed for the 50 to 100 mg dose. Since the administered dose will be 285 mg every two weeks, or 142.5 mg weekly, little increase in Cmax or AUC is expected upon multiple dosing in the clinical setting.
Special Populations
Renal impairment
A population pharmacokinetic analysis suggests that mild and moderate renal impairment has no clinically relevant effect on the systemic exposure of volanesorsen. No data are available in patients with severe renal impairment.
Hepatic impairment
The pharmacokinetics of volanesorsen in patients with hepatic impairment is unknown.
Age, sex, weight, and race
Based on the population pharmacokinetic analysis, age, body weight, sex, or race has no clinically relevant effect on volanesorsen exposure. There are limited data available in subjects >75 years of age.
Anti-volanesorsen antibody formation affecting pharmacokinetics
The formation of binding antibodies to volanesorsen appeared to increase total Ctrough by 2- to 19-fold.
5.3 Preclinical safety data
Non-clinical data reveal no special hazard for humans based on conventional studies of safety pharmacology, genotoxicity, carcinogenicity or toxicity to reproduction and development.
Dose and time-dependent reductions in platelet counts were observed in Cynomolgus monkey repeated dose studies. The decrease was gradual, self-sustaining and did not decrease to adverse levels. In individual monkeys, severe thrombocytopenia was noted in the 9 month study of drug treated groups at clinically relevant exposures and has also been observed in clinical studies. The decrease in platelet counts was not acute and decreased to below 50,000 cells/μl. Platelet counts recovered after cessation of treatment, but decreased again below 50,000 cells/μl after treatment was resumed in some monkeys. Decreased platelet counts were also observed in rodent repeated dose studies. A mode of action for the observed thrombocytopenia is currently not known.
In nonclinical studies, levels of volanesorsen in milk were very low in lactating mice. The concentrations in breast milk of mice were >800 fold lower than effective tissue concentrations in maternal liver. Due to the poor oral bioavailability of volanesorsen, it is considered unlikely that these low milk concentrations would result in systemic exposure from nursing (see section 4.6).
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Sodium hydroxide (for pH adjustment)
Hydrochloric acid (for pH adjustment)
Water for injections.
6.2 Incompatibilities
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
6.3 Shelf life
5 years
This medicinal product can be removed from refrigeration and stored, in the original carton, at room temperature (below 30 °C) for up to 6 weeks. In this 6-week period, it can be kept as needed between refrigerated and room temperature (up to 30 °C). This medicinal product must be discarded immediately if not used within the 6 weeks after the first time it is removed from refrigerated storage.
6.4 Special precautions for storage
Store in a refrigerator (2 ° - 8 °C).
Do not freeze.
Store in the original carton in order to protect from light.
6.5 Nature and contents of container
Single-dose, Type I glass pre-filled syringe with a siliconised chlorobutyl rubber stopper and staked needle with shield, filled to deliver 1.5 ml of solution.
Pack sizes of one pre-filled syringe or multipacks containing 4 (4 packs of 1) pre-filled syringes.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
This medicinal product should be inspected visually prior to administration. The solution should be clear and colourless to slightly yellow. If the solution is cloudy or contains visible particulate matter, the contents must not be injected and the medicinal product should be returned to the pharmacy.
Use each pre-filled syringe only once and then place in a sharps disposal container for disposal according to community guidelines.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Akcea Therapeutics Ireland Ltd
St. James House
72 Adelaide Road, Dublin 2
D02 Y017, Ireland
8 MARKETING AUTHORISATION NUMBER(S)
PLGB 51704/0003
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
17/09/2026
10 DATE OF REVISION OF THE TEXT
17/09/2026