

Summary of Product Characteristics (SmPC) - Trodelvy 180 mg powder for concentrate for solution for infusion
1 NAME OF THE MEDICINAL PRODUCT
Trodelvy 180 mg powder for concentrate for solution for infusion
2. QUALITATIVE AND QUANTITATIVE COMPOSITION
Each vial contains 180 mg sacituzumab govitecan. After reconstitution, one mL of solution contains 10 mg sacituzumab govitecan.
Sacituzumab is produced in Sp2/0-Ag14 cells by recombinant DNA technology.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Powder for concentrate for solution for infusion (powder for concentrate).
Off-white to yellowish lyophilized powder in a single-dose vial.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Triple-Negative Breast Cancer
TRODELVY is indicated:
- as monotherapy for the treatment of adult patients with unresectable locally advanced or metastatic triple-negative breast cancer (TNBC) who have not received prior systemic therapy for metastatic disease and who are not candidates for PD-1 or PD-L1 inhibitor therapy (see section 5.1).
- as monotherapy for the treatment of adult patients with unresectable locally advanced or metastatic TNBC who have received two or more prior systemic therapies, at least one of them given for unresectable locally advanced or metastatic disease (see section 5.1).
HR-Positive, HER2-Negative Breast Cancer
TRODELVY as monotherapy is indicated for the treatment of adult patients with unresectable or metastatic hormone receptor (HR)-positive, HER2-negative breast cancer who have received endocrine-based therapy, and at least two additional systemic therapies in the advanced setting (see section 5.1).
4.2 Posology and method of administration
TRODELVY must only be prescribed and administered to patients by healthcare professionals experienced in the use of anti-cancer therapies and should be administered in an environment where resuscitation facilities are available (see section 4.3 and 4.4).
Posology
The recommended dose of TRODELVY is 10 mg/kg administered as an intravenous infusion once weekly on Days 1 and 8 of 21-day treatment cycles. Continue treatment until disease progression or unacceptable toxicity.
Premedication
Prior to each dose of TRODELVY, premedication for prevention of infusion reactions and prevention of chemotherapy-induced nausea and vomiting (CINV) is recommended:
- Premedicate with antipyretics, and H1 and H2 blockers prior to infusion, and corticosteroids may be used for patients who had prior infusion reactions.
- Premedicate with a two or three drug combination regimen (e.g., dexamethasone with either a 5-HT3 receptor antagonist or an NK1 receptor antagonist, as well as other drugs as indicated).
Prophylaxis for Neutropenia
Primary prophylaxis with granulocyte colony-stimulating factor (G-CSF) should be considered starting in the first cycle in patients at increased risk of febrile neutropenia (see section 4.4 and 4.8).
Dose modifications for adverse reactions
Management of adverse reactions may require temporary interruption, dose reduction, or treatment discontinuation of TRODELVY. The recommended dosage reduction schedule is presented in Table 1 and the recommended dosage modifications for adverse reactions are provided in Table 2. The TRODELVY dose should not be re-escalated after a dose reduction for adverse reactions has been made.
Table 1: Dosage Reduction Schedule
| Dose Reduction Schedule | Dose Level |
| Recommended starting dose | 10 mg/kg |
| First dose reduction | Reduce to 7.5 mg/kg |
| Second dose reduction | Reduce to 5 mg/kg |
| Requirement for further dose reduction | Discontinue treatment |
The recommended dosage modifications for adverse reactions are provided in Table
2.
Table 2: Recommended dose modifications for adverse reactions
| Adverse reactions | Severity | Dose Modification |
| Neutropenia |
|
|
| Nausea/Vomiting/ Diarrhoea |
|
|
| Infusion-Related Reaction |
|
|
|
| |
| Other Toxicities |
|
|
Special populations
Elderly
No dose adjustment is required in patients > 65 years old. Data from TRODELVY in patients > 75 years are limited.
Hepatic impairment
No adjustment to the starting dose is required when administering TRODELVY to patients with mild hepatic impairment (see section 5.2)
The safety of TRODELVY in patients with moderate or severe hepatic impairment has not been established. TRODELVY has not been studied in patients with any of the following: serum bilirubin > 1.5 ULN, AST or ALT > 3 ULN in patients without liver metastases, or AST or ALT > 5 ULN in patients with liver metastases. The use of TRODELVY is not recommended in these patients.
Renal impairment
No adjustment to the starting dose is required when administering TRODELVY to patients with mild or moderate renal impairment. TRODELVY has not been studied in patients with severe renal impairment, or end-stage renal disease.
Paediatric population
The safety and efficacy of TRODELVY in children and adolescents aged below 18 years of age have not been established. No data are available.
Method of administration
TRODELVY should only be administered as an intravenous infusion, not as an intravenous push or bolus. It must be reconstituted and diluted by a healthcare professional experienced in the handling of anti-cancer therapies.
First infusion: the infusion should be administered over a period of 3 hours.
Subsequent infusions: the infusion should be administered over a period of 1 to 2 hours if prior infusions were tolerated.
Patients have to be observed during the infusion and for at least 30 minutes after each infusion, for signs or symptoms of infusion-related reactions.
For instructions on reconstitution and dilution of the medicinal product before administration, see section 6.6.
4.3 Contraindications
Hypersensitivity to the active substance, to any of the excipients listed in section 6.1, or to previous irinotecan therapy
4.4 Special warnings and precautions for use
Traceability
In order to improve the traceability of biological medicinal products, the name and the batch number of the administered product should be clearly recorded.
Neutropenia
TRODELVY can cause severe or life-threatening neutropenia. Fatal infections in the setting of neutropenia have been observed in clinical studies with TRODELVY, primarily in the first two cycles of treatment.
Primary prophylaxis with G-CSF should be considered starting in the first cycle of treatment in patients at increased risk of febrile neutropenia, e.g., older patients (in particular aged 65 years and older), patients with previous neutropenia, poor performance status, organ dysfunction (including renal, liver or cardiovascular dysfunction), or multiple comorbid conditions. Monitor ANC during treatment.
TRODELVY should not be administered if the ANC is below 1500/mm3 on Day 1 of any cycle or if the neutrophil count is below 1000/mm3 on Day 8 of any cycle. TRODELVY should not be administered in case of neutropenic fever. Dose reductions are required due to neutropenia or febrile neutropenia. Consider treating neutropenia with G-CSF and consider prophylaxis in subsequent cycles as clinically indicated (see section 4.2 and 4.8).
Diarrhoea
TRODELVY can cause severe diarrhoea. Diarrhoea in some cases was observed to have led to dehydration and subsequent acute kidney injury. TRODELVY should not be administered in case of Grade 3-4 diarrhoea at the time of scheduled treatment and treatment should only be continued when resolved to ≤ Grade 1 (see section 4.2).
Patients should be advised of the risk of diarrhoea and be closely monitored. Instruct patients to immediately contact their healthcare provider if they experience diarrhoea for the first-time during treatment.
At the onset of diarrhoea, and if no infectious cause can be identified, promptly initiate loperamide 4 mg initially followed by 2 mg with every episode of diarrhoea for a maximum of 16 mg daily. Discontinue loperamide 12 hours after diarrhoea resolves. In patients with infectious diarrhoea, initiate anti-infective treatment as clinically indicated. Additional supportive measures (e.g. fluid and electrolyte substitution) may also be employed as clinically indicated.
Instruct patients to immediately contact their healthcare provider if they experience melena, haematochezia, dehydration, an inability to tolerate oral fluids or an inability to manage diarrhoea within 24 hours.
Patients who exhibit an excessive cholinergic response to treatment with TRODELVY (e.g. abdominal cramping, diarrhoea, salivation, etc.) can receive appropriate premedication (e.g. atropine) for subsequent treatments.
Hypersensitivity
TRODELVY can cause severe and life-threatening hypersensitivity. Anaphylactic reactions have been observed in clinical studies with TRODELVY and the use of TRODELVY is contraindicated in patients with a known hypersensitivity to TRODELVY (see section 4.3). Other hypersensitivity events observed during and within 24 hours following the infusion included dyspnoea; rash; pruritus; hypotension; wheezing; oedema including facial and tongue; urticaria; and bronchospasm. Inform patients of the risk of serious infusion reactions and anaphylaxis. Instruct patients to immediately contact their healthcare provider if they experience these signs and symptoms. Medication to treat life-threatening hypersensitivity, as well as emergency equipment, should be available for immediate use.
Infusion-related reactions
Pre-infusion medication for patients receiving TRODELVY is recommended (see section 4.2). Patients should be closely observed for infusion-related reactions during each TRODELVY infusion and for at least 30 minutes after completion of each infusion. Medication to treat such reactions, as well as emergency equipment, should be available for immediate use. The infusion rate of TRODELVY should be slowed down or infusion interrupted if the patient develops an infusion-related reaction. TRODELVY should be permanently discontinued if life-threatening infusion-related reactions occur (see section 4.2).
Nausea and vomiting
TRODELVY is emetogenic. Premedication with a two or three drug combination regimen (e.g., dexamethasone with either a 5-HT3 receptor antagonist or an NK-1 receptor antagonist as well as other drugs as indicated) is recommended for prevention of chemotherapy-induced nausea and vomiting (CINV).
TRODELVY should not be administered in case of Grade 3 nausea or Grade 3-4 vomiting at the time of scheduled treatment administration and treatment should only be continued with additional supportive measures when resolved to ≤ Grade 1 (see section 4.2). Additional antiemetics and other supportive measures may also be employed as clinically indicated. All patients should be given take-home medications with clear instructions for prevention and treatment of nausea and vomiting.
Increased risk of adverse reactions in patients with reduced UGT1A1 activity Individuals who are homozygous for the uridine diphosphate-glucuronosyl transferase 1A1 (UGT1A1)*28 allele are at increased risk of severe neutropenia, severe diarrhoea, febrile neutropenia, and anaemia and are at increased risk for other adverse reactions following initiation of TRODELVY treatment (see section 4.8). A higher incidence of Grade 3-4 neutropenia, febrile neutropenia, and anaemia was observed in patients homozygous for the UGT1A1*28 allele and patients heterozygous for the UGT1A1*6 allele compared to patients homozygous for the wild-type allele. Patients with known reduced UGT1A1 activity should be closely monitored for adverse reactions. Withhold or permanently discontinue TRODELVY based on clinical assessment of the onset, duration and severity of the observed adverse reactions in patients with evidence of acute early-onset or unusually severe adverse reactions, which may indicate reduced UGT1A1 activity (see section 4.2).
4.5 Interaction with other medicinal products and other forms of interaction
No interaction studies have been performed. SN-38 (the small molecule moiety of sacituzumab govitecan) is primarily metabolised via UGT1A1. Inhibitors or inducers of UGT1A1 are expected to increase or decrease SN-38 exposure, respectively.
UGT1A1 inhibitors
Concomitant administration of TRODELVY with inhibitors of UGT1A1 may increase the incidence of adverse reactions due to potential increase in systemic exposure to SN-38. TRODELVY should be used with caution with UGT1A1 inhibitors (e.g. propofol, ketoconazole, EGFR tyrosine kinase inhibitors), and patients should be closely monitored.
UGT1A1 inducers
Exposure to SN-38 may be substantially reduced in patients concomitantly receiving UGT1A1 enzyme inducers. TRODELVY should be used with caution with UGT1A1 inducers (e.g. carbamazepine, phenytoin, rifampicin, protease inhibitors), and patients should be closely monitored.
Based on the limited data available from patients who received UGT1A1 inhibitors (n=15) or inducers (n=7) while being treated with TRODELVY, free SN-38 exposures in these patients were comparable to those in patients who did not receive UGT1A1 inhibitor or inducer.
CYP3A
SN-38 (the small molecule moiety of sacituzumab govitecan) is primarily metabolised via UGT1A1. Inhibitors or inducers of CYP3A are not anticipated to impact SN-38 exposure.
4.6 Fertility, Pregnancy and lactation
Pregnancy
Based on its mechanism of action, TRODELVY can cause teratogenicity and/or embryo-foetal lethality when administered during pregnancy. TRODELVY contains a genotoxic component, SN-38, and targets rapidly dividing cells. TRODELVY is not recommended during pregnancy. Advise female patients to contact their healthcare provider if they are pregnant or become pregnant. Inform female patients of the risk to the foetus and potential loss of the pregnancy.
Women of Childbearing Potential / Contraception in Males and Females Women of childbearing potential have to use effective contraception during treatment and for 6 months after the last dose. Male patients with female partners of childbearing potential have to use effective contraception during treatment with TRODELVY and for 3 months after the last dose. The pregnancy status of women of childbearing potential should be verified prior to the initiation of TRODELVY.
Breast-feeding
It is unknown whether TRODELVY or metabolites are excreted in human milk. Breast-feeding should be discontinued during treatment with TRODELVY and for 1 month after the last dose.
Fertility
Based on findings in animals, TRODELVY may impair fertility in females of reproductive potential.
4.7 Effects on ability to drive and use machines
TRODELVY has minor influence on the ability to drive and use machines. Dizziness has been reported. Advise patients to use caution when driving or using machines.
4.8 Undesirable effects
Summary of the safety profile
The frequencies of adverse reactions are based on pooled data from four clinical studies involving 963 patients who received TRODELVY 10 mg/kg for the treatment of metastatic TNBC and HR+/HER2- breast cancer. The median exposure to TRODELVY in this data set was 5.29 months.
The most common adverse drug reactions (ADRs) (reported at a frequency of ≥20%) with TRODELVY were neutropenia (67.3%), nausea (62.1%), diarrhoea (59.9%), fatigue (57.4%), alopecia (48.3%), anaemia (40.1%), constipation (36.7%), vomiting (31.3%), and decreased appetite (23.3%).
The most common Grade 3 or higher ADRs (reported at a frequency of ≥ 2%) were neutropenia (48.6%), diarrhoea (10.0%), leukopenia (9.6%), anaemia (7.7%), fatigue (5.8%), febrile neutropenia (5.6%), and lymphopenia (3.1%)..
The most common serious adverse reactions (reported at a frequency of ≥ 2%) were febrile neutropenia (4.5%), diarrhoea (3.7%), neutropenia (2.9%), and pneumonia (2.1%). Fatal adverse reactions occurred in 1.6% of patients who received TRODELVY.
The most common ADRs leading to treatment interruption (reported at a frequency of ≥ 2%) were neutropenia (44.0%), leukopenia (4.8%), anaemia (3.5%), diarrhoea (4.3%), COVID-19 (2.4%), fatigue (2.2%) and upper respiratory tract infection (2.1%).
The most common ADRs leading to dose reduction reported (at a frequency of ≥ 2%) were neutropenia (14.2%), diarrhoea (6.1%), fatigue (4.2%) and febrile neutropenia (2.7%).
The most common ADRs leading to treatment discontinuation (reported in >1 patient) were diarrhoea (0.4%), fatigue (0.4%), neutropenia (0.3%), pneumonia (0.3%), interstitial lung disease (0.3%), colitis (0.2%), neutropenic colitis (0.2%) and general physical health deterioration (0.2%).
Adverse reactions in patients with reduced UGT1A1 activity
The incidence of Grade 3-4 neutropenia was 59.6% in patients homozygous for the UGT1A1*28 allele, 50.7% in patients heterozygous for the UGT1A1*28 allele, and 44.9% in patients homozygous for the wild-type allele. The incidence of Grade 3-4 febrile neutropenia was 10.6% in patients homozygous for the UGT1A1*28 allele, 5.9% in patients heterozygous for the UGT1A1*28 allele, and 4.3% in patients homozygous for the wild-type allele. The incidence of Grade 3-4 anaemia was 10.6% in patients homozygous for the UGT1A1*28 allele, 6.4% in patients heterozygous for the UGT1A1*28 allele, and 6.3% in patients homozygous for the wild-type allele (See sections 4.2 and 4.4). For patients heterozygous for the UGT1A1*6 allele, the incidences of Grade 3-4 neutropenia, febrile neutropenia, and anaemia were 53.8%, 7.7%, and 7.7%, respectively.
Compared to patients homozygous for the wild-type allele, earlier median onset of neutropenia and
anaemia was observed in patients homozygous for the UGT1A1*28 allele and in patients heterozygous for the UGT1A1*28 allele.
Tabulated list of adverse reactions
Adverse reactions are classified by System Organ Class and sorted by frequencies calculated from all reported events, using the following convention: very common (≥ 1/10); common
(≥ 1/100 to < 1/10); uncommon (≥ 1/1,000 to < 1/100); rare (≥ 1/10,000 to < 1/1,000); very rare (< 1/10,000) or not known (cannot be estimated from available data). Within each frequency grouping, adverse reactions are presented in the order of decreasing seriousness.
Table 3: List of adverse reactions
| System organ class (SOC) | Frequency | Adverse reactions |
| Infections and infestations | ||
| Very common | Urinary tract infection Upper respiratory tract infection | |
| Common | Sepsis Pneumonia Influenza Bronchitis Nasopharyngitis Sinusitis Oral herpes | |
| Blood and lymphatic system disorders | ||
| Very common | Neutropenia1 Anaemia2 Leukopenia3 Lymphopenia4 | |
| Common | Febrile neutropenia Thrombocytopenia5 | |
| Immune system disorders | ||
| Very common | Hypersensitivity6 | |
| Metabolism and nutrition disorders | ||
| Very common | Decreased appetite Hypokalaemia Hypomagnesaemia | |
| Common | Dehydration Hyperglycaemia Hypophosphataemia Hypocalcaemia Hyponatraemia | |
| Psychiatric disorders | ||
| Common | Insomnia Anxiety | |
| Nervous system disorders | ||
| Very common | Headache Dizziness | |
| Common | Dysgeusia | |
| Vascular disorders | ||
| Common | Hypotension | |
| Respiratory, thoracic and mediastinal disorders | ||
| Very common | Dyspnoea7 Cough | |
| Common | Epistaxis Productive cough Rhinorrhoea Nasal congestion Upper airway cough syndrome | |
| Gastrointestinal disorders | ||
| Very common | Diarrhoea Vomiting Constipation Stomatitis Nausea Abdominal Pain | |
| Common | Neutropenic colitis8 Colitis Abdominal pain upper Dyspepsia Gastrooesophageal reflux disease Abdominal distension | |
| Uncommon | Enteritis | |
| Skin and subcutaneous tissue disorders | ||
| Very common | Alopecia Rash Pruritus | |
| Common | Rash maculopapular Skin hyperpigmentation Dermatitis acneiform Dry skin | |
| Musculoskeletal and connective tissue disorders | ||
| Very common | Back pain Arthralgia | |
| Common | Musculoskeletal chest pain Muscle spasms | |
| Renal and urinary disorders | ||
| Common | Haematuria Proteinuria Dysuria | |
| General disorders and administration site conditions | ||
| Very common | Fatigue9 | |
| Common | Pain Chills | |
| Investigations | ||
| Very common | Blood alkaline phosphatase increased | |
| Common | Weight decreased Activated partial thromboplastin time prolonged Blood lactate dehydrogenase increased | |
| Injury, poisoning and procedural complications | ||
| Common | Infusion related reaction | |
1: Includes the following preferred terms: neutropenia; neutrophil count decreased.
2: Includes the following preferred terms: anaemia; haemoglobin decreased; red blood cell count decreased. 3: Includes the following preferred terms: leukopenia; white blood cell count decreased. 4: Includes the following preferred terms: lymphopenia; lymphocyte count decreased. 5: Includes the following preferred terms: thrombocytopenia; platelet count decreased. 6: Hypersensitivity events reported up to the end of the day after treatment was administered. Includes events coded to the following preferred terms: rash, infusion related reaction, hypersensitivity, periorbital oedema, catheter site dermatitis, contrast media reaction, dermatitis allergic, dermatitis contact, eczema, rash erythematous, urticaria, anaphylactic reaction, bronchospasm, conjunctivitis allergic, dermatitis, dermatitis acneiform, dermatitis exfoliative generalised, drug hypersensitivity, infusion related hypersensitivity reaction, rash macular, rash maculo-papular, rash papular, rash pustular, rhinitis allergic, swelling face, swelling of eyelid, swollen tongue, Type IV hypersensitivity reaction, cough with pruritus, cough with rash, dyspnoea with pruritus, dyspnoea with rash, dyspnoea with wheezing and rash, hypotension with dyspnoea 7: Includes the following preferred terms: dyspnoea; dyspnoea exertional
8: Includes the preferred term of neutropenic colitis and events reported as typhlitis
9: Includes the following preferred terms: fatigue, asthenia
Description of selected adverse reactions
Neutropenia
Neutropenia occurred in 67.3% of patients treated with TRODELVY, including Grade 3-4 neutropenia in 48.6% of patients. Neutropenia was the reason for dose reduction in 14.2% of patients. Neutropenic colitis was observed in 1.3% of patients. Fatal infections secondary to neutropenia (including neutropenic colitis) occurred in 0.6% of patients.
Febrile neutropenia occurred in 5.6% of patients treated with TRODELVY. Febrile neutropenia was the reason for dose reduction in 2.7% of patients.
G-CSF was used beyond treatment cycle 1 in 48.4% of patients who received TRODELVY. G-CSF was used at any time during the study for prophylaxis for neutropenia by 32.7% of patients and/or treatment of neutropenia by 33.9% of patients.
The median time to onset of neutropenia (including febrile neutropenia) following the start of the first treatment cycle was 20 days and has occurred earlier in some patient populations (see Adverse reaction in patients with reduced UGT1A1 activity section). Neutropenia was reversible with a median duration of 10 days.
Of the patients homozygous for the UGT1A1*28 allele, the incidence of febrile neutropenia was 10.6%. No patients had febrile neutropenia leading to permanent discontinuation.
Diarrhoea
Diarrhoea occurred in 59.9% of patients treated with TRODELVY. Grade 3 events occurred in 10.0% of patients. Four of 963 patients (< 1%) discontinued treatment because of diarrhoea. The median time to onset of diarrhoea following the start of the first treatment cycle was 13 days. The median duration of diarrhoea was 7 days.
Hypersensitivity
Hypersensitivity reactions reported up to the end of the day following dosing occurred in 12.8% of patients treated with TRODELVY. Grade 3 and above hypersensitivity occurred in 0.5% of patients treated with TRODELVY. The incidence of hypersensitivity reactions leading to permanent discontinuation of TRODELVY was
- 0. 2%.
Nausea and vomiting
Nausea occurred in 62.1% of patients treated with TRODELVY, including Grade 3-4 nausea in 2.5%of patients. Vomiting occurred in 31.3% of patients treated with TRODELVY, including Grade 3-4 vomiting in 2.3% of patients.
Alopecia
Alopecia occurred in 48.3% of patients treated with TRODELVY.
Immunogenicity
As with all therapeutic proteins, there is potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies in the studies described below with the incidence of antibodies in other studies may be misleading.
Across clinical studies in patients treated with TRODELVY, 13 (1.2%) of 1058 patients developed antibodies to TRODELVY following administration; 10 of these patients (0.9% of all patients treated TRODELVY) had neutralizing antibodies against TRODELVY.
Special Populations
There was a higher discontinuation rate due to adverse reactions in patients aged 65 years or older (8%) compared with younger patients (4%) with metastatic breast cancer. Higher incidence rates of febrile neutropenia and severe diarrhoea were observed in patients aged 65 years or older. A higher incidence rate of fatal infections was observed in patients aged 65 years or older. There was a higher incidence rate of serious adverse events in patients aged 75 years or older (52%) compared to patients aged 65 years or older (35%) and patients younger than 65 years (25%) with metastatic breast cancer.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
There is no information on overdose with TRODELVY. In clinical trials, doses of up to 18 mg/kg (approximately 1.8 times the maximum recommended dose of 10 mg/kg) led to a higher incidence of severe neutropenia.
In case of overdose, patients should be closely monitored for signs or symptoms of adverse reactions, in particular severe neutropenia and severe diarrhoea, and appropriate treatment instituted.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: antineoplastic agents, monoclonal antibodies and antibody drug conjugates, other monoclonal antibodies, and antibody drug conjugates, ATC code: L01FX17
Mechanism of action
Sacituzumab govitecan is a Trop-2-directed antibody-drug conjugate. Sacituzumab is a humanised antibody that recognises Trop-2. The small molecule, SN-38, is a topoisomerase I inhibitor, which is covalently attached to the antibody by a linker. Sacituzumab govitecan binds to Trop-2-expressing tumour cells and is internalised with the subsequent release of SN-38 via hydrolysis of the linker. SN-38 interacts with topoisomerase I and prevents re-ligation of topoisomerase I-induced single strand breaks. The resulting DNA damage leads to apoptosis and cell death. Sacituzumab govitecan decreased tumour growth in mouse xenograft models of triple-negative breast cancer.
The TRODELVY exposure-response relationships and pharmacodynamic time course for efficacy have not been fully characterized.
Cardiac electrophysiology
The maximum mean change from baseline was 9.7 msec (the upper bound of the two-sided 90% confidence interval is 16.8 msec) at the recommended dose. A positive exposure-response relationship was observed between QTc increases and SN-38 concentrations.
Clinical efficacy and safety
Triple Negative Breast Cancer (TNBC)
Previously Untreated, Unresectable Locally Advanced or Metastatic TNBC in patients who are not candidates for PD-1/PD-L1 inhibitor therapy (ASCENT-03)
The efficacy of sacituzumab govitecan was evaluated in a multicentre, open-label, randomised study (ASCENT-03) conducted in 558 patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who had not received previous systemic therapy for advanced disease and who were not candidates for PD-1 or PD-L1 inhibitor therapy. The study enrolled patients with tumours that are PD-L1 negative (defined as having a tumour CPS < 10 using the IHC 22C3 assay), and patients with tumours that are PD-L1 positive (defined as having a CPS ≥ 10 using the IHC 22C3 assay) if they received a PD-1 or PD-L1 inhibitor in the (neo)adjuvant setting or if they had a comorbidity precluding treatment with PD-1 or PD-L1 inhibitor therapy.
Patients may have received chemotherapy with or without a PD-1 or PD-L1 inhibitor and/or radiotherapy in the early-stage of TNBC, however at least 6 months must have elapsed between the completion of systemic (neo) adjuvant breast cancer therapy or surgery, whichever occurred last, and first local or distant recurrence. No prior treatment with topoisomerase 1 inhibitors or antibody drug conjugates containing a topoisomerase inhibitor was allowed.
Patients were randomised (1:1) to receive sacituzumab govitecan 10 mg/kg as an intravenous infusion on Days 1 and 8 of a 21-day cycle (n=279) or Treatment of Physician’s Choice (TPC) (n=279). TPC was determined by the investigator before randomisation from one of the following regimens: gemcitabine and carboplatin, paclitaxel or nab-paclitaxel. Randomisation was stratified by de novo vs recurrent disease within 6 to 12 months from completion of treatment in the curative setting versus recurrent disease > 12 months from completion of treatment in the curative setting, and by geographic region (United States, Canada, Western Europe vs. Rest of World).
Patients were treated until BICR-verified disease progression, unacceptable toxicity, death, or consent withdrawal. Tumour imaging was obtained every 6 weeks for the first year followed by every 12 weeks thereafter. Following BICR-verified objective disease progression and study treatment discontinuation, patients who were randomised to TPC chemotherapy were able to receive SG supplied on trial in the crossover phase of this study if eligible.
The primary efficacy outcome was progression-free survival (PFS) by BICR per RECIST v1.1. Additional efficacy outcomes measures included overall survival (OS) and objective response rate (ORR) by BICR.
The median age of the study population was 55 years (range: 23-86 years), and 26% of patients were 65 years or over; 99.5% of patients were female. The majority of patients were White (64%); 23% were Asian, 3% were Black, and 4% were other race. Thirty-one percent (31%) of patients had de novo disease, 21% of patients had recurrent disease with a disease-free interval (DFI) 6 to 12 months and 48% of patients with DFI > 12 months. Ninety-nine point five percent (99.5%) of patients enrolled had tumours that were PD-L1 negative and 0.5% of patients had tumours that were PD-L1 positive. At study entry, all patients had an ECOG performance status of 0 (66%) or 1 (34%). The majority of patients (97.8%) had metastatic disease at screening; brain metastases were observed in 5% of patients. BRCA 1/2 mutation status was known for 76% of participants, out of which 18% of tested study participants had positive BRCA mutations.
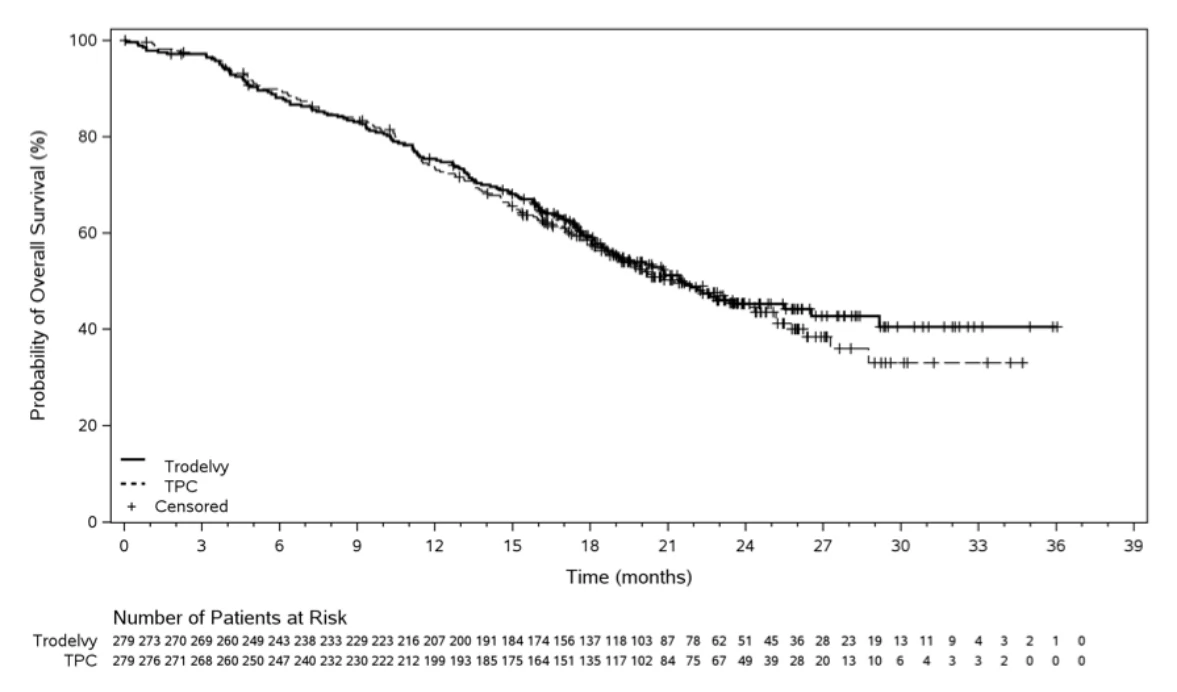
Sacituzumab govitecan demonstrated a statistically significant improvement in PFS versus TPC by BICR. At the time of the first interim OS analysis, patients had a median follow-up of 17.7 months.
Efficacy results are summarized in Table 4, Figure 1 and Figure 2.
Table 4. Efficacy endpoints (ASCENT-03)
TRODELVY N=279 | TPC N=279 | |
| Progression-Free Survival by BICR1 | ||
| Number (%) of patients with events | 161 (58%) | 188 (67%) |
| Median PFS in months (95% CI) | 9.7 (8.1, 11.1) | 6.9 (5.6, 8.2) |
| Hazard ratio (95% CI)2 | 0.62 (0.50, 0.77) | |
| p-value3 | < 0.0001 | |
| Objective Response Rate by BICR1 | ||
| ORR, (95% CI)4 | 48% (42%, 54%) | 46% (40%, 52%) |
| Overall Survival5 | ||
| Number (%) of patients with events | 139 (50%) | 144 (52%) |
| Median OS in months (95% CI) | 21.5 (18.9, 26.5) | 21.3 (18.7, 25.2) |
| Hazard ratio (95% CI)2 | 0.95 (0.75, 1.20) | |
- 1. Based on PFS primary analysis (data cut-off 2 April 2025) with median follow-up time 13.2 months.
- 2. Hazard ratio with 95% CIs based on the stratified Cox proportional hazards model adjusted for randomisation stratification factors: disease stratification (de novo vs recurrent disease within 6 to 12 months vs recurrent disease occurring > 12 months from completion of treatment in the curative setting) and geographic region (US/Canada/Western Europe vs rest of the world).
- 3. 2-sided p-value based on log-rank test adjusted for randomisation stratification factors: disease stratification (de novo vs recurrent disease within 6 to 12 months vs recurrent disease occurring > 12 months from completion of treatment in the curative setting) and geographic region (US/Canada/Western Europe vs rest of the world)
- 4. The 95% CI is based on the Clopper-Pearson exact method.
- 5. Based on first interim OS analysis (data cut-off 27 October 2025) with median follow-up time 17.7 months
BICR = Blinded Independent Central Review; CI = Confidence Interval
TPC = gemcitabine and carboplatin, paclitaxel, or nab-paclitaxel
Figure 1: Progression free survival by BICR in ASCENT-03 (data cut-off date 2 April
2025)
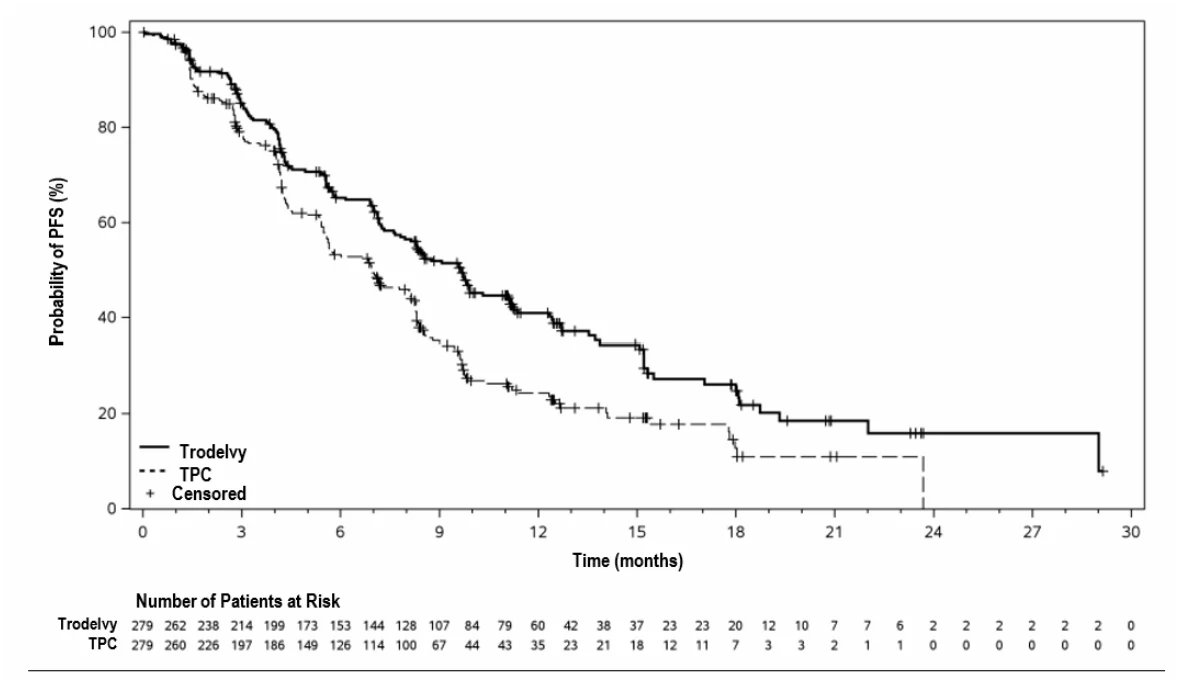
Figure 2: Overall survival in ASCENT-03 (data cut-off date 27 Oct 2025)
Unresectable or metastatic Triple Negative Breast Cancer
The efficacy of TRODELVY in the treatment of adult patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who have received at least two prior lines of chemotherapies was evaluated in two studies: ASCENT (IMMU-132-05) and IMMU-132-01.
ASCENT (IMMU-132-05)
ASCENT was a multicentre, open-label, randomised Phase 3 study conducted in 529 patients with unresectable locally advanced or metastatic triple-negative breast cancer (mTNBC) who had relapsed after at least two prior lines of chemotherapies (one of which could be in the neoadjuvant or adjuvant setting provided progression occurred within a 12 month period. All patients received previous taxane treatment in either the adjuvant, neoadjuvant, or advanced stage unless there was a contraindication or intolerance to taxanes during or at the end of the first taxane cycle. Poly-ADP ribose polymerase (PARP) inhibitors were allowed as one of the two prior chemotherapies for patients with a documented germline BRCA1/BRCA2 mutation.
Patients with brain metastases had to have stable disease for at least 4 weeks, and were allowed to enrol up to a pre-defined maximum of 15% of the trial population. Of the 529 patients randomised, 61 patients had brain metastases, 468 patients did not have brain metastases. Patients with Gilbert’s disease, chronic inflammatory bowel disease/bowel obstruction, ECOG performance status 2 or higher, bone-only disease, or who had received live attenuated vaccine within 30 days before the start of TRODELVY, or who were pregnant, or breastfeeding were excluded.
Patients were randomised 1:1 to receive TRODELVY 10 mg/kg as a slow intravenous infusion on Days 1 and 8 of a 21-day treatment cycle (n = 267) or physician’s choice of single-agent chemotherapy as per approved labelling (TPC, n = 262). Single-agent chemotherapy was determined by the investigator before randomisation from one of the following regimens: eribulin (n = 139), capecitabine (n = 33), gemcitabine (n = 38), or vinorelbine (n = 52).
Prior to the administration of TRODELVY, all patients were given pre-medication for prevention of chemotherapy-induced nausea and vomiting (e.g. dexamethasone with either a 5-HT3 receptor antagonist or a NK1 receptor antagonist and other drugs as indicated). Premedication, with antipyretics, H1 and H2 blockers, or corticosteroids (50 mg hydrocortisone or equivalent orally or IV), was strongly recommended to prevent infusion reactions with TRODELVY. All patients were given additional medications for prevention and treatment of nausea, vomiting, and diarrhoea for use at home.
Patients were treated until disease progression or unacceptable toxicity. The primary efficacy endpoint was PFS in patients without brain metastases at baseline (i.e. BMNeg) as measured by a BICR using RECIST v1.1 criteria. Key secondary efficacy endpoints included overall survival (OS), objective response rate (ORR) and duration of response (DOR) in BMNeg patients, and PFS and OS for the full population (including all patients with and without brain metastases).
The primary analysis included 235 BMNeg patients in the TRODELVY group and 233 BMNeg patients in the TPC group. The demographics of the BMNeg population were: median age of 54 years (range: 27–82 years) with 81% < 65 years; ECOG performance status of 0 (44%) or 1 (57%); 99.6% female; 78.8% White; 12% Black/African American. The baseline disease characteristics were: 42.5% had hepatic metastases; 7.3% were BRCA1/BRCA2 mutational status positive; 70.5% had previously received 2 to 3 prior systemic therapies. Overall, 27.1% of patients had received prior PD-1 or PD-L1 therapy. The median number of prior systemic therapies was 4.0 (range: 2 – 17). Thirteen percent of patients in the TRODELVY group in the full population received only 1 prior line of systemic therapy in the metastatic setting.
The efficacy results in the BMNeg population are summarised in Table 5, Figure 3, and Figure 4.
Table 5: Efficacy Endpoints (Brain Metastases-Negative Population) from ASCENT
TRODELVY n = 235 | Treatment of Physician’s Choice (TPC) n = 233 | p- value*** | Hazard Ratio (HR) or Odds Ratio (OR) (95% CI) *** | |
Median Progression-free Survival (PFS)*, ** Months (95% CI) | 5.6 (4.3-6.3) | 1.7 (1.5-2.6) | < 0.0001 | HR: 0.41 (0.32-0.52) |
Median Overall Survival Months (95% CI)** | 12.1 (10.7- 14.0) | 6.7 (5.8-7.7) | < 0.0001 | HR: 0.48 (0.38-0.59) |
| Objective Response Rate; n (%) | 82 (35%) | 11 (5%) | < 0.0001 | OR: 10.86 (5.59-21.10) |
Median Duration of Response Months (95% CI) | 6.3 (5.5-9.0) | 3.6 (2.8-NE) | - | - |
* PFS is defined as the time from the date of randomization to the date of the first radiological disease progression or death due to any cause, whichever comes first. ** Controlled for multiplicity statistical testing
*** For PFS and OS, P-values are based on stratified log-rank test; and HRs are from stratified Cox regression adjusted for stratification factors: number of prior chemotherapies (2-3 vs. >3), presence of known brain metastases at study entry (yes vs. no), and region (North America vs. rest of world). For ORR, P-value is based on Cochran–Mantel–Haenszel (CMH) test for common odds-ratio; and stratified odds-ratio is reported.
Figure 3: Progression Free Survival by BICR (Brain Metastases-Negative Population) in
ASCENT 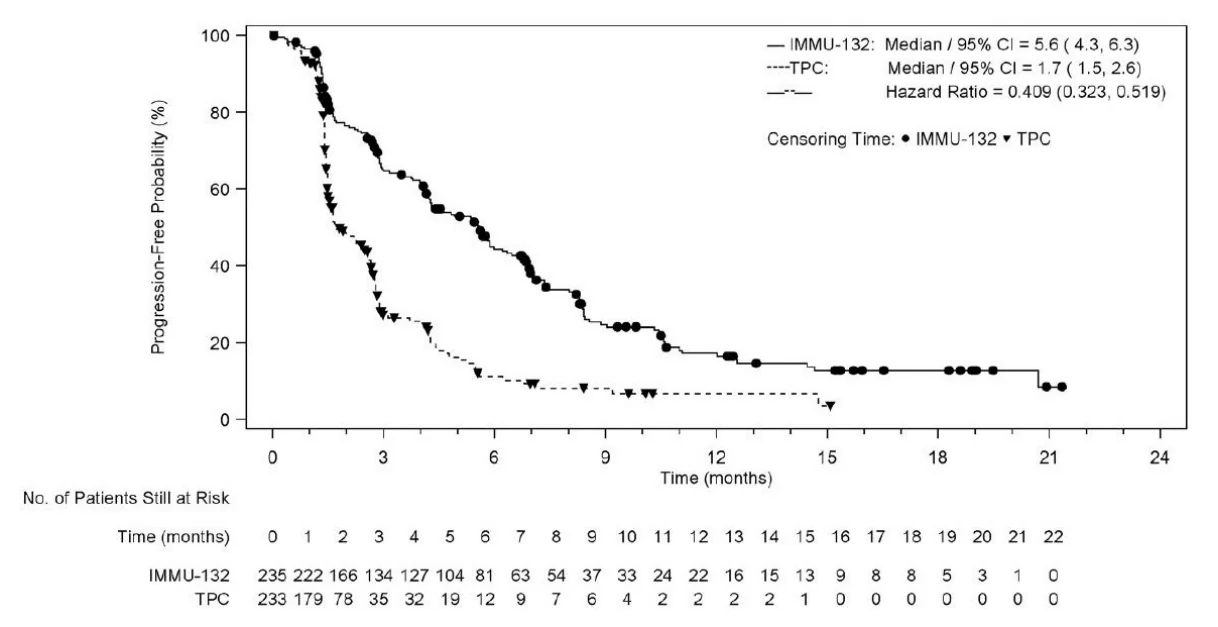
Figure 4: Overall Survival (Brain Metastases Negative Population) from in ASCENT
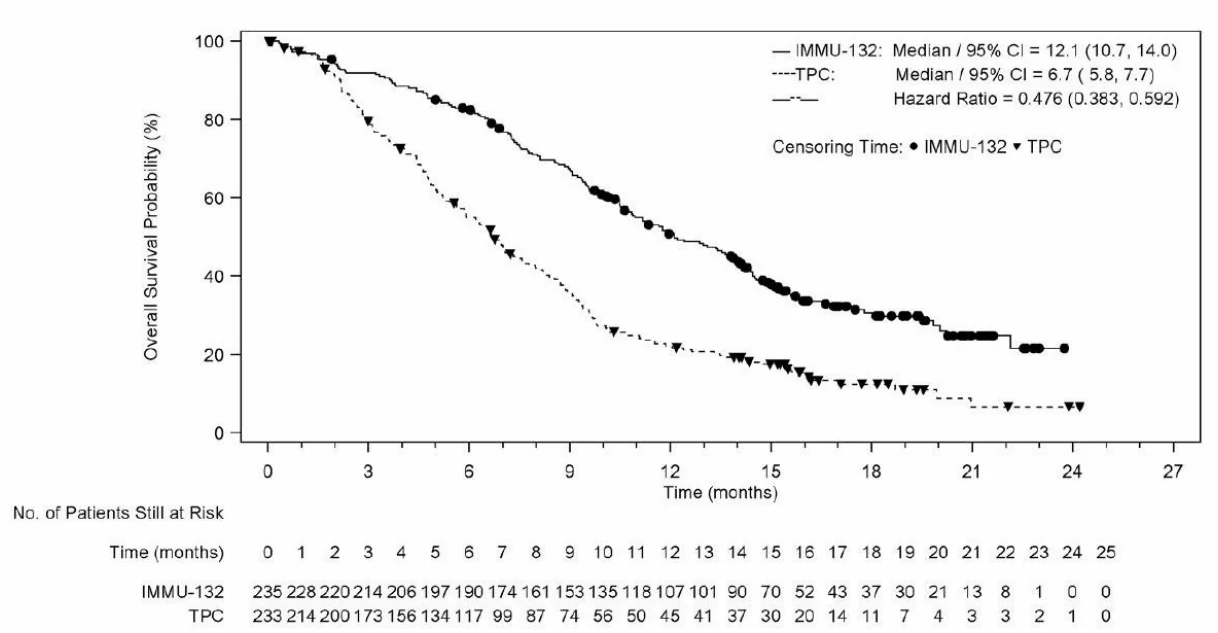
The analysis of the overall population included 267 patients in the TRODELVY group (235BMNeg patients and 32 patients with brain metastases) and 262 patients in the TPC group (233 BMNeg patients and 29 patients with brain metastases. The demographics and baseline characteristics of the BMNeg patients and overall population were similar.
The efficacy results in the overall population were consistent with the BMNeg population. Analyses of PFS (HR=0.43; 95% CI: 0.35, 0.54) and OS (HR=0.51; 95% CI: 0.41, 0.62) for the overall population were in favour of the TRODELVY arm.
In study IMMU-132-05, a generally consistent treatment effect of TRODELVY compared to TPC was seen in all pre-specified subgroups evaluated in favour of the TRODELVY arm. Efficacy results for the subgroup of patients who had received only 1 prior line of systemic therapy in the metastatic setting (in addition to having disease recurrence or progression within 12 months of neoadjuvant/adjuvant systemic therapy) were consistent with those who had received at least two prior lines in the metastatic setting.
An exploratory analysis of PFS in 61 patients with previously treated, stable brain metastases showed a stratified HR of 0.65 (95% CI: 0.35, 1.22). The median PFS in the TRODELVY arm was 2.8 months (95% CI: 1.5, 3.9) and the median PFS with single agent chemotherapy was 1.6 months (95% CI: 1.3, 2.9). Exploratory OS analysis in the same population showed a stratified HR of 0.87 (95% CI: 0.47, 1.63). The median OS in the TRODELVY arm was 6.8 months (95% CI: 4.7, 14.1) and the median OS with single agent chemotherapy was 7.5 months (95% CI: 4.7, 11.1).
IMMU-132-01
IMMU-132-01 (NCT01631552) was a multicentre, single-arm, clinical study that enrolled 108 patients with metastatic triple-negative breast cancer (mTNBC) who had received at least two prior treatments for metastatic disease. Patients with bulky disease, defined as a mass > 7 cm, were not eligible. Patients with treated brain metastases not receiving high dose steroids (> 20 mg prednisone or equivalent) for at least four weeks were eligible. Patients with known Gilbert’s disease were excluded.
Patients received TRODELVY 10 mg/kg intravenously on Days 1 and 8 of a 21-day treatment cycle. Patients were treated with TRODELVY until disease progression or intolerance to the therapy. Tumour imaging was obtained every 8 weeks, with confirmatory CT/MRI scans obtained 4-6 weeks after an initial partial or complete response, until progression requiring treatment discontinuation. Major efficacy outcome measures were investigator assessed overall response rate (ORR) using RECIST 1.1 and duration of response.
The median age was 55 years (range: 31-80 years); 82% of patients were younger than 65 years. The majority of patients were female (99%) and White (76%). At study entry, all patients had an ECOG performance status of 0 (29%) or 1 (71%). Seventy-six percent had visceral disease, 42% had hepatic metastases, 56% had lung/pleura metastases, and 2% had brain metastases. Fourteen patients (13%) had Stage IV disease at the time of initial diagnosis.
The median number of prior systemic therapies received in the metastatic setting was 3 (range: 2-10). Prior chemotherapies in the metastatic setting included carboplatin or cisplatin (69%), gemcitabine (55%), paclitaxel or docetaxel (53%), capecitabine (51%), eribulin (45%), doxorubicin (24%), vinorelbine (16%), cyclophosphamide (19%), and ixabepilone (8%).
Overall, 98% of patients had received prior taxanes and 86% had received prior anthracyclines either in the (neo)adjuvant or metastatic setting.
Table 6 summarises the efficacy results.
Table 6: Efficacy results for patients with mTNBC in IMMU-132-01
TRODELVY (N = 108) | |
| Overall Response Ratei | |
| ORR (95% CI) | 33.3% (24.6, 43.1) |
| Complete response | 2.8% |
| Partial response | 30.6% |
| Response durationi | |
| Number of responders | 36 |
| Median, Months (95% CI) | 7.7 (4.9, 10.8) |
| Range, Months | 1.9+, 30.4+ |
| % with duration ≥ 6 months | 55.6% |
| % with duration ≥ 12 months | 16.7% |
i investigator assessment CI: confidence interval +: denotes ongoing
HR-Positive, HER2-Negative Breast Cancer
Unresectable or metastatic HR-positive/ HER2-negative breast cancer (TROPiCS-02)
The efficacy of TRODELVY was evaluated in a multicentre, open-label, randomised study TROPiCS-02 (IMMU-132-09) conducted in 543 patients with unresectable locally advanced or metastatic HR-positive, HER2-negative (IHC 0, IHC 1+, or IHC 2+/ISH-) breast cancer whose disease has progressed after the following in any setting: a CDK 4/6 inhibitor, endocrine therapy, and a taxane; patients received at least two prior chemotherapies in the metastatic setting (one of which could be in the neoadjuvant or adjuvant setting if progression or recurrence occurred within 12 months of completion of the chemotherapy). Patients with bone-only disease, active chronic inflammatory bowel disease and known history of bowel obstruction, known history of unstable angina or myocardial infarction or congestive heart failure or active hepatitis B or C infection were excluded from the study.
Patients were randomised (1:1) to receive TRODELVY 10 mg/kg as an intravenous infusion on Days 1 and 8 of a 21-day cycle (n=272) or TPC (n=271). TPC was determined by the investigator before randomisation from one of the following single-agent regimens: eribulin (n=130), vinorelbine (n=63), gemcitabine (n=56), or capecitabine (n=22). Randomisation was stratified based on prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (yes vs. no), and endocrine therapy in the metastatic setting for at least 6 months (yes vs. no).
Patients were treated until disease progression or unacceptable toxicity. The primary efficacy outcome measure was PFS as determined by BICR per RECIST v1.1. Additional efficacy outcome measures were OS, ORR by BICR, and DOR by BICR.
The median age of the study population was 56 years (range: 27-86 years), and 26% of patients were 65 years or over. Almost all patients were female (99%). The majority of patients were White (67%); 4% were Black, 3% were Asian, and 26% were of unknown race. Patients received a median of 7 (range: 3 to 17) prior systemic regimens in any setting and 3 (range: 0 to 8) prior systemic chemotherapy regimens in the metastatic setting. Approximately 42% of patients had 2 prior chemotherapy regimens for metastatic disease compared to 58% of patients who had 3 to 4 prior chemotherapy regimens. Most patients received endocrine therapy in the metastatic setting for ≥ 6 months (86%). Patients had an ECOG performance status of 0 (44%) or 1 (56%). Ninety-five percent of patients had visceral metastases; 4.6% of patients had stable, pre-treated brain metastases.
TRODELVY demonstrated a statistically significant improvement in PFS by BICR and OS versus TPC. The improvement in PFS by BICR and OS was generally consistent across pre-specified subgroups. Efficacy results are summarized in Table 7.
Table 7. Efficacy endpoints – Pre-specified Final Analysis (TROPiCS-02)
TRODELVY n=272 | TPC n=271 | |
| Progression-Free Survival by BICR1 | ||
| Number of events (%) | 170 (62.5%) | 159 (58.7%) |
| Median PFS in months (95% CI) | 5.5 (4.2, 7.0) | 4.0 (3.1, 4.4) |
| Hazard ratio (95% CI) | 0.661 (0.529, 0.826) | |
| p-value2 | 0.0003 | |
| PFS rate at 12 months, % (95% CI) | 21.3 (15.2, 28.1) | 7.1 (2.8, 13.9) |
| Overall Survival3 | ||
| Number of events (%) | 191 (70.2%) | 199 (73.4%) |
| Median OS in months (95% CI) | 14.4 (13.0, 15.7) | 11.2 (10.1, 12.7) |
| Hazard ratio (95% CI) | 0.789 (0.646, 0.964) | |
| p-value2 | 0.0200 | |
| Objective Response Rate by BICR3 | ||
| Number of responders (%) | 57 (21.0%) | 38 (14.0%) |
| Odds ratio (95% CI) | 1.625 (1.034, 2.555) | |
| p-value | 0.0348 | |
1 PFS is defined as the time from the date of randomisation to the date of the first radiological disease progression or death due to any cause, whichever comes first (data cut-off 3 January 2022).
2 Stratified log-rank test adjusted for stratification factors: prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (yes vs. no), and endocrine therapy in the metastatic setting for at least 6 months (yes vs. no).
3 Based on second interim OS analysis (data cut-off 1 July 2022).
BICR = Blinded Independent Central Review; CI = Confidence Interval
In an updated efficacy analysis with a median duration of follow-up of 12.8 months (data cut-off 1 December 2022), results were consistent with the pre-specified final analysis. The median PFS by BICR was 5.5 months vs 4.0 months, in patients treated with TRODELVY and TPC, respectively (HR of 0.65; 95% CI: 0.53, 0.81). The median OS was 14.5 months vs 11.2 months, respectively (HR of 0.79; 95% CI: 0.65, 0.95). Kaplan-Meier curves for updated PFS by BICR and OS are presented in Figures 5 and 6.
Figure 5: Progression free survival by BICR (data cut-off 1 December 2022) in TROPiCS-
Figure 6: Overall Survival (data cut-off 1 December 2022) in TROPiCS-02 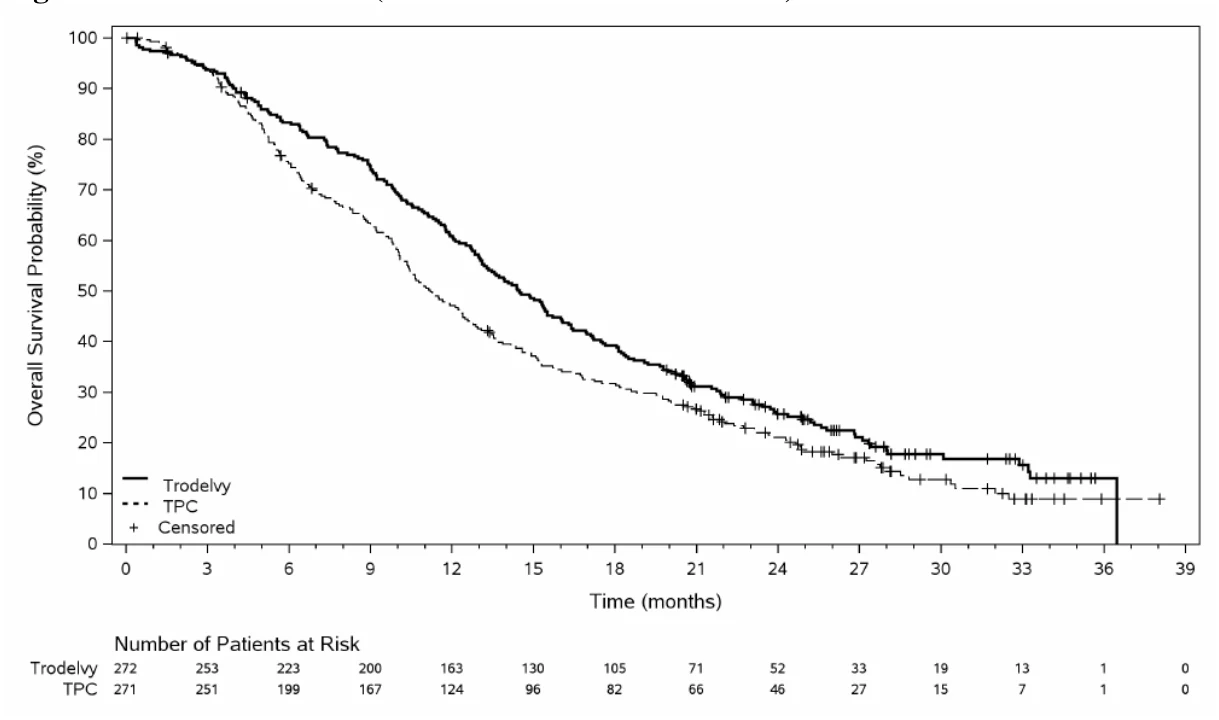
Paediatric population
The Medicines and Healthcare Regulatory Agency has waived the obligation to submit the results of studies with TRODELVY in all subsets of the paediatric population for the treatment of breast cancer (see section 4.2 for information on paediatric use).
5.2 Pharmacokinetic properties
The serum pharmacokinetics of sacituzumab govitecan and SN-38 were evaluated in patients with metastatic breast cancer (mBC) who received sacituzumab govitecan as a single agent at a dose of 10 mg/kg. The pharmacokinetic parameters of sacituzumab govitecan and free SN-38 are presented in Table 8.
Table 8: Summary of Mean PK Parameters (CV%) of Sacituzumab Govitecan and Free
SN-38
| Sacituzumab govitecan | Free SN-38 | |
| Cmax [ng/mL] | 257107 (17.9%) | 108.4 (39.4%) |
| AUC0-168 [ng*h/mL] | 12049500 (18.5%) | 3510.2 (62.6%) |
*Parameters estimated based on population PK analyses
Cmax: maximum serum concentration from 0-168 hours after the first dose
AUC0-168: area under serum concentration curve through 168 hours after the first dose
Distribution
Based on population pharmacokinetic analyses, the steady state volume of distribution of sacituzumab govitecan is 4.62 L.
Elimination
The median elimination half-life (t1/2) of sacituzumab govitecan and free SN-38, based on population pharmacokinetic analysis was 155 and 21.5 hours, respectively. The estimated mean (%CV) clearance of sacituzumab govitecan is 0.132 L/h (19.8%).
Metabolism
No metabolism studies with sacituzumab govitecan have been conducted. The glucuronide metabolite of SN-38 (SN-38G) was detectable in the serum of patients.
SN-38 (the small molecule moiety of sacituzumab govitecan) is metabolised via UGT1A1. Genetic variants of the UGT1A1 gene such as the UGT1A1*28 allele lead to reduced UGT1A1 enzyme activity. Individuals who are homozygous for the UGT1A1*28 allele are at increased risk for neutropenia, febrile neutropenia, and anaemia from TRODELVY (see sections 4.4 & 4.5). Approximately 20% of the Black or African American population, 10% of the White population, and 2% of the East Asian population are homozygous for the UGT1A1*28 allele. Approximately 0.2% of the Black population, 0.3% of the White population, and 27% of the East Asian population are heterozygous for the UGT1A1*6 allele. Decreased function alleles other than UGT1A1*28 and *6 may be present in certain populations.
Special Populations
Pharmacokinetic analyses in patients treated with TRODELVY did not identify an effect of age, race, and mild or moderate renal impairment on the pharmacokinetics of sacituzumab govitecan.
Renal impairment
Renal elimination is known to contribute minimally to the excretion of SN-38, the small molecule moiety of sacituzumab govitecan. There are no data on the pharmacokinetics of sacituzumab govitecan in patients with severe renal impairment or end-stage renal disease.
Hepatic impairment
The exposure of sacituzumab govitecan is similar in patients with mild hepatic impairment (bilirubin ≤ ULN and AST > ULN, or bilirubin > 1.0 to ≤ 1.5 ULN and AST of any level) to patients with normal hepatic function (bilirubin and AST ≤ ULN). There is limited data on sacituzumab govitecan and free SN-38 exposures in patients with moderate or severe hepatic impairment.
5.3 Preclinical safety data
Non-clinical data reveal no special hazard for humans based on conventional nonclinical safety studies. Effects in non-clinical studies were observed at levels considered sufficiently in excess of the maximum human exposure, those with possible relevance to clinical use were as follows.
SN-38 was clastogenic in an in vitro mammalian cell micronucleus test in Chinese hamster ovary cells and was not mutagenic in an in vitro bacterial reverse mutation (Ames) assay.
In a repeat-dose toxicity study in cynomolgus monkeys, intravenous administration of sacituzumab govitecan resulted in endometrial atrophy, uterine haemorrhage, increased follicular atresia of the ovary, and atrophy of vaginal epithelial cells at doses ≥ 60 mg/kg (1.9 times the human recommended dose of 10 mg/kg based on body weight allometric scaling).
No toxicity was attributed to the novel excipient, MES, upon evaluation in two in vitro cellular cytotoxicity assays either alone or in combination with sacituzumab govitecan at dose levels which exceed clinical exposure. In addition, the toxicity of MES was assessed in a mouse toxicity study and two repeat dose toxicity studies in monkeys. No adverse or toxicologically significant findings were observed for MES in repeat-dose toxicity studies at concentrations that exceeded clinical exposure.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
2-(N-morpholino) ethane sulfonic acid (MES)
Polysorbate 80
Trehalose dihydrate
6.2 Incompatibilities
This medicinal product must not be mixed with other medicinal products except those mentioned in section 6.6.
6.3 Shelf life
Unopened vial
36 months
After reconstitution
The infusion bag containing TRODELVY solution can be stored in a refrigerator at 2°C to 8°C for up to 24 hours protected from light.
6.4 Special precautions for storage
Store in a refrigerator (2°C-8°C).
Do not freeze.
Keep the vial in the outer carton in order to protect from light.
For storage conditions after reconstitution of the medicinal product, see section 6.3.
6.5 Nature and contents of container
Type 1 clear glass single-dose 50 mL vials, with a dark grey butyl rubber stopper and crimp-sealed with an aluminum flip-off cap.
Each pack contains one vial.
6.6 Special precautions for disposal and other handling
TRODELVY is a cytotoxic drug. Applicable special handling and disposal procedures have to be followed.
Reconstitution
- Calculate the required dose (mg) of TRODELVY based on the patient’s body weight.
- Using a sterile syringe, slowly inject 20 mL of sodium chloride 0.9% solution for injection, into each 180 mg TRODELVY vial. The resulting concentration will be 10 mg/mL.
- Gently swirl vials and allow to dissolve for up to 15 minutes. Do not shake. The product should be inspected visually for particulate matter and discoloration prior to administration. The solution should be free of visible particulates, clear and yellow. Do not use the reconstituted solution if it is cloudy or discoloured.
- Use immediately to prepare a diluted TRODELVY solution for infusion.
Dilution
- Calculate the required volume of the reconstituted TRODELVY solution needed to obtain the appropriate dose according to patient’s body weight. Withdraw this amount from the vial(s) using a syringe. Discard any unused portion remaining in the vial(s).
- Adjust the volume in the infusion bag as needed with sodium chloride 0.9% solution for injection, to obtain a concentration of 1.1 mg/mL to 3.4 mg/mL.
- Slowly inject the required volume of reconstituted TRODELVY solution into a polyvinyl chloride, polyolefin (polypropylene and/or polyethylene), or ethylene vinyl acetate infusion bag to minimise foaming. Do not shake the contents.
- Only sodium chloride 0.9% solution for injection should be used since the stability of the reconstituted product has not been determined with other infusion-based solutions. Use the diluted solution in the infusion bag immediately. If not used immediately, the infusion bag containing TRODELVY solution can be stored refrigerated at 2°C to 8°C for up to 24 hours protected from light. After refrigeration, administer diluted solution at room temperature up to 25°C within 8 hours (including infusion time).
Do not freeze or shake.
Administration
- Administer TRODELVY as an intravenous infusion. Protect infusion bag from light.
- An infusion pump may be used.
- Do not mix TRODELVY, or administer as an infusion, with other medicinal products.
- Upon completion of the infusion, flush the intravenous line with 20 mL sodium chloride 0.9% solution for injection.
Disposal
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Gilead Sciences Ltd
280 High Holborn
London
WC1V 7EE
United Kingdom
8 MARKETING AUTHORISATION NUMBER(S)
PLGB 11972/0050
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
08/09/2021
10 DATE OF REVISION OF THE TEXT
07/10/2026