

Summary of Product Characteristics (SmPC) - Tetrofosmin Rotop 0.23 mg kit for Radiopharmaceutical Preparation
1 NAME OF THE MEDICINAL PRODUCT
Tetrofosmin ROTOP 0.23 mg Kit for radiopharmaceutical preparation
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
The kit contains two different vials: Vial 1 and Vial 2.
Vial 1 contains 0.23 mg of tetrofosmin as tetrofosmin (bis)tetrafluoroborate.
Vial 2 contains 2.5 ml sodium hydrogen carbonate solution (0.2 M).
For the full list of excipients, see section 6.1.
The radionuclide is not part of the kit.
3 PHARMACEUTICAL FORM
Kit for radiopharmaceutical preparation.
Vial 1: white to off-white powder
Vial 2: clear, colourless solution
For radiolabelling with sodium pertechnetate (99mTc) solution
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
This medicinal product is for diagnostic use only. It is indicated for adults. For paediatric population see section 4.2.
After radiolabelling with sodium pertechnetate (99mTc) solution, the solution of technetium (99mTc) tetrofosmin obtained is indicated for:
Myocardial Imaging
Technetium (99mTc) tetrofosmin is a myocardial perfusion agent indicated as an adjunct in the diagnosis and localization of myocardial ischaemia and/ or infarction. In patients undergoing myocardial perfusion scintigraphy, ECG-gated SPECT can be used for assessment of left ventricular function (left ventricular ejection fraction and wall motion).
Breast Tumour Imaging
Technetium (99mTc) tetrofosmin is indicated as an adjunct to the initial assessments (e.g. palpation, mammography, or alternative imaging modalities and/or cytology) in the characterisation of malignancy of suspected breast lesions where all these other recommended tests were inconclusive.
4.2 Posology and method of administration
Adults and elderly population
Posology may vary depending on gamma camera characteristics and reconstruction modalities. The injection of activities greater than local DRLs (Diagnostic Reference Levels) should be justified.
The recommended activity range for intravenous administration to an adult patient of average weight (70 kg) is for:
Myocardial Imaging
For diagnosis and localization of myocardial ischaemia (using planar or SPECT techniques) and assessment of left ventricular function using ECG-gated SPECT, the usual procedure involves two intravenous injections of technetium (99mTc) tetrofosmin, one given at peak stress and one given at rest. The order of the two administrations can be either rest first and stress second or stress first and rest second.
When rest and stress injections are administered on the same day, the activity administered for the second dose should result in a myocardial count rate at least three times greater than that of the residual activity from the first dose. The recommended activity range for the first dose is 250 - 400 MBq; the recommended activity range for the second dose given at least 1 hour later, is 600 - 800 MBq. For studies employing ECG-gated SPECT, use of activities at the higher end of these ranges is warranted.
When rest and stress injections are administered on different days, the recommended activity range for each dose technetium (99mTc) tetrofosmin is 400 - 600 MBq. For studies on larger-sized individuals (e.g. those with abdominal obesity or women with large breasts) and for those employing ECG-gated SPECT, use of activities at the higher end of this range is warranted.
The total activity administered for stress and rest myocardial imaging studies, whether performed on one or two days, should be restricted to 1200 MBq. As an adjunct in the diagnosis and localization of myocardial infarction, one injection of technetium (99mTc) tetrofosmin (250 - 400 MBq) at rest is sufficient.
Breast Imaging
For the diagnosis and localization of suspected breast lesions, the recommended procedure involves a single intravenous injection of technetium (99mTc) tetrofosmin between 500 – 750 MBq. The injection should preferably be given in a foot vein or a site other than the arm on the side of the suspected breast lesion.
Renal impairment
Careful consideration of the activity to be administered is required since an increased radiation exposure is possible in these patients.
Hepatic impairment
In general, activity selection for patients with a decreased hepatic function should be cautious, usually starting at the low end of the dosing range. Paediatric population
The use in children and adolescents has to be considered carefully, based upon clinical needs and assessing the risk/benefit ratio in this patient group. The activities to be administered to children and adolescents may be calculated according to the recommendations of the European Association of Nuclear Medicine (EANM) paediatric dosage card; the activity administered to children and to adolescents may be calculated by multiplying a baseline activity (for calculation purposes) by the weight-dependent multiples given in the table below.
A [MBq] Administered = Baseline Activity × Multiple
The baseline activity is 63 MBq as a cancer seeking agent. For cardiac imaging, the minimum and maximum baseline activities are 42 and 63 MBq, respectively, for the two-day protocol cardiac scan both at rest and stress. For the one-day cardiac imaging protocol, the baseline activity is 28 MBq at rest and 84 MBq at stress. The minimum activity for any imaging study is 80 MBq.
| Weight [kg] | Multiple | Weight [kg] | Multiple | Weight [kg] | Multiple |
| 3 | 1 | 22 | 5.29 | 42 | 9.14 |
| 4 | 1.14 | 24 | 5.71 | 44 | 9.57 |
| 6 | 1.71 | 26 | 6.14 | 46 | 10.00 |
| 8 | 2.14 | 28 | 6.43 | 48 | 10.29 |
| 10 | 2.71 | 30 | 6.86 | 50 | 10.71 |
| 12 | 3.14 | 32 | 7.29 | 52-54 | 11.29 |
| 14 | 3.57 | 34 | 7.72 | 56-58 | 12.00 |
| 16 | 4.00 | 36 | 8.00 | 60-62 | 12.71 |
| 18 | 4.43 | 38 | 8.43 | 64-66 | 13.43 |
| 20 | 4.86 | 40 | 8.86 | 68 | 14.00 |
Image acquisition
Myocardial Imaging
Planar or preferably SPECT imaging should begin not earlier than 15 minutes post-injection.
There is no evidence for significant changes in myocardial concentration or redistribution of technetium (99mTc) tetrofosmin, therefore, images may be acquired up to at least four hours post-injection.
For planar imaging the standard views (anterior, LAO 40°- 45°, LAO 65°- 70° and/or left lateral) should be acquired.
Breast Imaging
Breast imaging is optimally initiated 5 – 10 minutes post injection with the patient in the prone position with the breast(s) freely pendant. A special imaging couch designed for nuclear medicine breast imaging is recommended. A lateral image of the breast suspected of containing lesions should be obtained with the camera face as close to the breast as is practicable. The patient should then be repositioned so that a lateral image of the pendant contralateral breast can be obtained. An anterior supine image may then be obtained with the patient’s arms behind her head.
For patient preparation, see section 4.4.
4.3 Contraindications
Hypersensitivity to the active substance, to any of the excipients listed in section 6.1 or to any of the components of the labelled radiopharmaceutical. Pregnancy (see section 4.6)
4.4 Special warnings and precautions for use
Potential for hypersensitivity or anaphylactic reactions
The possibility of hypersensitivity including anaphylactic/anaphylactoid reactions should always be considered. If hypersensitivity or anaphylactic reactions occur, the administration of the medicinal product must be discontinued immediately and intravenous treatment initiated, if necessary. To enable immediate action in emergencies, the necessary medicinal products and equipment such as endotracheal tube and ventilator must be immediately available.
Individual benefit/risk justification
For each patient, the radiation exposure must be justifiable by the likely benefit. The activity administered should in every case be as low as reasonably achievable to obtain the required diagnostic information.
Renal impairment and hepatic impairment
Careful consideration of the benefit risk ratio in these patients is required since an increased radiation exposure is possible.
Paediatric population
For information on the use in paediatric population, see section 4.2.
Patient preparation
The patient should be well hydrated before the start of the examination and urged to void as often as possible during the first hours after the examination in order to reduce radiation.
Myocardial Imaging
Patients should be requested to fast overnight or to have only a light breakfast on the morning of the procedure.
Breast Imaging
The patient does not need to fast before the injection.
Interpretation of technetium (99mTc) tetrofosmin images
Breast lesions less than 1 cm in diameter may not all be detected with scintimammography as the sensitivity of technetium (99mTc) tetrofosmin for the detection of these lesions is 36% relative to histological diagnosis. A negative examination does not exclude breast cancer especially in such a small lesion.
Efficacy in the identification of axillary lesions has not been proven, consequently scintimammography is not indicated for staging breast cancer.
Specific warnings
In myocardial scintigraphy investigations under stress conditions, the general contraindications and precautions associated with the induction of ergometric or pharmacological stress should be considered.
This medicinal product contains less than 1 mmol sodium (23 mg) per dose, i.e. essentially ‘sodium-free’.
Precautions with respect to environmental hazard see section 6.6.
4.5 Interaction with other medicinal products and other forms of interaction
No formal studies on the interaction of Tetrofosmin ROTOP with other drugs have been performed.
However, no interactions were reported in clinical studies in which technetium (99mTc) tetrofosmin was administered to patients receiving comedication. Drugs which influence myocardial function and/or blood flow, e.g. beta blockers, calcium antagonists or nitrates, can lead to false negative results in diagnosis of coronary artery disease. Therefore, the results of imaging studies should always be considered in the light of current medication.
4.6 Fertility, Pregnancy and lactation
Women of childbearing potential
When an administration of radiopharmaceuticals to a woman of childbearing potential is intended, it is important to determine whether or not she is pregnant. Any woman who has missed a period should be assumed to be pregnant until proven otherwise. If in doubt about her potential pregnancy (if the woman has missed a period, if the period is very irregular, etc.), alternative techniques not using ionising radiation (if there are any) should be offered to the patient.
Pregnancy
Tetrofosmin ROTOP is contraindicated in pregnancy (see section 4.3).
Animal reproductive toxicity studies have not been performed with this product. Radionuclide procedures carried out on pregnant women also involve radiation doses to the foetus. Administration of 250 MBq tetrofosmin (99mTc) at exercise, followed by 750 MBq at rest results in an absorbed dose to the uterus of 8.1 mGy. A radiation dose above 0.5 mGy (equivalent to the exposure from annual background radiation) would be regarded as a potential risk to the foetus.
Breast feeding
Before administering a radiopharmaceutical to a mother who is breast feeding, consideration should be given to the possibility of delaying the administration of a radionuclide until the mother has ceased breast feeding and to what is the most appropriate choice of radiopharmaceutical, bearing in mind the secretion of activity in breast milk.
It is not known whether technetium (99mTc) tetrofosmin is secreted in human milk, therefore, if administration is considered necessary, formula feeding should be substituted for breast feeding for at least 12 hours.
4.7 Effects on ability to drive and use machines
Effects on the ability to drive or use machines have not to be expected after use of this product.
4.8 Undesirable effects
The following undesirable effects are recognised for technetium (99mTc) tetrofosmin:
| System Organ Class | Very rare (less than 1 in 10,000) |
| Immune system disorders | Face oedema, hypersensitivity reaction, allergic reaction, anaphylactic reaction |
| Nervous system disorders | Headache, dizziness, taste metallic, disturbances of smell and taste |
| Vascular disorders | Flushing, hypotension |
| Respiratory, thoracic and mediastinal disorders | Dyspnoea |
| Gastrointestinal disorders | Vomiting, nausea, burning mouth |
| Skin and subcutaneous tissue disorder | Urticaria, itching, erythematous rash |
| General disorders and administration site condition | Feeling of warmth |
| Investigations | White blood cell count increased |
Some reactions were delayed by several hours following administration of technetium (99mTc) tetrofosmin. Isolated cases of serious reactions have been reported, including anaphylactic reaction (less than 1 in 100,000) and severe allergic reaction (single report).
Since the administered substance quantity is very low, the major risk is caused by the radiation. Exposure to ionising radiation is linked with cancer induction and a potential for developing hereditary defects.
As the effective dose is 7.3 mSv when the maximal recommended activity of 1200 MBq is administered these adverse reactions are expected to occur with a low probability.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system United Kingdom
Yellow Card Scheme
Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store
4.9 Overdose
In the event of administration of a radiation overdose with technetium (99mTc) tetrofosmin the absorbed dose to the patient should be reduced where possible by increasing the elimination of the radionuclide from the body by frequent micturition and defaecation. It might be helpful to estimate the effective dose that was applied.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: diagnostic radiopharmaceuticals, cardiovascular system, technetium (99mTc) tetrofosmin, ATC Code: V09GA02. Pharmacological effects are not expected following intravenous administration of technetium (99mTc) tetrofosmin at the recommended dosage. Studies in animals have shown that myocardial uptake of technetium (99mTc) tetrofosmin is linearly related to coronary blood flow, confirming the effectiveness of the complex as a myocardial perfusion imaging agent.
Based upon clinical experience with ECG-gated myocardial perfusion scintigraphy, this method can be used to monitor for changes (or stability) in left ventricular function over time. Reliability of such serial assessment is expected to be similar to that of other commonly used measurement techniques (e.g. ECG-gated blood-pool scintigraphy).
Limited data in animals show uptake of technetium (99mTc) tetrofosmin into breast tumour cells.
Clinical Efficacy
The diagnostic value of (99mTc) tetrofosmin has been studied in several trials. Myocardial perfusion scintigraphy:
In a multicenter study in 252 patients with suspected coronary artery disease, patients underwent exercise and rest imaging with Tc-99m tetrofosmin using two separate injections of the radiotracer 4 hours apart on the same day and planar images were obtained. Coronary angiography was used as standard of reference. Tc-99m tetrofosmin showed a sensitivity of 77 %, specificity of 58 %, positive predictive value of 89 % and negative predictive value of 37 %. Scintimammography:
In a prospective study with 137 patients presenting with suspicious lesions in mammography and/or high resolution ultrasound, sensitivity of Tc-99m tetrofosmin scintimammography was 90%, specificity 80%, positive predictive value 71% and negative predictive value 93% for planar imaging, and 93%, 76%, 68% and 95% for SPECT, respectively.
Paediatric population
Few reports are available about the use of Tc-99m in children, mostly in cardiac birth defects and Kawasaki disease. Proyo et al. presented a case study of a 14-year old boy for whom stress myocardial bridging was detectable in coronary angiography and confirmed by myocardial perfusion imaging with 430 MBq (99mTc)-Tetrofosmin at rest and under physical stress. The authors conclude that myocardial bridging is a rare and important differential diagnosis for angina-like pain in childhood without hypertrophic cardiomyopathy. Ekman-Joelsson et al reported results of myocardial perfusion scintigraphy performed with Tc-99m Tetrofosmin 4 to 15 years after surgery in 12 patients with pulmonary atresia showing perfusion defects in 9 of the 12 children. Mostafa et al. confirmed that Tc-99m tetrofosmin is an accurate non-invasive diagnostic technique for detecting myocardial perfusion defects in patients with Kawasaki disease, and pre- and post-coronary bypass grafting. Kashyap et al. assessed the feasibility and results of exercise myocardial perfusion scintigraphy with Tc-99m tetrofosmin or thallium-201 in 84 children with Kawasaki disease. The authors found reversible perfusion defects in 12 patients and concluded that that reversible perfusion defects are seen in asymptomatic patients with Kawasaki disease. Lim et al. studied the safety and utility of exercise myocardial perfusion stress testing with Tc-99m tetrofosmin in 11 children with a history of Kawasaki disease. There were no adverse events associated with radioisotope injection. Ten of 11 patients had normal tests. The single subject with an abnormal scan showed a minimal (2%) fixed defect in the left ventricular wall. The authors conclude that exercise myocardial perfusion stress is a safe and useful method for the assessment of myocardial perfusion in co-operative children with a history of Kawasaki disease and is a useful addition to conventional methods for coronary risk stratification in such patients. Fu et al. showed poor agreement between 2D-Echo and Tc-99m Tetrofosmin in 28 children as well as between dipyridamole stress Tc-99m tetrofosmin SPECT and coronary angiography in 29 children with Kawasaki disease.
In conclusion, Tc-99m tetrofosmin is used in selected indications in children and provides additional information which is complementary to other diagnostic methods. The potential benefit of Tc-99m tetrofosmin imaging in children should be carefully balanced against the potential risk of radiation exposure.
5.2 Pharmacokinetic properties
Organ uptake
Myocardial uptake is rapid, reaching a maximum of about 1.2% of injected dose with sufficient retention to allow imaging of the myocardium by planar or SPECT techniques from 15 minutes up to 4 hours post-administration.
Elimination
Technetium (99mTc) tetrofosmin is rapidly cleared from the blood after intravenous injection; less than 5% of the administered activity remains in whole blood at 10 minutes post-injection. Background tissue clearance is rapid from lung and liver and activity is reduced in these organs following exercise, with enhanced sequestration in skeletal muscle. Approximately 66% of the injected activity is excreted within 48 hours post-injection, with approximately 40% excreted in the urine and 26% in the faeces.
5.3 Preclinical safety data
Acute toxicity studies employing technetium (99mTc) tetrofosmin at dosage levels of approximately 1,050 times the maximum human single dose failed to reveal mortality or any significant signs of toxicity in rats or rabbits. In repeated dose studies some evidence of toxicity was observed in rabbits, but only at cumulative doses exceeding 10,000 times the maximum human single dose. In rats receiving these doses there was no significant evidence of toxicity. Studies on reproductive toxicity have not been conducted.
Tetrofosmin showed no evidence of mutagenic potential in vitro or in vivo mutagenicity studies. Studies to assess the carcinogenic potential of tetrofosmin have not been performed.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Vial 1:
Stannous chloride dihydrate
Disodium sulphosalicylate trihydrate
Sodium gluconate
Mannitol
Vial 2:
Sodium hydrogen carbonate
Water for injection
6.2 Incompatibilities
This medicinal product must not be mixed with other medicinal products except those mentioned in section 12.
6.3 Shelf life
The shelf life of the packaged product is 12 months.
After radiolabelling 12 hours when stored below 25 °C. Radiochemical in-use stability after radiolabelling has been demonstrated for one work-day. From a microbiological point of view, unless the method of radiolabelling and dilution precludes the risk of microbiological contamination, the product should be used immediately. If not used immediately, in-use storage times and conditions are the responsibility of the user.
6.4 Special precautions for storage
Store in a refrigerator at 2 °C – 8 °C.
Store in the original package in order to protect from light. For storage conditions after radiolabelling of the medicinal product, see section 6.3.
Storage of radiopharmaceuticals should be in accordance with national regulation on radioactive materials.
6.5 Nature and contents of container
Glass vials (Type I, Ph. Eur.) of 10 mL nominal capacity, closed with a synthetic rubber stopper and an aluminium cap with flip off seal. Tetrofosmin ROTOP is supplied as kit consisting of two vials which cannot be used separately.
Pack size: 2 Kits (Vial 1 and Vial 2)
5 Kits (Vial 1 and Vial 2)
6.6 Special precautions for disposal
The reconstituted and radiolabelled product is a clear colourless solution.
General warning
Radiopharmaceuticals should be received, used and administered only by authorised persons in designated clinical settings. Their receipt, storage, use, transfer and disposal are subject to the regulations and/or appropriate licences of the competent official organisation.
Radiopharmaceuticals should be prepared in a manner which satisfies both radiation safety and pharmaceutical quality requirements. Appropriate aseptic precautions should be taken.
Contents of the vial are intended only for use in the preparation of technetium (99mTc) tetrofosmin injection and are not to be administered directly to the patient without first undergoing the preparative procedure.
For instructions on reconstitution and radiolabelling of the medicinal product before administration, see section 12.
If at any time in the preparation of this product the integrity of this vial is compromised, it should not be used.
Administration procedures should be carried out in a way to minimise risk of contamination of the medicinal product and irradiation of the operators. Adequate shielding is mandatory.
The content of the kit before reconstitution and radiolabelling is not radioactive. However, after sodium pertechnetate (99mTc) (Ph. Eur.) is added, adequate shielding of the final preparation must be maintained.
The administration of radiopharmaceuticals creates risks for other persons from external radiation or contamination from spill of urine, vomiting etc. Radiation protection precautions in accordance with national regulations must therefore be taken.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
ROTOP Pharmaka GmbH
Bautzner Landstraße 400
01328 Dresden, Germany
Phone: +49 351 26 31 02 10
Fax: +49 351 26 31 03 13
e-mail: service@rotop-pharmaka.de
8 MARKETING AUTHORISATION NUMBER(S)
PL 45925/0004
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
23/03/2018 / 30/01/2024
10 DATE OF REVISION OF THE TEXT
08/07/2019
11 DOSIMETRY (IF APPLICABLE)
Technetium (99mTc) is produced by means of a (99Mo/99mTc) generator and decays with the emission of gamma radiation with a mean energy of 140 keV and a half-life of 6.02 hours to technetium (99Tc) which, in view of its long half-life of 2.13 x 10⁵ years, can be regarded as quasi stable.
The estimated absorbed radiation doses to an average adult patient (70 kg) from intravenous injections of technetium (99mTc) tetrofosmin according to ICRP 128 and Andersson et al. 2014 are listed in the tables below. For the calculation of effective doses to adults Andersson et al. used computational voxel phantoms and weighting factors from ICRP publications 110 and 103, respectively.
| Resting subject | Absorbed dose per unit activity administered (mGy/MBq) | ||||
| Organ | Adult | 15 Years | 10 Years | 5 Years | 1 Year |
| Adrenals | 0.0042 | 0.0053 | 0.0081 | 0.012 | 0.022 |
| Bladder | 0.017 | 0.022 | 0.032 | 0.042 | 0.056 |
| Bone surface | 0.0058 | 0.0069 | 0.01 | 0.015 | 0.027 |
| Brain | 0.0023 | 0.0029 | 0.0046 | 0.0074 | 0.013 |
| Breast | 0.002 | 0.0025 | 0.0037 | 0.0061 | 0.012 |
| Gallbladder wall | 0.036 | 0.041 | 0.053 | 0.093 | 0.3 |
| Gastrointestinal tract contents | |||||
| Stomach wall | 0.0045 | 0.006 | 0.0097 | 0.014 | 0.024 |
| Small intestine wall | 0.015 | 0.018 | 0.029 | 0.046 | 0.081 |
| Colon wall | 0.024 | 0.031 | 0.05 | 0.079 | 0.15 |
| Upper large intestine wall | 0.027 | 0.035 | 0.056 | 0.089 | 0.16 |
| Lower large intestine wall | 0.02 | 0.026 | 0.042 | 0.066 | 0.12 |
| Heart wall | 0.0047 | 0.0059 | 0.0089 | 0.013 | 0.023 |
| Kidneys | 0.013 | 0.016 | 0.022 | 0.032 | 0.055 |
| Liver | 0.004 | 0.005 | 0.0077 | 0.011 | 0.02 |
| Lungs | 0.0028 | 0.0037 | 0.0055 | 0.0085 | 0.016 |
| Muscles | 0.0033 | 0.0041 | 0.0062 | 0.0094 | 0.017 |
| Oesophagus | 0.0028 | 0.0036 | 0.0054 | 0.0085 | 0.016 |
| Ovaries | 0.0088 | 0.011 | 0.016 | 0.024 | 0.04 |
| Pancreas | 0.0049 | 0.0062 | 0.01 | 0.015 | 0.025 |
| Red marrow | 0.0038 | 0.0046 | 0.0068 | 0.0095 | 0.016 |
| Skin | 0.002 | 0.0024 | 0.0038 | 0.006 | 0.011 |
| Spleen | 0.0039 | 0.005 | 0.0078 | 0.0012 | 0.021 |
| Testes | 0.0031 | 0.0039 | 0.0062 | 0.0096 | 0.017 |
| Thymus | 0.0028 | 0.0036 | 0.0054 | 0.0085 | 0.016 |
| Thyroid | 0.0055 | 0.0082 | 0.013 | 0.026 | 0.047 |
| Urinary bladder wall | 0.017 | 0.022 | 0.032 | 0.042 | 0.056 |
| Uterus | 0.0078 | 0.0097 | 0.015 | 0.022 | 0.035 |
| Remaining organs | 0.0038 | 0.0049 | 0.0076 | 0.012 | 0.02 |
| Effective dose (mSv/MBq) | 0.0063 | 0.01 | 0.015 | 0.024 | 0.046 |
| Exercise | Absorbed dose per unit activity administered (mGy/MBq) | ||||
| Organ | Adult | 15 Years | 10 Years | 5 Years | 1 Year |
| Adrenals | 0.0044 | 0.0055 | 0.0083 | 0.012 | 0.022 |
| Bladder | 0.014 | 0.018 | 0.027 | 0.035 | 0.049 |
| Bone surface | 0.0063 | 0.0075 | 0.011 | 0.016 | 0.03 |
| Brain | 0.0027 | 0.0034 | 0.0055 | 0.0089 | 0.016 |
| Breast | 0.0023 | 0.0029 | 0.0043 | 0.0069 | 0.013 |
| Gallbladder wall | 0.027 | 0.032 | 0.042 | 0.073 | 0.23 |
| Gastrointestinal tract contents | |||||
| Stomach wall | 0.0046 | 0.0061 | 0.0098 | 0.014 | 0.024 |
| Small intestine wall | 0.011 | 0.014 | 0.022 | 0.034 | 0.062 |
| Colon wall | 0.018 | 0.022 | 0.037 | 0.058 | 0.11 |
| Upper large intestine wall | 0.02 | 0.025 | 0.041 | 0.065 | 0.12 |
| Lower large intestine wall | 0.015 | 0.019 | 0.032 | 0.049 | 0.092 |
| Heart wall | 0.0052 | 0.0065 | 0.0097 | 0.015 | 0.025 |
| Kidneys | 0.01 | 0.012 | 0.017 | 0.025 | 0.043 |
| Liver | 0.0033 | 0.0041 | 0.0063 | 0.0092 | 0.016 |
| Lungs | 0.0032 | 0.0042 | 0.0063 | 0.0096 | 0.017 |
| Muscles | 0.0035 | 0.0043 | 0.0065 | 0.0099 | 0.018 |
| Oesophagus | 0.0033 | 0.0042 | 0.0062 | 0.0096 | 0.017 |
| Ovaries | 0.0077 | 0.0096 | 0.014 | 0.021 | 0.036 |
| Pancreas | 0.005 | 0.0063 | 0.0098 | 0.015 | 0.025 |
| Red marrow | 0.0039 | 0.0047 | 0.0071 | 0.01 | 0.017 |
| Skin | 0.014 | 0.0027 | 0.0043 | 0.0068 | 0.013 |
| Spleen | 0.0041 | 0.0052 | 0.0082 | 0.012 | 0.022 |
| Testes | 0.0034 | 0.0043 | 0.0066 | 0.01 | 0.018 |
| Thymus | 0.0033 | 0.0042 | 0.0062 | 0.0096 | 0.017 |
| Thyroid | 0.0047 | 0.0068 | 0.011 | 0.02 | 0.037 |
| Urinary bladder wall | 0.014 | 0.018 | 0.027 | 0.035 | 0.049 |
| Uterus | 0.007 | 0.0087 | 0.013 | 0.02 | 0.32 |
| Remaining organs | 0.0038 | 0.0049 | 0.0075 | 0.012 | 0.02 |
| Effective dose (mSv/MBq) | 0.0058 | 0.0088 | 0.013 | 0.021 | 0.039 |
Cardiac imaging: Technetium (99mTc) tetrofosmin is administered as two intravenous injections either rest first and stress second or stress first and rest second. The recommended activity range for the first dose is 250 - 400 MBq; the recommended activity range for the second dose given at least 1 hour later, is 600 - 800 MBq.
The effective dose after administration of the maximum dose 800 MBq at rest is 5.0 mSv (per 70 kg adult patient) and 4.6 mSv at exercise.
If the maximum recommended activity of 1200 MBq is applied within 1 h an effective dose of 7.3 mSv has to be considered.
Breast imaging: The effective dose after administration of the maximum dose 750 MBq is 4.7 mSv (per 70 kg adult patient).
12 INSTRUCTIONS FOR PREPARATION OF
RADIOPHARMACEUTICALS (IF APPLICABLE)
Withdrawals should be performed under aseptic conditions. The vials must not be opened before disinfecting the stopper, the solution should be withdrawn via the stopper using a single dose syringe fitted with suitable protective shielding and a disposable sterile needle or using an authorised automated application system.
If the integrity of this vial is compromised, the product should not be used.
Procedure for the preparation of technetium (99mTc) tetrofosmin injection:
Tetrofosmin ROTOP is a two-vial kit.
Vial 1 contains a powder for intravenous use after reconstitution with 0.5 ml of Vial 2 and subsequent radiolabelling with sodium pertechnetate solution. Do not mix the order of Vial 2 and sodium pertechnetate solution as this will lead to decreased labelling efficiency.
Use aseptic technique throughout.
- Place Vial 1 in a suitable shielding container and sanitize the rubber septum of Vial 1 and Vial 2 with a suitable alcohol swab.
Use a syringe to transfer 0.5 ml of solution from Vial 2 to Vial 1. Withdraw
0.5 ml of nitrogen from Vial 1 before removing the needle. Shake the vial gently to dissolve the contents.
- Insert a needle (venting needle with suitable sterile filter) through the rubber septum of Vial 1.
- Inject sodium pertechnetate solution into Vial 1 using a syringe. Before removing the syringe from the vial, withdraw 5 ml of gas from above the solution. Remove the venting needle. Shake the vial to ensure complete dissolution of the powder (including upside-down motions).
- After 15 minutes reaction time, determine the total radioactivity and calculate the volume to be injected.
- If necessary, dilute with sterile isotonic saline up to final total volume of 10 ml. Shake again for good mixing. The radiolabelled preparation can be further diluted outside the original vial in a ratio of up to 1:10.
Note:
The volume of the pertechnetate solution must be in the range 3.5 – 5.5 ml.
The concentration of the pertechnetate solution must not exceed 2.2 GBq/ ml.
Do not skip the venting step as this might impair the radiochemical purity.
Do not use the kit if the radiochemical purity is less than 90 %.
The radiochemical purity generally increases within the first hours after radiolabelling and usually approaches 99 % after 6 hours.
Store the radiolabelled preparation below 25 °C and use it within 12 hours of preparation. Dispose any unused material and its container via an authorised route.
Properties of the product after radiolabelling:
Appearance: Clear to slightly opalescent, colourless, aqueous solution pH: 7.5-9.0
Quality control
Radiochemical purity should be checked according to one of the following procedures:
- 1. TLC
Chromatographic system:
(1) Glass microfiber chromatography paper impregnated with silicic acid (ITLC-SA) TLC strip (2 cm x 20 cm) – Do not heat activate
(2) Ascending chromatography tank and cover
(3) 65:35 % v/v acetone: dichloromethane mixture (prepared fresh daily) (4) 1 ml syringe with 22-25 G needle
(5) Suitable counting equipment
Method:
(1) Pour the 65 : 35 % v/v acetone : dichloromethane mixture into the
chromatography tank to a depth of 1 cm and cover the tank to allow the solvent vapour to equilibrate.
(2) Mark a glass microfiber chromatography paper impregnated with silicic acid
(ITLC-SA) TLC strip with a pencil line at 3 cm from the bottom and at 15 cm from the pencil line using an ink marker pen. The pencil line indicates the origin and movement of colour from the ink line will indicate the position of the solvent front when upward elution should be stopped.
(3) Cutting positions at 3.75 cm and 12 cm above the origin (Rf’s 0.25 and 0.8 respectively) should also be marked in pencil.
(4) Using a 1 ml syringe and needle, apply a 10 µl sample of the prepared injection at the origin of the strip. Do not allow the applied sample to come into contact with the pencil mark. Do not allow the spot to dry. Place the strip in the chromatography tank immediately and replace the cover.
Ensure that the strip is not adhering to the walls of the tank. Note: A 10 µl sample will produce a spot with a diameter of approximately 10 mm. Different sample volumes have been shown to give unreliable radiochemical purity values.
(5) When the solvent reaches the ink line, remove the strip from the tank and allow it to dry.
(6) Cut the strip into 3 pieces at the marked cutting positions and measure the activity on each using suitable counting equipment. Try to ensure similar counting geometry for each piece and minimize equipment dead time losses. (7) Calculate the radiochemical purity from:
Activity of centre piece Technetium (99mTc) tetrofosmin [%] = --------------------------------------- x 100 Total activity of all 3 pieces
Note: Free technetium (99mTc) pertechnetate runs to the top piece of the strip. Technetium (99mTc) tetrofosmin runs to the centre piece of the strip. Reduced hydrolysed- technetium (99mTc) and any hydrophilic complex impurities remain at the origin in the bottom piece of the strip.
Do not use the kit if the radiochemical purity is less than 90 %.
- 2. Simplified chromatographic procedure for rapid quality control
- a) Assay of technetium (99mTc) pertechnetate and other hydrophilic impurities
(impurity A) 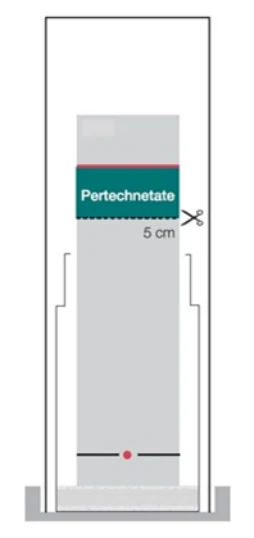
Chromatographic system:
TLC plate: ITLC-SA
Solvent: water
Sample: 1-2 µl
Running distance: 6-8 cm
Detector: a suitable detector
Detection by radio activity counters without special resolution: After development remove the strip from the chromatographic chamber, dry in air and cut it at the prescribed position. Measure radioactivity of
both parts separately. Relate activity of upper part to total activity.
Detection by radio-scanner:
After development remove the strip from the chromatographic chamber, dry in air and measure the activity distribution and display them in a chromatogram. Calculate the percentages of the single peaks. 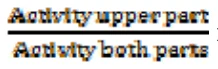
Impurity A [%] = × 100
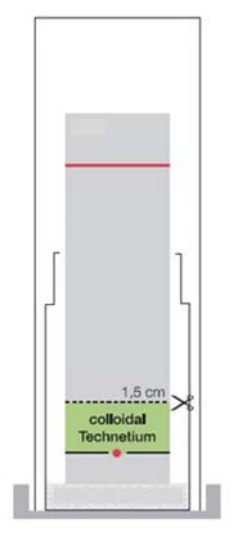
- b) Assay of technetium (99mTc) in colloidal form (impurity B)
Chromatographic system:
TLC plate: ITLC-SA
Solvent: water/acetonitrile/glacial acetic acid 1:1:2 Sample: 1-2 µl
Running distance: 6-8 cm
Detector: a suitable detector
Detection by radio activity counters without special resolution After development remove the strips from the chromatographic chamber, dry in air and cut it at the marked position. Measure radioactivity of both parts separately. Relate activity of the part with the starting point to total activity.
Detection by radio-scanner:
After development remove the strip from the chromatographic chamber, dry in air fix the strip on the support of the scanner. Measure the activity distribution and display them in a chromatogram. Calculate the percentages of the single peaks by peak integration.
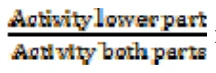
Impurity B [%] = × 100
- c) Calculate the radiochemical purity from:
Technetium (99mTc) tetrofosmin [%] = 100 % - (impurity A [%] + impurity B [%])