


Patient leaflet - NUMETA G16%E EMULSION FOR INFUSION
1. What Numeta G16%E is and what it is used for
Numeta G16%E is a specialised nutrition emulsion designed for full term newborns and children up to 2 years. It is given through a tube which is placed in your child’s vein, when your child is not able to eat all of his or her nutrition by mouth.
Numeta is presented in the form of a three chamber bag in which the separate chambers contain:
a 50 % glucose solution
a 5.9% paediatric amino acid solution, with electrolytes
a 12.5% lipid (fat) emulsion
Depending on your child’s needs, two or three of these solutions are mixed together in the bag before it is given to your child.
Numeta G16%E must only be used under medical supervision.
2. What you need to know before your child is given Numeta G16%E
Your child should not be given Numeta G16%E, in the following cases:
With 2 solutions mixed together in the bag (“2 in 1”):
- If your child is allergic to egg proteins, soya, peanuts or to any ingredient in the glucose or amino acids chamber (listed in section 6).
- If your child’s body has problems using building blocks of protein.
- If your child has high concentrations of any of the electrolytes included in Numeta G16%E in their blood.
- If your child is newborn (≤28 days of age), Numeta G16%E (or other calcium containing solutions) must not be given at the same time as ceftriaxone (an antibiotic), even if separate infusion lines are used. There is a risk of particle formation in the newborn´s bloodstream which may be fatal.
- If your child has hyperglycaemia (especially high levels of sugar in his/her blood).
With 3 solutions mixed together in the bag (“3 in 1”).
- All of the above situations mentioned for the “2 in 1” plus the following:
- If your child has especially high level of fats in his/her blood.
In all cases, your doctor will base their decision on whether your child should receive this medicine on factors such as age, weight and clinical condition. Your doctor will also consider the results of any tests performed.
Warnings and precautions
Talk to your child’s doctor or nurse before they are given Numeta G16%E.
When used in neonates and children below 2 years, the solution (in bags and administration sets) should be protected from light exposure until administration is completed. Exposure of Numeta G16%E to ambient light, especially after admixtures with trace elements and/or vitamins, generates peroxides and other degradation products that can be reduced by protection from light exposure.
Allergic Reactions:
The infusion must be stopped immediately if any signs or symptoms of an allergic reaction (such as fever, sweating, shivering, headache, skin rashes, or difficulty breathing) develop. This medicinal product contains soybean oil, which may rarely cause hypersensitivity reactions. Uncommonly, it has been observed that some people who are allergic to peanut proteins are also allergic to soybean proteins.
Numeta G16%E contains glucose produced from cornstarch. Therefore, Numeta G16%E should be used with caution in patients with known allergy to corn or corn products.
Risk of particle formation with ceftriaxone (antibiotic):
A certain antibiotic named ceftriaxone must not be mixed or given simultaneously with any calcium containing solutions (including Numeta G16%E) given to you by a drip into your vein.
Your doctor knows this and will not give you them together even via different infusion lines or different infusion sites.
However, your doctor may give calcium and ceftriaxone sequentially one after another if infusion lines at different sites are used or if the infusion lines are replaced or were thoroughly flushed with physiological salt solution between the infusions to avoid precipitation.
Formation of small particles in blood vessels of the lungs:
Difficulty breathing could also be a sign that small particles have formed, blocking blood vessels in the lungs (pulmonary vascular precipitates). If your child experiences any difficulty breathing, tell your child’s doctor or nurse. They will decide of a course of action to be taken.
Infection and Sepsis:
Your doctor will carefully watch your child for any signs of infection. An “aseptic technique” (germ free technique) when placing and maintaining the catheter as well as when making the nutritional formula can reduce the risk of infection.
Occasionally, children can develop infection and sepsis (bacteria in the blood) when they have a tube in their vein (intravenous catheter). Certain medications and illnesses can increase the risk of developing infection or sepsis. Patients who require parenteral nutrition (giving nutrition through a tube in your child’s vein) can be more likely to develop infection from their medical conditions.
Fat overload syndrome:
Fat overload syndrome has been reported with similar products. A reduced or limited ability of the body to remove the fats contained in Numeta G16%E, or an overdose, may result in a "fat overload syndrome" (see section 3 and section 4).
Changes in blood chemistry levels:
Your doctor will check and monitor your child’s fluids, blood chemistries and other blood levels since occasionally, refeeding someone who is severely undernourished can result in changes in blood chemistry levels. Extra fluid in the tissues and swelling can also develop. It is recommended that parenteral nutrition is started slowly and carefully.
Elevated levels of Magnesium in blood
The amount of magnesium in Numeta G16%E, may cause elevated levels of magnesium in blood. The signs of this could include weakness, slow reflexes, nausea, vomiting, low calcium levels in blood, breathing difficulties, low blood pressure and irregular heartbeat. As these signs may be difficult to detect, your child´s blood values may be monitored by their doctor, in particular if your child has risk factors for elevated levels of magnesium in blood, including impaired renal function. If blood magnesium levels are elevated, the infusion will be stopped or reduced.
Monitoring and Adjustment:
Your doctor will be closely monitoring and adjusting Numeta G16%E to meet your child’s individual needs if they have the following conditions:
- severe post-traumatic conditions
- severe diabetes mellitus
- shock
- heart attack
- severe infection
- certain types of coma
Use with caution:
Numeta should be used with caution if your child has:
- pulmonary oedema (fluid in the lungs) or heart failure.
- severe liver problems.
- problems in using nutrients.
- high blood sugar.
- kidney problems.
- severe metabolic disorders (when the body cannot break down substances in a normal way).
- blood clotting disorders.
Your child´s fluid status, liver test values and/or blood values will be closely monitored.
Other medicines and Numeta G16%E
Tell your doctor if your child is taking or using, has recently taken or used or might take or use any other medicines.
Numeta must not be given at the same time as:
- ceftriaxone (an antibiotic) not even in separate infusion lines because of the risk of particle formation.
- blood through the same infusion tubing due to the risk of pseudoagglutination (red blood cells becoming stuck together in a stack).
- Ampicillin, fosphenytoin or furosemide through the same infusion line because of the risk of particle formation
Coumarin and warfarin (Anticoagulants):
Your doctor will carefully watch your child if they are taking coumarin or warfarin. Olive and soybean oil have a natural content of vitamin K1. Vitamin K1 may interfere with drugs such as coumarin and warfarin. These drugs are anticoagulants used to prevent clotting of the blood.
Laboratory tests:
The lipids contained in this emulsion may interfere with the results of certain laboratory tests. Laboratory tests may be performed after a period of 5 to 6 hours when no additional lipids are administered.
Interactions of Numeta G16%E on drugs that may affect potassium levels/metabolism:
Numeta contains potassium. High levels of blood potassium may cause abnormal heart rhythm. Special care should be taken in patients taking diuretics (drugs to reduce fluid retention) or ACE inhibitors (drugs for high blood pressure) or angiotensin II receptor antagonists (drugs for high blood pressure) or immunosuppressants (drugs that may lower the body’s normal immune defences). These types of drugs may increase potassium levels.
3. How Numeta G16%E is given
Your child should always be given Numeta G16%E exactly as the doctor has indicated. Check with your doctor if you are not sure.
Age groups
Numeta G16%E has been designed to meet the nutritional needs of full term newborns and children up to 2 years.
Your doctor will decide if this medicine is suitable for your child.
Administration
This medicine is an emulsion for infusion. It is given through a plastic tube in a vein in your child’s arm or in a large vein in your child’s chest.
Your child’s doctor may choose not to give lipids to your child. The design of the Numeta G16%E bag allows only the peel seal between the amino acids/electrolyte and glucose chambers to be broken if necessary. The peel seal between the amino acids and lipid chambers remains intact in this case. The content of the bag can then be infused without lipids.
When used in neonates and children below 2 years, the solution (in bags and administration sets) should be protected from light exposure until administration is completed (see section 2).
Dosage and duration of treatment
Your child’s doctor will decide the dose and for how long it will be given. The dosage depends on the nutrition needs of your child. The dosage will be based on your child’s weight, medical condition, and on their body’s ability to break down and use the ingredients in Numeta G16%E. Additional nutrition or proteins given orally/enterally may also be given.
If your child is given too much Numeta G16%E
Symptoms
Too much of this medicine, or giving it too quickly may result in the following:
- nausea (feeling sick)
- vomiting
- shivering
- electrolyte disturbances (improper amounts of electrolytes in the blood)
- signs of hypervolemia (increase of circulating blood volume)
- acidosis (increased acidity of the blood)
In such situations, the infusion must be stopped immediately. Your child’s doctor will decide if additional actions are required.
An overdose of fats contained in Numeta G16%E may result in a "fat overload syndrome", which is usually reversible after the infusion is stopped. In newborn babies (neonates) and young children (infants), the fat overload syndrome has been associated with breathing disorder leading to reduced oxygen in the body (respiratory distress) and conditions leading to an increased acidity of the blood (acidosis).
To prevent these events occurring, the doctor will regularly monitor your child’s condition and test their blood levels during treatment.
4. Possible side effects
Like all medicines, this medicine can cause side effects, although not every child gets them.
If you notice any changes in the way your child feels during or after the treatment, tell your doctor or nurse straight away.
The tests your doctor will perform while your child is taking the medicine should minimise the risk of side effects.
If signs of an allergic reaction occur, the infusion shall be stopped and a doctor contacted immediately. This can be serious and the signs may include:
- sweating
- shivering
- headache
- skin rashes
- breathing difficulties
Other side effects that have been noticed are:
Common: may affect up to 1 in 10 people
- Low phosphate level in the blood (hypophosphataemia)
- High sugar level in the blood (hyperglycaemia)
- High calcium level in the blood (hypercalcaemia)
- High triglycerides level in the blood (hypertriglyceridaemia)
- Electrolyte disturbance (hyponatraemia)
Uncommon: may affect up to 1 in 100 people
- High lipid level in the blood (hyperlipidaemia)
- Condition where bile cannot flow from the liver to the duodenum (cholestasis). The duodenum is a part of the intestines.
Not known: frequency cannot be estimated from the available data (These adverse reactions have been reported only for Numeta G13%E Preterm and G16%E when peripherally administered with insufficient dilution).
- Skin necrosis
- Soft tissue injury
- Extravasation
The following side effects have been reported with other products for parenteral nutrition:
The reduced or limited ability to remove the lipids contained in Numeta may result in a "fat overload syndrome”. The following signs and symptoms of this syndrome are usually reversible when the infusion of the lipid emulsion is stopped:
- Sudden and abrupt worsening of the patient’s medical condition
- High levels of fats in the blood (hyperlipidaemia)
- Fever
- Liver fatty infiltration (hepatomegaly)
- Worsening liver function
- Reduction in red blood cells which can make the skin pale and cause weakness or breathlessness (anaemia)
- Low white blood cell count, which can increase the risk of infection (leukopenia)
- Low platelet count which can increase the risk of bruising and/or bleeding (thrombocytopenia)
- Coagulation disorders which effect the ability of the blood to clot
- Breathing disorder leading to reduced oxygen in the body (respiratory distress)
- Conditions leading to an increased acidity of the blood (acidosis)
- Coma, requiring hospitalisation.
Formation of small particles which may lead to blockage of blood vessels in the lungs (pulmonary vascular precipitates) or difficulty breathing.
Reporting of side effects
If your child gets any side effects talk to your child’s doctor or nurse. This includes any possible side effects not listed in this leaflet.
You can also report side effects directly (see details below). By reporting side effects you can help provide more information on the safety of this medicine.
United Kingdom:
Via the Yellow Card Scheme:
www.mhra.gov.uk/yellowcard
Ireland:
HPRA Pharmacovigilance,
Earlsfort Terrace,
IRE - Dublin 2.
Tel: +353 1 6764971,
Fax: +353 1 6762517,
Website: www.hpra.ie;
E-mail: medsafety@hpra.ie
5. How to store Numeta G16%E
Keep this medicine out of the sight and reach of children when not being administered.
When used in neonates and children below 2 years, the solution (in bags and administration sets) should be protected from light exposure until administration is completed (see section 2).
Do not use this medicine after the expiry date which is stated on the bag and the outer packaging (MM/YYYY). The expiry date refers to the last day of that month.
Do not freeze.
Store in the overpouch.
Do not throw away any medicines via wastewater or household waste. Ask your pharmacist how to throw away medicines you no longer use. These measures will help protect the environment.
6. Contents of the pack and other information
What Numeta G16%E looks like and contents of the pack
Numeta is presented in the form of a triple-chamber bag. Each bag contains a sterile combination of a glucose solution, an amino acid solution for children, with electrolytes, and a lipid emulsion, as described below.
| Container size | 50% glucose solution | 5.9% amino acids solution with electrolytes | 12.5% lipid emulsion |
|---|---|---|---|
| 500 mL | 155 mL | 221 mL | 124 mL |
Appearance before reconstitution:
- The solutions in the amino acids and glucose chambers are clear, colorless or slightly yellow
- The lipid emulsion chamber is a uniform and milky-white liquid
Appearance after reconstitution:
- “2 in 1” solution for infusion is clear, colorless or slightly yellow
- “3 in 1” emulsion for infusion is uniform and milky-white
The three-compartment bag is a multi-layer plastic bag.
To prevent air contact, Numeta is packaged in an oxygen barrier overpouch that contains and oxygen absorber sachet and an oxygen indicator.
Pack sizes
500 mL bag: 6 units per cardboard box
1 bag of 500 mL
Not all pack sizes may be marketed.
Marketing Authorisation Holder and Manufacturer
Marketing Authorisation Holder
United Kingdom
Baxter Healthcare Ltd
Caxton Way, Thetford,
Norfolk, IP24 3SE
United Kingdom
Ireland
Baxter Holding B.V.
Kobaltweg 49,
3542CE Utrecht,
Netherlands
Manufacturer
BAXTER S.A.
BOULEVARD RENE BRANQUART, 80
7860 LESSINES
BELGIUM
This medicinal product is authorised in the Member States of the EEA under the following names:
Austria
Germany
Numeta G 16 % E Emulsion zur Infusion
Belgium
Luxembourg
NUMETZAH G16%E, émulsion pour perfusion
France
NUMETAH G16 %E émulsion pour perfusion
Denmark
Norway
Sweden
Numeta G16E
Czech Republic
Greece
NUMETA G 16 % E
Netherlands
NUMETA G16%E emulsie voor infusie
Ireland
United Kingdom
Numeta G16%E, Emulsion for Infusion
Italy
NUMETA G16%E emulsione per infusione
Finland
Numeta G16E infuusioneste, emulsio
Poland
NUMETA G 16 % E
Portugal
Numeta G16%E
Spain
NUMETA G16%E, emulsión para perfusión
This leaflet was last revised September 2025
The following information is intended for medical or healthcare professionals only*
*Please observe that in certain cases this product may be administered at home by parents or other caregivers. In such cases parents/caregivers should read the following information.
No additions to the bag should be made without first checking the compatibility. Formation of particles or breaking down of the lipid emulsion could result. This can lead to blockage of the blood vessels.
Numeta G16%E should be at room temperature before use.
Before taking Numeta G16%E, the bag will be prepared as shown below.
Confirm that the bag is not damaged. Use the bag only if it is not damaged. An undamaged bag looks like this:
- The non-permanent seals are intact. This is indicated by no mixture of any of the three chambers
- The amino acids solution and the glucose solution are clear, colorless, or slightly yellow without visible particles
- The lipid emulsion is a uniform liquid with a milky white appearance.
Before opening the overpouch, check the colour of the oxygen indicator.
- Compare it to the reference colour printed next to the OK symbol and shown in the printed area of the indicator label.
- Do not use the product if the colour of the oxygen indicator does not correspond to the reference color printed next to the OK symbol.
Figures 1 and 2 illustrate how to remove the protective overpouch. Discard the overpouch, oxygen indicator and oxygen absorber.
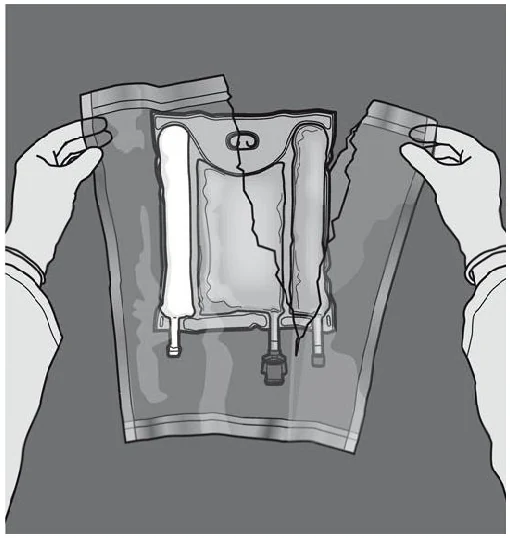
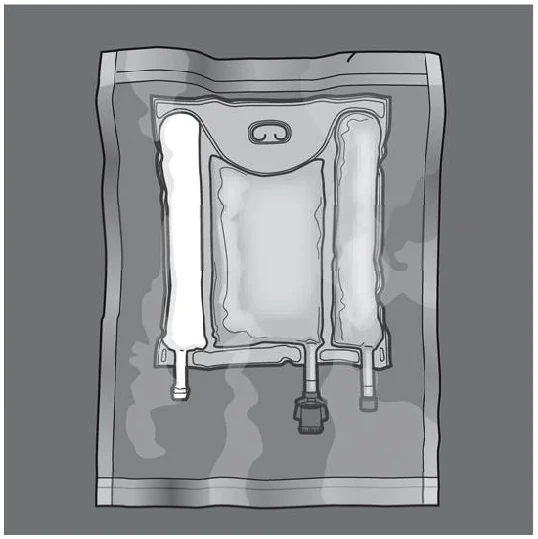
Figure 1 Figure 2
Preparation of the mixed emulsion:
- Ensure that the product is at room temperature when breaking the non-permanent seals.
- Place bag onto a flat clean surface.
Activating the 3 chamber bag (mixing of 3 solutions by breaking two non-permanent seals)
Step 1: Start rolling the bag from the D-hanger side.
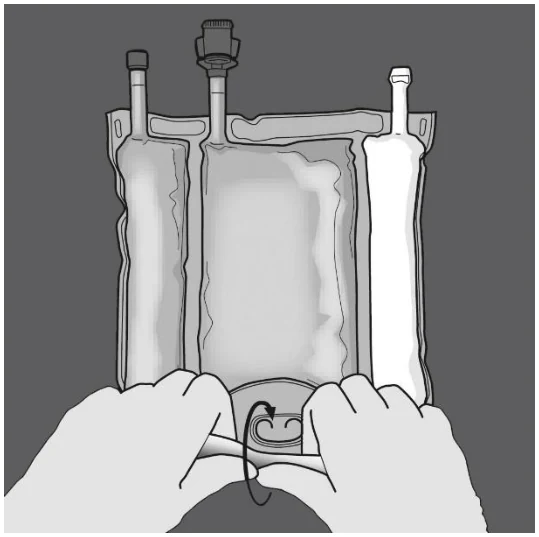
Step 2: Apply pressure until peal seals open.
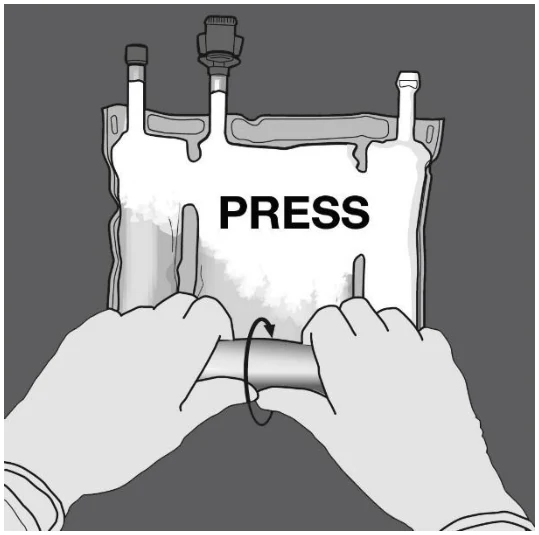
Step 3: Change direction by rolling the bag towards the D-hanger. Continue until the seal is completely opened. Proceed the same way to complete the opening of the second peel seal.
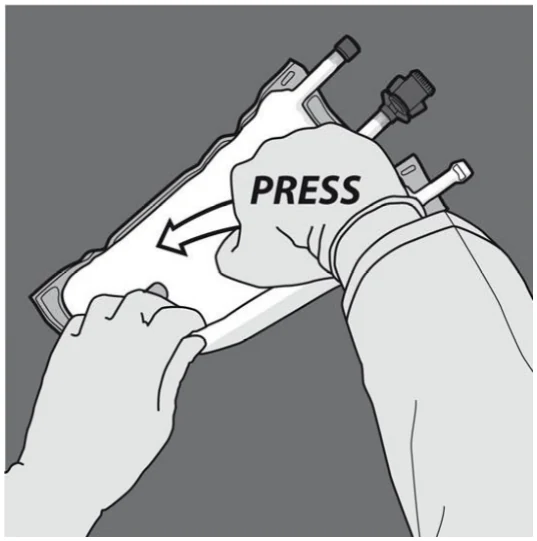
Step 4: Turn the bag over at least three times to mix the contents thoroughly. The appearance of the mixed solution should be a milky-white emulsion.
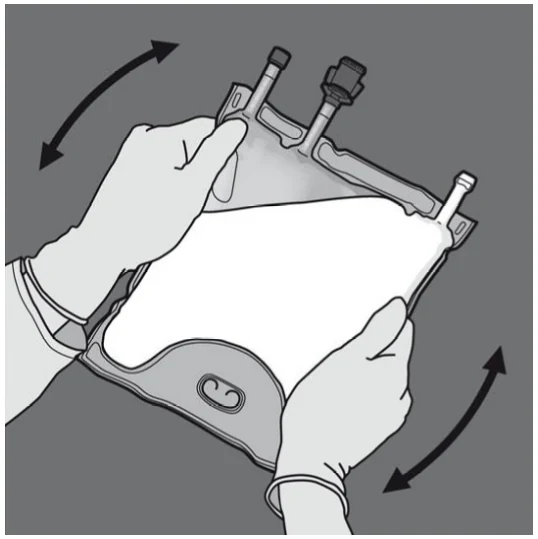
Step 5: Remove the protective cap from the administration site and insert the administration set.
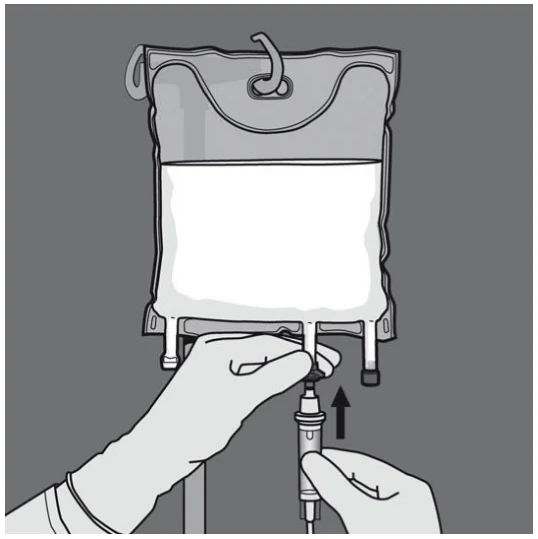
Activating the 2 chambers (mixing 2 solutions by breaking the non-permanent seal between the amino acid and glucose chambers)
Step 1: To mix only 2 solutions, roll the bag from the top (hanger end) corner of the seal separating the solutions. Apply pressure to open the seal separating the glucose and amino acids compartments.
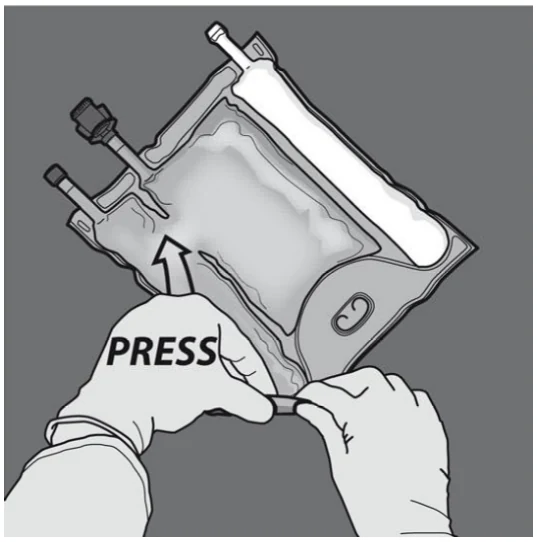
Step 2: Place the bag such that the lipid emulsion compartment is nearest to the operator. Roll the bag while protecting the lipid emulsion compartment in the palms of the hands.
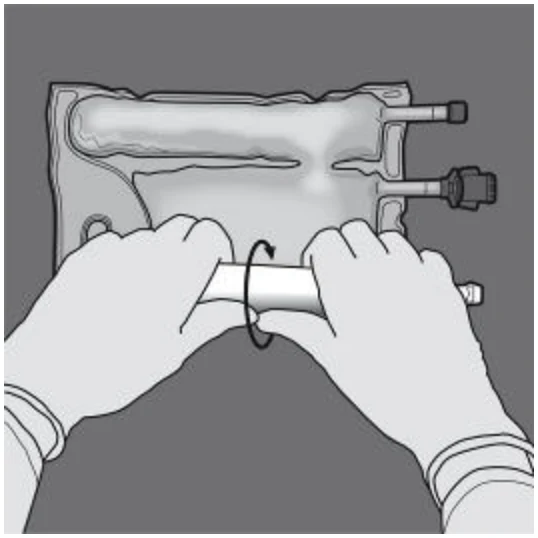
Step 3: Apply pressure with one hand and roll the bag toward the tubes.
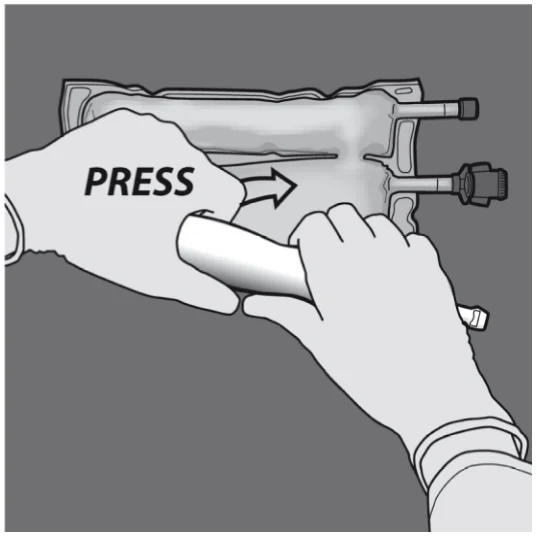
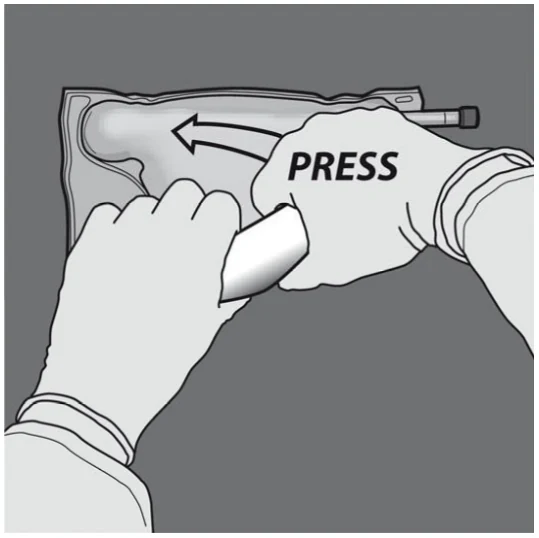
Step 4: Change direction by rolling the bag towards the top (hanger end). Press with the other hand, continuing until the seal separating the amino acids and glucose solutions is completely opened.
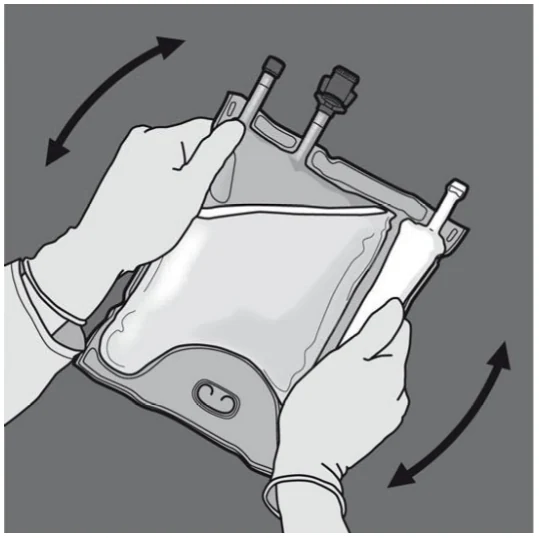
Step 5: Turn the bag over at least three times to mix the content thoroughly. The appearance of the mixed solution should be clear, colorless or slightly yellow.
Step 6: Remove the protective cap from the administration site and insert the administration set.
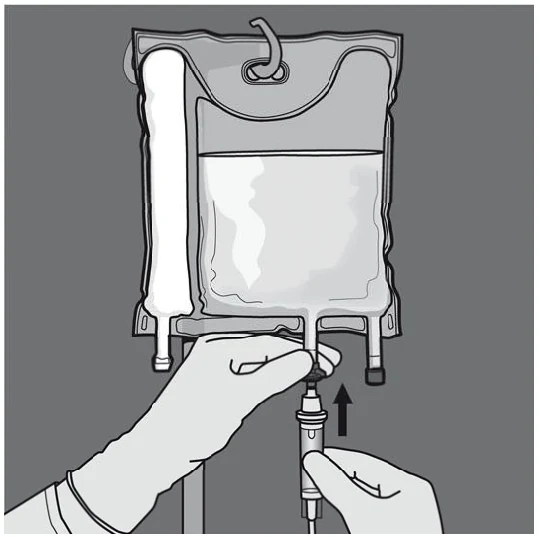
The flow rate should be increased gradually during the first hour. The administration flow rate must be adjusted based on the following factors:
the dose being administered
the daily volume intake
the duration of the infusion.
Method of administration:
When used in neonates and children below 2 years, the solution (in bags and administration sets) should be protected from light exposure until administration is completed.
Due to its high osmolarity, undiluted Numeta G16%E can only be administered through a central vein. However, sufficient dilution of Numeta G16%E with water for injection lowers the osmolarity and allows peripheral infusion.
Use of a 1.2 micron filter is recommended for administration of Numeta G16%E.
The table below indicates the minimum volume of water for injection to be added to the activated bag in order to achieve the target osmolarity for peripheral administration. It should be noted that any other addition made to the activated bag will modify the final osmolarity.
| Target Osmolarity (mOsm/L) | Minimum addition of water for injection to achieve target osmolarity (mL) | |
|---|---|---|
| Numeta G16%E after 2-in-1 activation | < 900 | 330 |
| < 850 | 380 | |
| < 800 | 430 | |
| Numeta G16%E after 3-in-1 activation | < 900 | 220 |
| < 850 | 260 | |
| < 800 | 320 |
Addition of additives
Light exposure of solutions for intravenous parenteral nutrition, especially after admixture with trace elements and/or vitamins, may have adverse effects on the clinical outcome in neonates, due to the generation of peroxides and other degradation products. When used in neonates and children below 2 years, Numeta G16%E should be protected from ambient light until administration is completed. Compatible additives may be added via the injection site into the reconstituted mixture (after the non-permanent seals have been opened and after the contents of the two or three chambers have been mixed).
Vitamins may also be added into the glucose chamber before the mixture is reconstituted (before opening the non-permanent seals and before mixing the solutions and the emulsion).
Possible additions of commercially available trace element solutions (identified as TE1, TE2 and TE4), vitamins (identified as lyophilizate V1 and emulsion V2), and electrolytes in defined quantities are shown in Tables 1-6.
- 1. Compatibility with TE4, V1 and V2
Table 1: Compatibility of 3-in-1 (Activated 3CB) with and without dilution with water
| Per 500 mL (3 in 1 admixture with lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 12.0 | 25.6 | 37.6 | 12.0 | 25.6 | 37.6 |
| Potassium (mmol) | 11.4 | 26.2 | 37.6 | 11.4 | 26.2 | 37.6 |
| Magnesium (mmol) | 1.6 | 3.6 | 5.2 | 1.6 | 3.6 | 5.2 |
| Calcium (mmol) | 3.1 | 16.4 | 19.5 | 3.1 | 8.2 | 11.3 |
| Phosphate* (mmol) | 4.4 | 6.9 | 11.3 | 4.4 | 6.9 | 11.3 |
| Trace elements & vitamins | - | 10 mL TE4 + 1 vial V1 + 30 mL V2 | 10 mL TE4 + 1 vial V1 + 30 mL V2 | - | 5 mL TE4 + ½ vial V1 + 5 mL V2 | 5 mL TE4 + ½ vial V1 + 5 mL V2 |
| Water for Injection | - | - | - | - | 350 mL | 350 mL |
* Organic phosphate
Table 2: Compatibility of 2-in-1 (Activated 2CB) with and without dilution with water
| Per 376 mL (2 in 1 admixture without lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 11.6 | 26.0 | 37.6 | 11.6 | 0.0 | 11.6 |
| Potassium (mmol) | 11.4 | 26.2 | 37.6 | 11.4 | 0.0 | 11.4 |
| Magnesium (mmol) | 1.6 | 3.6 | 5.2 | 1.6 | 0.0 | 1.6 |
| Calcium (mmol) | 3.1 | 8.2 | 11.3 | 3.1 | 0.0 | 3.1 |
| Phosphate* (mmol) | 3.2 | 8.1 | 11.3 | 3.2 | 0.0 | 3.2 |
| Trace elements & vitamins | - | 5mL TE4 + ½ vial V1 | 5mL TE4 + ½ vial V1 | - | 5mL TE4 + ½ vial V1 | 5mL TE4 + ½ vial V1 |
| Water for Injection | - | - | - | - | 450 mL | 450 mL |
* Organic phosphate
- 2. Compatibility with TE1, V1 and V2
Table 3: Compatibility of 3-in-1 (Activated 3CB) with and without dilution with water
| Per 500 mL (3 in 1 admixture with lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 12.0 | 4.0 | 16.0 | 12.0 | 0.0 | 12.0 |
| Potassium (mmol) | 11.4 | 6.2 | 17.6 | 11.4 | 0.0 | 11.4 |
| Magnesium (mmol) | 1.6 | 0 | 1.6 | 1.6 | 0.0 | 1.6 |
| Calcium (mmol) | 3.1 | 2.1 | 5.2 | 3.1 | 0.0 | 3.1 |
| Phosphate* (mmol) | 4.4 | 2.0 | 6.4 | 4.4 | 0.0 | 4.4 |
| Trace elements & vitamins | - | 5 mL TE1 + ½ vial V1 + 5 mL V2 | 5 mL TE1 + ½ vial V1 + 5 mL V2 | - | 5 mL TE1 + ½ vial V1 + 5 mL V2 | 5 mL TE1 + ½ vial V1 + 5 mL V2 |
| Water for Injection | - | - | - | - | 350 mL | 350 mL |
* Organic phosphate
Table 4: Compatibility of 2-in-1 (Activated 2CB) with and without dilution with water
| Per 376 mL (2 in 1 admixture without lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 11.6 | 26.0 | 37.6 | 11.6 | 0.0 | 11.6 |
| Potassium (mmol) | 11.4 | 26.2 | 37.6 | 11.4 | 0.0 | 11.4 |
| Magnesium (mmol) | 1.6 | 3.6 | 5.2 | 1.6 | 0.0 | 1.6 |
| Calcium (mmol) | 3.1 | 8.2 | 11.3 | 3.1 | 0.0 | 3.1 |
| Phosphate* (mmol) | 3.2 | 8.1 | 11.3 | 3.2 | 0.0 | 3.2 |
| Trace elements & vitamins | - | 5 mL TE1 + ½ vial V1 | 5 mL TE1 + ½ vial V1 | - | 5 mL TE1 + ½ vial V1 | 5 mL TE1 + ½ vial V1 |
| Water for Injection | - | - | - | - | 450 mL | 450 mL |
* Organic phosphate
- 3. Compatibility with TE2, V1 and V2
Table 5: Compatibility of 3-in-1 (Activated 3CB) with and without dilution with water
| Per 500 mL (3 in 1 admixture with lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 12.0 | 4.0 | 16.0 | 12.0 | 0.0 | 12.0 |
| Potassium (mmol) | 11.4 | 6.2 | 17.6 | 11.4 | 0.0 | 11.4 |
| Magnesium (mmol) | 1.6 | 0 | 1.6 | 1.6 | 0.0 | 1.6 |
| Calcium (mmol) | 3.1 | 2.1 | 5.2 | 3.1 | 0.0 | 3.1 |
| Phosphate* (mmol) | 4.4 | 2.0 | 6.4 | 4.4 | 0.0 | 4.4 |
| Trace elements & vitamins | - | 5 mL TE2 + ½ vial V1 + 5 mL V2 | 5 mL TE2 + ½ vial V1 + 5 mL V2 | - | 5 mL TE2 + ½ vial V1 + 5 mL V2 | 5 mL TE2 + ½ vial V1 + 5 mL V2 |
| Water for Injection | - | - | - | - | 350 mL | 350 mL |
* Organic phosphate
Table 6: Compatibility of 2-in-1 (Activated 2CB) with and without dilution with water
| Per 376 mL (2 in 1 admixture without lipids) | ||||||
|---|---|---|---|---|---|---|
| Admixture without dilution | Admixture with dilution | |||||
| Additives | Included level | Maximum further addition | Maximum total level | Included level | Maximum further addition | Maximum total level |
| Sodium (mmol) | 11.6 | 26.0 | 37.6 | 11.6 | 0.0 | 11.6 |
| Potassium (mmol) | 11.4 | 26.2 | 37.6 | 11.4 | 0.0 | 11.4 |
| Magnesium (mmol) | 1.6 | 3.6 | 5.2 | 1.6 | 0.0 | 1.6 |
| Calcium (mmol) | 3.1 | 8.2 | 11.3 | 3.1 | 0.0 | 3.1 |
| Phosphate* (mmol) | 3.2 | 8.1 | 11.3 | 3.2 | 0.0 | 3.2 |
| Trace elements & vitamins | - | 5 mL TE2 + ½ vial V1 | 5 mL TE2 + ½ vial V1 | - | 5 mL TE2 + ½ vial V1 | 5 mL TE2 + ½ vial V1 |
| Water for Injection | - | - | - | - | 450 mL | 450 mL |
* Organic phosphate
The composition of vitamins and trace elements preparations are illustrated in Tables 7 and 8.
Table 7:Composition of the commercial trace elements preparation used:
| Composition per 10mL | TE1 | TE2 | TE4 |
|---|---|---|---|
| Iron | - | 8.9µmol or 0.5mg | - |
| Zinc | 38.2µmol or 2.5mg | 15.3µmol or 1mg | 15.3µmol or 1mg |
| Selenium | 0.253µmol or 0.02mg | 0.6µmol or 0.05mg | 0.253µmol or 0.02mg |
| Copper | 3.15µmol or 0.2mg | 4.7µmol or 0.3mg | 3.15µmol or 0.2mg |
| Iodine | 0.0788µmol or 0.01mg | 0.4µmol or 0.05mg | 0.079µmol or 0.01mg |
| Fluorine | 30µmol or 0.57mg | 26.3µmol or 0.5mg | - |
| Molybdenum | - | 0.5µmol or 0.05mg | - |
| Manganese | 0.182µmol or 0.01mg | 1.8µmol or 0.1mg | 0.091µmol or 0.005mg |
| Cobalt | - | 2.5µmol or 0.15mg | - |
| Chromium | - | 0.4µmol or 0.02mg | - |
Table 8: Composition of the commercial vitamin preparations used:
| Composition per vial | V1 | V2 |
|---|---|---|
| Vitamin B1 | 2.5 mg | - |
| Vitamin B2 | 3.6 mg | - |
| Nicotinamide | 40 mg | - |
| Vitamin B6 | 4.0 mg | - |
| Pantothenic acid | 15.0 mg | - |
| Biotin | 60 µg | - |
| Folic acid | 400 µg | - |
| Vitamin B12 | 5.0 µg | - |
| Vitamin C | 100 mg | - |
| Vitamin A | - | 2300 IU |
| Vitamin D | - | 400 IU |
| Vitamin E | - | 7 IU |
| Vitamin K | - | 200 µg |
To perform an addition:
- Aseptic conditions must be observed
- Prepare the injection site of the bag
- Puncture the injection site and inject the additives using an injection needle or a reconstitution device
- Mix content of the bag and the additives
Preparation of the infusion:
- Aseptic conditions must be observed
- Suspend the bag
- Remove the plastic protector from the administration outlet
- Firmly insert the infusion set spike into the administration outlet
Administration of the infusion:
- For single use only
- Only administer the product after the non-permanent seals between the two or three chambers have been opened and the contents of the two or three chambers have been mixed
- Ensure that the final activated 3CB emulsion for infusion does not show any evidence of phase separation or the final 2CB solution for infusion does not show any evidence of particles
- Immediate use once non-permanent seals are broken is recommended. Numeta G16%E should not be stored for subsequent infusion. Do not connect any partially used bag
- Do not connect in series in order to avoid the possibility of air embolism due to possible residual gas contained in the primary bag.
- Use of a 1.2 micron filter is recommended for administration of Numeta G16%E.
- When used in neonates and children below 2 years, protect from light exposure until administration is completed. Exposure of Numeta G16%E to ambient light, expecially after admixtures with trace elements and/or vitamins, generates peroxides and other degradation products that can be reduced by protection from light exposure.
- Any unused product or waste material and all necessary disposable devices must be properly discarded.
Shelf Life after the Solutions are Mixed
Use the product immediately after the non-permanent seals between the two or three chambers have been opened. Stability studies of the mixtures have been performed for 7 days between 2°C and 8°C followed by 48 hours at 30°C.
Shelf life after supplementation (electrolytes, trace elements, vitamins, water):
For specific admixtures in-use stability of the Numeta formulation has been demonstrated for 7 days between 2°C and 8°C followed by 48 hours at 30°C.
From a microbiological point of view, the product should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2 to 8°C, unless reconstitution /dilution /supplementation has taken place in controlled and validated aseptic conditions.
Do not use Numeta G16%E if the bag is damaged. A damaged bag looks like this:
- The non-permanent seals are broken
- Any one of the chambers contains a mixture of any of the solutions
- The amino acids solution and the glucose solution are not clear, colorless, or slightly yellow, and/or contain visible particles
- The lipid emulsion is not a uniform liquid with a milky white appearance.
Medicines should not be disposed of via wastewater or household waste. Ask your pharmacist how to dispose of medicines no longer required. These measures will help to protect the environment.
What Numeta G16%E contains
The active substances are:
| Composition | ||
|---|---|---|
| Composition | ||
| Active Substance | Activated 2CB (376 mL) | Activated 3CB (500 mL) |
| Active Substance | Activated 2CB (376 mL) | Activated 3CB (500 mL) |
| Amino Acid Chamber | ||
| Alanine | 1.03 g | 1.03 g |
| Arginine | 1.08 g | 1.08 g |
| Aspartic acid | 0.77 g | 0.77 g |
| Cysteine | 0.24 g | 0.24 g |
| Glutamic acid | 1.29 g | 1.29 g |
| Glycine | 0.51 g | 0.51 g |
| Histidine | 0.49 g | 0.49 g |
| Isoleucine | 0.86 g | 0.86 g |
| Leucine | 1.29 g | 1.29 g |
Lysine monohydrate (equivalent to Lysine) | 1.59 g (1.42 g) | 1.59 g (1.42 g) |
| Methionine | 0.31 g | 0.31 g |
Ornithine hydrochloride (equivalent to Ornithine) | 0.41 g (0.32 g) | 0.41 g (0.32 g) |
| Phenylalanine | 0.54 g | 0.54 g |
| Proline | 0.39 g | 0.39 g |
| Serine | 0.51 g | 0.51 g |
| Taurine | 0.08 g | 0.08 g |
| Threonine | 0.48 g | 0.48 g |
| Tryptophan | 0.26 g | 0.26 g |
| Tyrosine | 0.10 g | 0.10 g |
| Valine | 0.98 g | 0.98 g |
| Sodium chloride | 0.30 g | 0.30 g |
| Potassium acetate | 1.12 g | 1.12 g |
| Calcium chloride dihydrate | 0.46 g | 0.46 g |
| Magnesium acetate tetrahydrate | 0.33 g | 0.33 g |
| Sodium glycerophosphate hydrated | 0.98 g | 0.98 g |
| Glucose Chamber | ||
Glucose monohydrate (equivalent to glucose anhydrous) | 85.25 g (77.50 g) | 85.25 g (77.50 g) |
| Lipid Chamber | ||
| Refined olive oil (approximately 80%) + Refined soya bean oil (approximately 20%) | - | 15.5 g |
The reconstituted solution/emulsion provides the following:
| Composition | ||||
|---|---|---|---|---|
| Composition | ||||
| Activated 2CB | Activated 3CB | |||
| Activated 2CB | Activated 3CB | |||
| Per volume unit (mL) | 376 | 100 | 500 | 100 |
| Per volume unit (mL) | 376 | 100 | 500 | 100 |
| Nitrogen (g) | 2.0 | 0.52 | 2.0 | 0.39 |
| Amino acids (g) | 13.0 | 3.5 | 13.0 | 2.6 |
| Glucose (g) | 77.5 | 20.6 | 77.5 | 15.5 |
| Lipids (g) | 0 | 0 | 15.5 | 3.1 |
| Energy | ||||
| Total calories (kcal) | 362 | 96 | 517 | 103 |
| Non-protein calories (kcal) | 310 | 82 | 465 | 93 |
| Glucose calories (kcal) | 310 | 82 | 310 | 62 |
| Lipid calories (kcal)a | 0 | 0 | 155 | 31 |
| Non-prot calories / nitrogen (kcal/g N) | 158 | 158 | 237 | 237 |
| Lipid calories (%non-protein calories) | NA | N/A | 33 | 33 |
| Lipid calories (% total calories) | NA | N/A | 30 | 30 |
| Electrolytes | ||||
| Sodium (mmol) | 11.6 | 3.1 | 12.0 | 2.4 |
| Potassium (mmol) | 11.4 | 3.0 | 11.4 | 2.3 |
| Magnesium (mmol) | 1.6 | 0.41 | 1.6 | 0.31 |
| Calcium (mmol) | 3.1 | 0.82 | 3.1 | 0.62 |
| Phosphateb (mmol) | 3.2 | 0.85 | 4.4 | 0.87 |
| Acetate (mmol) | 14.5 | 3.9 | 14.5 | 2.9 |
| Malate (mmol) | 4.3 | 1.1 | 4.3 | 0.86 |
| Chloride (mmol) | 13.8 | 3.7 | 13.8 | 2.8 |
| pH (approx.) | 5.5 | 5.5 | 5.5 | 5.5 |
| Osmolarity approx. (mOsm/L) | 1585 | 1585 | 1230 | 1230 |
a Includes calories from egg phospholipids for injection b Includes phosphate from egg phospholipids for injection component of the lipid emulsion
The other ingredients are:
L-Malic acid a
Hydrochloric acid a
Egg phospholipids for injection
Glycerol
Sodium oleate
Sodium hydroxide a
Water for injections
a for pH adjustment