

Summary of Product Characteristics (SmPC) - Mitomycin 40 mg powder and solvent for intravesical solution
1 NAME OF THE MEDICINAL PRODUCT
Mitomycin 40 mg powder and solvent for intravesical solution
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each vial of Mitomycin medac contains 40 mg mitomycin.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Powder and solvent for intravesical solution.
Powder: Grey to grey blue powder or cake.
Solvent: Clear and colourless solution
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Mitomycin medac is indicated as intravesical administration for relapse prevention in adults with superficial urinary bladder carcinoma after transurethral resection.
4.2 Posology and method of administration
Mitomycin medac must be administered by physicians experienced in this therapy, only if strictly indicated.
Mitomycin medac is only intended for intravesical use following reconstitution.
Posology
The content of one vial is required for one bladder instillation.
There are many intravesical mitomycin regimens, varying in the dose of mitomycin used, the frequency of instillation and the duration of therapy.
Unless otherwise specified, the dose of mitomycin is 40 mg instilled into the bladder once weekly. Regimens with instillations every 2 weeks, every month or 3 monthly can also be used.
The specialist should decide on the optimum regimen, frequency and duration of therapy on an individual patient basis.
Special populations
Elderly
Insufficient data from clinical studies are available concerning the use of mitomycin in patients ≥ 65 years of age.
Renal or hepatic impairment
The medicinal product should be used with caution in patients with renal or hepatic impairment.
Paediatric population
The safety and efficacy of Mitomycin medac in children have not been established. No data are available.
Method of administration
Mitomycin medac is only intended for intravesical instillation after being dissolved.
It is advised to use this medicinal product at its optimal pH (urinary pH > 6) and to maintain the concentration of mitomycin by reducing fluid intake before, during and after instillation. The bladder must be emptied before instillation with a catheter. Mitomycin is introduced into the bladder by means of a catheter and at low pressure. The length of individual instillation should be 1 – 2 hours. During this period the solution should have sufficient contact with the entire mucosal surface of the bladder. Therefore the patient should be mobilised as much as possible. After 2 hours the patient should void the instilled solution, preferably in a sitting position.
For instructions on reconstitution and dilution of the medicinal product before administration, see section 6.6.
4.3 Contraindications
- Hypersensitivity to the active substance(s) or to any of the excipients listed in section 6.1
- Breastfeeding
- Bladder wall perforation
- Cystitis
4.4 Special warnings and precautions for use
If cystitis does occur, symptomatic treatment with local anti-inflammatories and analgesics should be given. In most cases the mitomycin therapy can be continued, if necessary at a reduced dose. Isolated cases of allergic (eosinophilic) cystitis have been reported which necessitated discontinuation of therapy (see section 4.8).
Extravasation following intravesical administration
Symptoms of extravasation after intravesical mitomycin administration might present straight after the application or weeks or months later. It can be unclear if the extravasation occurred due to unnoticed perforation, a thinned muscularis propria or if the medicinal product was not administered correctly.
First symptoms present as pelvic or abdominal pain that are refractory to simple analgesia. (Fat) tissue necrosis in the surrounding area as a consequence of the extravasation was observed in most cases. Bladder perforation or development of fistula and/or abscess has also been reported (see section 4.8).
Therefore, physicians should consider the possibility that extravasation occurred if the patient complains about pelvic or abdominal pain to prevent serious consequences.
General hygiene for the patient
It is recommended to wash hands and genital area after micturition. This applies especially to the first micturitions following mitomycin administration.
Mitomycin is a mutagenic and potentially carcinogenic substance in humans. Contact with the skin and mucous membranes is to be avoided.
Bone marrow toxicity
Due to the toxic effects of mitomycin on the bone marrow, other myelotoxic therapy modalities (in particular other cytostatics, radiation) must be administered with particular caution in order to minimise the risk of additive myelosuppression.
Long-term therapy may result in cumulative bone marrow toxicity. Bone marrow suppression may only manifest itself after a delay, being expressed most strongly after 4-6 weeks, accumulating after prolonged use and therefore often requiring an individual dose adjustment.
Occurrence of acute leukaemia (in some cases following preleukaemic phase) and myelodysplastic syndrome has been reported in patients concomitantly treated intravenously with mitomycin and other antineoplastic agents.
In the case of pulmonary symptoms, which cannot be attributed to the underlying disease, therapy should be stopped immediately. Pulmonary toxicity can be well treated with steroids.
Therapy should be stopped immediately also if there are symptoms of haemolysis or indications of renal dysfunction (nephrotoxicity). The occurrence of a haemolytic-uraemic syndrome (HUS: irreversible renal failure, microangiopathic haemolytic anaemia [MAHA syndrome] and thrombocytopenia) is commonly fatal.
At intravenous doses > 30 mg of mitomycin/m² of body surface microangiopathic-haemolytic anaemia has been observed. Close monitoring of renal function is recommended. No cases of MAHA have been observed so far after intravesical use of mitomycin.
New findings suggest a therapeutic trial may be appropriate for the removal of immune complexes that seem to play a significant role in the onset of symptoms by means of immunoadsorption with staphylococcal protein A columns.
Elderly
Elderly patients often have reduced physiological function, bone marrow depression, which may be protracted, so administer mitomycin with special caution in this population while closely monitoring the patient’s condition.
4.5 Interaction with other medicinal products and other forms of interaction
Possible interaction under systemic therapy
Myelotoxic interactions with other bone marrow-toxic treatment modalities (especially other cytotoxic medicinal products, radiation) are possible.
Combination with vinca alkaloids or bleomycin may reinforce pulmonary toxicity.
An increased risk of haemolytic-uraemic syndrome has been reported in patients receiving concomitant administration of intravenous mitomycin and 5-fluorouracil or tamoxifen.
In animal experiments, pyridoxine hydrochloride (vitamin B6) resulted in the loss of effect of mitomycin.
No injections with live vaccines should be carried out in connection with mitomycin treatment, as this may result in an increased risk of infection by the live vaccine.
The cardiotoxicity of doxorubicin may be reinforced by mitomycin.
4.6 Fertility, pregnancy and lactation
Pregnancy
There are no data from the use of mitomycin in pregnant women. Studies in animals have shown reproductive toxicity (see section 5.3). Mitomycin has a mutagenic, teratogenic and carcinogenic effect and therefore may impair the development of an embryo.
Women must not become pregnant during treatment with mitomycin. In the event of pregnancy during treatment, genetic counselling must be provided.
Breast-feeding
It is suggested that mitomycin is excreted in human milk. Due to its proven mutagenic, teratogenic and carcinogenic effects, breastfeeding must be discontinued during treatment with Mitomycin medac (see section 4.3).
Fertility
Women of childbearing potential have to use effective contraception or practise sexual abstinence during chemotherapy and for 6 months afterwards.
Mitomycin is genotoxic. Men who are being treated with mitomycin are therefore advised not to father a child during treatment and up to 6 months thereafter and to seek advice on the preservation of sperm before the start of therapy due to the possibility of irreversible infertility caused by the therapy with mitomycin.
4.7 Effects on ability to drive and use machines
Even when used in accordance with instructions this medicinal product may cause nausea and vomiting and thereby reduce reaction times to such an extent that the ability to drive and use machines is impaired. This applies even more if alcohol is consumed at the same time.
4.8 Undesirable effects
Undesirable effects are listed below by system organ class and frequency. Frequencies below are defined as: Very common (≥ 1/10), common (≥ 1/100 to < 1/10), uncommon (≥ 1/1,000 to < 1/100), rare (≥ 1/10,000 to < 1/1,000), very rare (< 1/10,000) or not known (cannot be estimated from the available data).
Possible adverse reactions under intravesical therapy
Adverse reactions may result either from the solution for intravesical instillation or after deep resection.
The most common adverse reactions of intravesically administered mitomycin are allergic skin reactions in the form of local exanthema (e.g. contact dermatitis, also in the form of palmar and plantar erythema), and cystitis.
| Skin and subcutaneous tissue disorders | Common Allergic skin rash, contact dermatitis, palmar-plantar erythema, pruritus Rare Generalised exanthema |
| Renal and urinary disorders | Common Cystitis (possibly haemorrhagic), dysuria, nocturia, pollakiuria, haematuria, local irritation of the bladder wall |
Very rare or not known
Necrotising cystitis, allergic (eosinophilic) cystitis, stenosis of the efferent urinary tract, reduced bladder capacity, bladder wall calcification, bladder wall fibrosis, bladder perforation
Not known
in case of extravasation:
Bladder perforation, (fat) tissue necrosis of the surrounding area, vesical fistula, abscesses
After intravesical administration, only minor amounts of mitomycin reach the systemic circulation. Nevertheless, in very rare cases the following systemic undesirable effects have been reported:
Possible systemic undesirable effects occurring very rarely following intravesical administration:
| Blood and lymphatic system disorders | Leukocytopenia, thrombocytopenia |
| Respiratory, thoracic and mediastinal disorders | Interstitial lung disease |
| Gastrointestinal disorders | Nausea, vomiting, diarrhoea |
| Hepatobiliary disorders | Transaminases increased |
| Skin and subcutaneous tissue disorders | Alopecia |
| Renal and urinary disorders | Renal dysfunction |
| General disorders and administration site conditions | Fever |
Possible adverse reactions under systemic therapy
The most common adverse reactions of mitomycin administered systemically are gastrointestinal symptoms like nausea and vomiting and bone marrow suppression with leukopenia and mostly dominant thrombocytopenia. This bone marrow suppression occurs in up to 65 % of patients.
In up to 10 % of patients serious organ toxicity in the form of interstitial pneumonia or nephrotoxicity must be expected.
Mitomycin is potentially hepatotoxic.
Blood and lymphatic system disorders Very common
Bone marrow suppression, leukopenia,
thrombocytopenia Rare Haemolytic anaemia, thrombotic microangiopathy (TMA), incl. thrombotic thrombocytopenic purpura (TTP) Not known Anaemia | |
| Infections and infestations | Rare Life-threatening infection, sepsis Not known Infection |
| Immune system disorders | Very rare Severe allergic reaction |
| Cardiac disorders | Rare Heart failure after previous therapy with anthracyclines |
| Respiratory, thoracic and mediastinal disorders | Common Interstitial pneumonia, dyspnoea, cough, shortness of breath Rare Pulmonary hypertension, pulmonary veno-occlusive disease (PVOD) |
| Gastrointestinal disorders | Very common Nausea, vomiting Uncommon Mucositis, stomatitis, diarrhoea, anorexia |
| Hepatobiliary disorders | Rare Hepatic dysfunction, increased transaminases, jaundice, veno-occlusive disease (VOD) of the liver |
| Skin and subcutaneous tissue disorders | Common Exanthema, allergic skin rash, contact dermatitis, palmar-plantar erythema Uncommon Alopecia Rare Generalised exanthema |
| Renal and urinary disorders | Common Renal dysfunction, increase in serum creatinine, glomerulopathy, nephrotoxicity |
Rare Haemolytic uraemic syndrome (HUS) (commonly fatal), microangiopathic-haemolytic anaemia (MAHA syndrome) | |
| General disorders and administration site conditions | Common Following extravasation: Cellulitis, tissue necrosis Uncommon Fever |
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
In case of overdose severe myelotoxicity or even myelophthisis must be expected, with the fullblown clinical effect only appearing after approximately 2 weeks.
The period until which the number of leukocytes falls to the lowest value may be 4 weeks. Prolonged close haematological monitoring therefore also has to be carried out if an overdose is suspected.
However, up until now, no cases of overdose of intravesical administration of mitomycin have been reported. As no effective antidote is available, the utmost caution should be exercised at each administration.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Antineoplastic agents, cytotoxic antibiotics and related substances, other cytotoxic antibiotics, ATC code: L01DC03
The antibiotic mitomycin is a cytostatic medicinal product from the group of alkylating agents.
Mechanism of action
Mitomycin is an antibiotic with an antineoplastic effect which is isolated from Streptomyces caespitosus. It is present in an inactive form. Activation to a trifunctional alkylating agent takes place rapidly, either at physiological pH in the presence of NADPH in serum or intracellularly in virtually all cells of the body with the exception of the cerebrum, as the blood-brain barrier is not overcome by mitomycin. The three alkylating radicals all stem from a quinone, an aziridine and a urethane group. The mechanism of action is based predominantly on DNA (to a lesser extent RNA) alkylation, with the corresponding inhibition of DNA synthesis. The degree of DNA damage correlates with the clinical effect and is lower in resistant cells than in sensitive cells. As with other alkylating agents, proliferating cells are damaged to a greater extent than those in the resting phase (G0) of the cell cycle. Additionally, free peroxide radicals are released, particularly in the case of higher doses, which result in DNA breaks. The release of peroxide radicals is associated with the organ-specific pattern of adverse reactions.
5.2 Pharmacokinetic properties
Absorption
Following intravesical administration only a small proportion of mitomycin reaches the serum. Maximum peak plasma levels of 0.05 µg/mL 40 minutes after intravesical instillation of 40 mg mitomycin have been measured. This is well below the level of 0.4 µg/mL of mitomycin in serum which is known to be myelosuppressive. Nevertheless, a systemic effect cannot be excluded completely.
In comparison, following intravenous administration of 10-20 mg/m² mitomycin, peak plasma levels of 0.4-3.2 μg/mL have been measured.
Distribution
The biological half life is short, between 40 and 50 minutes. The serum level falls biexponentially, steeply within the first 45 minutes and more slowly thereafter.
After approximately 3 hours the serum levels are usually below the detection limit.
Biotransformation and elimination
The main location for metabolism and elimination after systemic application is the liver. Accordingly, high concentrations of mitomycin have been found in the gall bladder. Renal excretion plays only a minor role with respect to the elimination.
5.3 Preclinical safety data
In animal studies mitomycin has a toxic effect on all proliferating tissues, in particular on the cells of the bone marrow and the gastrointestinal mucosa, and spermatogenesis is inhibited.
Mitomycin has mutagenic, carcinogenic and teratogenic properties, which can be demonstrated in appropriate experimental models.
If injected outside a vein, or in the event of extravasation into surrounding tissue, mitomycin causes severe necrosis.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Powder for solution for intravesical use: Urea.
Solvent for intravesical solution: Sodium chloride, water for injections pH adjusting agents (1 M sodium hydroxide, 1 M hydrochloric acid).
6.2 Incompatibilities
This medicinal product must not be mixed with other medicinal products except those mentioned in section 6.6.
6.3 Shelf life
Mitomycin medac, vials with 40 mg mitomycin and instillation set
18 months
The physical and chemical in-use stability has been demonstrated for 48 hours when stored protected from light at room temperature (15 °C – 25 °C) and for 72 hours when stored protected from light at 2 °C – 8 °C in a refrigerator.
From a microbiological point of view, the medicinal product should be used immediately.
If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user and would normally not be longer than 24 hours at 2 °C to 8 °C, protected from light, unless reconstitution has taken place in controlled and validated aseptic conditions.
Protect the reconstituted solution from light.
6.4 Special precautions for storage
This medicinal product does not require any special temperature storage conditions.
Keep the vial in the outer carton in order to protect from light.
For storage conditions after reconstitution of the medicinal product, see section 6.3.
6.5 Nature and contents of container
Mitomycin medac is contained within clear glass vials (type I) with fluoropolymer coated bromobutyl rubber stopper and a flip off aluminium seal.
Packs of 1 vial (50 ml), 1 APP* bag of 40 ml with 0.9 % sodium chloride solution, 1 catheter, 1 connector.
Packs of 4 vials (50 ml), 4 APP bags of 40 ml with 0.9 % sodium chloride solution, 4 catheters, 4 connectors.
Packs of 5 vials (50 ml), 5 APP bags of 40 ml with 0.9 % sodium chloride solution, 5 catheters, 5 connectors.
Packs of 1 vial (50 ml), 1 APP bag of 40 ml with 0.9 % sodium chloride solution, 1 catheter.
Packs of 4 vials (50 ml), 4 APP bags of 40 ml with 0.9 % sodium chloride solution, 4 catheters.
Packs of 5 vials (50 ml), 5 APP bags of 40 ml with 0.9 % sodium chloride solution, 5 catheters.
Packs of 1 vial (50 ml), 1 APP bag of 40 ml with 0.9 % sodium chloride solution, 1 connector.
Packs of 4 vials (50 ml), 4 APP bags of 40 ml with 0.9 % sodium chloride solution, 4 connectors.
Packs of 5 vials (50 ml), 5 APP bags of 40 ml with 0.9 % sodium chloride solution, 5 connectors.
Packs of 1 vial (50 ml), 1 APP bag of 40 ml with 0.9 % sodium chloride solution.
Packs of 4 vials (50 ml), 4 APP bags of 40 ml with 0.9 % sodium chloride solution.
Packs of 5 vials (50 ml), 5 APP bags of 40 ml with 0.9 % sodium chloride solution.
* APP = Advanced Polypropylene (polyolefin/polypropylene/styrene-block copolymer)
Not all pack sizes may be marketed.
6.6 Special precautions for disposal and other handling
Important information on the use of Mitomycin medac
Mitomycin medac may only be used by appropriately trained healthcare professionals.
Ensure suitable storage (see section 6.3) and the integrity of the packaging.
Basic principles and protective measures for the use of Mitomycin medac
In general, direct contact with Mitomycin medac should be avoided. Mitomycin medac is a cytostatic that poses a risk to people and the environment. A hazard may occur if the medicinal product is able to enter the body via injuries or through unprotected softened skin, if aerosols are inhaled, droplets get into the eyes or come into contact with mucous membranes, or if ingested. Do not eat, drink or smoke in the work areas and do not store any food, drinks or tobacco products here.
It is recommended that a closed, splashproof protective gown, disposable gloves, a suitable respirator mask and safety goggles with side shields are worn as personal protective equipment during handling. Mitomycin medac may only be transported in closed containers (for storage conditions after reconstitution, see section 6.3).
After working and in the case of contact with skin, wash your hands thoroughly with plenty of water and use skin care products.
Preparation of the reconstituted intravesical solution
Before use, the medicinal product must be dissolved under aseptic conditions with sterile 0.9% (9 mg/ml) sodium chloride solution (see Instructions for Use, step 7). Dissolve the content of one vial of Mitomycin medac (equivalent to 40 mg mitomycin) in 40 ml sterile 0.9% (9 mg/ml) sodium chloride solution. The content of the vial must dissolve to form a blue-purple clear solution within 2 minutes.
Only clear blue-purple solutions may be used.
Use of a lubricant is recommended to minimise the risk of traumatic catheterisation and to make the procedure more comfortable. Women might need less lubricant than men. Drain the bladder after catheterisation to reduce the amount of lubricant potentially introduced before you administer Mitomycin medac.
The content of the vial is intended for single use/single dose only. Unused solution must be disposed of.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
For further information regarding the catheter please see the corresponding instructions for use.
Instructions for users of Mitomycin medac
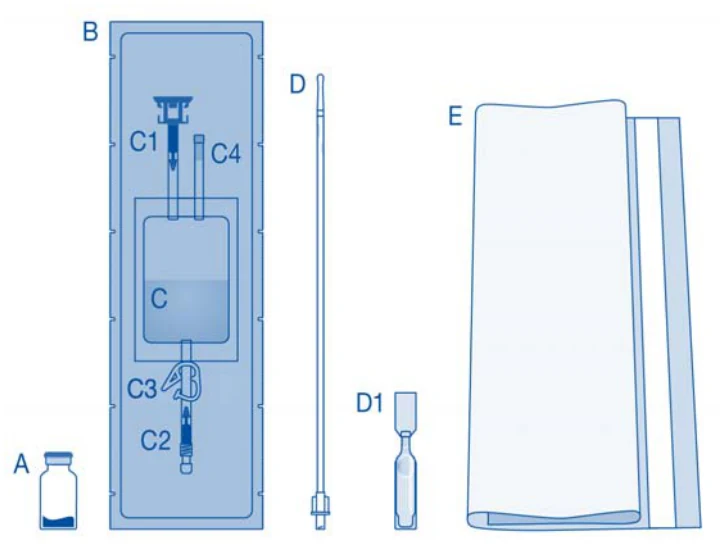
Constituents and application of the instillation set <with catheter, with connector>
Main constituents of the instillation set 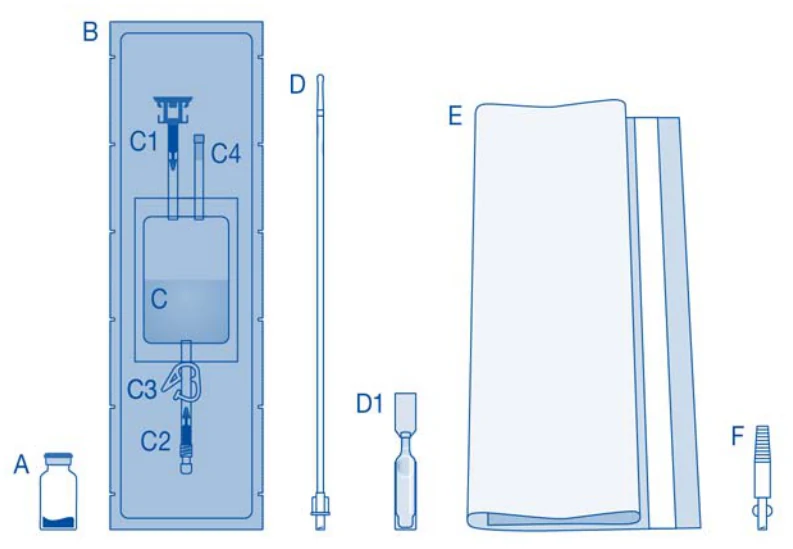
| Main constituent | Description |
| A | Vial with powder |
| B | Protective cover |
| C | Solvent bag with 0.9% (9 mg/ml) sodium chloride solution |
| C1 | Vial connector with protective cap and break-open seal |
| C2 | Luer-Lock catheter connector with protective cap and break-open seal |
| C3 | Pressure clamp |
| C4 | Filling port without application function |
| D | Luer-Lock catheter |
| D1 | Lubricant |
| E | Disposal bag |
| F | Luer-Lock to conical connector |
Connecting the vial to the solvent bag
- 1. Lay out the disposal bag (E) ready for direct disposal of the set after instillation to prevent contamination.
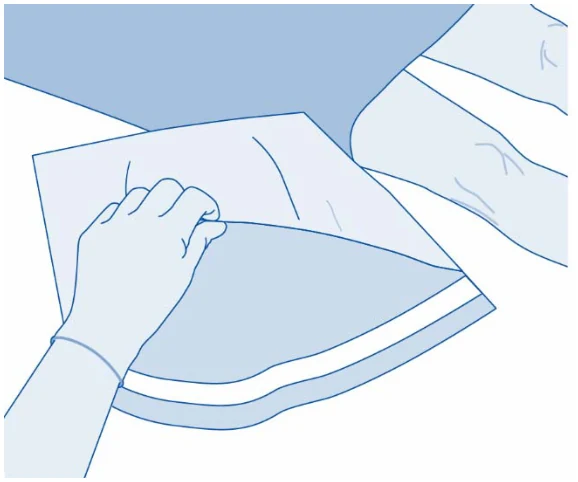
- 2. Remove the flip-off cap from the vial (A) and disinfect the stopper according to local
regulations. 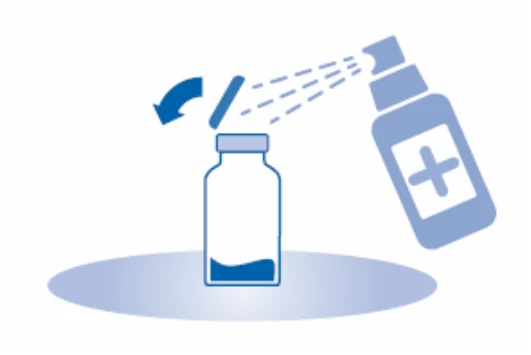
- 3. Tear open the protective cover (B) of the solvent bag (C) and remove the protective cover completely.
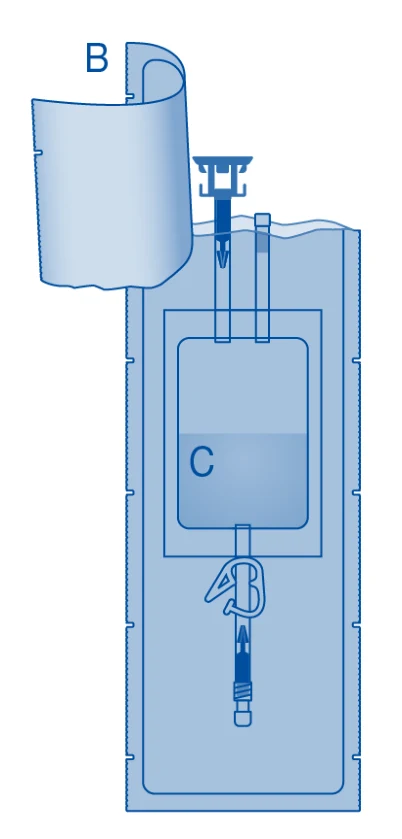
- 4. Remove the protective cap from the vial connector (C1).
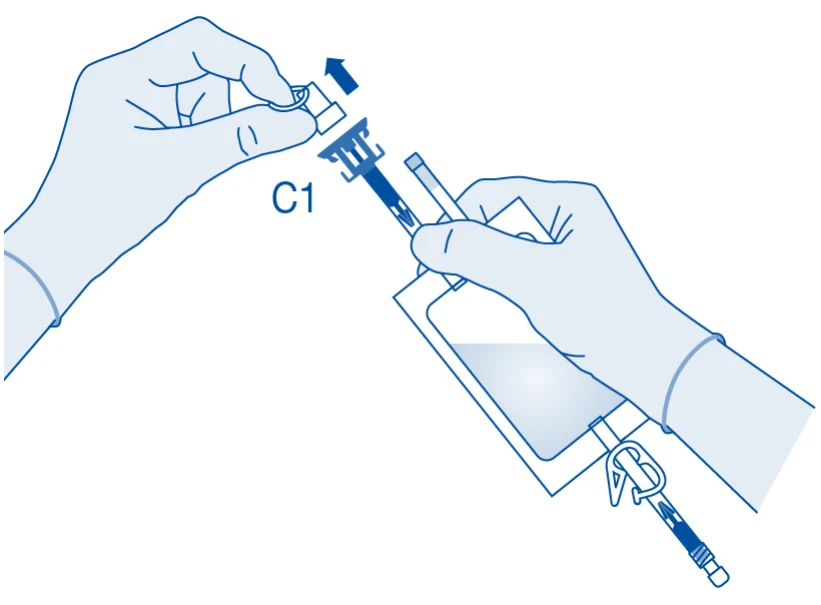
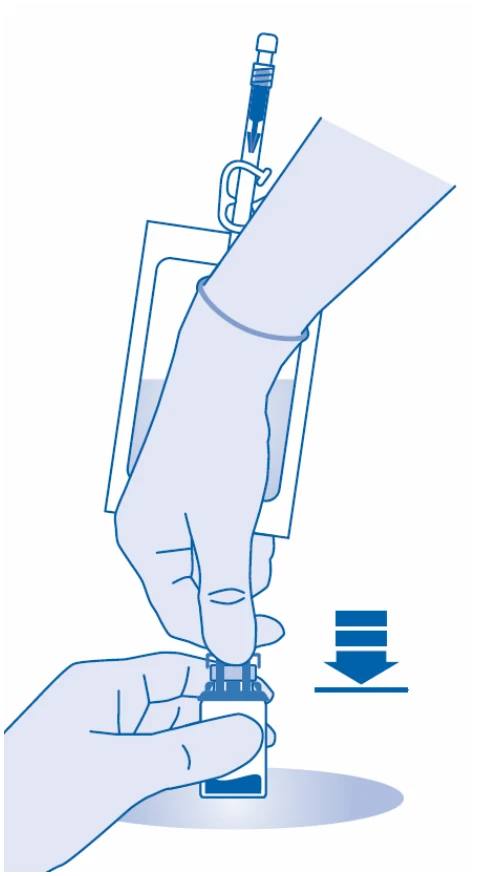
- 5. Push the connector onto the vial up to the stop.
Mixing the powder with the solvent
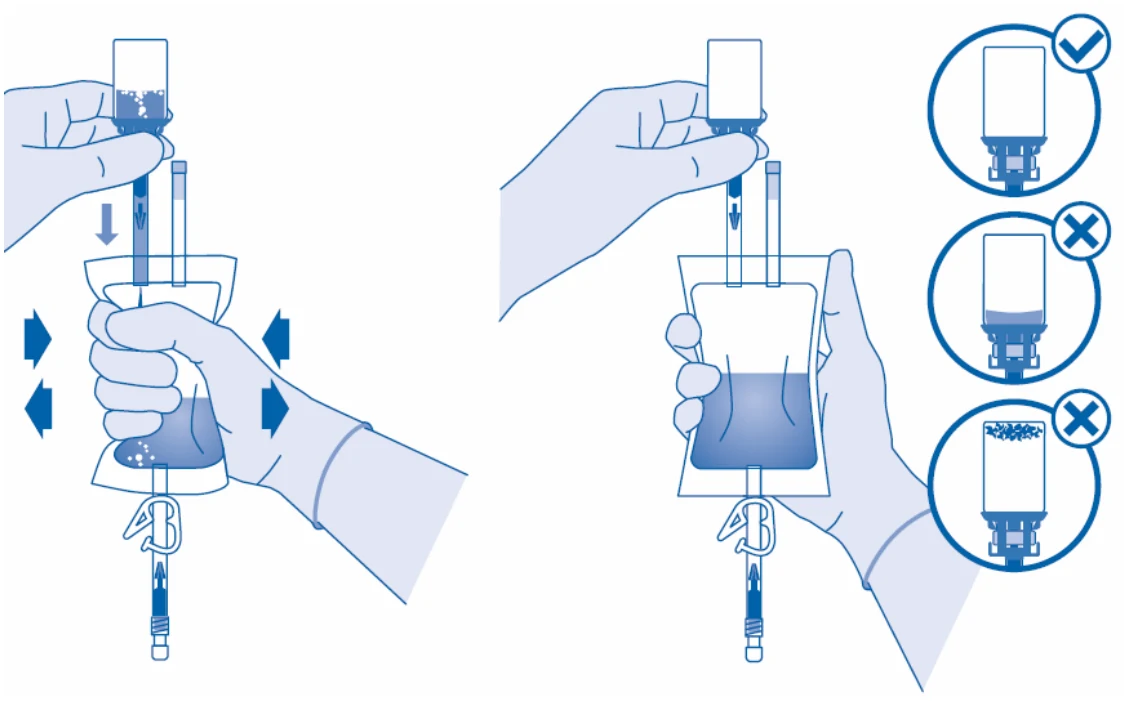
- 6. Bend the break-open seal inside the tube of the vial connector (C1) up and down
multiple times to break the seal. 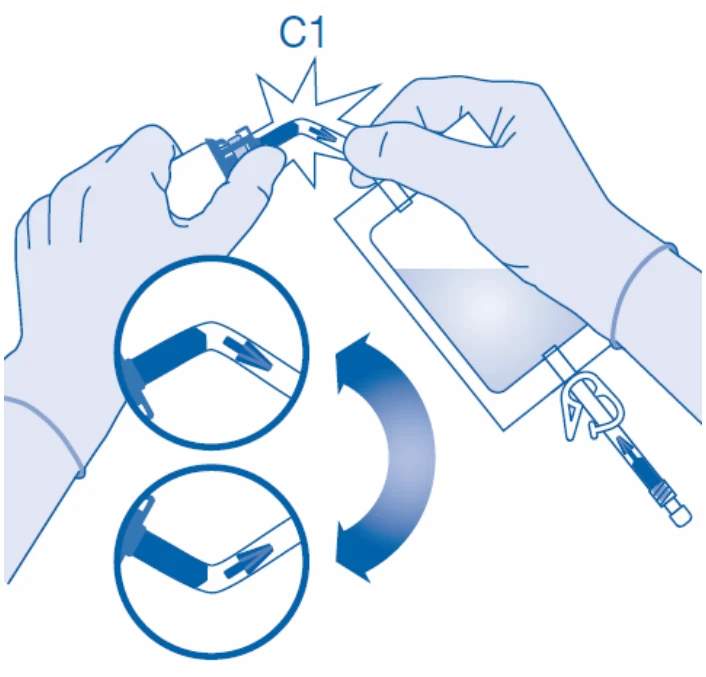
- 7.
Hold the solvent bag so that the vial is below it.
Squeeze the solvent bag multiple times to transfer enough solvent into the vial.
Make sure that the vial is not filled completely to allow for the subsequent transfer of the solution into the solvent bag. Some solvent may remain inside the bag.
Swirl the vial slowly to dissolve the medicinal product with the solvent.
The contents of the vial must dissolve to form a blue-purple clear solution within 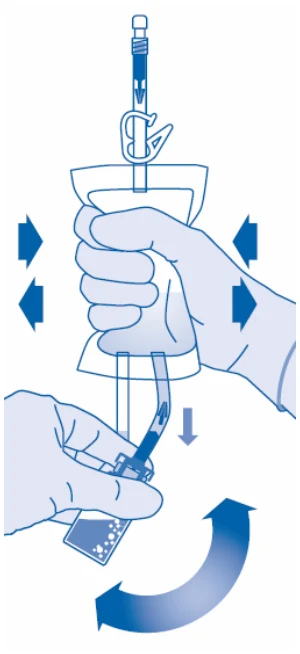
2 minutes.
- 8.
Turn the solvent bag upside down and hold it so that the vial is above it.
Hold the vial.
Squeeze the solvent bag multiple times until the vial is completely empty.
If any powder remains inside the vial, repeat steps 7 and 8.
From a microbiological point of view the medicinal product should be used immediately.
If the medicinal product is not used immediately, please see section 6.3 “Shelf life”.
Only use clear blue-purple solutions. The solution should not be administered at refrigerator temperature in order to prevent the patient from feeling the need to urinate resulting in a shortened exposure time.
Catheterisation
- 9.
Catheterise the patient according to local regulations and the instructions for use using the enclosed Luer-Lock catheter (D) and lubricant (D1) or another suitable catheter and lubricant.
Empty the urinary bladder using the catheter.
Note for use with self-selected catheter with conical connector:
The enclosed Luer-Lock to conical connector (F) must be used to connect the bag to a catheter with conical connector (not shown).
To do this, the following additional steps must be carried out:
- Remove the protective cap from the catheter connector (C2, see step 10).
- Connect the Luer-Lock to conical connector (F) to the catheter connector (C2) of the bag.
- Carefully connect the bag with the Luer-Lock to conical connector (F) to the patient’s permanent catheter.
- Then proceed with step 11.
Connecting the catheter to the solvent bag
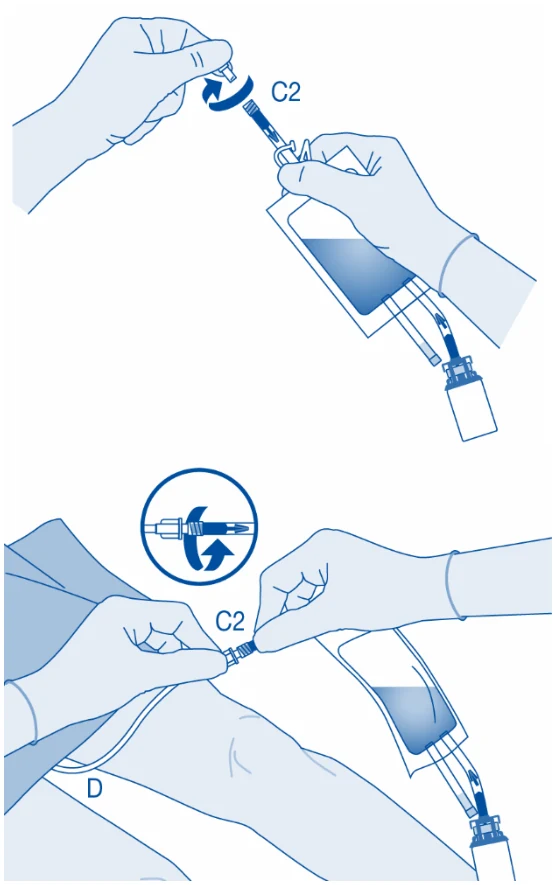
- 10.
Rotate and swirl the bag before connecting it.
Do not administer the solution at refrigerator temperature.
Remove the protective cap from the catheter connector (C2).
Connect the patient’s Luer-Lock catheter (D) with the catheter connector (C2) of the solvent bag.
Instillation
- 11.
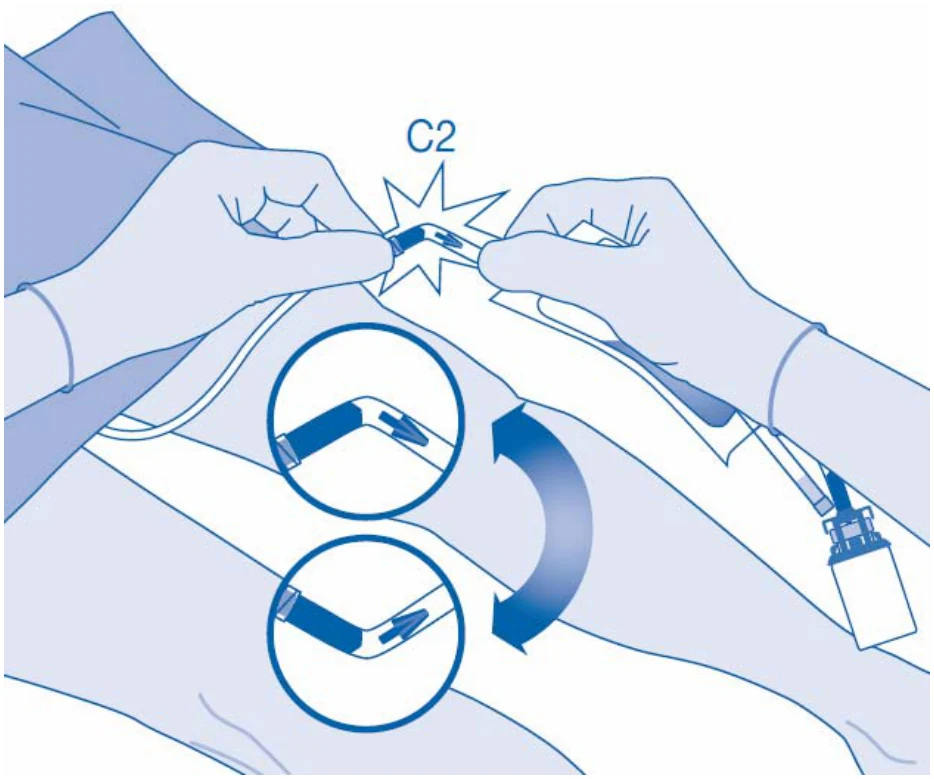
Bend the break-open seal inside the tube of the catheter connector (C2) up and down multiple times to break the seal.
Hold the patient’s catheter steady while doing so.
- 12.
Hold the solvent bag with the vial upside down above the bag.
Squeeze the solvent bag gently with the other hand so that the medicinal product is slowly instilled into the patient’s urinary bladder.
Continue to squeeze until the solvent bag and the vial are empty. 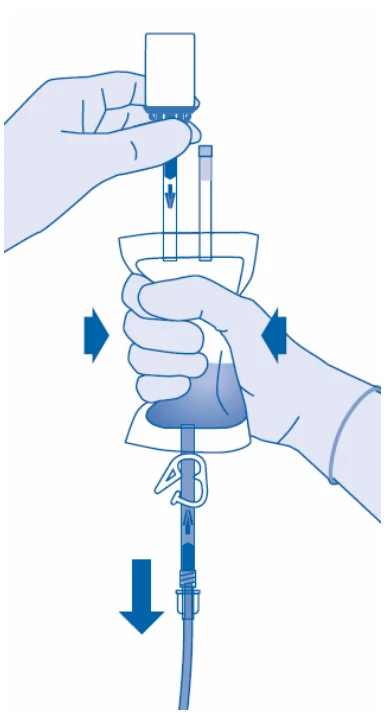
- 13. Squeeze the remaining air out of the solvent bag to empty the catheter as much as
possible. 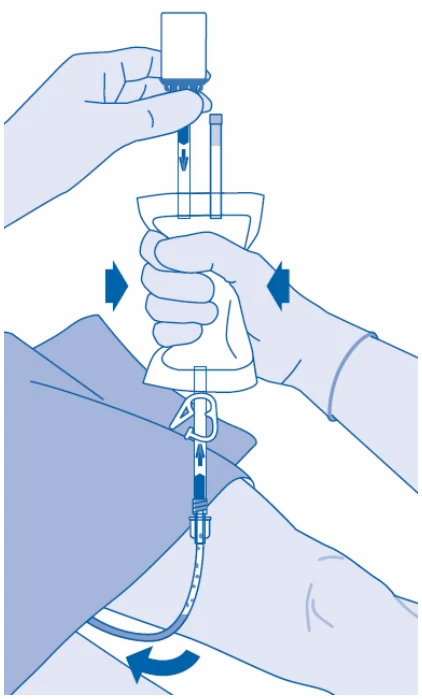
After instillation
- 14. Closing the pressure clamp (C3) prevents a reflux of fluid into the catheter and minimises the risk of contamination. Alternatively, you can keep the solvent bag compressed while performing steps 15 and 16.
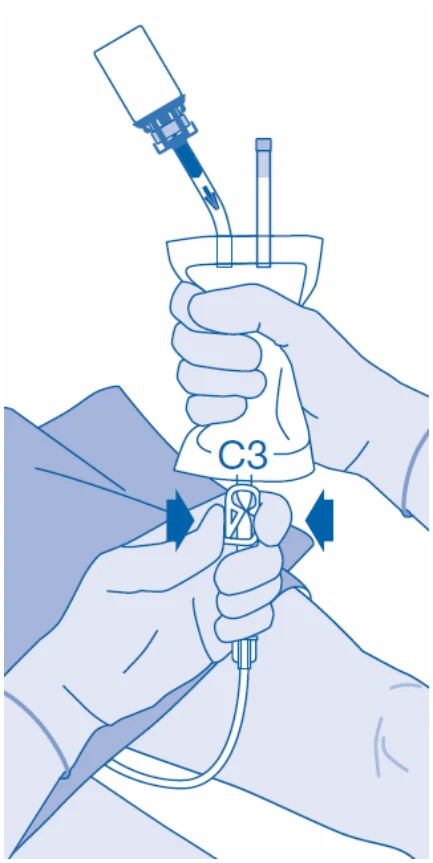
- 15.
Immediately remove the catheter carefully from the bladder without disconnecting the solvent bag from the catheter when the instillation set is emptied. After the catheter has been removed, the solution should remain in the bladder for 1 – 2 hours. Avoid contamination from splashing droplets.
Note for use with self-selected catheter with conical connector:
Separate the bag including the Luer-Lock to conical connector from the permanent catheter. Close the permanent catheter, for example using a catheter stopper or a clamp, to ensure that the medicinal product remains active in the bladder for the intended duration.
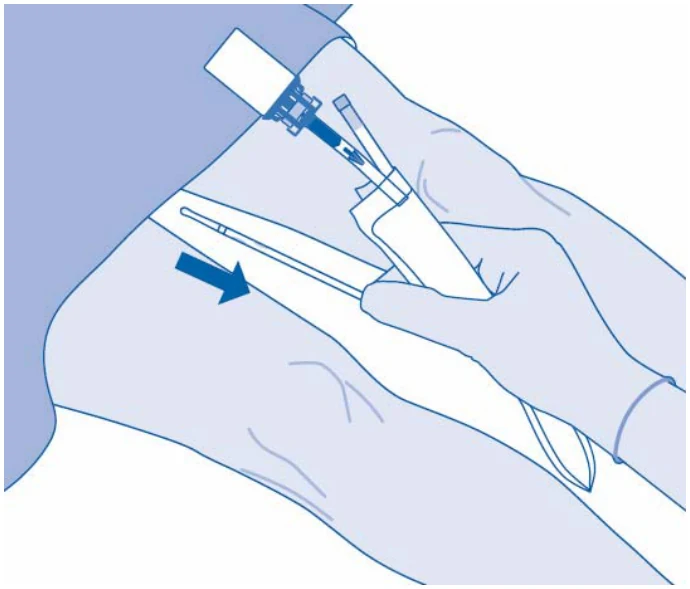
- 16.
Dispose of the product according to national regulations using the disposal bag.
The contents of the vial are intended for single use/single dose only. Any remaining solution must be disposed of.
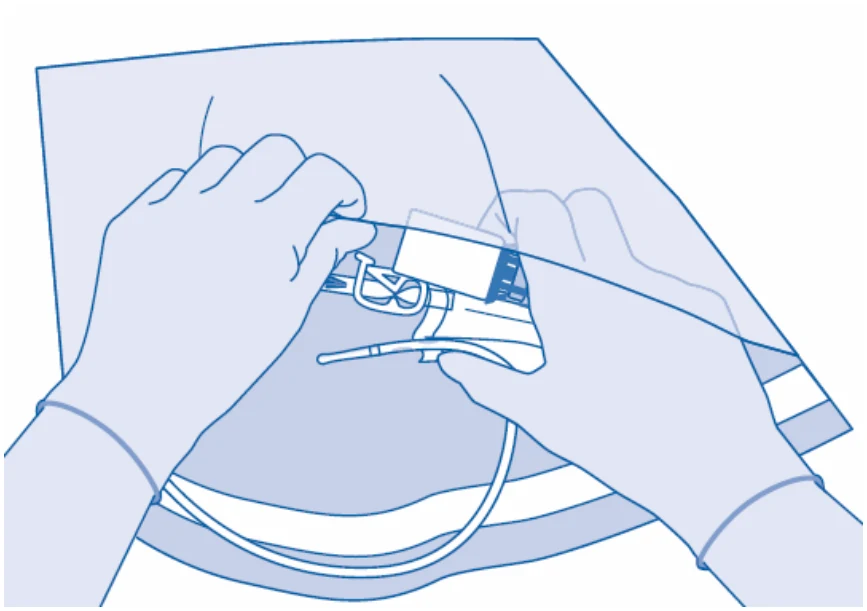
Instructions for users of Mitomycin medac
Constituents and application of the instillation set <with catheter, without connector>
Main constituents of the instillation set
| Main constituent | Description |
| A | Vial with powder |
| B | Protective cover |
| C | Solvent bag with 0.9% (9 mg/ml) sodium chloride solution |
| C1 | Vial connector with protective cap and break-open seal |
| C2 | Luer-Lock catheter connector with protective cap and break-open seal |
| C3 | Pressure clamp |
| C4 | Filling port without application function |
| D | Luer-Lock catheter |
| D1 | Lubricant |
| E | Disposal bag |
Connecting the vial to the solvent bag
- 1. Lay out the disposal bag (E) ready for direct disposal of the set after instillation to prevent contamination.
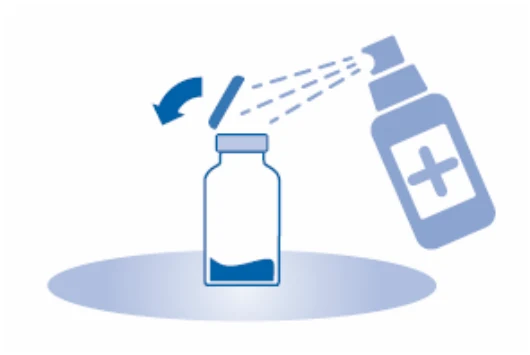
- 2. Remove the flip-off cap from the vial (A) and disinfect the stopper according to local regulations.
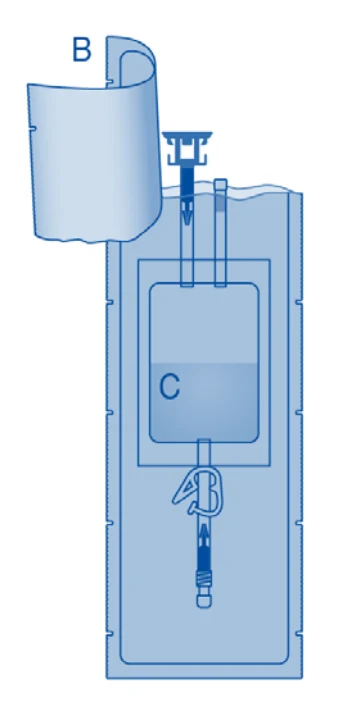
- 3. Tear open the protective cover (B) of the solvent bag (C) and remove the protective cover completely.
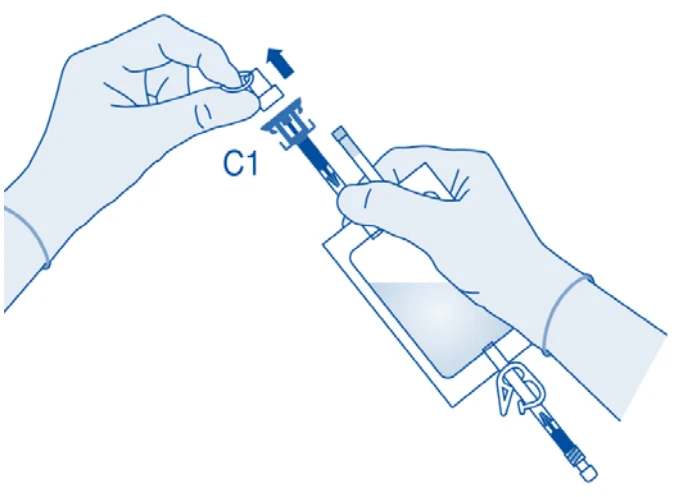
- 4. Remove the protective cap from the vial connector (C1).
- 5. Push the connector onto the vial up to the stop.
Mixing the powder with the solvent
- 6. Bend the break-open seal inside the tube of the vial connector (C1) up and down
multiple times to break the seal. 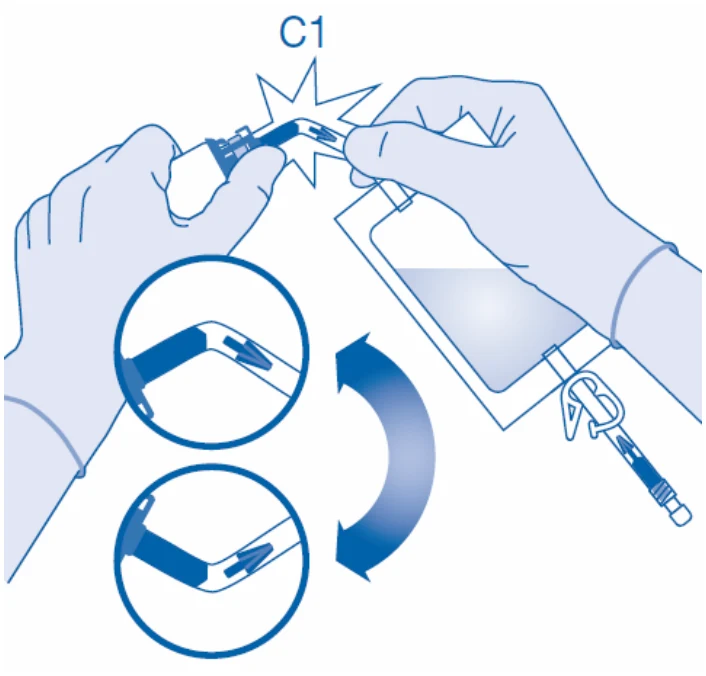
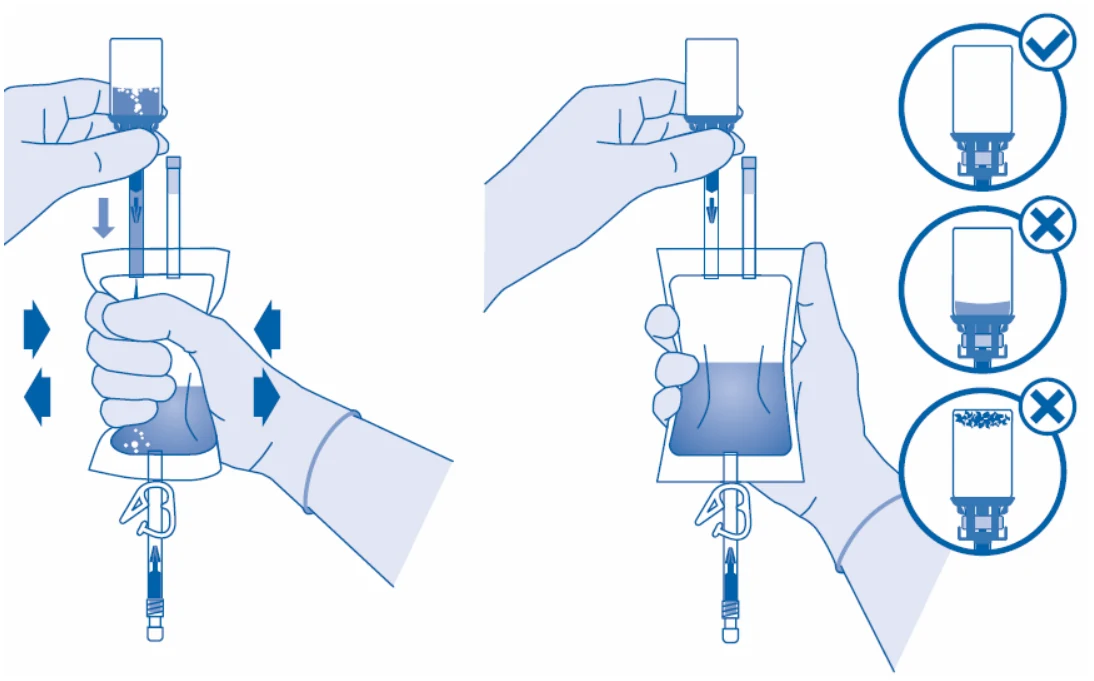
- 7.
Hold the solvent bag so that the vial is below it.
Squeeze the solvent bag multiple times to transfer enough solvent into the vial.
Make sure that the vial is not filled completely to allow for the subsequent transfer of the solution into the solvent bag. Some solvent may remain inside the bag.
Swirl the vial slowly to dissolve the medicinal product with the solvent.
The contents of the vial must dissolve to form a blue-purple clear solution within
2 minutes.
- 8.
Turn the solvent bag upside down and hold it so that the vial is above it.
Hold the vial.
Squeeze the solvent bag multiple times until the vial is completely empty.
If any powder remains inside the vial, repeat steps 7 and 8.
From a microbiological point of view the medicinal product should be used immediately. If the medicinal product is not used immediately, please see section 6.3 “Shelf life”.
Only use clear blue-purple solutions. The solution should not be administered at refrigerator temperature in order to prevent the patient from feeling the need to urinate resulting in a shortened exposure time.
Catheterisation
- 9.
Catheterise the patient according to local regulations and the instructions for use using the enclosed Luer-Lock catheter (D) and lubricant (D1) or another suitable catheter and/or lubricant.
Empty the urinary bladder using the catheter.
Connecting the catheter to the solvent bag
- 10.
Rotate and swirl the bag before connecting it.
Do not administer the solution at refrigerator temperature.
Remove the protective cap from the catheter connector (C2).
Connect the patient’s Luer-Lock catheter (D) with the catheter connector (C2) of the solvent bag.
Instillation
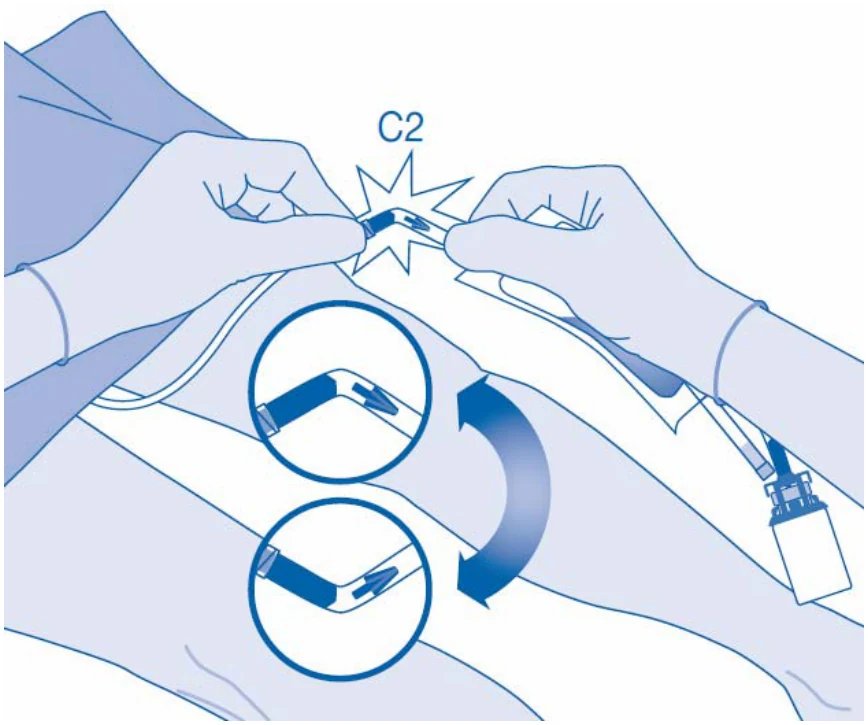
- 11.
Bend the break-open seal inside the tube of the catheter connector (C2) up and down multiple times to break the seal.
Hold the patient’s catheter steady while doing so.
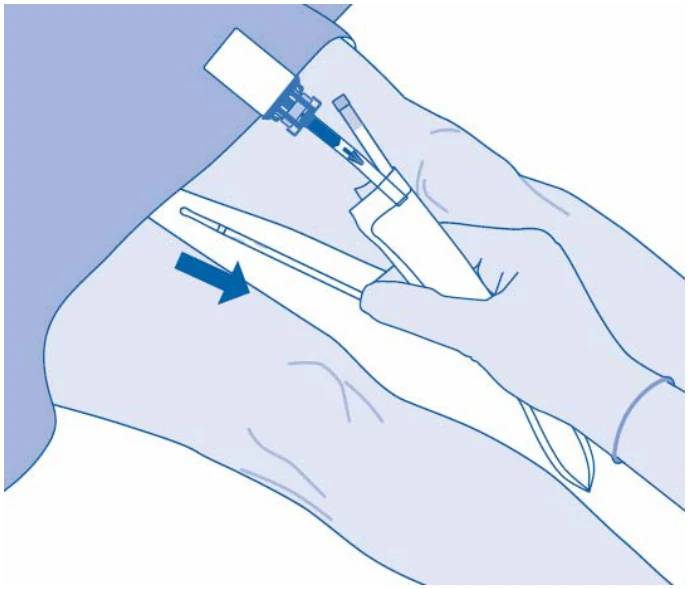
- 12.
Hold the solvent bag with the vial upside down above the bag.
Squeeze the solvent bag gently with the other hand so that the medicinal product is slowly instilled into the patient’s urinary bladder.
Continue to squeeze until the solvent bag and the vial are empty.
- 13. Squeeze the remaining air out of the solvent bag to empty the catheter as much as possible.
After instillation
- 14. Closing the pressure clamp (C3) prevents a reflux of fluid into the catheter and
minimises the risk of contamination. Alternatively, you can keep the solvent bag compressed while performing steps 15 and 16.
- 15. Immediately remove the catheter carefully from the bladder without disconnecting the solvent bag from the catheter when the instillation set is emptied. After the catheter has been removed, the solution should remain in the bladder for 1 – 2 hours. Avoid contamination from splashing droplets.
- 16.
Dispose of the product according to national regulations using the disposal bag.
The contents of the vial are intended for single use/single dose only. Any remaining solution must be disposed of.
Instructions for users of Mitomycin medac
Constituents and application of the instillation set <without catheter, with connector>
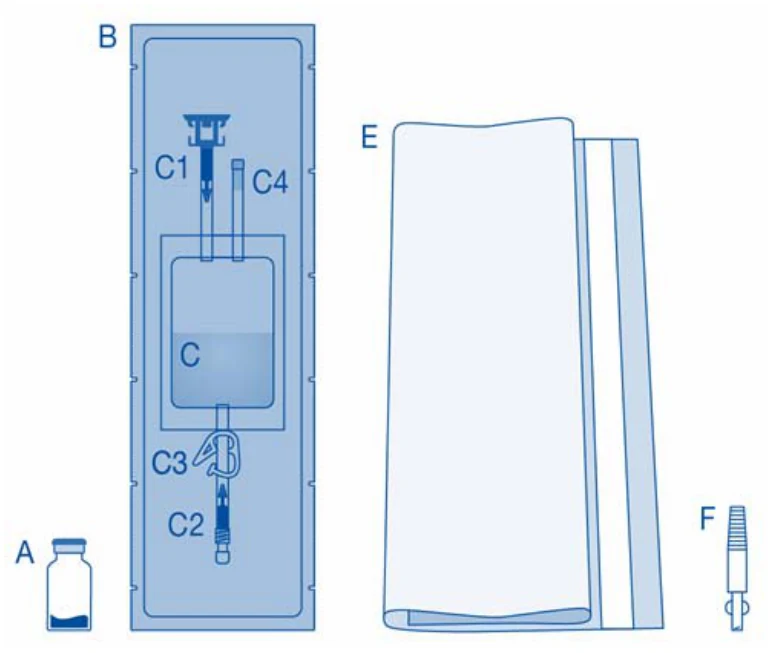
Main constituents of the instillation set
| Main constituent | Description |
| A | Vial with powder |
| B | Protective cover |
| C | Solvent bag with 0.9% (9 mg/ml) sodium chloride solution |
| C1 | Vial connector with protective cap and break-open seal |
| C2 | Luer-Lock catheter connector with protective cap and break-open seal |
| C3 | Pressure clamp |
| C4 | Filling port without application function |
| E | Disposal bag |
| F | Luer-Lock to conical connector |
Connecting the vial to the solvent bag
- 1. Lay out the disposal bag (E) ready for direct disposal of the set after instillation to prevent contamination.
- 2. Remove the flip-off cap from the vial (A) and disinfect the stopper according to local
regulations. 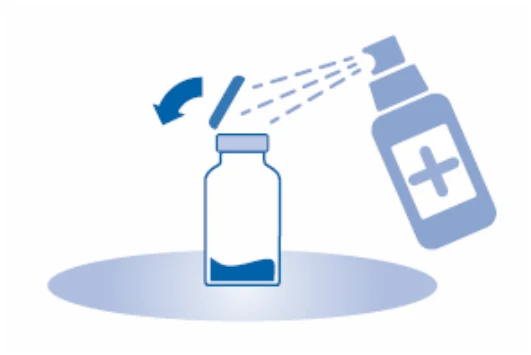
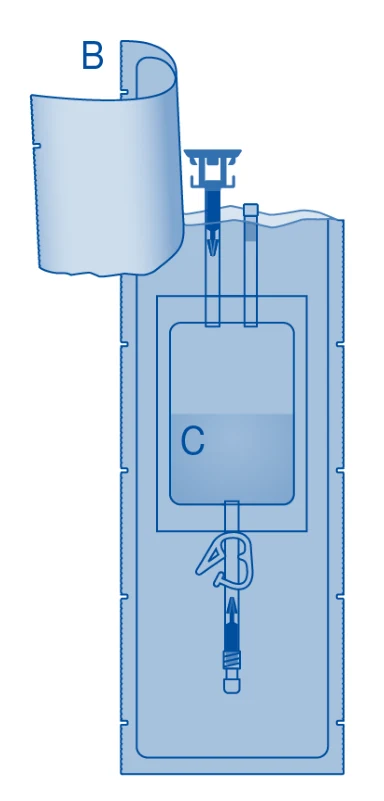
- 3. Tear open the protective cover (B) of the solvent bag (C) and remove the protective cover completely.
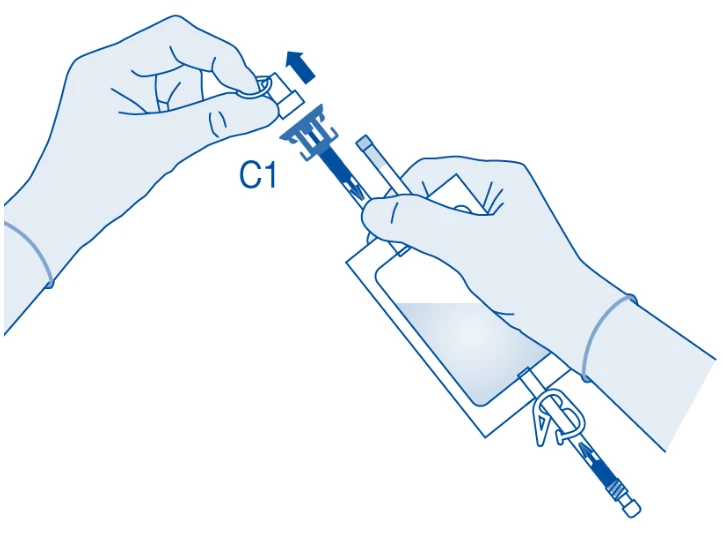
- 4. Remove the protective cap from the vial connector (C1).
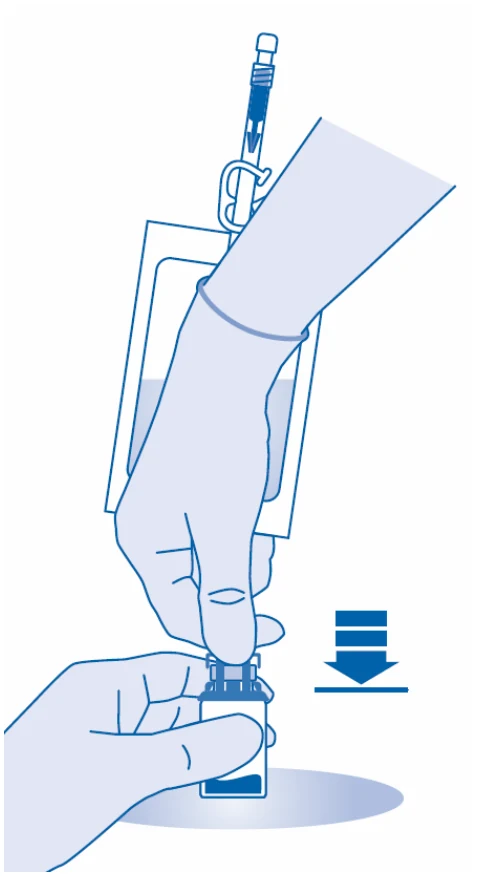
- 5. Push the connector onto the vial up to the stop.
Mixing the powder with the solvent
- 6. Bend the break-open seal inside the tube of the vial connector (C1) up and down multiple times to break the seal.
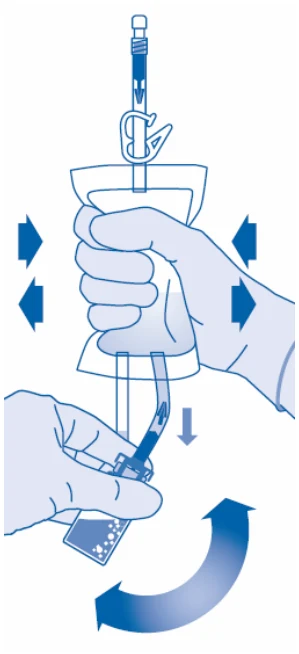
- 7.
Hold the solvent bag so that the vial is below it.
Squeeze the solvent bag multiple times to transfer enough solvent into the vial.
Make sure that the vial is not filled completely to allow for the subsequent transfer of the solution into the solvent bag. Some solvent may remain inside the bag.
Swirl the vial slowly to dissolve the medicinal product with the solvent.
The contents of the vial must dissolve to form a blue-purple clear solution within 2 minutes.
- 8.
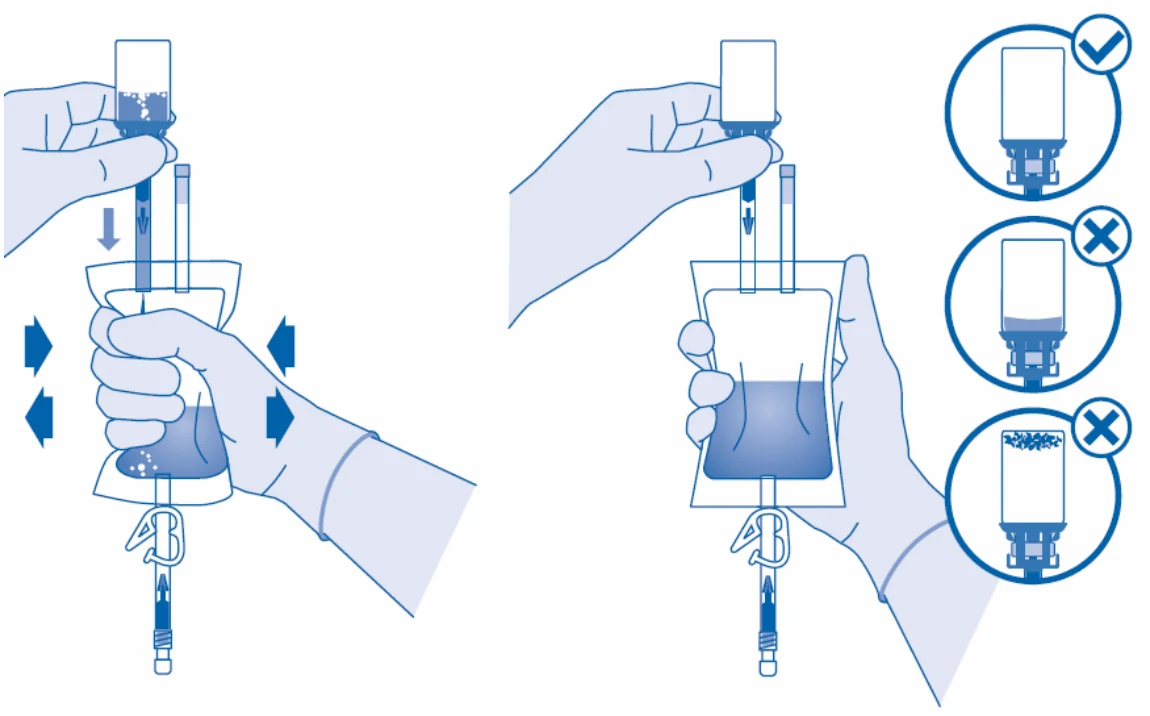
Turn the solvent bag upside down and hold it so that the vial is above it.
Hold the vial.
Squeeze the solvent bag multiple times until the vial is completely empty.
If any powder remains inside the vial, repeat steps 7 and 8.
From a microbiological point of view the medicinal product should be used immediately.
If the medicinal product is not used immediately, please see section 6.3 “Shelf life”.
Only use clear blue-purple solutions. The solution should not be administered at refrigerator temperature in order to prevent the patient from feeling the need to urinate resulting in a shortened exposure time.
Catheterisation
- 9.
Catheterise the patient according to local regulations and the instructions for use using a suitable catheter and lubricant.
Empty the urinary bladder using the catheter.
Note for use with self-selected catheter with conical connector:
This pack does not contain a catheter. Use the enclosed Luer-Lock to conical connector (F) to connect the bag to the patient’s permanent catheter as part of early instillation (not shown).
To do this, the following additional steps must be carried out:
- Remove the protective cap from the catheter connector (C2, see step 10).
- Connect the Luer-Lock to conical connector (F) to the catheter connector (C2) of the bag.
- Carefully connect the bag with the Luer-Lock to conical connector (F) to the patient’s permanent catheter.
- Then proceed with step 11.
Connecting the catheter to the solvent bag
- 10.
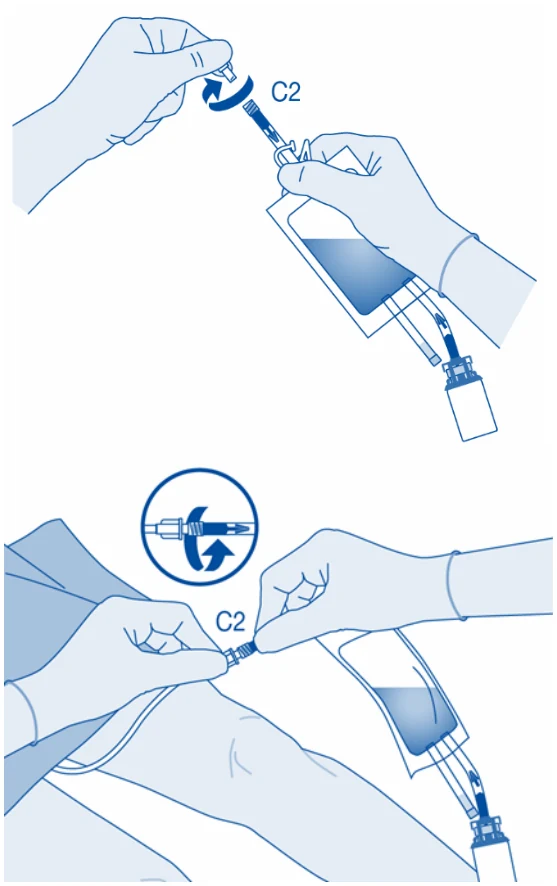
Rotate and swirl the bag before connecting it.
Do not administer the solution at refrigerator temperature.
Remove the protective cap from the catheter connector (C2).
Connect the patient’s catheter with the catheter connector (C2) of the solvent bag.
Instillation
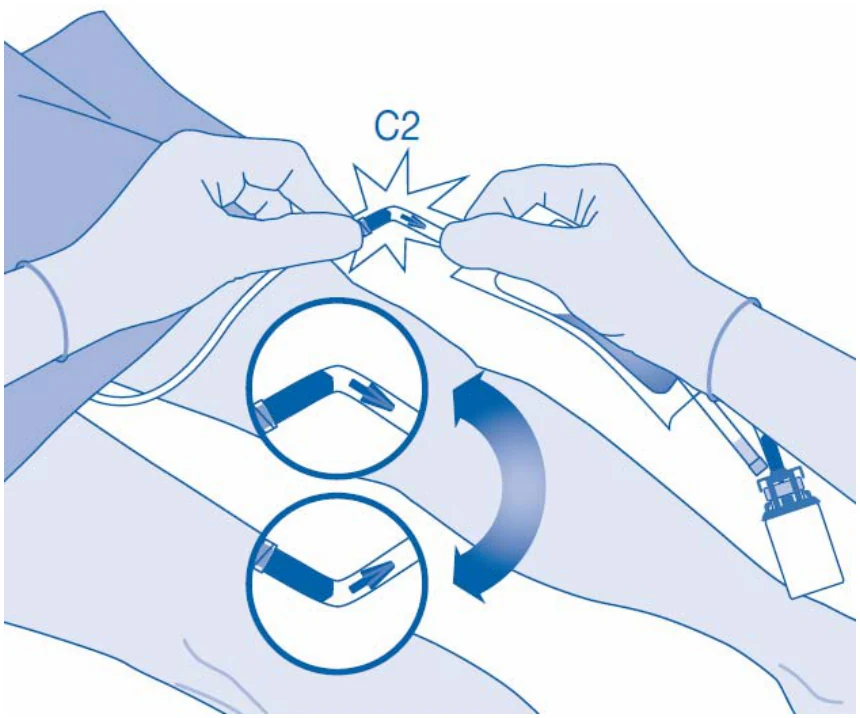
- 11.
Bend the break-open seal inside the tube of the catheter connector (C2) up and down multiple times to break the seal.
Hold the patient’s catheter steady while doing so.
- 12.
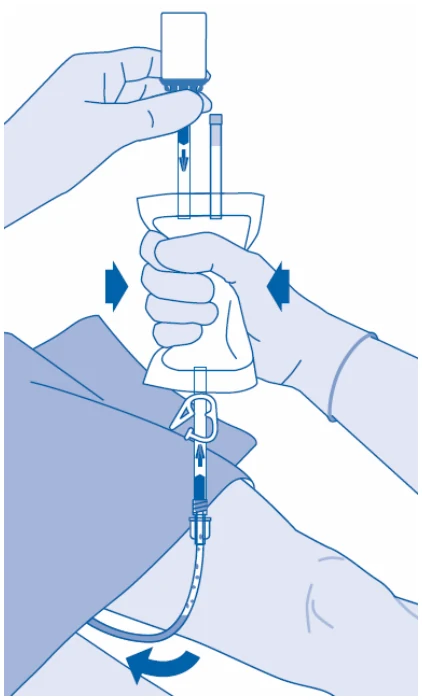
Hold the solvent bag with the vial upside down above the bag.
Squeeze the solvent bag gently with the other hand so that the medicinal product is slowly instilled into the patient’s urinary bladder.
Continue to squeeze until the solvent bag and the vial are empty.
- 13. Squeeze the remaining air out of the solvent bag to empty the catheter as much as possible.
After instillation
- 14. Closing the pressure clamp (C3) prevents a reflux of fluid into the catheter and minimises the risk of contamination. Alternatively, you can keep the solvent bag compressed while performing steps 15 and 16.
- 15.
Immediately remove the catheter carefully from the bladder without disconnecting the solvent bag from the catheter when the instillation set is emptied. After the catheter has been removed, the solution should remain in the bladder for 1 – 2 hours. Avoid contamination from splashing droplets.
Note for use with self-selected catheter with conical connector:
Separate the bag including the Luer-Lock to conical connector from the permanent catheter. Close the permanent catheter, for example using a catheter stopper or a clamp, to ensure that the medicinal product remains active in the bladder for the intended duration.
- 16.
Dispose of the product according to national regulations using the disposal bag.
The contents of the vial are intended for single use/single dose only. Any remaining solution must be disposed of.
Instructions for users of Mitomycin medac
Constituents and application of the instillation set <without catheter, without connector>
Main constituents of the instillation set 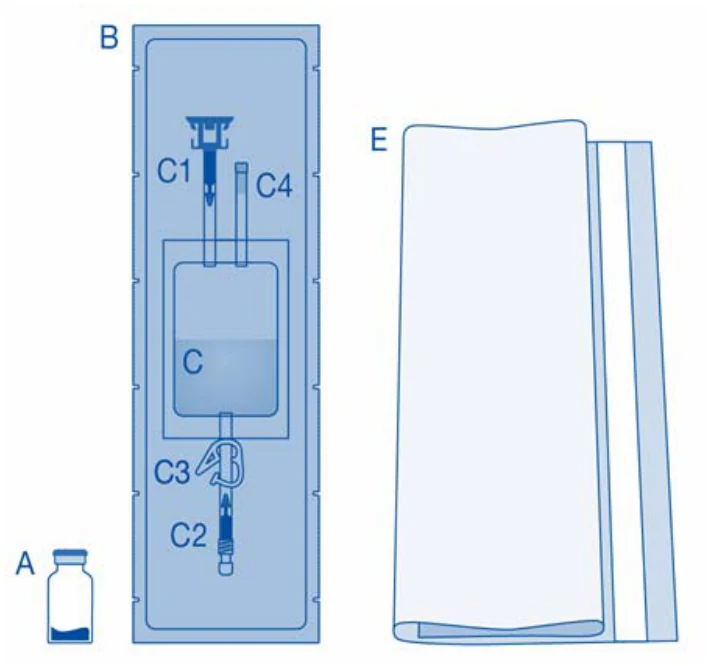
| Main constituent | Description |
| A | Vial with powder |
| B | Protective cover |
| C | Solvent bag with 0.9% (9 mg/mL) sodium chloride solution |
| C1 | Vial connector with protective cap and break-open seal |
| C2 | Luer-Lock catheter connector with protective cap and break-open seal |
| C3 | Pressure clamp |
| C4 | Filling port without application function |
| E | Disposal bag |
Connecting the vial to the solvent bag
- 1. Lay out the disposal bag (E) ready for direct disposal of the set after instillation to prevent contamination.
- 2. Remove the flip-off cap from the vial (A) and disinfect the stopper according to local
regulations.
- 3. Tear open the protective cover (B) of the solvent bag (C) and remove the protective cover completely.
- 4. Remove the protective cap from the vial connector (C1).
- 5. Push the connector onto the vial up to the stop.
Mixing the powder with the solvent
- 6. Bend the break-open seal inside the tube of the vial connector (C1) up and down multiple times to break the seal.
- 7.
Hold the solvent bag so that the vial is below it.
Squeeze the solvent bag multiple times to transfer enough solvent into the vial.
Make sure that the vial is not filled completely to allow for the subsequent transfer of the solution into the solvent bag. Some solvent may remain inside the bag.
Swirl the vial slowly to dissolve the medicinal product with the solvent.
The contents of the vial must dissolve to form a blue-purple clear solution within 2 minutes.
- 8.
Turn the solvent bag upside down and hold it so that the vial is above it.
Hold the vial.
Squeeze the solvent bag multiple times until the vial is completely empty.
If any powder remains inside the vial, repeat steps 7 and 8.
From a microbiological point of view the medicinal product should be used immediately.
If the medicinal product is not used immediately, please see section 6.3 “Shelf life”.
Only use clear blue-purple solutions. The solution should not be administered at refrigerator temperature in order to prevent the patient from feeling the need to urinate resulting in a shortened exposure time.
Catheterisation
- 9.
Catheterise the patient according to local regulations and the instructions for use using a suitable catheter and lubricant.
Empty the urinary bladder using the catheter.
Connecting the catheter to the solvent bag
- 10.
Rotate and swirl the bag before connecting it.
Do not administer the solution at refrigerator temperature.
Remove the protective cap from the catheter connector (C2).
Connect the patient’s catheter with the catheter connector (C2) of the solvent bag.
Instillation
- 11.
Bend the break-open seal inside the tube of the catheter connector (C2) up and down multiple times to break the seal.
Hold the patient’s catheter steady while doing so.
- 12.
Hold the solvent bag with the vial upside down above the bag.
Squeeze the solvent bag gently with the other hand so that the medicinal product is slowly instilled into the patient’s urinary bladder.
Continue to squeeze until the solvent bag and the vial are empty.
- 13. Squeeze the remaining air out of the solvent bag to empty the catheter as much as possible.
After instillation
- 14. Closing the pressure clamp (C3) prevents a reflux of fluid into the catheter and minimises the risk of contamination. Alternatively, you can keep the solvent bag compressed while performing steps 15 and 16.
- 15. Immediately remove the catheter carefully from the bladder without disconnecting the solvent bag from the catheter when the instillation set is emptied. After the catheter has been removed, the solution should remain in the bladder for 1 – 2 hours. Avoid contamination from splashing droplets.
- 16.
Dispose of the product according to national regulations using the disposal bag.
The contents of the vial are intended for single use/single dose only. Any remaining solution must be disposed of.
7 MARKETING AUTHORISATION HOLDER
medac Gesellschaft für klinische Spezialpräparate mbH
Theaterstr. 6
22880 Wedel
Germany
Tel.: +49 4103 8006-0
Fax: +49 4103 8006-100
8 MARKETING AUTHORISATION NUMBER(S)
PL 11587/0090
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
Date of first authorisation: 08/04/2016
Date of latest renewal: 28/10/2020
10 DATE OF REVISION OF THE TEXT
16/01/2025