

Summary of Product Characteristics (SmPC) - Metoclopramide Hydrochloride 5 mg / ml solution for injection
1 NAME OF THE MEDICINAL PRODUCT
Metoclopramide hydrochloride 5 mg/ml Solution for injection
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
1 ml of solution for injection contains 5.25 mg of metoclopramide hydrochloride monohydrate (equivalent to 5 mg/ml of metoclopramide hydrochloride anhydrous)
2 ml of solution for injection contain 10.5 mg of metoclopramide hydrochloride monohydrate (equivalent to 10 mg/ml of metoclopramide hydrochloride anhydrous)
Excipient with known effect:
Sodium – 2.95 mg/ml (as sodium chloride)
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Solution for injection
Clear, colourless solution, free of visible particles.
pH: 4.0 to 5.5
Osmolality: 261 mOsmol/L
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Adult population
Metoclopramide hydrochloride injection is indicated in adults for:
- Prevention of post-operative nausea and vomiting (PONV)
- Symptomatic treatment of nausea and vomiting, including acute migraine induced nausea and vomiting
- Prevention of radiation induced nausea and vomiting (RINV).
Paediatric population
Metoclopramide hydrochloride injection is indicated in children (aged 1-18 years) for:
- Prevention of delayed chemotherapy induced nausea and vomiting (CINV) as a second line option
- Treatment of post-operative nausea and vomiting (PONV) as a second line option.
4.2 Posology and method of administration
Posology
All indications (adult patients)
For prevention of PONV a single dose of 10 mg is recommended.
For the symptomatic treatment of nausea and vomiting, including acute migraine induced nausea and vomiting and for the prevention of radiotherapy induced nausea and vomiting (RINV): the recommended dose is 10 mg, repeated up to three times daily.
The maximum recommended daily dose is 30 mg or 0.5 mg/kg body weight.
The injectable treatment duration should be as short as possible and transfer to oral or rectal treatment should be made as soon as possible.
Paediatric population
All indications (paediatric patients aged 1-18 years)
The recommended dose is 0.1 to 0.15 mg/kg body weight, repeated up to three times daily by intravenous route. The maximum dose in 24 hours is 0.5 mg/kg body weight.
Dosing table
| Age | Body weight | Dose | Frequency |
| 1-3 years | 10-14 kg | 1 mg | Up to 3 times daily |
| 3-5 years | 15-19 kg | 2 mg | Up to 3 times daily |
| 5-9 years | 20-29 kg | 2.5 mg | Up to 3 times daily |
| 9-18 years | 30-60 kg | 5 mg | Up to 3 times daily |
| 15-18 years | Above 60 kg | 10 mg | Up to 3 times daily |
For the treatment of established post operative nausea and vomiting (PONV) , the maximum treatment duration is 48 hours.
For the prevention of delayed chemotherapy induced nausea and vomiting (CINV), the maximum treatment duration is 5 days.
Method of administration
The solution can be administered intravenously or intramuscularly.
Intravenous doses should be administered as a slow bolus (at least over 3 minutes).
A minimal interval of 6 hours between two administrations is to be respected, even in case of vomiting or rejection of the dose (see section 4.4).
Special population
Elderly
In elderly patients, a dose reduction should be considered, based on renal and hepatic function and overall frailty.
Renal impairment:
In patients with end stage renal disease (creatinine clearance ≤ 15 ml/min), the daily dose should be reduced by 75%.
In patients with moderate to severe renal impairment (creatinine clearance 15-60 ml/min), the dose should be reduced by 50% (see section 5.2).
Hepatic impairment:
In patients with severe hepatic impairment, the dose should be reduced by 50% (see section 5.2).
Paediatric population
Metoclopramide is contraindicated in children aged less than 1 year (see section 4.3).
4.3 Contraindications
- Hypersensitivity to the active substance or to any of the excipients listed in section 6.1
- Gastrointestinal bleeding, mechanical obstruction or gastrointestinal perforation for which gastrointestinal motility constitutes a risk
- Known or suspected pheochromocytoma because of the risk of episodes of severe hypertension
- History of neuroleptic or metoclopramide induced tardive dyskinesia
- Epilepsy (increased crises frequency and intensity)
- Parkinson’s disease
- Combination with levodopa or dopaminergic agonists (see section 4.5)
- Known history of methaemoglobinaemia with metoclopramide or NADH cytochrome-b5 deficiency
- Use in children less than 1 year of age due to an increased risk of extrapyramidal disorders (see section 4.4)
4.4 Special warnings and precautions for use
Neurological disorders
Extrapyramidal disorders may occur, particularly in children and young adults and/or when high doses are used. These reactions occur usually at the beginning of the treatment and can occur after a single administration. Metoclopramide should be discontinued immediately in the event of extrapyramidal symptoms. These effects are generally reversible after treatment discontinuation, but may require a symptomatic treatment (benzodiazepines in children and/or anticholinergic anti-Parkinsonian medicinal products in adults).
The time interval, of at least 6 hours, between each metoclopramide administration, mentioned in section 4.2, should be respected, even in case of vomiting or rejection of the dose, in order to avoid overdose.
Prolonged treatment with metoclopramide may cause tardive dyskinesia, potentially irreversible, especially in the elderly. Treatment should not exceed 3 months because of the risk of tardive dyskinesia (see section 4.8). Treatment must be discontinued if clinical signs of tardive dyskinesia appear.
The neuroleptic malignant syndrome has been reported with metoclopramide in combination with neuroleptics as well as with metoclopramide monotherapy (see section 4.8). Metoclopramide should be discontinued immediately in the event of symptoms of neuroleptic malignant syndrome and appropriate treatment should be initiated.
Special care should be exercised in patients with underlying neurological conditions and in patients being treated with other centrally-acting medicinal products (see section 4.3)
Symptoms of Parkinson’s disease may also be exacerbated by metoclopramide.
Methaemoglobinemia
Methemoglobinemia which could be related to NADH cytochrome b5 reductase deficiency has been reported. In such cases, metoclopramide should be immediately and permanently discontinued and appropriate measures initiated (such as treatment with methylene blue).
Cardiac disorders
There have been reports of serious cardiovascular undesirable effects including cases of circulatory collapse, severe bradycardia, cardiac arrest and QT prolongation following administration of metoclopramide by injection, particularly via the intravenous route (see section 4.8).
Special care should be taken when administering metoclopramide, particularly via the intravenous route to the elderly population, to patients with cardiac conduction disturbances (including QT prolongation), patients with uncorrected electrolyte imbalance, bradycardia and those taking other medicinal products known to prolong QT interval.
Intravenous doses should be administered as a slow bolus (at least over 3 minutes) in order to reduce the risk of adverse effects (e.g. hypotension, akathisia).
Renal and hepatic impairment
In patients with renal impairment or with severe hepatic impairment, a dose reduction is recommended (see section 4.2).
This medicine contains less than 1 mmol sodium (23 mg) per ampoule, that is to say essentially ‘sodium-free’.
4.5 Interaction with other medicinal products and other forms of interaction
Contraindicated combination
Levodopa or dopaminergic agonists and metoclopramide have a mutual antagonism (see section 4.3).
Combination to be avoided
Alcohol potentiates the sedative effect of metoclopramide.
Combination to be taken into account
Due to the prokinetic effect of metoclopramide, the absorption of certain drugs may be modified.
Anticholinergics and morphine derivatives
Anticholinergics and morphine derivatives may have both a mutual antagonism with metoclopramide on the intestinal tract motility.
Central nervous system depressants (morphine derivatives, anxiolytics, sedative H1 antihistamines, sedative antidepressants, barbiturates, clonidine and related)
Sedative effects of Central Nervous System depressants and metoclopramide are potentiated.
Neuroleptics
Metoclopramide may have an additive effect with other neuroleptics on the occurrence of extrapyramidal disorders.
Serotonergic drugs
The use of metoclopramide with serotonergic drugs such as SSRIs may increase the risk of serotonin syndrome.
Digoxin
Metoclopramide may decrease digoxin bioavailability. Careful monitoring of digoxin plasma concentration is required.
Ciclosporin
Metoclopramide increases ciclosporin bioavailability (Cmax by 46% and exposure by 22%). Careful monitoring of ciclosporin plasma concentration is required. The clinical consequence is uncertain.
Mivacurium and suxamethonium
Metoclopramide injection may prolong the duration of neuromuscular block (through inhibition of plasma cholinesterase).
Strong CYP2D6 inhibitors
Metoclopramide exposure levels are increased when co-administered with strong CYP2D6 inhibitors such as fluoxetine and paroxetine. Although the clinical significance is uncertain, patients should be monitored for adverse reactions.
4.6 Fertility, pregnancy and lactation
Pregnancy
A large amount of data on pregnant women (more than 1000 exposed outcomes) indicates no malformative toxicity nor fetotoxicity. Metoclopramide can be used during pregnancy if clinically needed. Due to pharmacological properties (as other neuroleptics), in case of metoclopramide administration at the end of pregnancy, extrapyramidal syndrome in the newborn cannot be excluded. Metoclopramide should be avoided at the end of pregnancy. If metoclopramide is used, neonatal monitoring should be undertaken.
Breastfeeding
Metoclopramide is excreted in breast milk at a low level. Adverse reactions in the breast-fed baby cannot be excluded. Metoclopramide is contraindicated during breastfeeding. Discontinuation of metoclopramide treatment in breastfeeding women should be considered.
4.7 Effects on ability to drive and use machines
Metoclopramide may cause drowsiness, dizziness, dyskinesia and dystonias, which may affect vision and could also interfere with the ability to drive and operate machinery.
4.8 Undesirable effects
Adverse reactions listed by System Organ Class. Frequencies are defined using the following convention: very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1,000 to <1/100), rare (≥1/10000 to <1/1,000), very rare (<1/10,000), not known (cannot be estimated from the available data).
| System Organ Class | Frequency | Adverse reactions |
| Blood and lymphatic system disorders | ||
| Not known | Methaemoglobinaemia, which could be related to NADH cytochrome b5 reductase deficiency, particularly in neonates (see section 4.4). Sulfhaemoglobinaemia, mainly with concomitant administration of high doses of sulphur-releasing medicinal products | |
| Immune system disorders | ||
| Uncommon | Hypersensitivity | |
| Not known | Anaphylactic reaction (including anaphylactic shock, particularly with the intravenous formulation) | |
| Endocrine disorders* | ||
| Uncommon | Amenorrhea, Hyperprolactinemia | |
| Rare | Galactorrhoea | |
| Not known | Gynaecomastia | |
| Psychiatric disorders | ||
| Common | Depression | |
| Uncommon | Hallucinations | |
| Rare | Confused state | |
| Nervous system disorders | ||
| Very common | Somnolence | |
| Common | Extrapyramidal disorders (especially in children and young adults and/or when the recommended dose is exceeded, even after administration of a single dose of the medicinal product) (see section 4.4), Parkinsonism, Akathisia | |
| Uncommon | Dystonia, Dyskinesia, Decreased consciousness | |
| Rare | Convulsion especially in epileptic patients | |
| Not known | Tardive dyskinesia which may be persistent, during or after long-term treatment, especially in elderly patients (see section 4.4), Malignant neuroleptic syndrome (see section 4.4) | |
| Cardiac disorders | ||
| Uncommon | Bradycardia, especially with intravenous formulation | |
| Not known | Cardiac arrest, occurring shortly after injectable use, and that may follow bradycardia (see section 4.4); Atrioventricular block, sinus arrest particularly with the intravenous formulation; Extended Electrocardiogram QT; Torsades de pointes | |
| Vascular disorders | ||
| Common | Hypotension, especially with the intravenous formulation | |
| Not known | Shock, syncope following injectable use, Acute hypertension in patients with pheochromocytoma (see section 4.3) | |
| Gastrointestinal disorders | ||
| Common | Diarrhoea | |
| General disorders and administration site conditions | ||
| Common | Asthenia | |
* Endocrine disorders following long-term treatment with regard to hyperprolactinemia (amenorrhea, galactorrhoea, gynecomastia).
The following reactions, sometimes associated, occur more frequently when high doses are used:
- Extrapyramidal symptoms: acute dystonia and dyskinesia, parkinsonian syndrome, akathisia, even after administration of a single dose of the medicinal product, especially in children and young adults (see section 4.4).
- Sleepiness, reduced consciousness, confusion, hallucinations.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Symptoms
Extrapyramidal disorders, somnolence, decreased consciousness, confusion, hallucinations and cardio-respiratory arrest may occur.
Treatment
In the case of extrapyramidal symptoms, whether or not related to overdosing, the treatment is only symptomatic (benzodiazepines in children and/or anticholinergic anti-Parkinsonian medicinal products in adults).
Symptomatic treatment and continuous monitoring of cardiovascular and respiratory functions should be performed in accordance with the clinical condition.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: gastric motility modifiers or prokinetics, ATC code: A03FA01
Metoclopramide is a substituted benzamide of the neuroleptic class, mainly used because of its anti- emetic properties.
The anti-emetic activity results from two mechanisms of action:
- Antagonism of the dopamine D2 receptors in the chemoceptor trigger zone and in the vomiting centre in the medulla involved in vomiting induced by apomorphine.
- Antagonism of the serotonergic 5-HT3 receptors and agonism of the 5-HT4 receptors involved in vomiting induced by chemotherapy.
5.2 Pharmacokinetic properties
Absorption
After oral and intramuscular administration, the relative bioavailability as compared to the intravenous use, is of 60 to 100%. Peak plasma levels are reached within 0.5 to 2 hours. After rectal administration, the bioavailability is lower (53 to 72%) and the maximum serum concentrations are reached later (2 to 3 hours).
Distribution
Metoclopramide distribution is large and quick.
Biotransformation and Elimination
Metoclopramide is excreted primarily in the urine, both in the natural form as in sulphate or glucuronide form. The main metabolite is N-4 sulphur conjugate.
The plasma elimination half-life is 5 to 6 hours, regardless of route of administration.
Renal impairment
The clearance of metoclopramide has been reduced to 70% in patients with severe renal impairment, while the plasma elimination half-life is increased (approximately 10 hours at a creatinine clearance 10-50 ml/minute and 15 hours at a creatinine clearance <10 ml/minute).
Hepatic impairment
In patients with hepatic cirrhosis, accumulation of metoclopramide was observed, accompanied with a 50% reduction in plasma clearance.
5.3 Preclinical safety data
These data do not indicate the need of special precautions beyond those already previously mentioned.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Sodium chloride
Hydrochloric acid (for pH adjustment)
Water for injections
6.2 Incompatibilities
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
This medicinal product must not be mixed with other medicinal products except those mentioned in section 6.6.
6.3 Shelf life
3 years.
For single use only. After first opening, the product should be used immediately.
6.4 Special precautions for storage
Keep the ampoules in the outer carton to protect from light.
Do not refrigerate or freeze.
6.5 Nature and contents of container
Type I, colourless glass ampoules, with 2 ml capacity, in packs of 10 ampoules.
6.6 Special precautions for disposal
No special requirements for disposal. Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
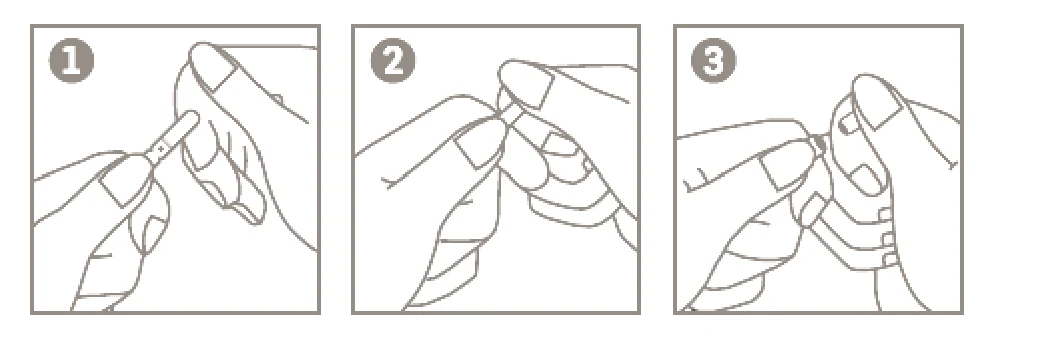
Instruction to open the OPC (One-Point-Cut) ampoules
- 1. Hold the body of the ampoule between the thumb and the index finger, with the point face up;
- 2. Place the index finger of the other hand supporting the upper part of the ampoule. Place the thumb in order to cover the point;
- 3. With the index fingers close to each other, press in the area of the point, to open the ampoule.
7 MARKETING AUTHORISATION HOLDER
SVP Pharma Ltd
Unit 1, 39 Mahoney Green
Rackheath, Norwich, NR13 6JY
United Kingdom
8 MARKETING AUTHORISATION NUMBER(S)
PL 56639/0004
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
Date of first authorisation: 30 September 2024
10 DATE OF REVISION OF THE TEXT
29/09/2026