

Summary of medicine characteristics - Menitorix powder and solvent for solution for injection
1 NAME OF THE MEDICINAL PRODUCT
Menitorix - Powder and solvent for solution for injection
Haemophilus type b and Meningococcal group C conjugate vaccine
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
After reconstitution, each 0.5 ml dose contains:
Haemophilus type b polysaccharide
(polyribosylribitol phosphate) 5 micrograms
conjugated to tetanus toxoid as carrier protein 12.5 micrograms
Neisseria meningitidis group C (strain C11) polysaccharide 5 micrograms conjugated to tetanus toxoid as carrier protein 5 micrograms
Excipients with known effect:
This product contains sodium 75 micromol per dose (see section 4.4)
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Powder and solvent for solution for injection
White powder and a clear colourless solvent
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Active immunization of infants from the age of 2 months and toddlers up to the age of 2 years for the prevention of invasive diseases caused by Haemophilus influenzae type b (Hib) and Neisseria meningitidis group C (MenC).
See also section 4.4.
4.2 Posology and method of administration
Posology
Menitorix should be used in accordance with official recommendations.
Primary vaccination in infants:
Alternative vaccination schedules in infants are available with Menitorix.
Three dose primary series
The vaccination schedule consists of three primary doses, each of 0.5ml which should be administered from 2 months up to 12 months of age with an interval of at least 1 month between doses (see section 5.1).
Two-dose primary series
The vaccination schedule, consisting of two primary doses, each of 0.5ml, may be given from 3 months up to 12 months of age with an interval of at least 2 months between doses (see section 5.1).
Preterm infants born between 25 weeks and 36 weeks of gestational age Three primary doses, each of 0.5ml, should be administered from 2 months up to 12 months of age with an interval of at least 2 months between doses (see sections 4.4 and 5.1).
There are no data on the use of Menitorix for one or two doses of the primary vaccination course and other Hib and/or MenC conjugate vaccines for other dose(s). It is recommended that infants who receive Menitorix for the first dose should also receive this vaccine for the second and third doses of the primary vaccination course.
Booster vaccination:
After primary vaccination in infancy, booster doses of Hib and MenC must be administered. In children who received an acellular pertussis combination vaccine containing Hib in the primary infant immunisation series the Hib booster dose should be given before the age of 2 years.
A single (0.5ml) dose of Menitorix may be used to boost immunity to Hib and MenC in children who have previously completed a primary immunisation series with Menitorix or with other Hib or MenC conjugate vaccines (see section 5.1). The booster dose of Menitorix should be given before the age of 2 years. The timing of the booster dose should be from the age of 12 months onwards and at least 6 months after the last priming dose. In children primed with 2 doses of Menitorix, the timing of the booster should be at least 5 months after the last priming dose.
Paediatric population
The safety and efficacy of Menitorix in children over 2 years of age have not yet been established.
Method of administration
For instructions on reconstitution of the medicinal product before administration, see section 6.6.
Menitorix should be given by intramuscular injection only, preferably in the anterolateral thigh region. In children 12 to 24 months of age, the vaccine may be administered in the deltoid region (see also sections 4.4 and 4.5). Menitorix should under no circumstances be administered intravascularly, intradermally or subcutaneously.
4.3 Contraindications
Hypersensitivity to the active substances, including tetanus toxoid (see section 2), or to any of the excipients listed in section 6.1.
Hypersensitivity reaction after previous administration of Menitorix. Acute severe febrile illness. The presence of a minor infection is not a contraindication for vaccination.
4.4 Special warnings and precautions for use
As with all injectable vaccines, appropriate medical treatment and supervision should always be readily available in case of a rare anaphylactic event following the administration of the vaccine.
Vaccination should be preceded by a review of the medical history (especially with regard to previous vaccination and possible occurrence of undesirable events) and a clinical examination.
The vaccine should be given with caution to individuals with thrombocytopenia or any coagulation disorder. No data are available on subcutaneous administration of Menitorix, therefore the possibility of any toxicity or reduced efficacy that might occur with this route of administration is unknown.
Menitorix will only confer protection against Haemophilus influenzae type b and Neisseria meningitidis group C. As for any vaccine, Menitorix may not completely protect against the infections it is intended to prevent in every vaccinated individual.
There are no data available on administration of Menitorix in toddlers not already primed with Hib and MenC conjugates.
The duration of protection in a vaccinated individual against Meningococcal group C disease is unknown. However a decline over time has been observed in the percentages of subjects with at least 1:8 rSBA-MenC titres (see section 5.1).
No data are available on the use of Menitorix in immunodeficient subjects. In individuals with impaired immune responsiveness (whether due to the use of immunosuppressive therapy, a genetic defect, human immunodeficiency virus (HIV) infection, or other causes) a protective immune response to Hib and MenC conjugate vaccines may not be obtained. Individuals with complement deficiencies and individuals with functional or anatomical asplenia may mount an immune response to Hib and MenC conjugate vaccines; however the degree of protection that would be afforded is unknown.
Individuals with familial complement deficiencies (for example, C3 or C5 deficiencies) and individuals receiving treatments that inhibit terminal complement activation (for example, eculizumab) are at increased risk for invasive disease caused by Neisseria meningitidis group C, even if they develop antibodies following vaccination with Menitorix.
Although symptoms of meningism such as neck pain/stiffness or photophobia have been reported following administration of other MenC conjugate vaccines, there is no evidence that MenC conjugate vaccines cause meningitis. Clinical alertness to the possibility of co-incidental meningitis should be maintained.
The potential risk of apnoea and the need for respiratory monitoring for 48-72h should be considered when administering the primary immunisation series to very premature infants (born ≤ 28 weeks of gestation) and particularly for those with a previous history of respiratory immaturity.
As the benefit of the vaccination is high in this group of infants, vaccination should not be withheld or delayed.
Immunisation with this vaccine does not substitute for routine tetanus immunisation.
Since Hib capsular polysaccharide antigen is excreted in the urine, a positive urine antigen test can be observed within 1-2 weeks following vaccination. Other diagnostic tests, not based on the detection of the capsular antigen in urine, should be used to confirm Hib disease during this period.
The solvent of the vaccine contains less than 1mmol sodium (23 mg) per dose, i.e. essentially “sodium-free”.
4.5 Interaction with other medicinal products and other forms of interaction
Menitorix must not be mixed with any other vaccine in the same syringe.
Different injectable vaccines should always be given at different injection sites.
In various studies with licensed monovalent meningococcal group C conjugate vaccines, concomitant administration with combinations containing diphtheria, tetanus and acellular pertussis components (with or without inactivated polio viruses, hepatitis B surface antigen or Hib conjugate [e.g. DTPa-HBV-IPV-Hib*]), has been shown to result in lower serum bactericidal antibody (SBA) geometric mean titres (GMT) compared to separate administrations or to co-administration with whole cell pertussis vaccines. The proportions reaching SBA titres of at least 1:8 are not affected. At present, the potential implications of these observations for the duration of protection are not known.
In clinical trials of primary vaccination series, Menitorix was administered concomitantly (into opposite thighs) with a DTPa-HBV-IPV vaccine. Responses to all the co-administered antigens were satisfactory and were similar to those achieved in control groups that received DTPa-HBV-IPV-Hib* concomitantly with a MenC conjugate vaccine (MenCC) or DTPa-HBV-IPV* concomitantly with a Hib conjugate vaccine and no MenCC. The immune response to the Hib and MenC components of Menitorix was only assessed in primary vaccination clinical studies that employed co-administration with DTPa-IPV* or DTPa-HBV-IPV* vaccines.
In a trial of primary vaccination, concomitant administration of Menitorix with DTPa-HBV-IPV* and a 7-valent or 10-valent pneumococcal saccharide conjugated vaccine (the three injections were made into anatomically distant sites) gave similar immune responses to the seven or ten pneumococcal serotypes as achieved in groups that received DTPa-HBV-IPV* concomitantly with Hib (conjugated to tetanus toxoid) and a 7-valent or 10-valent pneumococcal saccharide conjugated vaccine
As a booster dose, Menitorix can be given concomitantly with a 7-valent or 10-valent pneumococcal saccharide conjugated vaccine or with a first dose of combined measles, mumps and rubella (MMR) vaccine. Clinical studies demonstrated that the immune responses and the safety profiles of the co-administered vaccines were unaffected.
There are no data on concomitant use of Menitorix with whole cell pertussis and oral poliomyelitis vaccines, however, concomitant use of whole cell pertussis and oral poliomyelitis vaccines with monovalent MenC and Hib conjugate vaccines did not result in interferences.
*GlaxoSmithKline vaccine
4.6 Fertility, pregnancy and lactation
Menitorix is not intended for use in adults. Information on the safety of the vaccine when used during pregnancy or lactation is not available.
4.7 Effects on ability to drive and use machines
Not relevant
4.8 Undesirable effects
Summary of the safety profile
In clinical trials, Menitorix has been administered as a 3 or 2-dose primary series (N=2,452) or as a booster (N=2,190) dose. When Menitorix was administered as a primary vaccination course, a DTPa-HBV-IPV* vaccine (N=2077) or a DTPa-IPV vaccine* (N=375) was administered concomitantly.
Adverse reactions occurring during these studies were mostly reported within 48 hours following vaccination.
In two clinical trials (N=578), Menitorix was administered concomitantly with Measles, Mumps, Rubella (MMR) vaccine. In one of these trials, the incidences of adverse reactions observed in subjects (N=102) who received Menitorix concomitantly with MMR* were similar to those observed in the group who received MMR alone (N=91) or Menitorix alone (N=104) (see sections 4.5 and 5.1).
In another clinical study, Menitorix was administered as a 3-dose primary series (2, 4, 6 months of age) in 163 preterm infants (gestational age <36 weeks including 56 infants < 31 weeks) and 150 full-term infants (gestational age ≥36 weeks). 154 preterm infants and 144 full-term infants received a booster dose at 16 to 18 months of age.
The safety and reactogenicity profile of Menitorix was similar in preterm and full-term infants.
Tabulated list of adverse reactions
Adverse reactions considered as being at least possibly related to vaccination have been categorised by frequency per dose as follows:
Very common (≥1/10)
Common (≥1/100, <1/10)
Uncommon (≥1/1,000, <1/100)
Rare (≥1/10,000, <1/1,000)
Very rare (<1/10,000),
Not known (cannot be estimated from the available data)
| System Organ Class | Frequency | Adverse reactions |
| Clinical trials | ||
| Metabolism and nutrition disorders | Very common | Decreased appetite |
| Psychiatric disorders | Very common | Irritability |
| Uncommon | Crying | |
| Rare | Insomnia | |
| Nervous system disorders | Very common | Drowsiness |
| Gastrointestinal disorders | Uncommon | Diarrhoea, vomiting |
| Rare | Abdominal pain | |
| Skin and subcutaneous tissue disorders | Uncommon | Atopic dermatitis, rash ≥ |
General disorders and administration site conditions | Very common | Fever (rectal 38ºC), injection site reactions (swelling, pain, redness) |
| Common | Injection site reactions (including induration and nodule) | |
| Uncommon | Fever (rectal > 39.5ºC) | |
| Rare | Malaise | |
| Post-marketing experience | ||
| Blood and lymphatic system disorders | Not known | Lymphadenopathy |
| Immune system disorders | Not known | Allergic reactions (including urticaria and anaphylactoid reactions) |
| Nervous system disorders | Not known | Febrile seizures, hypotonia, headache, dizziness ≤ |
| Respiratory, thoracic and mediastinal disorders | Not known | Apnoea in very premature infants ( 28 weeks of gestation) (see section 4.4) |
The following adverse reactions have not been reported in association with administration of Menitorix but have occurred very rarely during routine use of licensed meningococcal group C conjugate vaccines:
severe skin reactions, collapse or shock-like state (hypotonic-hyporesponsiveness episode), faints, seizures in patients with pre-existing seizure disorders, hypoaesthesia, paraesthesia, relapse of nephrotic syndrome, arthralgia, petechiae and/or purpura.
*GlaxoSmithKline combination vaccine
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
No case of overdose has been reported.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: bacterial vaccines, ATC code: J07AG53
Antibody against Haemophilus influenzae type b (anti- polyribosylribitol phosphate [anti-PRP]) was measured with an enzyme-linked immunosorbent assay (ELISA). Antibody against Neisseria meningitidis group C was measured by a serum bactericidal activity assay using rabbit complement (rSBA-MenC).
Immunogenicity after primary vaccination course
Six clinical trials have evaluated the antibody responses at one month after two doses and after completion of a 3-dose primary vaccination course of Menitorix given at approximately 2, 3, 4 months or 2, 4, 6 months to 1163 full-term infants. Menitorix was always co-administered with GlaxoSmithKline combined DTPa-IPV or DTPa-HBV-IPV. In 349 of these infants, it was also co-administered with a 7-valent or 10-valent pneumococcal conjugate vaccine.
Percentages of subjects with antibody titres ≥ assay cut-off one month after primary vaccination with Menitorix were as follows:
| Antibody | 2-3-4 month schedule | ||
| After two doses | After three doses | ||
| Anti-PRP | N | 93 | 702 |
% ≥0.15 micrograms/ml | 96.8 | 100.0 | |
| % ≥1 micrograms/ml | 76.3 | 98.0 | |
GMC (micrograms/ml) | 3.40 | 14.25 | |
| rSBA-MenC* | N | 93 | 688 |
| % ≥1:8 | 100.0 | 99.3 | |
| % ≥1:128 | 98.9 | 94.5 | |
| GMT | 679.6 | 924.8 | |
N= number of subjects with available results
%= percentage of subjects with titres equal to or above the cut-off GMC or GMT= geometric mean antibody concentration or titre *= testing performed at GSK laboratories
| Antibody | 2-4-6 month schedule | ||
| After two doses | After three doses | ||
| Anti-PRP | N | 457 | 453 |
% ≥0.15 micrograms/ml | 94.1 | 99.3 | |
| % ≥1 micrograms/ml | 67.2 | 96.9 | |
GMC (micrograms/ml) | 2.06 | 12.41 | |
| rSBA-MenC* | N | 445 | 368 |
| % ≥1:8 | 98.4 | 99.7 | |
| % ≥1:128 | 90.6 | 97.0 | |
| GMT | 581 | 1735.0 |
N= number of subjects with available results
%= percentage of subjects with titres equal to or above the cut-off GMC or GMT= geometric mean antibody concentration or titre *= testing performed at GSK laboratories
In addition, the immunogenicity of Menitorix was evaluated in a clinical study in which the subjects were primed with two doses of Menitorix (co-administered with DTPa-HBV-IPV) at 3 and 5 months of age.
Percentages of subjects with antibody titres ≥ assay cut-off one month after a 3-5 month primary vaccination course with Menitorix were as follows:
| 3-5 month schedule | |
| Anti-PRP | |
| N | 325 |
| % ≥0.15 micrograms/ml | 96.9 |
| % ≥1 micrograms/ml | 78.8 |
| GMC (micrograms/ml) | 4.24 |
| rSBA-MenC* | |
| N | 323 |
| % ≥1:8 | 99.1 |
| % ≥1:128 | 82.4 |
| GMT | 466.1 |
N= number of subjects with available results
%= percentage of subjects with titres equal to or above the cut-off GMC or GMT= geometric mean antibody concentration or titre
*= testing performed at GSK laboratories
Immunogenicity after booster vaccination
Immune responses to a booster dose of Menitorix may vary according to the vaccines used for the primary series. It is not known if the differences that have been observed are of any clinical significance. See also below regarding antibody persistence after booster doses.
In five clinical studies, antibody responses were evaluated one month after a booster vaccination with Menitorix in children who had received three doses of Menitorix, Menjugate or Meningitec or two doses of NeisVac-C in infancy. The rSBA-MenC immune response to a booster dose of Menitorix was lower after a three-dose course of a MenC-CRM197197 conjugate vaccine in infancy (i.e. Menjugate or Meningitec) compared to administration of a MenC-TT conjugate vaccine in infancy (i.e. two doses of NeisVac-C or three doses of Menitorix). It should be noted that immune responses to a booster dose of Menitorix after administration of two doses of a MenC-CRM197197 vaccine in infancy have not been documented and that responses may differ from the data shown in the table.
In these clinical studies, the booster dose of Menitorix was administered alone, co-administered with GlaxoSmithKline combined DTPa-HBV-IPV vaccine, or co-administered with GlaxoSmithKline combined DTPa-HBV-IPV vaccine and a 7-valent or 10-valent pneumococcal conjugate vaccine or co-administered with measles, mumps, rubella GlaxoSmithKline combined vaccine (MMR).
Percentages of subjects with antibody titres ≥ assay cut-off one month after booster vaccination with Menitorix were as follows:
| Primary vaccination history | ||||
Subjects primed with 3 doses of Menitorix* | Subjects primed with 3 doses of Meningitec + Pediacel | Subjects primed with 3 doses of Meningitec** or Menjugate** | Subjects primed with 2 doses of NeisVac-C** | |
| Anti-PRP antibodies | ||||
| N | 780 | 114 | 305 | 165 |
% ≥0.15 micrograms/ml | 100 | 100 | 100 | 100 |
% ≥1 micrograms/ml | 100 | 100 | 99.0 | 98.8 |
GMC (micrograms/ml) | 70.14 | 44.27 | 38.18 | 77.15 |
| rSBA-MenC*** | ||||
| N | 624 | 114 | 304 | 167 |
| % ≥1:8 | 99.5 | 95.6 | 97.7 | 99.4 |
| % ≥1:128 | 98.2 | 86.0 | 89.1 | 99.4 |
| GMT | 3486.4 | 477.9 | 575.1 | 11710.5 |
N= number of subjects with available results
GMC or GMT= geometric mean antibody concentration or titre %= percentage of subjects with titres equal to or above the cut-off *= co-administered with GlaxoSmithKline combined DTPa-IPV vaccines **= co-administered with DTPa-Hib-TT containing vaccines
***= testing performed at GSK laboratories
In one clinical study, the antibody responses were evaluated one month after a booster vaccination with Menitorix in children primed in infancy either with two doses of Menitorix or a licensed meningococcal C-TT conjugate (MenC-TT) vaccine.
Antibody responses one month after administration of a booster dose of Menitorix (ATP cohort for immunogenicity) were as follows:
| Primary vaccination history | |
Subjects primed with 2 doses of Menitorix* | |
| Anti-PRP antibodies | |
| N | 311 |
| % ≥0.15 micrograms/ml | 100 |
| % ≥1 micrograms/ml | 99.4 |
| GMC (micrograms/ml) | 30.49 |
| rSBA-MenC** | |
| N | 310 |
| % ≥1:8 | 100 |
| % ≥1:128 | 98.1 |
| GMT | 1861.8 |
N= number of subjects with available results
GMC or GMT= geometric mean antibody concentration or titre
%= percentage of subjects with titres equal to or above the cut-off *= co-administered with DTPa-HBV-IPV/Hib vaccine
**= testing performed at GSK laboratories
Immunogenicity in preterm infants
In one clinical study, the immunogenicity of Menitorix in 143 preterm infants (gestational age <36 weeks including 45 infants < 31 weeks) and 144 full-term infants (gestational age ≥36 weeks) was evaluated following a 3-dose primary vaccination course at 2, 4 and 6 months of age. Immunogenicity was evaluated in 135 preterm and 138 full-term infants following a booster dose at 16 to 18 months of age.
Antibody responses one month after completion of a 3-dose primary vaccination course and one month after administration of a booster dose of Menitorix in preterm and full-term infants (ATP cohort for immunogenicity) were as follows:
| Preterm | Full-term | |||
| Post-primary | Post-booster | Post-primary | Post-booster | |
| Anti-PRP antibodies | ||||
| N | 140 | 132 | 142 | 134 |
| % ≥0.15 µg/ml | 99.3 | 100 | 99.3 | 100 |
| % ≥1 µg/m | 95.0 | 100 | 94.4 | 100 |
| GMC (µg/ml) | 10.44 | 50.34 | 10.47 | 54.62 |
| rSBA-MenC* | ||||
| N | 143 | 133 | 140 | 137 |
| % ≥1:8 | 99.3 | 99.2 | 100 | 99.3 |
| % ≥1:128 | 94.4 | 98.5 | 97.1 | 99.3 |
| GMT | 1055.9 | 4883.1 | 1346.2 | 5288.8 |
N= number of subjects with available results
GMC or GMT= geometric mean antibody concentration or titre %= percentage of subjects with titres equal to or above the cut-off *= testing performed at GSK laboratories
Antibody persistence
Antibody persistence without a booster dose:
Antibody persistence has been demonstrated for Hib in three clinical trials (N=217) with 98.2% of subjects having an anti-PRP concentration of ≥ 0.15 micrograms/ml at 11-18 months of age i.e. at 7-14 months following completion of a 3-dose primary series with Menitorix.
In three clinical trials (N=209), 92.3% of subjects had an SBA-MenC titre ≥ 1/8 at 11–18 months of age, i.e. at 7-14 months following completion of a 3-dose primary series with Menitorix. All subjects responded immunologically to a challenge dose of 10 µg of unconjugated group C meningococcal polysaccharide with a thirty-three-fold increase in SBA titres demonstrating the immune memory induced by the primary vaccination course.
Antibody persistence after a 2-dose primary vaccination course has been demonstrated for Hib and MenC in subjects aged 11-13 months and primed with Menitorix in infancy at 3-5 months of age. Following completion of the 2-dose primary series with Menitorix, 86.1% of the subjects (286/332) had anti-PRP titres ≥ 0.15 µg/ml and 94.5% of the subjects (308/326) had SBA-MenC titres ≥ 1:8.
Antibody persistence after a booster dose:
Antibody persistence was evaluated in subjects primed either with Menitorix or with co-administration of licensed meningococcal C conjugate and Hib containing vaccines and boosted with Menitorix.
In one long-term antibody persistence study, the antibody levels were evaluated in subjects primed either with Menitorix or with Meningitec both given as a 3-dose primary schedule and boosted with Menitorix. The results in the comparator group may not predict what would be seen with a 2-dose primary schedule of Meningitec followed by a booster dose of Menitorix.
Antibody levels at Month 1 post-booster and at Months 12, 24 and 48 post-booster persistence time-points (ATP cohort for persistence) were as follows:
| Primary vaccination history | Subjects primed with 3 doses of Menitorix1 (2, 3, 4 months) | Subjects primed with 3 doses of Meningitec2 (2, 3, 4 months) | ||||||
| Booster vaccination history | Menitorix3 (12-15 months) | Menitorix3 (12-15 months) | ||||||
Time-point (post-booster) Month | 1 | 12 | 24 | 48 | 1 | 12 | 24 | 48 |
| Anti-PRP antibodies | ||||||||
| N | 195 | 164 | 194 | 197 | 57 | 48 | 56 | 58 |
| % ≥0.15 micrograms/ml | 100 | 100 | 99.5 | 100 | 100 | 100 | 98.2 | 100 |
| GMC (micrograms/ml) | 90.10 | 7.45 | 4.93 | 3.82 | 39.10 | 3.56 | 2.08 | 1.67 |
| rSBA-MenC* | ||||||||
| N | 195 | 166 | 187 | 194 | 58 | 45 | 56 | 58 |
| %≥1:8 | 99.5 | 89.2 | 65.8 | 59.3 | 96.6 | 66.7 | 35.7 | 44.8 |
| %>1:128 | 99.0 | 53.0 | 41.7 | 29.9 | 86.2 | 24.4 | 10.7 | 8.6 |
| GMT | 2537.0 | 124.1 | 47.9 | 30.4 | 507.0 | 30.6 | 12.1 | 11.3 |
N= number of subjects with available results
GMC or GMT= geometric mean antibody concentration or titre %= percentage of subjects with titres equal to or above the cut-off 1 co-administered with GlaxoSmithKline combined DTPa-IPV 2 co-administered with DTPa-IPV/Hib-TT
3 co-administered with GlaxoSmithKline combined MMR * testing performed at GSK laboratories
In another long-term antibody persistence study, the subjects were primed either with 3 doses of Menitorix or with 2 doses of NeisVac-C. All subjects were boosted with Menitorix.
The antibody levels at Months 18, 30, 42, 54 and 66 post-booster persistence time-points (ATP cohort for persistence) were as follows:
Primary vaccination history | Subjects primed with 3 doses of Menitorix1 (2, 4, 6 months) | ||||
Subjects primed with 2 doses of
NeisVac-C2 (2, 4 months)
Booster vaccination history | Menitorix (13-14 months) | ||||
Menitorix (13-14 months)
Persistence time-point (post- booster) (Month) | 18 | 30 | 42 | 54 | 66 | 18 | 30 | 42 | 54 |
66
Anti-PRP antibodies
| N | 46 | 47 | 47 | 47 | 47 | 102 | 98 | 101 | 102 |
101
% ≥0.15 micrograms/ml | 100 | 100 | 100 | 100 | 100 | 99.0 | 99.0 | 99.0 | 99.0 |
100
GMC (micrograms/ml) | 2.94 | 1.92 | 1.70 | 1.51 | 1.60 | 5.49 | 3.52 | 3.00 | 2.74 |
2.62 rSBA-MenC*
| N | 42 | 45 | 47 | 47 | 46 | 88 | 93 | 101 | 102 |
101
| % ≥1:8 | 97.6 | 82.2 | 80.9 | 78.7 | 82.6 | 96.6 | 94.6 | 96.0 | 97.1 |
94.1
| % ≥1:128 | 59.5 | 57.8 | 61.7 | 55.3 | 60.9 | 84.1 | 77.4 | 79.2 | 80.4 |
68.3
| GMT | 224.8 | 113.3 | 110.5 | 93.5 | 121.5 | 737.6 | 404.9 | 380.9 | 342.9 |
227.6
N= number of subjects with available results
GMC or GMT= geometric mean antibody concentration or titre %= percentage of subjects with titres equal to or above the cut-off 1 co-administered with GlaxoSmithKline combined DTPa-HBV-IPV 2 co-administered with DTPa-HBV-IPV/Hib-TT (2, 4, 6 months) or with DTPa-
HBV-IPV/Hib-TT (2, 6 months) and DTPa-IPV/Hib-TT (4 months) (GlaxoSmithKline combined vaccines)
* testing performed at GSK laboratories
Another study evaluated the long-term antibody persistence in children up to 6 years of age who previously received a full vaccination course (primary and booster vaccination) with Menitorix or MenC conjugate vaccines (Meningitec or NeisVac-C) co-administered with a GlaxoSmithKline combined DTPa vaccine (DTPa-HBV-IPV/Hib or DTPa-IPV/Hib or DTPa-HBV-IPV or DTPa-IPV) and a 7-valent or 10-valent pneumococcal conjugated vaccines. The percentage of subjects with rSBA-MenC* titres ≥1:8 at 6 years of age was at least 25.4% in the children that received Menitorix, 24.2% in the children that received Meningitec and 40.1% in the children that received NeisVac-C as a booster in the second year of life. The percentage of subjects with anti-PRP concentrations ≥0.15 μg/mL at 6 years of age was 100% in children vaccinated with Menitorix.
*testing performed at Public Health England (PHE) in the United Kingdom.
Post-marketing surveillance following an immunisation campaign in the UK
Estimates of vaccine effectiveness from the UK’s routine immunisation programme (using various quantities of three meningococcal group C conjugate vaccines) covering the period from introduction at the end of 1999 to March 2004 demonstrated the need for a booster dose after completion of the primary series (three doses administered at 2, 3 and 4 months). Within one year of completion of the primary series, vaccine effectiveness in the infant cohort was estimated at 93% (95% confidence intervals 67-99). However, more than one year after completion of the primary series, there was clear evidence of waning protection.
Up to 2007, the overall estimates of effectiveness in age cohorts from 1-18 years that received a single dose of meningococcal group C conjugate vaccine during the initial catch-up vaccination programme in the UK fall between 83 and 100%. The data show no significant fall in effectiveness within these age cohorts when comparing time periods less than a year or one year or more since immunisation.
5.2 Pharmacokinetic properties
Evaluation of pharmacokinetic properties is not required for vaccines.
5.3 Preclinical safety data
Non-clinical data reveal no special hazard for humans based on conventional studies of safety pharmacology and single and repeated dose toxicity studies.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Powder:
Trometamol
Sucrose
Solvent:
Sodium chloride
Water for injections
6.2 Incompatibilities
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
6.3 Shelf life
3 years.
After reconstitution, the vaccine should be administered promptly or kept in the refrigerator (2°C – 8°C). If it is not used within 24 hours, do not administer the vaccine.
Experimental data show that the reconstituted vaccine could also be kept up to 24 hours at ambient temperature (25°C). If it is not used within 24 hours, do not administer the vaccine.
6.4 Special precautions for storage
Store in a refrigerator (2°C – 8°C).
Do not freeze
Store in the original package in order to protect from light.
For storage conditions after reconstitution of the medicinal product, see section 6.3.
6.5 Nature and contents of container
Powder in a vial (type I glass) with a stopper (butyl rubber), 0.5 ml of solvent in a pre-filled syringe (type I glass) with a plunger stopper (butyl rubber) with or without separate needles in the following pack sizes:
- pack size of 1 vial of powder plus 1 pre-filled syringe of solvent with 2 separate needles or without needles
- pack size of 10 vials of powder plus 10 pre-filled syringes of solvent with 20 separate needles or without needles
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
Menitorix must be reconstituted by adding the entire contents of the pre-filled syringe of solvent to the vial containing the powder.
To attach the needle to the syringe, carefully read the instructions given with pictures 1 and 2. However, the syringe provided with Menitorix might be slightly different (without screw thread) than the syringe illustrated. In that case, the needle should be attached without screwing.
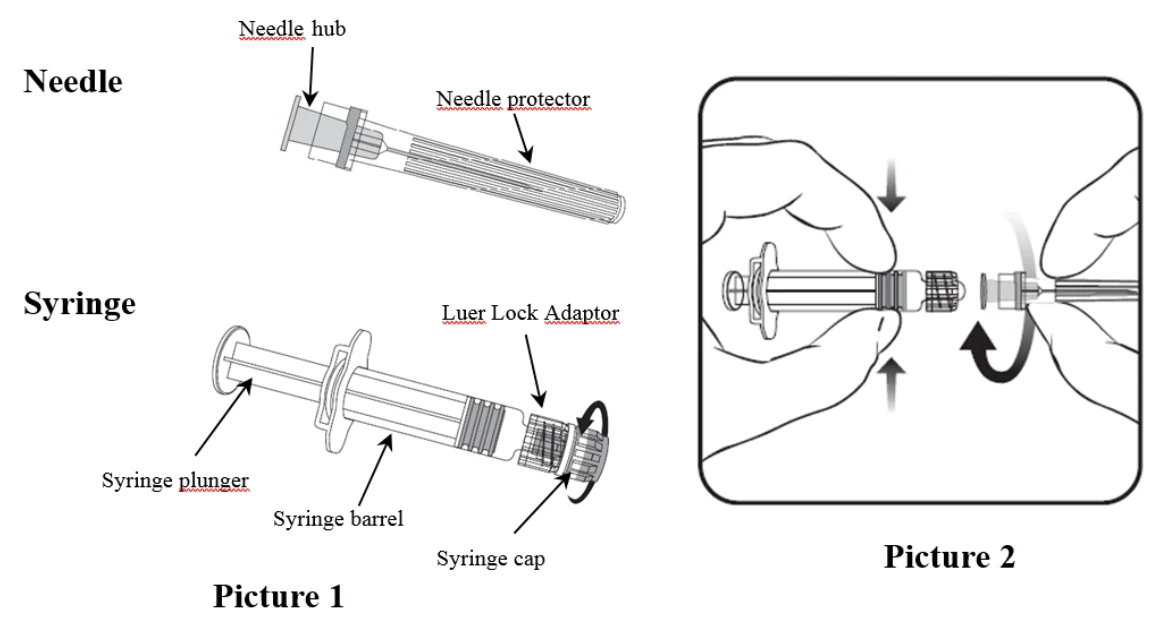
Always hold the syringe by the barrel, not by the syringe plunger or the Luer Lock Adaptor (LLA), and maintain the needle in the axis of the syringe (as illustrated in picture 2). Failure to do this may cause the LLA to become distorted and leak.
During assembly of the syringe, if the LLA comes off, a new vaccine dose (new syringe and vial) should be used.
- 1. Unscrew the syringe cap by twisting it anticlockwise (as illustrated in picture 1). Whether the LLA is rotating or not, please follow below steps:
- 2. Attach the needle to the syringe by gently connecting the needle hub into the LLA and rotate a quarter turn clockwise until you feel it lock (as illustrated in picture 2).
- 3. Remove the needle protector, which may be stiff.
- 4. Add the solvent to the powder. The mixture should be well shaken until the powder is completely dissolved in the solvent.
The reconstituted vaccine is a clear and colourless solution.
The reconstituted vaccine should be inspected visually for any foreign particulate matter and/or variation of physical aspect prior to administration. In the event of either being observed, do not administer the vaccine.
- 5. Withdraw the entire contents of the vial.
- 6. A new needle should be used to administer the vaccine. Unscrew the needle from the syringe and attach the injection needle by repeating step 2.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7. MARKETING AUTHORISATION HOLDER
SmithKline Beecham Ltd
79 New Oxford Street
London
WC1A 1DG
United Kingdom
Trading as:
GlaxoSmithKline UK
8 MARKETING AUTHORISATION NUMBER(S)
PL 10592/0217
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
19/12/2005
10 DATE OF REVISION OF THE TEXT
07/11/2024