

Summary of Product Characteristics (SmPC) - Illuccix 25 micrograms kit for Radiopharmaceutical Preparation
1 NAME OF THE MEDICINAL PRODUCT
Illuccix 25 micrograms kit for radiopharmaceutical preparation
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
The vial of powder for solution for injection contains 25 micrograms of gozetotide (as trifluoroacetate salt).
The radionuclide is not part of the kit.
Excipient with known effect
The vial of solvent contains 42 mg of sodium.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Kit for radiopharmaceutical preparation containing:
- One vial of powder for solution for injection: the vial contains a white lyophilised powder.
- One vial of solvent: the vial contains a clear, colourless solution.
- One empty vial: the vial is sterile, vacuum sealed and used for the radiolabelling of the kit.
For radiolabelling with gallium (68Ga) chloride solution.
pH (after reconstitution and radiolabelling): 4.0 – 5.0
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
This medicinal product is for diagnostic use only.
After radiolabelling of Illuccix with gallium (68Ga) chloride solution, gallium (68Ga) gozetotide is indicated for Positron Emission Tomography (PET) imaging scan for detection and localization of prostate-specific membrane antigen (PSMA)-positive lesions in adults with prostate cancer (PCa).
4.2 Posology and method of administration
This medicinal product should only be administered by trained healthcare professionals with technical expertise in using and handling nuclear medicine imaging agents and only in a designated nuclear medicine facility.
Posology
Adults
The recommended injected activity is 1.8–2.2 MBq per kilogram of body weight (corresponding to 126 to 154 MBq for an adult weighing 70 kg), with a minimum dose of 111 MBq up to a maximum dose of 259 MBq.
Special populations
Elderly
No dose adjustment is required.
Renal impairment
No dose adjustment is required in patients with renal impairment (see section 5.2).
Hepatic impairment
Gallium (68Ga) gozetotide solution for injection prepared using Illuccix has not been studied in patients with hepatic impairment.
Paediatric population
There is no relevant use of Illuccix in the paediatric population.
Method of administration
This medicinal product is for intravenous and multidose use. It should be reconstituted and radiolabelled before administration to the patient.
After reconstitution and radiolabelling, gallium (68Ga) gozetotide solution for injection should be administered as a slow single intravenous bolus followed by an intravenous flush of sterile sodium chloride 9 mg/ml (0.9%) solution for injection to ensure full delivery of the dose. Local extravasation resulting in inadvertent radiation exposure to the patient and imaging artefacts should be avoided. The speed of administration depends on the venous tolerability to low pH solution, which is mainly dependent of the blood flow of the vein used for the injection.
The radioactivity of gallium (68Ga) gozetotide solution for injection in the syringe should be measured with a dose calibrator immediately before and after administration to the patient. The dose calibrator must be calibrated and comply with international standards.
For patient preparation, see section 4.4.
For instructions on reconstitution and radiolabelling of the medicinal product before administration, see section 12.
Image acquisition
The patient should be positioned supine with arms above the head whenever possible. A low-dose Computed Tomography (CT) or Magnetic Resonance Imaging (MRI) scan should be obtained for attenuation correction and anatomic correlation. PET scanning should begin 60 min after the intravenous administration of gallium (68Ga) gozetotide solution for injection, with an acceptable range of 50 to 100 min.
The interval between intravenous administration of gallium (68Ga) gozetotide solution for injection and imaging should be recorded. PET must include a whole-body acquisition from the mid-thigh to the vertex as to exploit the reduced gallium (68Ga) gozetotide ligand activity in the urinary bladder after pre-scan voiding.
Acquisition should proceed from the lower end of the axial field of view cranially, in a three-dimensional (3D) mode with an acquisition time of usually 2-4 min per bed position. Overall, PET coverage should be identical to the anatomical CT scan range. Typically, total scan time is between 20-30 minutes.
Image reconstruction
Image acquisition should be performed in 3D acquisition mode with appropriate data corrections; the CT or MRI scan may be used for attenuation correction. PET reconstruction should be performed with and without attenuation correction to identify potential artefacts caused by the correction algorithm.
If acquired, contrast-enhanced CT shall not be used for attenuation correction, since iodine content may induce wrong attenuation correction.
4.3 Contraindications
Hypersensitivity to the active substance, to any of the excipients listed in section 6.1 or to any of the components of the labelled radiopharmaceutical.
4.4 Special warnings and precautions for use
Individual benefit/risk justification
For each patient, the radiation exposure must be justifiable by the likely benefit. The activity administered should, in every case, be as low as reasonably achievable to obtain the required diagnostic information.
Radiation risk
Gallium (68Ga) gozetotide contributes to the patient’s overall long-term cumulative radiation exposure, which is associated with an increased risk of cancer. Safe handling, reconstitution and radiolabelling procedures should be ensured to protect patients and healthcare professionals from unintentional radiation exposure (see sections 6.6 and 12).
Paediatric population
For information on use in the paediatric population, see section 4.2.
Patient preparation
In order to obtain images of best quality and to reduce the radiation exposure, patients should be encouraged to drink sufficient amounts (with e.g. oral intake of 500 mL of water 2 hours prior to acquisition), and to empty their bladder prior to and after the PET examination.
The prostate-specific antigen (PSA) value may affect the diagnostic performance of gallium (68Ga) gozetotide PET (see section 5.1, Pharmacodynamic properties).
Interpretation of gallium (68Ga) gozetotide PET images
PET images with gallium (68Ga) gozetotide should be interpreted by visual assessment. Gallium (68Ga) gozetotide PET images should be interpreted only by readers trained in the interpretation of PET images with gallium (68Ga) gozetotide PET. Additional imaging may be used to differentiate between the physiological and pathological uptake of gallium (68Ga) gozetotide. In recurrent setting, PSMA-PET detection rate is influenced by several factors: PSA, PSA doubling time, Gleason score, administration of concurrent ADT and clinical stage of the disease are parameters able to influence the likelihood of a positive scan. Suspicion of cancer in sites typical for prostate cancer recurrence is based on gallium (68Ga) gozetotide uptake in comparison with tissue background. Usually, attention should be paid to prostate gland/bed, seminal vesicles, regional and distant lymph nodes, bones, lungs, and liver, as well as the regions that may relate to any symptoms given by the patient.
Physiological variable PSMA ligand uptake can be found in the lacrimal gland, salivary glands, liver, spleen, celiac lymph nodes, small intestine, kidney and the ureters. Variably high activity can be observed in the urinary bladder. Minor but visible uptake can be observed in the pharyngeal and laryngeal area and the cavum, the thyroid gland and mediastinal lymph nodes. Usually, tumour lesions inside and outside the prostate gland show a strong tumour-background ratio compared to surrounding tissue.
The impact of quantitative/semiquantitative measurement of gallium (68Ga) gozetotide uptake as an aid to image interpretation has not been assessed. Image interpretation errors can occur with gallium (68Ga) gozetotide PET (see section 5.1). An important pitfall is relevant PSMA ligand uptake in coeliac ganglia of the autonomic nervous system which is prone to be misinterpreted as retroperitoneal lymph node metastases. Gallium (68Ga) gozetotide uptake is not specific for prostate cancer and may occur with other types of cancer, prostatitis and benign prostatic hyperplasia. False-positive cases have been also described in association with an inflammatory response after cryotherapy and radiation artefacts in patients previously treated with radiotherapy. Clinical correlation, which may include histopathological evaluation of the suspected recurrence site, should be considered where appropriate.
After the procedure
Close contact with infants and pregnant women should be restricted during the initial 2 hours following the injection.
The patient should be encouraged to drink sufficient amounts of water and void as often as possible during the first hours post scan to reduce unnecessary radiation exposure, especially to the bladder.
Sodium content
This medicinal product contains up to 42 mg sodium per dose, equivalent to 2.1% of the WHO recommended maximum daily intake of 2 g sodium for an adult.
Extravasation and local vein irritation
In case of local vein irritation, injection must be adapted accordingly by the healthcare professional. Decreasing the infusion speed and/or rinsing the vein with isotonic saline solution when irritation occurs are measures to decrease the symptoms perceived by the patient.
In case of extravasation, the injection must be stopped, the site of injection must be changed, and the affected area should be irrigated with sodium chloride solution. The impact of extravasation on the actually injected dose and on image quality has to be considered when interpreting the imaging results.
Precautions with respect to environmental hazard are in section 6.6.
4.5 Interaction with other medicinal products and other forms of interaction
No interaction studies have been performed. Given the micro-dose administered, and given that significant hepatic metabolism is unlikely, the risk of clinically significant pharmacokinetic drug interactions is very low. The reduction in signal from the urinary bladder seen with the concomitant administration of furosemide, suggested that the use of furosemide and possibly other diuretics, could reduce the scatter severity in gallium (68Ga) gozetotide PET.
4.6 Fertility, pregnancy and lactation
Women of childbearing potential, pregnant or breast-feeding
Gallium (68Ga) gozetotide is not indicated for use in women.
Fertility
No studies on fertility have been conducted.
4.7 Effects on ability to drive and use machines
Gallium (68Ga) gozetotide has no or negligible influence on the ability to drive and use machines.
4.8 Undesirable effects
Summary of the safety profile
The radiation dose with gallium (68Ga) gozetotide PET/CT is the combination of the radiation exposure from the radiopharmaceutical and the CT. Recent advances in technology have allowed the radiation doses to be significantly reduced relative to a conventional CT or PET examination.
Low dose CT is sufficient for the claimed indication. So, the patient’s exposition to CT is close to 1 mSv but depends on the clinical site protocol.
Exposure to ionising radiation is linked with cancer induction and a potential for development of hereditary defects. As the effective dose is 3 mSv when the maximal recommended activity of 2.2 MBq per kilogram of body weight is administrated these adverse reactions are expected to occur with a low probability.
Tabulated list of adverse reactions
The following list of adverse reactions is based on experience from clinical trials, available literature and post-marketing surveillance. Adverse reactions are displayed by system organ class and frequency in Table 1 and defined as very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1,000 to <1/100), rare (≥1/10,000 to <1/1,000), very rare (<1/10,000) and not known (cannot be estimated from the available data).
Table 1: Adverse reactions by system organ class and frequency
| MedDRA system organ class | Adverse reactions | Frequency |
| Metabolism and nutrition disorders | Transient hyperamylasemia | Rare |
| Gastrointestinal disorders | Constipation | Rare |
General disorders and administration site conditions | Asthenia, injection site warmth | Rare |
| Injection site pain1 | Not known |
1 The injection site pain is transient.
Patient exposure
Three healthy volunteers and 597 patients were exposed to the product in 4 prospective studies. Gallium (68Ga) gozetotide was also evaluated in 1 retrospective study (100 patients).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via Yellow Card Scheme, Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
No case of overdose has been reported.
In the event of administration of a radiation overdose with gallium (68Ga) gozetotide solution for injection, the absorbed dose to the patient should be reduced where possible by increasing the elimination of the radionuclide from the body by reinforced hydration, forced diuresis and frequent micturition. It might be helpful to estimate the effective radiation dose that was applied.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Diagnostic radiopharmaceuticals, other diagnostic radiopharmaceuticals for tumour detection.
ATC code: V09IX14
Mechanism of action
| Gallium (68Ga) gozetotide binds specifically to the prostate-specific membrane | ||
| antigen (PSMA) that is expressed in nearly all prostate cancer with increased | ||
| expression in poorly differentiated, metastatic, and hormone-refractory carcinomas. | ||
Pharmacodynamic effects
At the chemical concentrations used for diagnostic examinations, gallium (68Ga) gozetotide does not appear to have any pharmacodynamics activity.
Clinical efficacy and safety
The key evidence of diagnostic efficacy derives from the below mentioned studies.
In Hope et al. (2021), 277 of the 764 enrolled adult patients with intermediate to high-risk prostate cancer underwent prostatectomy with lymph node dissection using gallium (68Ga) gozetotide PET/CT imaging for the detection of pelvic nodal metastases compared with histopathology. See Table 2 for efficacy results.
Table 2: Efficacy results in patients with intermediate to high-risk biopsy-proven prostate cancer considered for prostatectomy
Gallium (68Ga) gozetotide PET/CT1 (efficacy analysis cohort) N=277 | Gallium (68Ga) gozetotide PET/CT2 (excluding 15 patients with no nodes on pathology) N=262 | |
| Sensitivity (95% CI) | 40% (34, 46) | 41% (36, 47) |
| Specificity (95% CI) | 95% (92, 97) | 95% (91, 97) |
| PPV (95% CI) | 75% (70, 80) | 74% (69, 79) |
| NPV (95% CI) | 81% (76, 85) | 82% (76, 86) |
Abbreviations: NPV=negative predictive value, PPV=positive predictive value 1 Per-patient level analysis based on the majority reads
2 Post-hoc analysis that excluded 15 patients with no nodes on pathology
In Basha et al. (2019), the diagnostic sensitivity for diagnosis and staging with gallium (68Ga) gozetotide PET/CT was investigated in 173 adult patients with newly histologically proven diagnosed, untreated intermediate and/or high-risk prostate cancer. The gallium (68Ga) gozetotide PET/CT scans for 166 of 173 patients showed positivity for prostate cancer. The diagnostic sensitivity was established by histopathology. See Table 3 for efficacy results.
Table 3: Efficacy results in patients with newly diagnosed, untreated prostate cancer of low, moderate, and high risk disease severity
Gallium (68Ga) gozetotide PET/CT N=173 | |
| Sensitivity (95% CI)1 | 96% (91.84, 98.36) |
1 Per-patient level analysis
In Hofman et al. (2020), 300 adult patients with untreated, biopsy-proven prostate cancer and high-risk features were randomised 1:1 and underwent gallium (68Ga) gozetotide PET/CT (N=148) or CT and bone scanning imaging (N=152). A composite reference standard, including histopathology, imaging, clinical and biochemical findings, was available for 295 of 300 (98%) patients and the PET/CT scans were read by two independent readers. Gallium (68Ga) gozetotide PET/CT had improved sensitivity and specificity compared to CT and bone scanning imaging, as summarised in Table 4. Radiation exposure from gallium (68Ga) gozetotide was lower (8.4 mSv, 95% CI: 8.1, 8.7) than CT and bone scanning imaging radiation exposure (19.2 mSv, 95% CI: 18.2, 20.3).
Table 4: Efficacy results in patients with untreated, biopsy-proven prostate cancer
Gallium (68Ga) gozetotide PET/CT N=1451 | CT and bone scanning N=1501 | |
| Sensitivity (95% CI) | 85% (74, 96) | 38% (24, 52) |
| Specificity (95% CI) | 98% (95, 100) | 91% (85, 97) |
| Accuracy (95% CI) | 92% (88, 95)2 | 65% (60, 69) |
| Change in patient management | 28% (21, 36)3 | 15% (10, 22) |
1 Evaluable population 2 P<0.0001
3 included either a transition from curative to palliative treatment intent or a change in treatment approach (14% of patients each)
In van Kalmthout et al. (2020), the diagnostic accuracy of gallium (68Ga) gozetotide PET/CT was evaluated in detection of lymph node metastasis (LDM) during primary staging before external pelvic lymph node dissection (ePLND) in 103 newly diagnosed adult prostate cancer patients with intermediate/high risk. See Table 5 for efficacy results.
Table 5: Efficacy results in patients with newly diagnosed prostate cancer with intermediate to high risk disease severity and suspected lymph node metastasis
Gallium (68Ga) gozetotide PET/CT1 N=103 | |
| Sensitivity (95% CI) | 42% (27, 58) |
| Specificity (95% CI) | 91% (79, 97) |
| PPV (95% CI) | 77% (54, 91) |
| NPV (95% CI) | 68% (56, 78) |
Abbreviations: NPV=negative predictive value, PPV=positive predictive value 1 Per-patient level analysis
In Fendler et al. (2019), 635 adult patients with histopathology-proven and biochemical recurrence (BCR) prostate cancer after prostatectomy (N=262), radiation therapy (N=169) or both (N=204) underwent gallium (68Ga) gozetotide PET/CT or PET/MRI imaging. BCR was defined by serum PSA of ≥0.2 ng/mL more than 6 weeks after prostatectomy or by an increase in serum PSA of at least 2 ng/mL above nadir after definitive radiotherapy. Patients had median PSA level of 2.1 ng/mL above nadir after radiation therapy (range: 0.1-1154 ng/mL). A composite reference standard, including histopathology, serial serum PSA levels and imaging (CT, MRI, and/or bone scan) findings was available for 223 of 635 (35.1%) patients, while histopathology reference standard alone was available for 93 (14.6%) patients. PET/CT scans were read by 3 independent readers blinded to clinical information other than the type of primary therapy and most recent serum PSA level.
Detection of PSMA-positive lesions occurred in 475 of 635 (75%) patients receiving gallium (68Ga) gozetotide. The detection rate of gallium (68Ga) gozetotide PET positive lesion increased with increasing serum PSA levels (see section 4.4). Sensitivity and positive predictive value (PPV) of gallium (68Ga) gozetotide PET imaging are summarised in Table 6. Inter-reader Fleiss κ for gallium (68Ga) gozetotide PET imaging ranged from 0.65 (95% CI: 0.61, 0.70) to 0.78 (95% CI: 0.73, 0.82) across the assessed regions (prostate bed, pelvic nodes, extrapelvic soft tissues and bones).
Table 6: Efficacy results in patients with histopathology-proven and BCR prostate cancer
Composite reference standard N=2231 | Histopathology reference standard N=931 | |
| Sensitivity per-patient (95% CI) | NA | 92% (84, 96) |
| Sensitivity per-region (95% CI) | NA | 90% (82, 95) |
| PPV per-patient (95% CI) | 92% (88, 95) | 84% (75, 90) |
| PPV per-region (95% CI) | 92% (88, 95) | 84% (76, 91) |
Abbreviations: PPV=positive predictive value 1 Evaluable population
In Abghari-Gerst et al. (2022), the performance of gallium (68Ga) gozetotide PET/CT for detecting prostate adenocarcinoma was investigated in 2005 adult patients with histologically proven prostate cancer and BCR (elevated levels of PSA) after initial therapy. Patients had prostate cancer after radical prostatectomy with or without postoperative radiotherapy (PORT) or definitive radiotherapy. See Table 7 for efficacy results. The study confirmed a high PPV for gallium (68Ga) gozetotide PET/CT in BCR and the PSA level as the main predictor of scan positivity.
Table 7: Efficacy results in patients with histopathology-proven and BCR prostate cancer
Gallium (68Ga) gozetotide PET/CT N=2005 | |
| PPV | 78.0 |
| PSA range <0.25 ng/mL, percent positivity ≥ | 44.8 |
| PSA range 10 ng/mL, percent positivity | 96.2 |
Abbreviations: PPV=positive predictive value, PSA=prostate-specific antigen
In Hamed et al. (2019), the detection efficacy and diagnostic accuracy of gallium (68Ga) gozetotide PET/CT imaging was assessed in 188 adult prostate cancer patients who had undergone definitive primary therapy and subsequently found to have rising prostate-specific antigen (PSA) serum levels on routine follow-up examination. See Table 8 for efficacy results. Of the 188 patients, 64 (38.8%) of the patients, recurrence could be detected by both CT as well as gallium (68Ga) gozetotide PET/CT, while in an additional 101 (61.2%) patients, gallium (68Ga) gozetotide PET/CT alone could detect disease. A total of 59 patients had local recurrence in the prostate bed, of which 24 also had extra-prostatic metastases. It was found that there is a significant correlation between PSA level and maximum standard uptake value (SUVmax) of local reoccurrence (r=0.9970; P=0.0002; 95% CI: 0.95-0.100).
Table 8: Efficacy results in patients with histopathology-proven and BCR prostate cancer
Gallium (68Ga) gozetotide PET/CT N=188 | |
| Sensitivity (95% CI) | 98.8% (95.74, 99.85) |
| Specificity (95% CI) | 100% (83.89, 100) |
| Accuracy | 98.8% |
| PPV (95% CI) | 100.0% (97.79, 100.00) |
| NPV (95% CI) | 91.3% (71.96, 98.93) |
Abbreviations: NPV=negative predictive value, PPV=positive predictive value
In the LINZ study, 46 adult patients who previously had radical treatment for prostate cancer and with biochemical recurrence were randomised to receive both a gallium (68Ga) gozetotide PET/CT and 18F-fluorocholine PET/CT to detect recurrence. This study demonstrated superiority of gallium (68Ga) gozetotide PET/CT vs. the 18F-fluorocholine PET/CT for the number of prostate cancer lesions correctly identified. Gallium (68Ga) gozetotide detected 2.005 times more lesions compared to 18F-fluorocholine [95 % CI: 1.487, 2.702]; sensitivity analysis resulted in a superior detection rate of true lesions of 2.002 [95% CI: 1.486, 2.697]; for both p <0.001.
The VISION Study used gallium (68Ga) gozetotide PET imaging to select patients for lutetium (177Lu) vipivotide tetraxetan therapy. A total of 1003 male patients were selected based on the PSMA expression of their prostate cancer lesions. Imaging criteria allowed patients with PSMA-positive mCRPC to receive life-extending therapy on the basis of only one PET scan plus conventional imaging with a central reader defining PSMA positivity on the basis of this single PET scan using gallium (68Ga) gozetotide.
Paediatric population
The licensing authority has waived the obligation to submit the results of studies with Illuccix in all subsets of the paediatric population in the visualisation of prostate specific membrane antigen in prostate cancer.
5.2 Pharmacokinetic properties
Pharmacokinetic properties are derived from blood/plasma and urinary clearance of gallium (68Ga) gozetotide.
Blood, plasma and urine samples have been measured in a gamma well-counter together with an aliquot of the injected activity; activities were expressed as a percentage of the injected dose (%ID) after correction for radioactivity decay.
Clearance constants α, ß and γ (%ID/ml), and the area under the curve (AUC) have been calculated for blood and plasma samples; the determined constants, the corresponding half-lives (t1/2) and the AUC are presented in Table 2. Between 30 and 50% of gallium (68Ga) gozetotide is excreted in the urine 180 min after injection.
Table 2: Gallium (68Ga) gozetotide pharmacokinetic parameters
| Subject | Matrix | Clearance Alpha (%ID/ml) | Clearance Beta (%ID/ml) | Clearance Gamma (%ID/ml) | t1/2 Alpha (min) | t1/2 Beta (min) | t1/2 Gamma (min) | AUC (%ID.min) |
| Subject 1 | Blood Plasma | 5.6917 5.7264 | 0.0568 0.0751 | 0.0046 0.0052 | 0.1218 0.1210 | 12.2076 9.2349 | 149.9401 133.1981 | 2682.9110 2561.1106 |
| Subject 2 | Blood Plasma | 0.5315 0.5302 | 0.0560 0.0468 | 0.0049 0.0035 | 1.3041 1.3074 | 12.3848 14.8266 | 140.8626 196.2321 | 2535.8480 2995.4990 |
| Subject 3 | Blood Plasma | 0.5637 0.4451 | 0.0696 0.0420 | 0.0067 0.0051 | 1.2296 1.5572 | 9.9521 16.4992 | 104.1443 134.7231 | 2089.4772 2540.0317 |
Distribution
Gallium (68Ga) gozetotide global biodistribution in normal organs is relatively rapid, which accounts for the recommended 60 min interval (acceptable range 50 to 100 min) for uptake time between injection of the tracer and PET imaging.
Organ uptake
Gallium (68Ga) gozetotide is preferentially taken up into prostate cancer cells compared with surrounding normal tissues. Significant off-target tissue uptake was highest for the kidneys, urinary bladder wall, salivary glands, small bowel, spleen and liver with mean absorbed doses between 0.456 and 0.022 mGy/MBq in decreasing order, with the first 2 organs indicating that the primary route of excretion is via the urinary tract.
Biotransformation
Based on in vitro data, gallium (68Ga) gozetotide undergoes negligible hepatic and renal metabolism.
Elimination
The main pathway for elimination is via the kidneys. Urinary excretion is rapid. About 43% of the activity of gallium (68Ga) gozetotide is eliminated from the body by urine within 3 hours post-injection.
Half-life
The radioactive half-life of gallium (68Ga) is 67.7 minutes.
Other special populations
Elderly
No overall differences in safety and efficacy were observed between patients > 65 years of age versus patients ≤ 65 years of age.
Renal/Hepatic impairment
The pharmacokinetics in patients with renal or hepatic impairment have not been characterized.
5.3 Preclinical safety data
A toxicological study in rats has demonstrated that with a single intravenous injection of 86 µg gozetotide per kg body weight no adverse effects were observed. Based on the highest anticipated clinical dose of 25 μg gozetotide (0.5 μg/kg; based on 50 kg adult) and the NOAEL of gozetotide in the rat of 86 μg/kg, a safety margin of 28-fold was obtained based on body surface area.
Mutagenicity and long-term carcinogenicity studies have not been carried out.
No reproductive or developmental toxicity studies have been performed.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Powder for solution for injection
D-Mannose
Solvent
Water for injections
Sodium acetate anhydrous
Hydrochloric acid
6.2 Incompatibilities
This medicinal product must not be mixed with other medicinal products except those mentioned in section 12.
6.3 Shelf life
Kit: 2 years.
After radiolabelling: 2 hours. Do not store above 25 °C nor freeze the solution after radiolabelling.
From a microbiological point of view, once reconstituted and radiolabelled, the product should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user.
6.4 Special precautions for storage
Before reconstitution, store in a refrigerator (2°C – 8°C).
Store in the original package in order to protect from light.
For storage conditions after reconstitution and radiolabelling of the medicinal product, see section 6.3.
Storage of radiopharmaceuticals should be in accordance with national regulation on radioactive materials.
6.5 Nature and contents of container
Illuccix is supplied as a kit for radiopharmaceutical preparation of gallium (68Ga) gozetotide solution for injection.
For use with Eckert & Ziegler GalliaPharm germanium-68/gallium-68 (68Ge/68Ga) generator, the pack contains:
- One vial of powder for solution for injection: the vial contains 25 micrograms of gozetotide.
- One vial of solvent containing 2.5 mL of acetate buffer.
- One empty vial, sterile, vacuum-sealed.
- Label for radiolabelled product shielding.
For use with IRE ELiT Galli Ad germanium-68/gallium-68 (68Ge/68Ga) generator, the pack contains:
- One vial of powder for solution for injection: the vial contains 25 micrograms of gozetotide.
- One vial of solvent containing 6.4 mL of acetate buffer.
- One empty vial, sterile, vacuum-sealed.
- Label for radiolabelled product shielding.
Each vial is a 10 mL capacity type I glass vial closed with a chlorobutyl rubber stopper and sealed with an aluminium-coloured cap.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal and other handling
General warning
Radiopharmaceuticals should be received, used and administered only by authorised persons in designated clinical settings. Their receipt, storage, use, transfer and disposal are subject to the regulations and/or appropriate licences of the competent official organisation.
Radiopharmaceuticals should be prepared in a manner which satisfies both radiation safety and pharmaceutical quality requirements. Appropriate aseptic precautions should be taken.
The contents of the vials are intended only for use in the preparation of gallium (68Ga) gozetotide solution for injection and are not to be administrated directly to the patient without first undergoing the preparative procedure (see section 12).
Precautions to be taken before handling or administration of the medicinal product
The content of the kit before reconstitution and radiolabelling is not radioactive. However, after gallium (68Ga) chloride Ph. Eur. is added, adequate shielding of the final preparation must be maintained.
After reconstitution, Illuccix should be radiolabelled with a gallium-68 chloride solution having an activity of up to 1 227 MBq.
Gallium (68Ga) gozetotide is a sterile, clear, colourless solution for intravenous administration, practically free from visible particles and with pH between 4.0 to 5.0.
Appropriate aseptic precautions should be taken when withdrawing and administering gallium (68Ga) gozetotide solution for injection.
Administration procedures should be carried out in a way to minimise risk of contamination of the medicinal product and irradiation of the operators. Adequate shielding is mandatory.
If at any time in the preparation of this medicinal product the integrity of the vials is compromised, it should not be used.
The administration of radiopharmaceuticals creates risks for other persons from external radiation or contamination from spill of urine, vomiting etc. Radiation protection precautions in accordance with national regulations must therefore be taken.
For instructions on reconstitution and radiolabelling of the medicinal product before administration, see section 12.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
TELIX PHARMACEUTICALS (UK) LIMITED
St Mary's Court, The Broadway
Amersham
Buckinghamshire
United Kingdom
HP7 0UT
8 MARKETING AUTHORISATION NUMBER(S)
PL 57676/0001
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE AUTHORISATION
Date of first authorisation: 12/02/2025
10 DATE OF REVISION OF THE TEXT
05/06/2026
11 DOSIMETRY
Gallium 68 is produced by means of a germanium-68/galium-68 (68Ge/68Ga) generator and decays with a half-life of 68 min to stable zinc-68. Gallium-68 decays as follows:
- 89% through positron emission with a mean energy of 836 keV followed by photonic annihilation radiations of 511 keV (178%),
- 10% through orbital electron capture (X-ray or Auger emissions),
- 3% through 13 gamma transitions from 5 excited levels.
Estimated radiation absorbed doses per injection activity for organs and tissues of adult patients following an intravenous bolus of gallium (68Ga) gozetotide solution for injection, studied in Phase I study, are shown in Table 3. The software OLINDA-EXM was used to calculate absorbed organ doses according to the Committee on Medical Internal Radiation Dose (MIRD) methodology, and effective dose according to ICRP (International Commission on Radiological Protection) Publication 103.
The kidneys were the organs receiving the highest absorbed dose. Additional organs with higher dose were urinary bladder, small intestines, and salivary glands.
Table 3: Estimated mean radiation absorbed dose per injection activity in selected organs and tissues of adults after a gallium (68Ga) gozetotide dose
| Adults Organ/Tissue | Estimated Mean Radiation Absorbed Dose per Injection Activity (mGy/MBq) |
| Adrenals | 0.012 |
| Brain | 0.001 |
| Breasts | 0.006 |
| Gallbladder | 0.012 |
| Heart | 0.013 |
| Kidneys | 0.456 |
| Liver | 0.022 |
| Lower colon | 0.010 |
| Lungs | 0.008 |
| Muscle | 0.008 |
| Osteogenic cells | 0.013 |
| Pancreas | 0.011 |
| Red marrow | 0.012 |
| Salivary glands | 0.096 |
| Skin | 0.006 |
| Small intestine | 0.057 |
| Spleen | 0.037 |
| Stomach | 0.009 |
| Testes | 0.007 |
| Thymus | 0.007 |
| Thyroid | 0.007 |
| Total body | 0.011 |
| Upper Colon | 0.013 |
| Urinary bladder | 0.112 |
| Effective dose (mSv/MBq) | 0.0162 |
The effective dose resulting from the administration of a 2.2 MBq per kilogram of body weight is about 3 mSv (Fendler et al., 2017).
For an administered activity of 185 MBq, the typical radiation dose to the target organs is between 84, 21, 18 and 11 mGy for the kidneys, urinary bladder, salivary glands and small intestine, respectively, as being the normal target organs.
12 INSTRUCTIONS FOR PREPARATION OF
RADIOPHARMACEUTICALS
Method of preparation
Step 1: Reconstitution and radiolabelling
Illuccix allows the direct preparation of gallium (68Ga) gozetotide solution for injection (also known as gallium (68Ga) PSMA-11 injection) with the eluate from one of the following generators (see below for specific instructions for use with each generator):
- Eckert & Ziegler GalliaPharm germanium-68/gallium-68 (68Ge/68Ga) generator
- IRE-ELiT Galli Ad germanium-68/gallium-68 (68Ge/68Ga) generator
Before reconstitution and radiolabelling, confirm that the Illuccix kit is compatible with the 68Ge/68Ga generator being used.
Gallium (68Ga) chloride solution eluate from generator complies with the requirements of the Ph. Eur. monograph 2464, gallium (68Ga) chloride solution for radiolabelling. The instructions for use provided by the germanium-68/gallium-68 generator manufacturer should also be followed.
The preparation of gallium (68Ga) gozetotide solution for injection should be done according to the following aseptic procedure:
- Use suitable shielding to reduce radiation exposure.
- Wear waterproof gloves all the time during preparation and quality control of gallium (68Ga) gozetotide.
- Put the label for radiolabelled product on the shielding.
- Remove the flip-off disc from powder vial (gozetotide), solvent vial (acetate buffer) and empty vial, swab the top of each vial with alcohol to disinfect the surface and allow the stoppers to dry.
- Use only plastic syringes for preparation and administration. Do not use syringes with rubber plungers.
Reconstitution and radiolabelling with Eckert & Ziegler GalliaPharm generator
Reconstitution of powder vial
- 1.
Insert a sterile 10 mL syringe with a needle into the solvent vial and draw up the
2.5 mL of acetate buffer contained in the vial.
- 2. Inject the content of the 10 mL syringe into the powder vial.
- 3. Gently swirl powder vial to ensure the product is thoroughly dissolved.
Elution of generator and collection of gallium (68Ga) chloride
- 1. Prepare a syringe containing 5 mL of sterile ultrapure 0.1M HCl provided with the GalliaPharm generator for elution.
- 2. Pierce the empty vial with a sterile needle connected to a 0.2 micron sterile vented filter to maintain atmospheric pressure within the vial during the reconstitution process.
- 3. Connect the male luer of the outlet line of the GalliaPharm generator to a sterile needle.
- 4. Connect the empty vial directly to the outlet line of the GalliaPharm generator by pushing the needle through the rubber septum and place the vial in a radiation shielded container.
- 5. Elute the generator directly into the empty vial in the radiation shielded container according to the instructions for use of the GalliaPharm generator. Perform the elution manually or by means of a pump. Collect 5 mL of eluate.
- 6. At the end of the elution, disconnect the generator from the vial in the radiation shielded container by removing the needle from the rubber septum.
Radiolabelling
- 1. Insert a sterile 10 mL syringe with a needle into the powder vial containing the dissolved gozetotide and draw up the content of the vial.
- 2.
Transfer the content of the 10 mL syringe to the vial containing the gallium
(68Ga) chloride.
- 3. Wait for 5 minutes for radiolabelling to take place at room temperature.
At the end of radiolabelling step, the vial contains 7.5 mL of gallium (68Ga) gozetotide.
Then continue with Step 2.
Reconstitution and radiolabelling with IRE ELiT Galli Ad generator
Reconstitution of powder vial
- 1.
Insert a sterile 10 mL syringe with a needle into the solvent vial and draw up the
6.4 mL of acetate buffer contained in the vial.
- 2. Inject the content of the 10 mL syringe into the powder vial.
- 3. Gently swirl powder vial to ensure the product is thoroughly dissolved.
Elution of generator and collection of gallium (68Ga) chloride
- 1. Connect the male luer of the outlet line of the Galli Ad generator to a sterile needle.
- 2. Elute the generator directly into the empty vial in the radiation shielded container according to the instructions for use of the Galli Ad generator. Collect 1.1 mL of eluate.
- 3. At the end of the elution, disconnect the generator from the vial in the radiation shielded container by removing the needle from the rubber septum.
Radiolabelling
- 1. Insert a sterile 10 mL syringe with a needle into the powder vial containing the dissolved gozetotide and draw up the content of the vial.
- 2.
Transfer the content of the 10 mL syringe to the vial containing the gallium
(68Ga) chloride.
- 3. Wait for 5 minutes for radiolabelling to take place at room temperature.
At the end of radiolabelling step, the vial contains 7.5 mL of gallium (68Ga) gozetotide.
Then continue with Step 2.
Step 2: After radiolabelling
- 1.
After 5 minutes of radiolabelling, assay the vial containing the gallium (68Ga)
gozetotide solution for injection for total radioactivity concentration using a dose calibrator and record the result.
- 2. Perform quality controls according to the recommended methods in order to check compliance with the specifications (see Step 3).
- 3. Store the Illuccix vial containing the gallium (68Ga) gozetotide solution for injection upright in a lead shield container at room temperature until use.
Step 3: Specifications and Quality control
Perform the quality controls behind a lead glass shield for radioprotection purposes. The gallium (68Ga) gozetotide solution for injection should only be used if the acceptance criteria presented in Table 4 are met.
Table 4: Specifications of Gallium (68Ga) gozetotide solution for injection
| Test | Analytical method | Acceptance criteria |
| Appearance | Visual inspection | Clear, colourless solution, practically free from visible particles |
| pH | pH-strips or pH-meter | 4.0 to 5.0 ≤ |
Radiochemical purity Free and colloidal gallium-68 species | Instant Thin layer chromatography (iTLC, see details below) | 3% |
Determine labelling efficiency of gallium (68Ga) gozetotide solution for injection by performing thin layer chromatography (iTLC).
Materials and equipment
- Developing chamber for chromatography
- Mobile phase: Ammonium acetate 1M/methanol (1:1 V/V) solution
- iTLC SG plates 2 cm x 9 cm
- Radioactivity dose calibrator/ionization chamber or radioTLC scanner iTLC method:
- Transfer the mobile phase into a TLC developing chamber, to a depth of ± 0.5 cm. Cover the chamber and allow the vapour to equilibrate.
- Prepare a iTLC strip with 9 cm length and 2 cm width and draw:
- a pencil line at 1 cm from the bottom of the TLC plate (baseline)
- a pencil dotted line at 4.5 cm from the bottom of the TLC plate (middle of the elution path)
- a pencil line at 1 cm from the top of the TLC plate
- Apply one drop (about 5 μL) of gallium (68Ga) gozetotide at the centre on the plate baseline.
Develop the strip in the developing chamber until the solvent reaches the last line,
8 cm from the bottom of the plate.
- Measure with cut and count technique or radioTLC scanner.
Cut and count technique:
- Cut the iTLC plate at the middle line (4.5 cm) into two pieces and measure the count rate of each piece in the ionization chamber or radioactivity dose calibrator.
- Calculate the radiochemical purity (quantity (in percent) of free and colloidal gallium-68 species in the solution) using the formula:
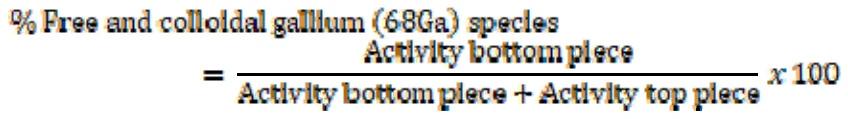
Scanning technique:
- Scan the iTLC SG strip with a radioTLC scanner.
- Calculate the radiochemical purity by integration of the peaks on the chromatogram.
The retention factor (Rf) specifications are:
- Free and colloidal gallium-68 species, Rf = 0 to 0.2
- Gallium (68Ga) gozetotide, Rf = 0.8 to 1.0
Step 4: Administration
- Aseptic technique and radiation shielding should be used when withdrawing and administering gallium (68Ga) gozetotide solution for injection.
- Prior to use, visually inspect the prepared gallium (68Ga) gozetotide solution for injection behind a lead glass shield for radioprotection purposes. Only solutions that are clear, colourless and practically free from visible particles should be used.
- Using a single-dose syringe fitted with a sterile needle and protective shielding, aseptically withdraw the prepared gallium (68Ga) gozetotide solution for injection prior to administration.
- The total radioactivity in the syringe should be verified with a dose calibrator immediately before and after gallium (68Ga) gozetotide solution for injection administration to the patient. The dose calibrator must be calibrated and comply with international standards.
- Radioactive waste must be disposed of in accordance with relevant national regulations.