

Summary of medicine characteristics - Heplisav B 20 micrograms solution for injection in Pre-filled syringe Hepatitis B vaccine
1 NAME OF THE MEDICINAL PRODUCT
HEPLISAV B 20 micrograms solution for injection in pre-filled syringe Hepatitis B vaccine (recombinant DNA, adjuvanted)
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
One dose (0.5 mL) contains:
Hepatitis B surface antigen (HBsAg)1,2 20 micrograms
1Adjuvanted with 3000 micrograms cytidine phosphoguanosine (CpG) 1018 adjuvant, a 22-mer phosphothioate oligonucleotide (PS-ODN) comprising microbial DNA-like unmethylated CpG motifs
2Produced in yeast cells (Hansenula polymorpha) by recombinant DNA technology
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Solution for injection in pre-filled syringe.
Clear to slightly opalescent, colourless to slightly yellow solution.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
HEPLISAV B is indicated for active immunisation against hepatitis B virus infection (HBV) caused by all known subtypes of hepatitis B virus in adults 18 years of age and older.
The use of HEPLISAV B should be in accordance with official recommendations.
It can be expected that hepatitis D will also be prevented by immunisation with HEPLISAV B as hepatitis D (caused by the delta agent) does not occur in the absence of hepatitis B infection.
4.2 Posology and method of administration
Posology
Adults:
The vaccine is administrated intramuscularly.
Primary vaccination:
Adults: Two doses of 0.5 ml each: an initial dose followed by a second dose 1 month later.
Adults with severe renal impairment (eGFR < 30 ml/min) including patients undergoing haemodialysis:
Four doses of 0.5-ml each: an initial dose followed by a second dose 1 month later, a third dose 2 months after the initial dose, and a fourth dose 4 months after the initial dose.
Booster dose
The need for a booster dose has not been established. Subjects who are immunocompromised or who have chronic renal failure may require a booster dose.
A 0.5-ml booster dose should be given when antibody levels decrease below recommended levels. See section 4.4.
Elderly population
No dose adjustment is required. See section 5.1.
Paediatric population
The safety and efficacy of HEPLISAV B in children less than 18 years of age have not been established. No data are available.
Method of administration
HEPLISAV B should be injected intramuscularly (IM) in the deltoid region. Injection into the gluteal region (buttocks) should be avoided.
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
Severe allergic reaction, such as anaphylaxis, after a previous dose of any hepatitis B vaccine.
Hypersensitivity to yeast.
4.4 Special warnings and precautions for use
Traceability
In order to improve the traceability of biological medicinal products, the name and the batch number of the administered product should be clearly recorded.
HEPLISAV B should not be administered intravenously, subcutaneously, or intradermally.
As with all injectable vaccines, appropriate medical treatment and supervision should be readily available in case of rare anaphylactic reactions following the administration of the vaccine.
As with other vaccines, the administration of HEPLISAV B should be postponed in subjects suffering from acute severe febrile illness. The presence of a minor infection, however, is not a contraindication for immunisation.
Syncope (fainting) can occur following, or even before, any vaccination as a psychogenic response to the needle injection. This can be accompanied by several neurological signs such as transient visual disturbance, paraesthesia, and tonic-clonic limb movements during recovery. It is important that procedures are in place to avoid injury.
As with any vaccine, a protective immune response may not be elicited in all vaccinees.
Because of the long incubation period of hepatitis B, it is possible for unrecognised HBV infection to be present at the time of immunisation. HEPLISAV B may not prevent HBV infection in such cases.
HEPLISAV B will not prevent infection caused by other pathogens known to infect the liver such as hepatitis A, hepatitis C, and hepatitis E viruses.
There are very limited data on the immune response to HEPLISAV in individuals who did not mount a protective immune response to another hepatitis B vaccine.
Immunodeficiency
Immunocompromised persons may have a diminished immune response to HEPLISAV B. There are very limited data available among immunocompromised population. Attention should be given to ensure that a protective antibody level is maintained as defined by national recommendations and guidelines. See section 4.2.
Patients with chronic liver disease or with HIV infection or hepatitis C carriers should not be precluded from vaccination against hepatitis B. The vaccine could be advised since HBV infection can be severe in these patients: the HEPLISAV B vaccination should thus be considered on a case by case basis by the physician.
Renal Impairment
As patients with CKD who are pre-haemodialysis or receiving haemodialysis are particularly at risk of exposure to HBV and have a higher risk of becoming chronically infected, attention should be given to ensure that a protective antibody level is maintained as defined by national recommendations and guidelines. See section 4.2.
Excipients
This medicinal product contains less than 1 mmol of sodium (23 mg) per dose, i.e. is essentially 'sodium-free’.
4.5 Interaction with other medicinal products and other forms of interaction
As there are no data on co-administration of HEPLISAV B with other vaccines, the concomitant use of HEPLISAV B with other vaccines is not recommended.
Concomitant administration of HEPLISAV B with hepatitis B immunoglobulin (HBIG) has not been studied. However, in circumstances where HEPLISAV B is administered with a standard dose of HBIG, these should be given at separate injection sites.
4.6 Fertility, pregnancy and lactation
Pregnancy
There are a limited amount of data from the use of HEPLISAV B vaccine in pregnant women.
Animal studies do not indicate direct or indirect harmful effects of relevance to humans with respect to reproductive toxicity (see section 5.3).
Vaccination during pregnancy should only be performed if the risk-benefit ratio at the individual level outweighs possible risks for the foetus.
Breast-feeding
It is unknown whether HEPLISAV B is excreted in human milk. A risk to the breastfed newborns/infants cannot be excluded.
A decision must be made whether to discontinue breast-feeding or to abstain from HEPLISAV B vaccination taking into account the benefit of breast-feeding for the child and the benefit of vaccination for the woman.
Fertility
No data on the effect of HEPLISAV B on fertility in humans are available.
Animal studies do not indicate direct or indirect harmful effects with respect to reproductive toxicity (see section 5.3).
4.7 Effects on ability to drive and use machines
HEPLISAV B may have a moderate influence on the ability to drive and use machine. Some of the effects mentioned under section 4.8 “Undesirable Effects” (e.g., malaise) may affect the ability to drive or operate machinery.
4.8 Undesirable effects
Summary of the safety profile:
The clinical trials safety profile is based on data from 9365 subjects followed in 3 pivotal studies.
In two studies, 3777 of the 9365 subjects were monitored for local and systemic post-injection reactions using diary cards for a 7-day period starting on the day of vaccination. The most common adverse reactions seen were the post-injection reactions injection site pain, headache, malaise, fatigue, and myalgia.
The reactogenicity profile of HEPLISAV B in 119 subjects on haemodialysis was generally comparable to that seen in healthy subjects.
Tabulated list of adverse reactions:
The frequency of adverse reactions is defined as follows:
Very common: (≥1/10) Common: (≥1/100 to <1/10) Uncommon: (≥1/1000 to <1/100) Rare: (≥1/10,000 to <1/1000) Very rare: (<1/10,000)
Within each frequency grouping, undesirable effects are presented in order of decreasing seriousness.
| System Organ Class | Frequency | Adverse Reactions |
| Nervous System Disorders | Very Common | Headache1 |
| Rare | Dizziness | |
| Rare | Paraesthesia | |
| Musculoskeletal and Connective Tissue Disorders | Very Common | Myalgia1 |
General Disorders and Administration Site Conditions | Very Common | Malaise1, fatigue1, injection site pain1 |
| Common | Injection site swelling, injection site erythema, fever1 | |
| Uncommon | Injection site pruritus2 | |
| Gastrointestinal disorders | Uncommon | Gastrointestinal symptoms 3 |
| Immune system disorders | Uncommon | Hypersensivity 4 |
| Very Rare | Anaphylaxis2 |
- 1. Local and systemic adverse reactions collected using diary cards.
- 2. Adverse reactions reported post-authorisation
- 3. Includes the individual preferred terms of nausea, vomiting, diarrhoea and abdominal pain.
- 4. Includes the individual preferred terms of urticaria, pruritus, and rash.
Additional information in special populations
Safety data are limited in immunocompromised adults, in adults previously vaccinated for hepatitis B and in adults with chronic renal failure, including patients on haemodialysis.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
No cases of overdose have been reported.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Vaccines, Viral Vaccines, Hepatitis Vaccine, ATC code: J07BC01
Mechanism of action
HEPLISAV B is comprised of recombinant hepatitis B surface antigen and the CpG 1018 adjuvant, which is a 22-mer PS-ODN immunostimulatory sequence.
HEPLISAV B induces specific antibodies against HBsAg (anti-HBs).
The biological actions of CpG 1018 are exerted locally at the injection site and draining lymph nodes. The adjuvant CpG 1018 component of HEPLISAV B has the following effects: (1) Activates plasmacytoid dendritic cells (pDCs) through the pattern recognition receptor Toll-like receptor 9; (2) converts pDCs into highly efficient antigen-presenting cells that present the processed HBsAg to CD4+ T cells; and, (3) promotes Th1 T-cell differentiation through the production of IFN-alpha and IL-12. This activation results in a high and sustained antibody response, likely due to the rapid generation of large numbers of anti-HBs-secreting plasmacytes and HBsAg-specific memory B and T cells.
Immune responses to HEPLISAV B
No efficacy trials were conducted due to the application of the well-established immune correlate of protection to the immune response (anti-HBs concentration ≥ 10 mIU/ml correlates with protection against HBV infection). The immunogenicity of HEPLISAV B was evaluated in 3 randomised, active controlled, observer-blinded, multicentre phase 3 clinical trials (HBV-10 with 3:1 randomisation, HBV-16 with 4:1 randomisation, and HBV-23 with 2:1 randomisation) including 9365 adults aged 18 to 70 years given HEPLISAV B, and 3867 adults given the comparator hepatitis B vaccine (Engerix-B 20 mcg HBsAg). HEPLISAV B was given as a 2-dose schedule at 0 and 1 month and Engerix-B was given using a 3-dose schedule at 0, 1, and 6 months.
Baseline characteristics were balanced between the treatment arms for age, sex, race, ethnicity, and body mass index (BMI). In the pooled analysis including all 3 trials, the mean age was 49.3 and 49.4 in the HEPLISAV B arm and Engerix-B arms, respectively and there were 50.8% and 51.5% female participants who received HEPLISAV B and Engerix-B, respectively.
The trials evaluated the seroprotection rates (SPR: percentage of vaccinated persons whose anti-HBs antibody levels were ≥ 10 mIU/ml after vaccination) after the second dose of HEPLISAV B compared to after the third dose of Engerix-B. The SPR and peak geometric mean concentration (GMC) after a 2-dose schedule of HEPLISAV B were statistically significantly higher than after a 3-dose schedule of Engerix-B (lower bound of the 95% confidence interval of the difference in SPRs between HEPLISAV B and Engerix-B was greater than 0%; lower bound of the 95% confidence interval of the ratio of GMCs between HEPLISAV B and Engerix-B was greater than 1.0) in all 3 trials (Table 1, Table 2).
Table 1 Comparison of Seroprotection Rates Between HEPLISAV
B and Engerix-B at Peak Weeks in Pooled Trials HBV-23, HBV-16 and HBV-10 (mITT Population)
| HEPLISAV B | Engerix-B | Difference | ||||
| N | n | SPR (%) (95% CI) | N | n | SPR (%) (95% CI) | (HEPLISAV B - Engerix-B) (95% CI) |
| 8701 | 8327 | 95.7 (95.3 - 96.1) | 3643 | 2898 | 79.5 (78.2 - 80.8) | 16.2 (14.8 - 17.6) |
N = number of evaluable subjects; n = number of seroprotected subjects; SPR = Seroprotection Rate, CI = confidence interval.
Seroprotection is defined as anti-HBs ≥ 10 mIU/mL.
Peak week comparison is for HEPLISAV B at Week 24 and Engerix-B at Week 28. The confidence intervals on seroprotection rates are calculated using the two-sided Clopper-Pearson method.
The confidence interval on the difference between treatment groups is calculated using the Miettinen and Nurminen method without stratification.
Table 2 Comparison of Anti-HBs Geometric Mean Concentrations at Peak Weeks Between HEPLISAV B and Engerix-B in Pooled Trials HBV-23, HBV-16 and HBV-10 (mITT Population)
| HEPLISAV B | Engerix-B | GMC Ratio | ||
| N | GMC (95% CI) | N | GMC (95% CI) | (HEPLISAV B / Engerix-B) (95% CI) |
| 8701 | 329.1 (317.1 - 341.5) | 3642 | 262.3 (236.4 - 291.1) | 1.3 (1.1 - 1.4) |
Peak week for HEPLISAV B is Week 24. Peak week for Engerix-B is Week 28.
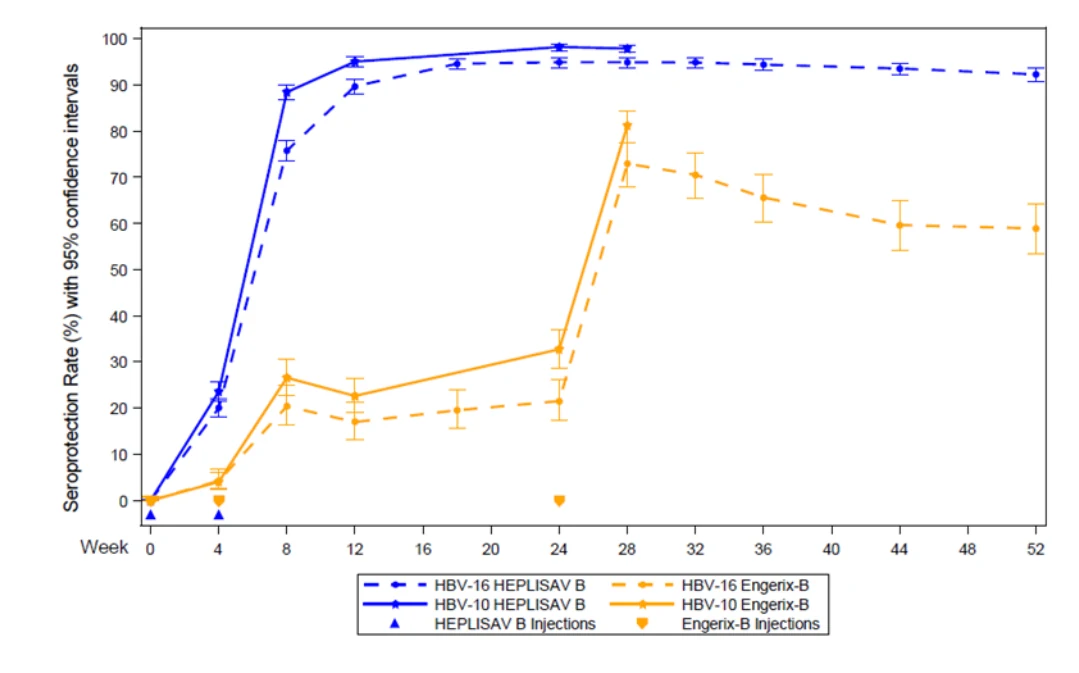
SPR results were collected at each study visit in two of the pivotal trials, HBV-10 (week 4 to 28) and HBV-16 (week 4 to 52). HEPLISAV B induced significantly higher SPRs than Engerix-B across all study visits in both studies (Figure 1).
Figure 1 Seroprotection Rates by Visit in Trials HBV-16 and HBV-
10 (Per Protocol Population)
In all three trials, SPRs induced by HEPLISAV B were statistically significantly higher than those induced by Engerix-B in older adults, men, obese individuals, smokers and subjects with type 2 diabetes mellitus (Table 3).
Table 3 Comparison of Seroprotection Rates Between HEPLISAV
B and Engerix-B at Peak Weeks by Category in Pooled Trials HBV-23, HBV-16 and HBV-10 (mITT Population)
| Category | HEPLISAV B | Engerix-B | Difference | ||||
| N | n | SPR (%) (95% CI) | N | n | SPR (%) (95% CI) | (HEPLISAV B - Engerix-B) (95% CI) | |
| All subjects | 8701 | 8327 | 95.7 (95.3 - 96.1) | 3643 | 2898 | 79.5 (78.2 - 80.8) | 16.2 (14.8 - 17.6) |
| Age Group (years) | |||||||
| 18 - 29 | 527 | 526 | 99.8 (98.9 - 100.0) | 211 | 196 | 92.9 (88.5 - 96.0) | 6.9 (4.1 - 11.2) |
| 30 - 39 | 1239 | 1227 | 99.0 (98.3 - 99.5) | 545 | 483 | 88.6 (85.7 - 91.2) | 10.4 (7.9 - 13.4) |
| 40 - 49 | 2377 | 2310 | 97.2 (96.4 - 97.8) | 963 | 771 | 80.1 (77.4 - 82.5) | 17.1 (14.6 - 19.8) |
| 50 - 59 ≥ | 2712 | 2578 | 95.1 (94.2 - 95.8) | 1120 | 872 | 77.9 (75.3 - 80.3) | 17.2 (14.7 - 19.8) |
| 60 | 1846 | 1686 | 91.3 (90.0 - 92.6) | 804 | 576 | 71.6 (68.4 - 74.7) | 19.7 (16.4 - 23.1) |
| Sex | |||||||
| Male | 4274 | 4055 | 94.9 (94.2 - 95.5) | 1765 | 1361 | 77.1 (75.1 - 79.1) | 17.8 (15.7 - 19.9) |
| Female | 4427 | 4272 | 96.5 (95.9 - 97.0) | 1878 | 1537 | 81.8 (80.0 - 83.6) | 14.7 (12.9 - 16.5) |
| BMI Stratum | |||||||
< 30 kg/m2 ≥ | 4904 | 4728 | 96.4 (95.9 - 96.9) | 2069 | 1756 | 84.9 (83.3 - 86.4) | 11.5 (10.0 - 13.2) |
| 30 kg/m2 | 3789 | 3591 | 94.8 (94.0 - 95.5) | 1570 | 1140 | 72.6 (70.3 - 74.8) | 22.2 (19.9 - 24.5) |
| Smoking Status | |||||||
| Smoker | 2634 | 2538 | 96.4 (95.6 - 97.0) | 1130 | 852 | 75.4 (72.8 - 77.9) | 21.0 (18.4 - 23.6) |
| Non-smoker | 6067 | 5789 | 95.4 (94.9 - 95.9) | 2513 | 2046 | 81.4 (79.8 - 82.9) | 14.0 (12.4 - 15.7) |
| Type 2 Diabetes Status and Age Group (Years) | |||||||
With T2D 20 - 39 | 38 | 37 | 97.4 (86.2 - 99.9) | 16 | 12 | 75.0 (47.6 - 92.7) | 22.4 (5.1 - 47.5) |
| 40 - 49 | 163 | 151 | 92.6 (87.5 - 96.1) | 67 | 49 | 73.1 (60.9 - 83.2) | 19.5 (9.2 - 31.7) |
| 50 - 59 ≥ | 334 | 303 | 90.7 (87.1 - 93.6) | 160 | 108 | 67.5 (59.7 - 74.7) | 23.2 (15.6 - 31.4) |
| 60 | 377 | 320 | 84.9 (80.9 - 88.3) | 165 | 97 | 58.8 (50.9 - 66.4) | 26.1 (17.9 - 34.5) |
BMI = body mass index; CI = confidence interval; N = number of evaluable subjects; n = number of seroprotected subjects; SPR = Seroprotection Rate; T2D = type 2 diabetes.
Seroprotection is defined as anti-HBs = 10 mIU/mL.
Peak week comparison is for HEPLISAV B at Week 24 and Engerix-B at Week 28. The confidence intervals on seroprotection rates are calculated using the two-sided Clopper-Pearson method.
The confidence interval on the difference between treatment groups is calculated using the Miettinen and Nurminen method without stratification
Haemodialysis
In a phase 1, open-label, single arm, multicentre study of 119 adults with end-stage renal disease who were undergoing haemodialysis, participants received a 4-dose regimen of HEPLISAV B at 0, 1, 2, and 4 months. The mean age was 59.9 years and 60.5% were male, 39.5% were female.
The primary analysis evaluated the SPR 5 months after the first dose of HEPLISAV B. In 75 participants who received all 4 doses of HEPLISAV-B, the SPR was 89.3% (95% confidence interval [CI]: 80.1%, 95.3%). In secondary analyses, 81.3% (95% CI: 70.7%, 89.4%) of subjects had an anti-HBs concentration ≥100 mIU/mL. The geometric mean concentration of anti-HBs was 1061.8 mIU/mL (95% CI: 547.2, 2060.2).
In a phase 3, randomised, open-label, multicentre study of 116 adult subjects with haemodialysis-dependent chronic kidney disease (CKD) who were non-responders to previous hepatitis B vaccination, participants received a 1-dose booster regimen of HEPLISAV B or Fendrix, or a double booster dose of Engerix-B.
Week 4 SPR in the HEPLISAV B group (42.1% n=16/38) was higher than the SPR in the Engerix-B group (18.9%, n=7/37) and the Fendrix group (29.3%, n=12/41). At Week 12, the SPR was 24.3% (n=9/37) in the HEPLISAV B group, 13.9% (n=5/36) in the Engerix-B group, and 26.8% (n=11/41) in the Fendrix group.
Paediatric population
The Medicines and Healthcare products Regulatory Agency has waived the obligation to submit the results of studies with HEPLISAV B in all subsets of the paediatric population for the prevention of hepatitis B virus infection (see section 4.2 for information on paediatric use).
5.2 Pharmacokinetic properties
The pharmacokinetic properties of the hepatitis B surface antigen used in HEPLISAV B have not been assessed.
Renal Impairment
The CpG 1018 adjuvant is cleared from plasma within 24 hours in renally-impaired adults after a single dose of 3000 micrograms. Dose adjustment is not required.
5.3 Preclinical safety data
Non-clinical data reveal no special hazard for humans based on conventional studies consisting of single-dose and repeat-dose toxicity (including local tolerance), and reproductive and developmental toxicity.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
- sodium chloride
- disodium phosphate dodecahydrate
- sodium dihydrogen phosphate dihydrate
- polysorbate 80 (E 433)
- water for injections
For adjuvants, see section 2.
6.2 Incompatibilities
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
6.3 Shelf life
3 years
6.4 Special precautions for storage
Store in a refrigerator (2°C to 8°C). Do not freeze.
Keep the pre-filled syringe in the outer carton in order to protect from light.
6.5 Nature and contents of container
0.5 ml of solution in a pre-filled syringe (Type I glass) with tip cap (synthetic isoprene-bromobutyl rubber blend) and plunger stopper (chlorobutyl rubber). The tip cap and stopper of the pre-filled syringe do not contain natural rubber latex.
Pack sizes of 1 and 5 pre-filled syringes without needle.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
HEPLISAV B is a clear to slightly opalescent, colourless to slightly yellow liquid and should be essentially free of visible particles. Do not administer if it appears otherwise.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Dynavax GmbH
Eichsfelder Strasse 11
D-40595 Düsseldorf
Germany
8 MARKETING AUTHORISATION NUMBER(S)
PLGB 55725/0001
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
Date of first authorisation: 24 February 2023
10 DATE OF REVISION OF THE TEXT
08/10/2024