

Summary of Product Characteristics (SmPC) - Fampridine Abdi 10 mg prolonged-release tablets
1 NAME OF THE MEDICINAL PRODUCT
Fampridine Abdi 10 mg prolonged-release tablets
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each prolonged-release tablet contains 10 mg of fampridine.
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Prolonged-release tablet.
An off-white, approximately 13.1 x 8.1 mm oval biconvex film coated tablets with flat edge, debossed “F 10” on one side and plain on other side.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Fampridine Abdi is indicated for the improvement of walking in adult patients with multiple sclerosis with walking disability (EDSS 4-7).
4.2 Posology and method of administration
Treatment with fampridine is restricted to prescription and supervision by physicians experienced in the management of MS.
Posology
The recommended dose is one 10 mg tablet, twice daily, taken 12 hours apart (one tablet in the morning and one tablet in the evening). Fampridine should not be administered more frequently or at higher doses than recommended (see section 4.4). The tablets should be taken without food
(see section 5.2).
Missed dose
The usual dosing regimen should always be followed. A double dose should not be taken if a dose is missed.
Starting and evaluating Fampridine Abdi treatment
- Initial prescription should be limited to two to four weeks of therapy as clinical benefits should generally be identified within two to four weeks after starting Fampridine Abdi
An assessment of walking ability, e.g. the Timed 25 Foot Walk (T25FW) or Twelve
Item Multiple Sclerosis Walking Scale (MSWS-12), is recommended to evaluate improvement within two to four weeks. If no improvement is observed, the treatment should be discontinued
- This medicinal product should be discontinued if benefit is not reported by patients.
Re-evaluating Fampridine Abdi treatment
If decline in walking ability is observed, physicians should consider an interruption to treatment in order to reassess the benefits of fampridine (see above). The re-evaluation should include withdrawal
of this medicinal product and performing an assessment of walking ability. Fampridine should be discontinued if patients no longer receive walking benefit.
Special populations
Elderly
Renal function should be checked in the elderly before starting treatment with this medicinal product. Monitoring renal function to detect any renal impairment is recommended in the elderly (see section 4.4).
Patients with renal impairment
Fampridine is contraindicated in patients with moderate and severe renal impairment (creatinine clearance < 50 mL/min) (see sections 4.3 and 4.4).
Patients with hepatic impairment
No dose adjustment is required for patients with hepatic impairment.
Paediatric population
The safety and efficacy of this medicinal product in children and adolescents aged 0 to 18 years have not been established. No data are available.
Method of administration
Fampridine Abdi is for oral use.
The tablet must be swallowed whole. It must not be divided, crushed, dissolved, sucked or chewed.
4.3 Contraindications
Hypersensitivity to fampridine or to any of the excipients listed in section 6.1.
Concurrent treatment with other medicinal products containing fampridine (4-aminopyridine). Patients with prior history or current presentation of seizure.
Patients with moderate or severe renal impairment (creatinine clearance < 50 mL/min).
Concomitant use of Fampridine Abdi with medicinal products that are inhibitors of Organic Cation Transporter 2 (OCT2) for example, cimetidine.
4.4 Special warnings and precautions for use
Seizure risk
Treatment with fampridine increases seizure risk (see section 4.8).
This medicinal product should be administered with caution in the presence of any factors which may lower seizure threshold.
Fampridine should be discontinued in patients who experience a seizure while on treatment.
Renal impairment
Fampridine is primarily excreted unchanged by the kidneys. Patients with renal impairment have higher plasma concentrations which are associated with increased adverse reactions, in particular neurological effects. Determining renal function before treatment and its regular monitoring during treatment is recommended in all patients (particularly in the elderly in whom renal function might be reduced). Creatinine clearance can be estimated using the Cockroft-Gault formula.
Caution is required when Fampridine Abdi is prescribed in patients with mild renal impairment or in patients using medicinal products that are substrates of OCT2 for example, carvedilol, propranolol and metformin.
Hypersensitivity reactions
In post-marketing experience, serious hypersensitivity reactions (including anaphylactic reaction) have been reported, the majority of these cases occurred within the first week of treatment. Particular attention should be given to patients with a previous history of allergic reactions. If an anaphylactic or other serious allergic reaction occurs, this medicinal product should be discontinued and not restarted.
Other warnings and precautions
Fampridine should be administered with caution to patients with cardiovascular symptoms of rhythm and sinoatrial or atrioventricular conduction cardiac disorders (these effects are seen in overdose).
There is limited safety information in these patients.
The increased incidence of dizziness and balance disorder seen with fampridine may result in an increased risk of falls. Therefore, patients should use walking aids as needed.
In clinical studies low white blood cell counts were seen in 2.1% of fampridine patients versus 1.9% of patients on placebo. Infections were seen in the clinical studies (see section 4.8) and increased infection rate and impairment of the immune response cannot be excluded.
4.5 Interaction with other medicinal products and other forms of interaction
Interaction studies have only been performed in adults.
Concurrent treatment with other medicinal products containing fampridine (4-aminopyridine) is contraindicated (see section 4.3).
Fampridine is eliminated mainly via the kidneys with active renal secretion accounting for about 60% (see section 5.2). OCT2 is the transporter responsible for the active secretion of fampridine. Thus, the concomitant use of fampridine with medicinal products that are inhibitors of OCT2 for example, cimetidine are contraindicated (see section 4.3) and concomitant use of fampridine with medicinal products that are substrates of OCT2 for example, carvedilol, propranolol and metformin is cautioned (see section 4.4.)
Interferon: fampridine has been administered concomitantly with interferon-beta and no pharmacokinetic medicinal product interactions were observed.
Baclofen: fampridine has been administered concomitantly with baclofen and no pharmacokinetic medicinal product interactions were observed.
4.6 Fertility, pregnancy and lactation
Pregnancy
There are limited amount of data from the use of fampridine in pregnant women.
Animal studies have shown reproductive toxicity (see section 5.3). As a precautionary measure it is preferable to avoid the use of fampridine in pregnancy.
Breast-feeding
It is unknown whether fampridine is excreted in human or animal milk. Fampridine Abdi is not recommended during breast-feeding.
Fertility
In animal studies no effects on fertility were seen.
4.7 Effects on ability to drive and use machines
Fampridine Abdi has a moderate influence on the ability to drive and use machines (see section 4.8).
4.8 Undesirable effects
Summary of the safety profile
The safety of fampridine has been evaluated in randomised controlled clinical studies, in open label long term studies and in the post marketing setting.
Adverse reactions identified are mostly neurological and include seizure, insomnia, anxiety, balance disorder, dizziness, paraesthesia, tremor, headache and asthenia. This is consistent with fampridine’s pharmacological activity. The highest incidence of adverse reactions identified from placebo- controlled trials in multiple sclerosis patients with fampridine given at the recommended dose, are reported as urinary tract infection (in approximately 12 % of patients).
Tabulated list of adverse reactions
Adverse reactions are presented below by system organ class and absolute frequency. Frequencies are defined as: very common (≥ 1/10); common (≥ 1/100 to < 1/10); uncommon (≥ 1/1,000 to < 1/100); rare (≥ 1/10,000 to < 1/1,000); very rare (< 1/10,000); not known (cannot be estimated from the available data).
Within each frequency grouping, adverse reactions are presented in the order of decreasing seriousness.
Table 1: Tabulated list of adverse reactions
| MedDRA System Organ Class (SOC) | Adverse reaction | Frequency category |
| Infections and infestations | Urinary tract infection1 Influenza1 Nasopharyngitis1 Viral infection1 | Very Common Common Common Common |
| Immune system disorders | Anaphylaxis Angioedema Hypersensitivity | Uncommon Uncommon Uncommon |
| Psychiatric disorders | Insomnia Anxiety | Commo n Commo n |
| Nervous system disorders | Dizziness Headache Balance disorder Vertigo Paraesthesia Tremor Seizure2 Trigeminal neuralgia3 | Common Common Common Common Common Common Uncommon Uncommon |
| MedDRA System Organ Class (SOC) | Adverse reaction | Frequency category |
| Cardiac disorders | Palpitations | Common |
| Tachycardia | Uncommon | |
| Vascular disorders | Hypotension4 | Uncommon |
| Respiratory, thoracic and mediastinal disorders | Dyspnoea Pharyngolaryngeal pain | Commo n Commo n |
| Gastrointestinal disorders | Nausea Vomiting Constipatio n Dyspepsia | Commo n Commo n Commo n Common |
| Skin and subcutaneous tissue disorders | Rash Urticaria | Uncommon Uncommon |
Musculoskeletal and connective tissue disorders | Back pain | Common |
| General disorders and administration site conditions | Asthenia Chest discomfort4 | Common Uncommon |
1 See section 4.4
2 See sections 4.3 and 4.4
3 Includes both de novo symptoms and exacerbation of existing trigeminal neuralgia 4 These symptoms were observed in the context of
hypersensitivity Description of selected adverse reactions
Hypersensitivity
In post-marketing experience, there have been reports of hypersensitivity reactions (including anaphylaxis) which have occurred with one or more of the following: dyspnoea, chest discomfort, hypotension, angioedema, rash and urticaria. For further information on hypersensitivity reactions, please refer to sections 4.3 and 4.4.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme.
Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Symptoms
Acute symptoms of overdose with fampridine were consistent with central nervous system excitation and included confusion, tremulousness, diaphoresis, seizure, and amnesia.
Central nervous system adverse reactions at high doses of 4-aminopyridine include dizziness, confusion, seizures, status epilepticus, involuntary and choreoathetoid movements. Other side effects at high doses include cases of cardiac arrhythmias (for example, supraventricular tachycardia and bradycardia) and ventricular tachycardia as a consequence of potential QT prolongation. Reports of hypertension have also been received.
Management
Patients who overdose should be provided supportive care. Repeated seizure activity should be treated with benzodiazepine, phenytoin, or other appropriate acute anti-seizure therapy.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Other nervous system drugs, ATC code: N07XX07.
Pharmacodynamic effects
Fampridine is a potassium channel blocker. By blocking potassium channels, fampridine reduces the leakage of ionic current through these channels, thereby prolonging repolarization and thus enhancing action potential formation in demyelinated axons and neurological function. Presumably, by enhancing action potential formation, more impulses might be conducted in the central nervous system.
Clinical efficacy and safety
Three phase III, randomised, double-blind, placebo controlled confirmatory studies, (MS-F203 and MS-F204 and 218MS305) have been performed. The proportion of responders was independent of concomitant immunomodulatory therapy (including interferons, glatiramer acetate, fingolimod and natalizumab). The fampridine dose was 10 mg twice a day.
Studies MS-F203 and MS-F204
The primary endpoint in studies MS-F203 and MS-F204 was the responder rate in walking speed as measured by the Timed 25-foot Walk (T25FW). A responder was defined as a patient who consistently had a faster walking speed for at least three visits out of a possible four during the double blind period as compared to the maximum value among five off-treatment visits.
A significantly greater proportion of fampridine treated patients were responders as compared to placebo (MS-F203: 34.8% vs. 8.3%, p< 0.001; MS-F204: 42.9% vs. 9.3%, p< 0.001).
Patients who responded to fampridineincreased their walking speed on average by 26.3% vs 5.3% on placebo (p< 0.001) (MS-F203) and 25.3% vs 7.8% (p< 0.001) (MS-F204). The improvement appeared rapidly (within weeks) after starting the treatment.
Statistically and clinically meaningful improvements in walking were seen, as measured by the 12-item Multiple Sclerosis Walking Scale.
Table 2: Studies MS-F203 and MS-F204
| STUDY * | MS-F203 | MS-F204 |


Placeb
o
Fampridi ne 10 mg twice daily
Placebo
Fampridi ne 10 mg twice daily 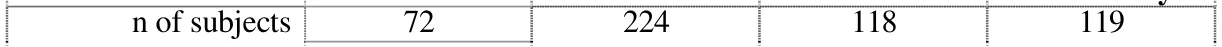
n of subjects 72 224 118 119 
Consistent improvement
34.8%
9.3%
42.9% 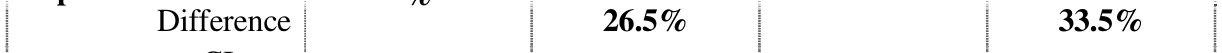
Difference 26.5% 33.5% 
CI95%
P-value
8.3
%
17.6%, 35.4% < 0.001
23.2%,
43.9% < 0.001
| STUDY * | MS-F203 | MS-F204 |


Placebo Fampridi
ne 10 mg
twice daily
Placebo
Fampridi ne 10 mg twice daily
≥ 20% improvement 11.1% 31.7% 15.3% 34.5%

Difference 20.6% 19.2% 
CI95%
P-value 11.1%,30.1
%
< 0.001
8.5%,29.9%
< 0.001 
Walking
speed
Feet/sec
Ft per sec Ft per sec Ft per sec Ft per sec 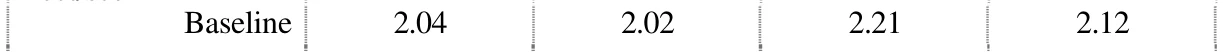
Baseline 2.04 2.02 2.21 2.12 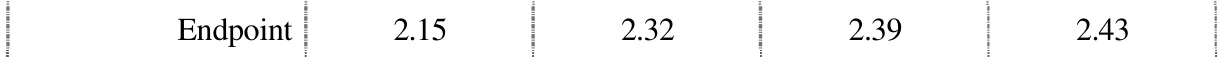 Endpoint 2.15 2.32 2.39 2.43
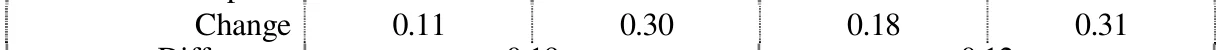 Change 0.11 0.30 0.18 0.31
 Difference 0.19 0.12
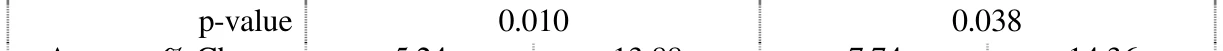
p-value 0.010 0.038 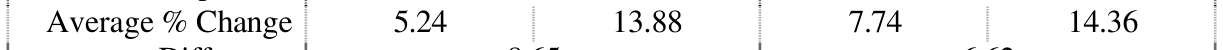 Average % Change 5.24 13.88 7.74 14.36

Difference 8.65 6.62 
p-value < 0.001 0.007 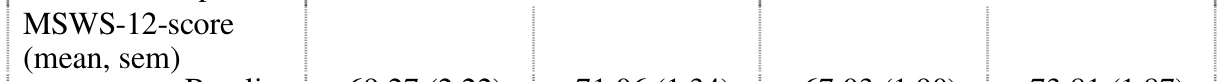 MSWS-12-score
(mean, sem) 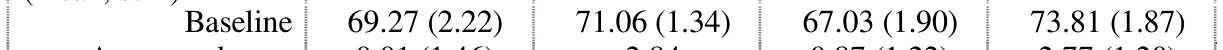
Baseline 69.27 (2.22) 71.06 (1.34) 67.03 (1.90) 73.81 (1.87) 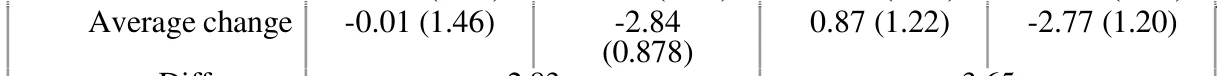 Average change -0.01 (1.46) -2.84
(0.878) 0.87 (1.22) -2.77 (1.20) 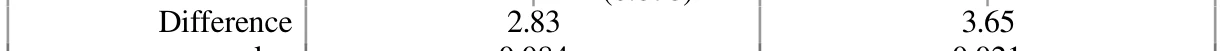
Difference 2.83 3.65 
p-value 0.084 0.021  LEMMT (mean, sem)
(Lower Extremity
Manual Muscle Test)
Baseline 3.92 (0.070) 4.01 (0.042) 4.01 (0.054) 3.95 (0.053) 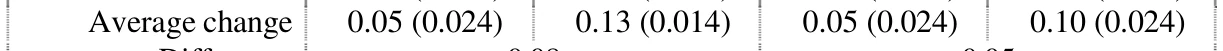 Average change 0.05 (0.024) 0.13 (0.014) 0.05 (0.024) 0.10 (0.024)

Difference 0.08 0.05 
p-value 0.003 0.106  Ashworth Score
(A test for
muscle
spasticity)
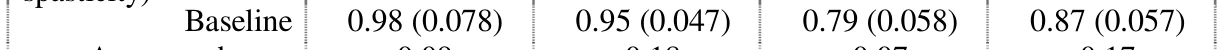
Baseline 0.98 (0.078) 0.95 (0.047) 0.79 (0.058) 0.87 (0.057) 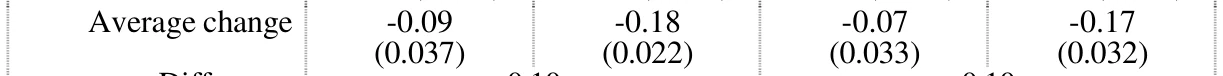 Average change -0.09
(0.037) -0.18
(0.022) -0.07
(0.033) -0.17
(0.032) 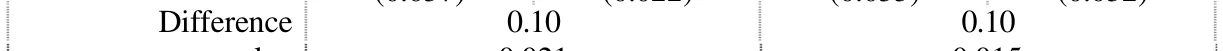 Difference 0.10 0.10

p-value 0.021 0.015
Study 218MS305
Study 218MS305 was conducted in 636 subjects with multiple sclerosis and walking disability. Duration of double-blind treatment was 24 weeks with a 2 week post–treatment follow-up. The primary endpoint was improvement in walking ability, measured as the proportion of patients achieving a mean improvement of ≥ 8 points from baseline MSWS-12 score over 24 weeks. In this study there was a statistically significant treatment difference, with a greater proportion of fampridine treated patients demonstrating an improvement in walking ability, compared to placebo-controlled patients (relative risk of 1.38 (95% CI: [1.06, 1.70]). Improvements generally appeared within 2 to 4 weeks of initiation of treatment, and disappeared within 2 weeks of treatment cessation.
Fampridine treated patients also demonstrated a statistically significant improvement in the Timed Up and Go (TUG) test, a measure of static and dynamic balance and physical mobility. In this secondary endpoint, a greater proportion of fampridine treated patients achieved ≥ 15% mean improvement from baseline TUG speed over a 24 week period, compared to placebo. The difference in the Berg Balance Scale (BBS; a measure of static balance), was not statistically significant.
In addition, patients treated with fampridine demonstrated a statistically significant mean improvement from baseline compared to placebo in the Multiple Sclerosis Impact Scale (MSIS-29) physical score (LSM difference -3.31, p<0.001).
Table 3: Study 218MS305
| Over 24 weeks | Placebo N = 318* | Fampridine 10 mg twice daily N = 315* | Difference (95% CI) p - value |
| Proportion of patients with mean improvement of ≥ 8 points from baseline MSWS-12 score | 34% | 43% | Risk difference: 10.4% (3% ; 17.8%) 0.006 |
MSWS-12 score Baseline Improvement from baseline | 65.4 -2.59 | 63.6 -6.73 | LSM: -4.14 (-6.22 ; -2.06) < 0.001 |
TUG Proportion of patients with mean improvement of ≥ 15% in TUG speed | 35% | 43% | Risk difference: 9.2% (0.9% ; 17.5%) 0.03 |
TUG Baseline Improvement from baseline (sec) | 27.1 -1.94 | 24.9 -3.3 | LSM: -1.36 (-2.85 ; 0.12) 0.07 |
MSIS-29 physical score Baseline Improvement from baseline | 55.3 -4.68 | 52.4 -8.00 | LSM: -3.31 (-5.13 ; -1.50) < 0.001 |
BBS score Baseline Improvement from baseline | 40.2 1.34 | 40.6 1.75 | LSM: 0.41 (-0.13 ; 0.95) 0.141 |
*Intent to treat population = 633; LSM = Least square mean, BID = twice a day
The European Medicines Agency has waived the obligation to submit the results of studies with the reference product containing fampridine in all subsets of the paediatric population in treatment of multiple sclerosis with walking disability (see section 4.2 for information on paediatric use).
5.2 Pharmacokinetic properties
Absorption
Orally administered fampridine is rapidly and completely absorbed from the gastrointestinal tract. Fampridine has a narrow therapeutic index. Absolute bioavailability of fampridine prolonged-release tablets has not been assessed, but relative bioavailability (as compared to an aqueous oral solution) is 95%. The fampridine prolonged-release tablet has a delay in the absorption of fampridine manifested by slower rise to a lower peak concentration, without any effect on the extent of absorption.
When fampridine prolonged-release tablets are taken with food, the reduction in the area under the plasma concentration-time curve (AUC0-∞) of fampridine is approximately 2-7% (10 mg dose). The small reduction in AUC is not expected to cause a reduction in the therapeutic efficacy. However, Cmax increases by 15-23%. Since there is a clear relationship between Cmax and dose related adverse reactions, it is recommended to take Fampridine Abdi without food (see section 4.2).
Distribution
Fampridine is a lipid-soluble active substance which readily crosses the blood-brain barrier. Fampridine is largely unbound to plasma proteins (bound fraction varied between 3-7% in human plasma). Fampridine has a volume of distribution of approximately 2.6 L/kg.
Fampridine is not a substrate for P-glycoprotein. Biotransformation
Fampridine is metabolised in humans by oxidation to 3-hydroxy-4-aminopyridine and further conjugated to the 3-hydroxy-4-aminopyridine sulfate. No pharmacological activity was found for the fampridine metabolites against selected potassium channels in vitro.
The 3-hydroxylation of fampridine to 3-hydroxy-4-aminopyridine by human liver microsomes appeared to be catalysed by Cytochrome P450 2E1 (CYP2E1).
There was evidence of direct inhibition of CYP2E1 by fampridine at 30 μM (approximately 12% inhibition) which is approximately 100 times the average plasma fampridine concentration measured for the 10 mg tablet.
Treatment of cultured human hepatocytes with fampridine had little or no effect on induction of CYP1A2, CYP2B6, CYP2C9, CYP2C19, CYP2E1 or CYP3A4/5 enzyme activities.
Elimination
The major route of elimination for fampridine is renal excretion, with approximately 90% of the dose recovered in urine as parent active substance within 24 hours. Renal clearance (CLR 370 mL/min) is substantially greater than glomerular filtration rate due to combined glomerular filtration and active excretion by the renal OCT2 transporter. Faecal excretion accounts for less than 1% of the administered dose.
Fampridine is characterized by linear (dose-proportional) pharmacokinetics with a terminal elimination half-life of approximately 6 hours. The maximum plasma concentration (Cmax) and, to a smaller extent, area under the plasma concentration-time curve (AUC) increase proportionately with dose. There is no evidence of clinically relevant accumulation of fampridine taken at the recommended dose in patients with full renal function. In patients with renal impairment, accumulation occurs relative to the degree of impairment.
Special populations
Elderly
Fampridine is primarily excreted unchanged by the kidneys, and with creatinine clearance known to decrease with age, monitoring of renal function in elderly patients is recommended (see section 4.2).
Paediatric population
No data are available.
Patients with renal impairment
Fampridine is eliminated primarily by the kidneys as unchanged active substance and therefore renal function should be checked in patients where renal function might be compromised. Patients with mild renal impairment can be expected to have approximately 1.7 to 1.9 times the fampridine concentrations achieved by patients with normal renal function. Fampridine Abdi must not be administered to patients with moderate and severe renal impairment (see sections 4.3 and 4.4).
5.3 Preclinical safety data
Fampridine was studied in oral repeat dose toxicity studies in several animal species.
Adverse responses to orally administered fampridine were rapid in onset, most often occurring within the first 2 hours post-dose. Clinical signs evident after large single doses or repeated lower doses were similar in all species studied and included tremors, convulsions, ataxia, dyspnoea, dilated pupils, prostration, abnormal vocalization, increased respiration, and excess salivation. Gait abnormalities and hyper-excitability were also observed. These clinical signs were not unexpected and represent exaggerated pharmacology of fampridine. In addition, single cases of fatal urinary tract obstructions were observed in rats. The clinical relevance of these findings remains to be elucidated, but a causal relationship with fampridine treatment cannot be excluded.
In reproduction toxicity studies in rats and rabbits, decreased weight and viability of foetuses and offspring were observed at maternally toxic doses. However, no increased risk for malformations or adverse effects on fertility was noted.
In a battery of in vitro and in vivo studies fampridine did not show any potential to be mutagenic, clastogenic or carcinogenic.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Tablet core
Hypromellose
Microcrystalline cellulose
Silica, colloidal anhydrous
Magnesium stearate
Film-coat
Hypromellose (E464)
titanium dioxide (E 171)
Macrogol (MW 400) (E1521)
6.2 Incompatibilities
Not applicable.
6.3 Shelf life
2 years
6.4 Special precautions for storage
This medicinal product does not require any special storage conditions.
6.5 Nature and contents of container
OPA/Al/PVC//Alblisters
Packs containing 28 and 56 prolonged-release tablets.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
No special requirements.
7 MARKETING AUTHORISATION HOLDER
Abdi Farma GmbH
Donnersbergstraße 4
64646 Heppenheim
Germany
8 MARKETING AUTHORISATION NUMBER(S)
PL 56740/0039
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
05/08/2025
10 DATE OF REVISION OF THE TEXT
05/08/2025