


Summary of Product Characteristics (SmPC) - Elzonris 1 mg / ml concentrate for solution for infusion
1 NAME OF THE MEDICINAL PRODUCT
ELZONRIS 1 mg/mL concentrate for solution for infusion
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
1 mL of concentrate for solution for infusion contains 1 mg tagraxofusp. Each vial contains 1 mg of tagraxofusp.
Tagraxofusp is a diphtheria toxin-interleukin-3 (IL-3) fusion protein produced by recombinant DNA technology in Escherichia coli.
Excipient with known effect
Each vial contains 50 mg of sorbitol (E420).
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Concentrate for solution for infusion (sterile concentrate).
Clear, colourless liquid. A few white to translucent particles may be present.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
ELZONRIS is indicated as monotherapy for the first-line treatment of adult patients with blastic plasmacytoid dendritic cell neoplasm (BPDCN) (see section 5.1).
4.2 Posology and method of administration
ELZONRIS should be administered under the supervision of a physician experienced in the use of anti-cancer agents. Appropriate resuscitation equipment should be available.
Posology
The recommended dose is 12 mcg/kg tagraxofusp administered as an intravenous infusion over 15 minutes, once daily, on days 1-5 of a 21-day cycle. The dosing period may be extended for dose delays up to day 10 of the cycle. Treatment should be continued until disease progression or unacceptable toxicity (see section 4.4).
First treatment cycle
The first cycle of ELZONRIS should be administered in the in-patient setting. Patients should be monitored for signs and symptoms of hypersensitivity or capillary leak syndrome (see section 4.4) until at least 24 hours after the last infusion.
Subsequent treatment cycles
ELZONRIS can be administered in the in-patient setting or in a suitable out-patient ambulatory care setting that is equipped for intensive monitoring of patients with haematopoietic malignancies undergoing treatment.
Pre-medication
Patients should be pre-medicated with a H1-histamine antagonist (e.g. diphenhydramine hydrochloride), a H2-histamine antagonist, a corticosteroid (e.g. 50 mg intravenous methylprednisolone or equivalent) and paracetamol approximately 60 minutes prior to the start of infusion (see section 4.4).
Dose adjustments
Vital signs should be monitored and albumin, transaminases, and creatinine checked prior to preparing each dose of ELZONRIS. See Table 1 for recommended dose modifications and Table 2 for capillary leak syndrome (CLS) management guidelines.
Vital signs should be monitored frequently during dosing.
Table 1: Recommended ELZONRIS dosing regimen modifications
| Parameter | Severity criteria | Dose modification |
| Serum albumin | Serum albumin < 3.5 g/dL or reduced ≥ 0.5 g/dL from value measured prior to initiation of the current cycle ≥ | See CLS Management Guidelines (Table 2) |
| Body weight | Body weight increase 1.5 kg over pre-treatment weight on prior treatment day | See CLS Management Guidelines (Table 2) |
Aspartate aminotransferase (AST) or alanine aminotransferase (ALT) | ALT or AST increase > 5 times the upper limit of normal | Withhold treatment until transaminase elevations are ≤ 2.5 times the upper limit of normal. |
| Serum creatinine | Serum creatinine > 1.8 mg/dL (159 micromol/L) or creatinine clearance < 60 mL/minute | Withhold treatment until serum creatinine resolves to ≤ 1.8 mg/dL (159 micromol/L) or creatinine clearance ≥ 60 mL/minute. |
| Systolic blood pressure | Systolic blood pressure ≥ 160 mmHg or ≤ 80 mmHg ≥ | Withhold treatment until systolic blood pressure is < 160 mmHg or > 80 mmHg. |
| Heart rate | Heart rate 130 bpm or ≤ 40 bpm | Withhold treatment until heart rate is < 130 bpm or > 40 bpm. |
Body temperature | Body temperature ≥ 38 °C | Withhold treatment until body temperature is < 38 °C. |
| Hypersensitivity reactions | Mild or moderate | Withhold treatment until resolution of any mild or moderate hypersensitivity reaction. Resume ELZONRIS at the same infusion rate. |
Table 2: CLS management guidelines
| Time of Presentation | CLS Sign/Symptom | Recommended Action | ELZONRIS Dosing Management |
| Prior to first dose of ELZONRIS in cycle 1 | Serum albumin < 3.2 g/dL | Administer ELZONRIS when serum albumin ≥ 3.2 g/dL | |
During ELZONRIS dosing | Serum albumin < 3.5 g/dL | Administer 25 g intravenous albumin every 12 hours (or more frequently as practical) until serum albumin is ≥ 3.5 g/dL AND not reduced by ≥ 0.5 g/dL from the value measured prior to dosing initiation of the current cycle | |
| Serum albumin reduced by ≥ 0.5 g/dL from the albumin value measured prior to ELZONRIS dosing initiation of the current cycle | |||
A pre-dose body weight that is increased by ≥ 1.5 kg over the previous day’s pre-dose weight | Administer 25 g intravenous albumin (every 12 hours or more frequently as practical), and manage fluid status as indicated clinically (e.g., generally with | ||
intravenous fluids and vasopressors
| Hold dosing until the relevant CLS sign/symptom has resolved 1 |
1 If ELZONRIS dose is held:
- ELZONRIS administration may resume in the same cycle if all CLS signs/symptoms have resolved and the patient did not require measures to treat haemodynamic instability.
- Administration should be held for the remainder of the cycle if CLS signs/symptoms have not resolved or the patient required measures to treat haemodynamic instability (e.g., required administration of intravenous fluids and/or vasopressors to treat hypotension) (even if resolved).
- Administration may only resume in the next cycle if all CLS signs/symptoms have resolved, and the patient is haemodynamically stable.
Special populations
Renal impairment
No data are available for patients with renal impairment (see section 5.2).
Hepatic impairment
No data are available for patients with hepatic impairment (see section 5.2).
Elderly
No dose adjustment is required for patients over 65 years of age (see section 5.2). Generally, safety was similar between elderly patients (≥ 65 years of age) and patients less than 65 years of age treated with ELZONRIS.
Paediatric population
The safety and efficacy of ELZONRIS in children and adolescents below 18 years have not been established (see section 5.1).
No data are available.
Method of administration
| longer |
≥
| 1.5 kg greater than the previous day’s pre-dose weight). | |||
| Oedema, fluid overload and/or hypotension | Administer 25 g intravenous albumin (every 12 hours, or more frequently as practical) until serum albumin is ≥ 3.5 g/dL. Administer 1 mg/kg of methylprednisolone (or an equivalent) per day, until resolution of CLS sign/symptom or as indicated clinically. Aggressive management of fluid status and hypotension if present, which could include intravenous fluids and/or diuretics or other blood pressure management, until resolution of CLS sign/symptom or as clinically indicated. |
ELZONRIS is for intravenous use.
The prepared dose of diluted ELZONRIS should be administered via an infusion syringe pump over 15 minutes. The total infusion time should be controlled using an infusion syringe pump to deliver the entire dose and the sodium chloride 9 mg/mL (0.9%) solution for injection within 15 minutes.
ELZONRIS must not be administered as an intravenous push or bolus. It should be administered through a dedicated intravenous line and it must not be mixed with other medicinal products (see section 6.2).
Prior to infusion, venous access should be established and maintained with sodium chloride 9 mg/mL (0.9%) solution for injection.
For instructions on preparation and administration of the medicinal product, see section 6.6.
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
4.4 Special warnings and precautions for use
Traceability
In order to improve the traceability of biological medicinal products, the name and the batch number of the administered product should be clearly recorded.
Capillary leak syndrome
Capillary leak syndrome (CLS), including life-threatening and fatal cases have been reported with most events occuring during the first five days of the first cycle of treatment. The most frequent signs and symptoms of CLS included weight increased, hypoalbuminemia and hypotension. The incidence of weight increased, hypoalbuminemia, hypotension, and blood alkaline phosphatase increased are all higher among patients who experienced CLS compared to patients that did not experience CLS. Renal failure and acute kidney injury have been reported in two patients with BPDCN and in one patient with AML secondary to CLS (see section 4.8).
Before initiating therapy, ensure that the patient has adequate cardiac function and serum albumin ≥ 3.2 g/dL. During treatment, regularly monitor serum albumin levels prior to the initiation of each dose, or more often as clinically indicated. Additionally, assess patients for other signs/symptoms of CLS including weight gain, new onset or worsening oedema, including pulmonary oedema, and hypotension including haemodynamic instability (see Table 2).
Patients should be made aware of identifying CLS symptoms and when to seek immediate medical attention. Intravenous albumin supplementation and dosing interruptions may be required (see section 4.2).
Hypersensitivity reactions
Severe hypersensitivity reactions have been reported with ELZONRIS. Commonly reported reactions include rash (generalised / maculo-papular); wheezing; pruritus; angioedema; swelling face; and flushing (see section 4.8). Monitor patients for hypersensitivity reactions during treatment. Depending on the severity and the required interventions, temporarily withhold treatment and resume after symptoms have resolved (see section 4.2).
Haematological abnormalities
Thrombocytopenia and neutropenia have been reported in patients treated with ELZONRIS monotherapy (see section 4.8). The majority of events were reported in cycle 1 and cycle 2 of treatment, were not dose-limiting and did not recur in subsequent cycles. Patients should be routinely monitored and treated as clinically indicated.
Tumour lysis syndrome
ELZONRIS can cause tumour lysis syndrome (TLS), which may be fatal as a result of its rapid anti-tumour activity (see section 4.8).
Identify TLS based on clinical presentation and symptoms, including acute renal failure, hyperkalaemia, hypocalcaemia, hyperuricaemia, or hyperphosphataemia from tumour lysis. Patients considered at high risk for TLS due to high tumour burden should be managed as clinically indicated, including correction of electrolyte abnormalities, monitoring of renal function and fluid balance, and administration of supportive care.
Hepatotoxicity
Treatment with ELZONRIS has been associated with elevations in liver enzymes (see section 4.8). Acute hepatic failure and liver encephalopathy has been reported in a patient treated with ELZONRIS at a higher dose (16 mcg/kg). During treatment, regularly monitor ALT and AST levels prior to the initiation of each dose. Temporarily withhold treatment if transaminases rise to greater than 5 times the upper limit of normal and resume treatment when transaminase elevations are ≤ 2.5 times the upper limit of normal (see section 4.2).
Choroid plexus lesions
Choroid plexitis was identified during non-clinical studies (see section 5.3). While not observed in clinical studies, if clinical symptoms or signs suggestive of central nervous system (CNS) damage occur, full clinical and neuro-imaging examination, including fundoscopy and brain magnetic resonance imaging, is recommended.
CNS-involved BPDCN
The passage of tagraxofusp through the blood brain barrier is unknown. Other treatment alternatives should be considered if CNS disease is present.
Women of childbearing potential/contraception
In women of childbearing potential, a negative pregnancy test should be obtained within 7 days prior to initiation of therapy. Effective contraception should be used before the first dose is administered and for at least one week after the last dose.
Hereditary fructose intolerence
Patients with hereditary fructose intolerance (HFI) must not be given this medicinal product unless strictly necessary.
A detailed history with regard to HFI symptoms has to be taken of each patient prior to being given this medicinal product.
Sodium sensitivity
This medicinal product contains less than 1 mmol sodium (23 mg) per mL, that is to say essentially ‘sodium-free’.
4.5 Interaction with other medicinal products and other forms of interaction
No interaction studies have been performed.
4.6 Fertility, pregnancy and lactation
Women of childbearing potential/Contraception
In women of childbearing potential, a negative pregnancy test should be obtained within 7 days prior to initiation of therapy. Effective contraception should be used before the first dose is administered and for at least one week after the last dose.
Pregnancy
There are no data from the use of ELZONRIS in pregnant women. Animal reproduction studies have not been conducted with tagraxofusp (see section 5.3).
ELZONRIS should not be used during pregnancy unless the clinical condition of the woman requires treatment with tagraxofusp.
Breast-feeding
It is unknown whether tagraxofusp/metabolites are excreted in human milk. A risk to breast-feeding newborns/infants cannot be excluded.
Breast-feeding should be discontinued during treatment with ELZONRIS and for at least one week after the last dose.
Fertility
No fertility studies have been conducted with tagraxofusp (see section 5.3). There are no data on the effect of tagraxofusp on human fertility.
4.7 Effects on ability to drive and use machines
ELZONRIS has no or negligible influence on the ability to drive or use machines.
4.8 Undesirable effects
Summary of the safety profile
The most serious adverse reaction that may occur during ELZONRIS treatment is CLS (see sections 4.2 and 4.4) which was reported in 18% of patients with a median time to onset of CLS of 6 days.
Adverse reactions occurring in ≥ 20% of patients treated with ELZONRIS were hypoalbuminemia, increased transaminases, thrombocytopenia, nausea, fatigue and pyrexia.
Adverse reactions grade 3 and above according to the Common Terminology Criteria for Adverse events (CTCAE) and occurring in > 5% of patients were increased transaminases, thrombocytopenia and anaemia.
Tabulated list of adverse reactions
The adverse reaction frequency is listed by MedDRA System Organ Class (SOC) at the preferred term level. Frequencies of occurrence of adverse reactions are defined as: very common (≥ 1/10), common (≥ 1/100 to < 1/10) and uncommon (≥ 1/1000 to < 1/100).
The adverse reactions described in this section were identified in clinical studies of patients with haematologic malignancies (N=176), including 89 patients with BPDCN. In these studies, ELZONRIS was administered as monotherapy at doses of 7 mcg/kg (12/176, 7%), 9 mcg/kg (9/176, 5%) and 12 mcg/kg (155/176, 88%). Incidence and severity of adverse reaction in patients with BPDCN were similar to those of the entire studied population.
Table 3: Tabulated list of adverse reactions by MedDRA System Organ Class
| MedDRA System Organ Class | Frequency of all CTCAE grades | Frequency of CTCAE grade 3 and above |
| Infections and infestations | Common Cellulitis Uncommon Pneumonia Urinary tract infection Gingivitis | None |
Blood and lymphatic system disorders | Very Common Thrombocytopenia Anaemia Common Febrile neutropenia Neutropenia Leukopenia Leukocytosis | Very Common Thrombocytopenia Common Febrile neutropenia Anaemia Neutropenia Leukopenia Lymphopenia |
| MedDRA System Organ Class | Frequency of all CTCAE grades | Frequency of CTCAE grade 3 and above |
| Lymphopenia | Uncommon Leukocytosis | |
| Immune system disorders | Common Cytokine release syndrome | Uncommon Cytokine release syndrome |
| Metabolism and nutrition disorders | Very Common Hypoalbuminemia Common Decreased appetite Tumour lysis syndrome Hyperglycaemia Hyperuricaemia Hypocalcaemia Hypomagnesaemia Hyponatraemia Hypokalaemia Hyperkalaemia Hyperphosphataemia Uncommon Hypophosphataemia Lactic acidosis Acidosis | Common Tumour lysis syndrome Hyperglycaemia Hypoalbuminemia Hyponatraemia Uncommon Hyperuricaemia Hypocalcaemia Hypokalaemia Lactic acidosis Acidosis |
| Psychiatric disorders | Common Confusional state Uncommon Anxiety Depression Insomnia Mental status changes | None |
| Nervous system disorders | Common Syncope Headache Dizziness Uncommon Encephalopathy Metabolic encephalopathy Cerebrovascular accident Facial paralysis Dysgeusia Multiple sclerosis relapse Somnolence Paraesthesia Parosmia Peripheral motor neuropathy Peripheral sensory neuropathy | Common Syncope Uncommon Cerebrovascular accident Metabolic encephalopathy |
| Eye Disorders | Common Vision blurred Uncommon Conjunctival haemorrhage Ocular hyperaemia Vitreous floaters | None |
| Cardiac Disorders | Common Pericardial effusion Tachycardia Sinus tachycardia Uncommon Ventricular fibrillation Supraventricular extrasystoles | Uncommon Ventricular fibrillation Pericardial effusion Sinus tachycardia Myocardial infarction |
| MedDRA System Organ Class | Frequency of all CTCAE grades | Frequency of CTCAE grade 3 and above |
Atrial fibrillation Bradycardia Myocardial infarction | ||
| Vascular disorders | Very Common Capillary leak syndrome Hypotensiona Common Flushing Uncommon Hypertension Haematoma | Common Capillary leak syndrome Hypotension |
| Respiratory, thoracic and mediastinal disorders | Common Hypoxia Pulmonary oedema Dyspnoea Epistaxis Pleural effusion Cough Uncommon Respiratory failure Wheezing Oropharyngeal pain Tachypnoea | Common Hypoxia Pulmonary oedema Uncommon Respiratory failure Dyspnoea |
| Gastrointestinal Disorders | Very Common Nausea Vomiting Common Dysphagia Diarrhoea Stomatitis Dyspepsia Dry mouth Constipation Uncommon Abdominal distension Abdominal pain Gingival bleeding Tongue blistering Tongue haematoma | Uncommon Nausea |
| Hepatobiliary disorders | Common Hyperbilirubinemia | None |
Skin and subcutaneous tissue disorders | Common Pruritus Rashb Hyperhidrosis Petechiae Uncommon Angioedema Swelling face Palmar-plantar erythrodysesthesia syndrome Urticaria Alopecia Pain of skin Stasis dermatitis Cold sweat Dry skin | Uncommon Angioedema Rash |
| Musculoskeletal | Common | Uncommon |
| MedDRA System Organ Class | Frequency of all CTCAE grades | Frequency of CTCAE grade 3 and above |
| and connective tissue disorders | Back pain Bone pain Myalgia Arthralgia Pain in extremity Muscular weakness Uncommon Musculoskeletal pain Coccydynia Muscle spasms Rhabdomyolysis | Back pain Arthralgia Rhabdomyolysis |
| Renal and urinary disorders | Common Acute kidney injury Uncommon Renal failure Urinary retention Urinary tract pain Pollakiuria Proteinuria | Uncommon Acute kidney injury |
| General disorders and administration site conditions | Very Common Pyrexia Chills Fatiguec Oedema peripherald Common Influenza-like illness Chest pain Pain Malaise Uncommon Drug intolerance Hypothermia Systemic inflammatory response syndrome | Common Fatigue Uncommon Pyrexia Chills Oedema peripheral Drug intolerance |
| Investigations | Very Common Transaminases increasede Weight increased Common Electrocardiogram QT prolonged Blood alkaline phosphatase increased Blood creatinine increased Blood lactate dehydrogenase increased Blood creatine phosphokinase increased Activated partial thromboplastin time prolonged International normalised ratio increased Uncommon Blood fibrinogen decreased Bacterial test positive Weight decreased | Very Common Transaminases increased Uncommon Electrocardiogram QT prolonged Blood lactate dehydrogenase increased Bacterial test positive |
| Injury, poisoning and procedural complications | Common Infusion related reaction Contusion | Uncommon Infusion related reaction |
a Includes procedural hypotension, orthostatic hypotension
b Includes rash pustular, rash maculo-papular, rash erythematous, rash generalised, rash macular
c Includes asthenia, lethargy
d Includes generalised oedema, oedema, peripheral swelling, fluid retention, fluid overload, periorbital oedema, hypervolaemia
e Includes ALT/AST increased, liver function test increased, hepatic enzyme increased
Description of selected adverse reactions
Capillary leak syndrome
Capillary leak syndrome was reported in 18% (32/176), with 12% (21/176) Grade 2, 3% (6/176) Grade 3, 1% (2/176) Grade 4, and fatal in 1.7% (3/176). Of the 25 patients that resumed treatment after experiencing an event of CLS, only 1 patient experienced a recurrence of CLS. The median time to onset of CLS was short (6 days), with all but 2 patients experiencing the first onset of CLS in cycle 1. No patient experienced the first onset of CLS after cycle 2. The overall incidence of CLS was similar in patients with BPDCN (20%, 18/89), including 12% (11/89) Grade 2, 2% Grade 3 (2/89), 2% Grade 4 (2/89) and 3 fatal cases (3%). Patients are required to have adequate cardiac function prior to administration of ELZONRIS (see sections 4.2 and 4.4).
Hepatotoxicity
ALT and AST elevations were reported as adverse reactions in 47% (83/176) and 46% (81/176) of patients treated with ELZONRIS monotherapy, respectively. ≥ Grade 3 ALT and AST increased were reported in 23% (40/176) and 23% (40/176), respectively. Elevated liver enzymes occurred in the majority of patients in cycle 1 and were reversible following dose interruptions (see section 4.4). Similar onset time and incidence were observed in patients with BPDCN, with 51% (45/89) of patients experiencing adverse events of ALT and AST elevations, with ≥ Grade 3 ALT and AST increased reported in 28% (25/89) and 29% (26/89) respectively. Two patients with BPDCN met the laboratory criteria for Hy’s Law; in both cases the laboratory abnormalities were noted during Cycle 1.
Haematological abnormalities
Thrombocytopenia was reported in 30% (53/176) of patients treated with ELZONRIS monotherapy and in 35% (31/89) of patients with BPDCN. Thrombocytopenia Grade ≥ 3 was reported in 23% (40/176) of patients treated with ELZONRIS monotherapy and in 26% (23/89) of patients with BPDCN. The majority of thrombocytopenia events were reported in cycle 1 and cycle 2 of treatment. Neutropenia was reported in 9% (15/176) of patients treated with ELZONRIS monotherapy and in 11% (10/89) of patients with BPDCN, with events ≥ Grade 3-reported in 6% (11/176) and 8% (7/89), respectively.
Hypersensitivity
Reactions representative of hypersensitivity were reported in 19% (33/176) of patients treated with ELZONRIS monotherapy and in 17% (15/89) of patients with BPDCN, with events ≥ Grade 3 reported in 3% (6/176) and 4% (4/89), respectively (see section 4.4).
Immunogenicity
Immune response was evaluated by assessment of serum binding reactivity against tagraxofusp (anti-drug antibodies; ADA) and neutralising antibodies by inhibition of functional activity. Immune response was assessed using two immunoassays. The first assay detected reactivity directed against tagraxofusp (ADA), and the second assay detected reactivity against the interleukin-3 (IL-3) portion of tagraxofusp. Two cell-based assays were used to investigate the presence of neutralising antibodies by inhibition of a cell-based functional activity.
In 190 patients treated with ELZONRIS in four clinical studies:
- 94% (176/187) of patients evaluable for the presence of pre-existing ADA at baseline before treatment were confirmed positive with 27% being positive for the presence of neutralising antibodies. The high prevalence of ADA at baseline was anticipated due to diphtheria immunisation.
- 100% (N=170) of patients evaluable for treatment-emergent ADA tested positive with most patients showing an increase in ADA titre by the end of Cycle 2 of ELZONRIS.
- 92% (155/169) of ADA-positive patients evaluable for the presence of neutralising antibodies post-treatment were neutralising antibody-positive.
- 75% (129/171) of patients evaluable for treatment-emergent anti-IL-3 antibodies tested positive with most patients testing positive by Cycle 3 of ELZONRIS.
- 74% (93/126) of patients who tested positive for anti-IL-3 antibodies and were evaluable for the presence of neutralising antibodies were neutralising antibody-positive
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme
Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
There have been no cases of overdose reported with ELZONRIS. In case of overdose, patients should be closely monitored for signs or symptoms of adverse reactions, and appropriate symptomatic treatment provided immediately.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Antineoplastic agents; other antineoplastic agents, ATC code: L01XX67
Mechanism of action
Tagraxofusp is a CD123-directed cytotoxin composed of recombinant human interleukin-3 (IL-3) and truncated diphtheria toxin (DT) fusion protein that targets CD123-expressing cells. Tagraxofusp irreversibly inhibits protein synthesis of target cells by inactivating elongation factor 2 (EF2), resulting in apoptosis (cell death).
Clinical efficacy and safety
Study STML-401-0114 was a multi-stage (stage 1 dose escalation, stage 2 expansion, stage 3 confirmatory, stage 4 continued access), non-randomised, open-label, multi-centre study of ELZONRIS. ELZONRIS was administered to 65 previously-untreated and 19 previously treated adult patients with BPDCN according to the WHO classification who received a 12 mcg/kg dose on days 1-5 of multiple 21-day cycles (Table 4). Patients who had known active or suspected CNS leukaemia were not included in the study. The primary endpoint was the rate of complete response (CR; complete resolution of the disease)/clinical complete response (CRc; CR with residual skin abnormality not indicative of active disease). Across all 65 previously untreated patients ELZONRIS resulted in a CR/CRc rate of 56.9% (95% CI: 44.0, 69.2), this included 13 patients in the confirmatory efficacy cohort where the CR/CRc rate was 53.8% (95% CI: 25.1, 80.8). (Table 5).
Patient baseline characteristics are presented in Table 4 and key efficacy measures in Table 5.
Table 4: Baseline demographics of patients with treatment-naïve BPDCN treated with 12 mcg/kg of ELZONRIS
Parameter
Treatment-naive
BPDCN N=65
Gender, N (%)
Male
Female
52 (80) 13 (20) Race, N (%)
White
Other
57 (88) 8 (12)
Age (years)
Median
68
Minimum, Maximum 22, 84 ECOG, N (%)
0
1
2
31 (48) 31 (48) 2 (3)
BPDCN at Baseline, N (%) Skin
Bone Marrow
Peripheral Blood
Lymph Nodes
Visceral
60 (92) 32 (49) 17 (26) 33 (51) 10 (15)
Table 5: Efficacy measures in patients with treatment-naïve BPDCN treated with 12 mcg/kg of ELZONRIS
Parameter
Confirmatory cohort
N=13
Treatment-naive BPDCN N=65
Response rate
CR/CRc* Rate, N (%)
(95% CI)
Duration of CR/CRc (months)**
Median
Minimum, Maximum
7 (54)
(25.1, 80.8)
NE
4.7, 28.5
37 (57)
(44.0, 62.9)
7.3
0.7, 49.1
Overall response rate, N (%)
(95% CI)
10 (77)
(46.2, 95.0)
49 (75)
(63.1, 85.2) Bridge to stem cell transplant
Rate, N (%)
(95% CI)
6 (46)
(19.2, 74.9)
21 (32)
(21.2, 45.1)
Overall survival
Median
Minimum, Maximum
12-month survival, % (95% CI)
18-month survival, % (95% CI)
24-month survival, % (95% CI)
18.9 (5.2, NE) 0.2, 28.9
53.8 (24.8, 76.0) 53.8 (24.8, 76.0) 46.2 (19.2, 69.6)
12.3 (9.3, 35.9) 0.2, 49.7
52.2 (38.5, 64.2)
48.2 (34.6, 60.5)
40.9 (27.5, 53.9)
* CRc is defined as complete response with residual skin abnormality not indicative of active disease.
** Duration of CR/CRc includes patients bridged to stem cell transplantation.
Paediatric population
The Medicines & Healthcare Products Regulatory Agency (MHRA) has waived the obligation to submit the results of studies with ELZONRIS in all subsets of the paediatric population in BPDCN (see section 4.2 for information on paediatric use).
This medicinal product has been authorised under ‘exceptional circumstances’. This means that due to the rarity of the disease it has not been possible to obtain complete information on this medicinal product. The MHRA will review any new information which may become available every year and this SmPC will be updated as necessary.
5.2 Pharmacokinetic properties
The pharmacokinetics of tagraxofusp has been evaluated in 43 patients with BPDCN. Most patients (n=38) had pre-existing anti-drug antibodies (ADA) against the diphtheria toxin (DT) component, due to previous vaccination. Pre-existing ADAs resulted in higher clearance and lower tagraxofusp concentrations. During treatment, all patients developed high ADA titres, and substantially reduced free tagraxofusp levels (see below). All data referred to below are based on free tagraxofusp concentrations in BPDCN patients without pre-existing anti-drug antibodies (ADA, n=5) in the first treatment cycle. Descriptive information is included for BPDCN patients with pre-existing ADAs (n=38).
Distribution
Following administration of ELZONRIS 12 mcg/kg via 15-minute infusion in patients with BPDCN without pre-existing anti-drug antibodies (ADA, N=5), the mean (SD) unbound area under the plasma drug concentration over time curve (AUCunbound) of free tagraxofusp on Day 1 of the first cycle of treatment (C1D1) was 230 (123) hr*mcg/L and maximum unbound plasma concentration (Cmax) was 162 (58.1) mcg/L.
The mean (SD) volume of distribution of free tagraxofusp on C1D1 was 5.1 (1.9) L in 4 patients with BPDCN without pre-existing ADA.
Elimination
Tagraxofusp is expected to be degraded into peptides and its constituent amino acids through proteolysis, with no involvement of CYP or transporters.
The mean (SD) clearance of free tagraxofusp at C1D1 was 7.1 (7.2) L/hr in 4 patients with BPDCN without pre-existing ADA, and the mean (SD) terminal half-life of tagraxofusp was 0.7 (0.3) hours.
Anti- drug antibody formation affecting pharmacokinetics
Patients with pre-existing ADA had lower unbound tagraxofusp plasma concentrations (AUC and Cmax) at C1D1 than patients without pre-existing ADA. Due to the limitation of the bioanalytical method in the presence of ADA, quantitative pharmacokinetic parameters in these patients cannot be given.
Pharmacokinetic/pharmacodynamic relationship
Data collected during Cycle 3 showed increased titres of ADAs and substantially reduced free tagraxofusp concentrations. However, clinical efficacy has been demonstrated beyond Cycle 1 despite the reduced exposure. Due to the limitation of the bioanalytical method, the utility of free tagraxofusp concentrations as a predictor of response is limited.
Pharmacokinetics in special populations
Due to the limitation of the bioanalytical method, the pharmacokinetics of tagraxofusp in patients with renal or hepatic impairment and the effect of body weight, age, and gender are considered unknown.
Paediatric population
The pharmacokinetics of tagraxofusp have not been studied in the paediatric population.
5.3 Preclinical safety data
Carcinogenicity or genotoxicity studies have not been performed with tagraxofusp. Tagraxofusp is a recombinant protein and is therefore not expected to interact directly with DNA.
At human equivalent doses greater than or equal to 1.6 times the recommended dose based on body surface area, severe kidney tubular degeneration/necrosis was observed in cynomolgus monkeys. At human equivalent doses equal to the recommended dose, degeneration/necrosis of the choroid plexus in the brain was observed in cynomolgus monkeys. These findings were generally noted after 5 days of daily dosing. The reversibility of this finding was not assessed at lower doses, but the finding was irreversible and became progressively more severe at a human equivalent dose 1.6 times the recommended dose, 3 weeks after dosing stopped. These findings in kidney and choroid plexus are considered likely relevant for the clinical situation.
No fertility studies have been conducted with tagraxofusp. A literature-based risk assessment suggests that exposure to exogenous IL-3 or blockade of IL-3 signaling may have embryotoxic effects on foetal haematopoiesis and embryo-foetal development. The effects of diphtheria toxin exposure on placental and embryo-foetal development are unknown.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Trometamol
Sodium chloride
Sorbitol (E420)
Water for injections
6.2 Incompatibilities
This medicinal product must not be mixed with other medicinal products except those mentioned in section 6.6.
6.3 Shelf life
Unopened vial
3 years.
After opening
From a microbiological point of view, once opened, the medicinal product should be diluted and infused immediately.
After preparation of solution for infusion
Chemical and physical in-use stability has been demonstrated for 4 hours at 25 °C.
From a microbiological point of view, the product should be used immediately. If not used immediately, in-use storage times and conditions prior to use are the responsibility of the user.
6.4 Special precautions for storage
Store and transport frozen (-20 °C ±5 °C).
Do not refreeze after thawing.
Keep the vial in the outer carton in order to protect from light.
For storage conditions after dilution of the medicinal product, see section 6.3.
6.5 Nature and contents of container
Type I plus glass vial with a butyl rubber stopper and an aluminium/plastic flip-off seal, containing 1 mL concentrate.
Pack size of 1 vial.
6.6 Special precautions for disposal
General precautions
Preparation and administration
Preparing the infusion
Ensure the following components required for dose preparation and administration are available prior to thawing ELZONRIS:
- One infusion syringe pump
- One empty 10 mL sterile vial
- Sodium chloride 9 mg/mL (0.9%) solution for injection
- Three 10 mL sterile syringes
- One 1 mL sterile syringe
- One mini-bifuse Y-connector
- Microbore tubing
- One 0.2 µm low protein binding polyethersulfone in-line filter
Use only if the solution is clear and colourless or with a few white to translucent particles.
Allow vials to thaw at 25 °C or below for up to 1 hour in the outer carton. Do not refreeze a vial once thawed.
Determining dosage amount
Calculation to determine the total ELZONRIS dose (mL) to be administered (see section 4.2):
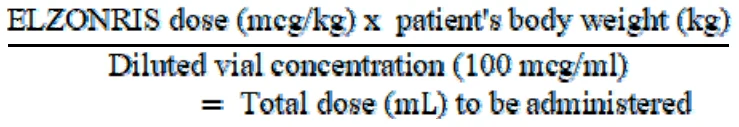
A 2-step process is required for preparation of the final ELZONRIS dose:
Step 1 -prepare 10 mL of 100 mcg/mL ELZONRIS
Using a sterile 10 mL syringe, transfer 9 mL of sodium chloride 9 mg/mL
(0.9%) solution for injection to an empty sterile 10 mL vial.
- Gently swirl the ELZONRIS vial to mix the contents, remove the cap, and using a sterile 1 mL syringe, withdraw 1 mL of thawed ELZONRIS from the product vial.
- Transfer the 1 mL of ELZONRIS into the 10 mL vial containing the 9 mL of sodium chloride 9 mg/mL (0.9%) solution for injection. Gently invert the vial at least 3 times to mix the contents. Do not shake vigorously.
- Following dilution the final concentration of ELZONRIS is 100 mcg/mL.
Step 2 – Prepare the ELZONRIS infusion set.
Calculate the required volume of diluted ELZONRIS (100 mcg/mL)
according to patient’s weight.
- Draw up the required volume into a new syringe (if more than 10 mL of diluted ELZONRIS (100 mcg/mL) is required for the calculated patient dose, repeat step 1 with a second vial of ELZONRIS). Label the ELZONRIS syringe.
Prepare a separate syringe with at least 3 mL of sodium chloride 9 mg/mL
(0.9%) solution for injection to be used to flush the administration set once the ELZONRIS dose is delivered.
- Label the sodium chloride 9 mg/mL (0.9%) solution for injection flush syringe.
- Connect the sodium chloride 9 mg/mL (0.9%) solution for injection flush syringe to one arm of the Y-connector and ensure the clamp is closed.
- Connect the product syringe to the other arm of the Y-connector and ensure the clamp is closed.
- Connect the terminal end of the Y-connector to the microbore tubing.
- Remove the cap from the supply side of the 0.2 µm filter and attach it to the terminal end of the microbore tubing.
Unclamp the arm of the Y-connector connected to the sodium chloride
9 mg/mL (0.9%) solution for injection flush syringe. Prime the Y-connector up to the intersection (do not prime the full infusion set with sodium chloride 9 mg/mL (0.9%) solution for injection). Re-clamp the Y-connector line on the sodium chloride 9 mg/mL (0.9%) solution for injection flush arm.
Remove the cap on the terminal end of the 0.2 µm filter and set it aside.
Unclamp the arm of the Y-connector connected to the product syringe, and prime the entire infusion set, including the filter. Recap the filter, and re-clamp the Y-connector line on the product side. The infusion set is now ready for delivery for dose administration.
The diluted solution should be used immediately once prepared.
Administration
- 1.
Establish venous access and maintain with sterile sodium chloride 9 mg/mL (0.9%)
solution for injection.
- 2. Administer the prepared ELZONRIS dose via infusion with an infusion syringe pump over 15 minutes. The total infusion time will be controlled using an infusion syringe pump to deliver the entire dose and the sodium chloride 9 mg/mL (0.9%) solution for injection flush over 15 minutes.
- 3.
Insert the ELZONRIS syringe into the infusion syringe pump, open the clamp on the
ELZONRIS side of the Y-connector and deliver the prepared ELZONRIS dose.
- 4. Once the ELZONRIS syringe has been emptied, remove it from the pump and place the sodium chloride 9 mg/mL (0.9%) solution for injection flush syringe in the infusion syringe pump.
- 5.
Open the clamp on the sodium chloride 9 mg/mL (0.9%) solution for injection flush side of the Y-connector and resume infusion via the infusion syringe pump at the pre-specified flow to push the remaining ELZONRIS dose out of the infusion line to complete delivery.
Disposal
ELZONRIS is for single use only.
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Stemline Therapeutics B.V.
Basisweg 10,
1043 AP Amsterdam
Netherlands
8 MARKETING AUTHORISATION NUMBER(S)
PLGB 53425/0001
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
15/10/2021
10 DATE OF REVISION OF THE TEXT
16/11/2022