


Summary of Product Characteristics (SmPC) - Co-cyprindiol 2000/35 coated tablets
1 NAME OF THE MEDICINAL PRODUCT
Co-Cyprindiol 2000/35 Coated Tablets
2. QUALITATIVE AND QUANTITATIVE COMPOSITION
Each tablet contains 2 milligrams cyproterone acetate and 35 micrograms of ethinylestradiol.
For excipients please see section 6.1
3. PHARMACEUTICAL FORM
Coated tablets.
Round, biconvex, yellow sugar-coated tablets with a 5.7mm nominal diameter.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Treatment of moderate to severe acne related to androgen-sensitivity (with or without seborrhoea) and/or hirsutism, in women of reproductive age. For the treatment of acne, Co - Cyprindiol should only be used after topical therapy or systemic antibiotic treatments have failed.
Since Co - Cyprindiol is also a hormonal contraceptive, it should not be used in combination with other hormonal contraceptives (see section 4.3).
4.2 Posology and method of administration
Method of Administration
Oral use
Dosage regimen
Co - Cyprindiol inhibits ovulation and thereby prevents conception. Patients who are using Co - Cyprindiol should not therefore use an additional hormonal contraceptive, as this will expose the patient to an excessive dose of hormones and is not necessary for effective contraception.
First treatment course:
One tablet daily for 21 days, starting on the first day of the menstrual cycle (the first day of menstruation counting as Day I).
Subsequent courses:
Each subsequent course is started 7 tablet-free days after the preceding course.
When the contraceptive action of Co - Cyprindiol is also to be employed, it is essential that the above instructions be rigidly adhered to. Should bleeding fail to occur during the tablet-free interval, the possibility of pregnancy must be excluded before the next pack is started.
When changing from an oral contraceptive and relying on the contraceptive action of Co Cyprindiol Coated Tablets, the instructions given below should be followed:
Changing from 21-day combined oral contraceptives:
The first tablet of Co - Cyprindiol should be taken on the first day immediately after the end of the previous oral contraceptive course. Additional contraceptive precautions are not required.
Changing from a combined Every Day Pill (28 day tablets):
The first Co - Cyprindiol tablet should be taken the day after taking the last active tablet from the Every Day Pill pack. Additional contraceptive precautions are not then required.
Changing from a progestogen-only pill (POP):
The first tablet of Co - Cyprindiol should be taken on the first day of bleeding, even if a POP has already been taken on that day. Additional contraceptive precautions are not then required. The remaining progestogen-only pills should be discarded.
Postpartum and post-abortum use:
After pregnancy, Co - Cyprindiol can be started 21 days after a vaginal delivery, provided the patient is fully ambulant and there are no puerperal complications. Additional contraceptive precautions will be required for the first 7 days of pill taking. Since the first postpartum ovulation may precede the first bleeding, another method of contraception should be used in the interval between childbirth and the first course of tablets.
After a first-trimester abortion, Co - Cyprindiol may be started immediately and no additional contraceptive precautions are required.
Duration of Use:
Time to relieve of symptoms is at least three months. The need to continue treatment should be evaluated periodically by the treating physician.
Special circumstances requiring additional contraception
Incorrect administration:
A single delayed tablet should be taken as soon as possible, and if this is within 12 hours of the correct time, contraceptive protection is maintained. With longer delays, additional contraception is needed. Only the most recently delayed tablet should be taken, earlier missed tablets being omitted. Additional non-hormonal methods of contraception (except the rhythm or temperature methods) should be used for the next 7 days, while the next 7 tablets are being taken. Also, if tablet(s) have been missed during the last 7 days of a pack, there should be no break before the next pack is started. In this situation, a withdrawal bleed should not be expected until the end of the second pack. Some breakthrough bleeding may occur on tablet taking days but this is not clinically significant. If the patient does not have a withdrawal bleed during the tablet- free interval following the end of the second pack, the possibility of pregnancy must be ruled out before starting the next pack.
Gastrointestinal upset:
Vomiting or diarrhoea may reduce the efficacy of oral contraceptives by preventing full absorption. Tablet taking from the current pack should be continued and additional non hormonal methods of contraception (except the rhythm or temperature methods) should be used during the gastrointestinal upset, and for 7 days following the upset. If these 7 days overrun the end of a pack, the next pack should be started without a break. In this situation, a withdrawal bleed should not be expected until the end of the second pack. If the patient does not have a withdrawal bleed during this period the possibility of pregnancy must be filled out before starting the next pack. Other methods of contraception should be considered if the gastrointestinal disorder is likely to be prolonged.
| Additional information on special populations | |
| Children and adolescents | |
| Co - Cyprindiol is only indicated after menarche. | |
| Geriatric patients | |
| Not applicable. Co - Cyprindiol is not indicated after menopause. | |
| Patients with hepatic impairment | |
| Co - Cyprindiol is contraindicated in women with severe hepatic disease as long as | |
| liver function values have not returned to normal. See also section 4.3. | |
| Patients with renal impairment | |
| Co - Cyprindiol has not been specifically studied in renally impaired patients. | |
| Available data do not suggest a change in treatment in this patient population. | |
4.3 Contraindications
| Preparations containing oestrogen/progestogen combinations should not be used in | ||
| the presence of any of the conditions listed below. Should any of the conditions | ||
| appear for the first time during their use, the product should be stopped immediately. | ||
- Concomitant use with another hormonal contraceptive (see section 4.1)
- Venous thrombosis present or in history (deep venous thrombosis, pulmonary embolism)
- Arterial thrombosis present or in history (e.g. myocardial infarction) or prodromal conditions (e.g. angina pectoris and transient ischaemic attack).
- Presence or history of cerebrovascular accident
- The presence of a severe or multiple risk factor(s) for venous or arterial thrombosis (see section 4.4) such as:
- diabetes mellitus with vascular symptoms
- severe hypertension
- severe dyslipoproteinaemia
- Hereditary or acquired predisposition for venous or arterial thrombosis, such as activated protein C (APC) resistance, antithrombin-III-deficiency, protein C deficiency, protein S deficiency, hyperhomocysteinaemia and antiphospholipid-antibodies (anticardiolipin-antibodies, lupus anticoagulant)
- History of migraine with focal neurological symptoms
•
| Presence or history of severe hepatic disease e.g. active viral hepatitis and | |||
| severe cirrhosis, as long as liver function values have not returned to normal. | |||
•
| Presence or history of liver tumours (benign or malignant). |
•
| Current or history of breast cancer |
- Meningioma or history of meningioma
- Pregnancy or lactation (see section 4.6)
- Hypersensitivity to any of the components of Co - Cyprindiol Coated Tablets.
Co - Cyprindiol is contraindicated for concomitant use with the medicinal products containing ombitasvir / paritaprevir / ritonavir and dasabuvir, medicinal products containing glecaprevir / pibrentasvir or sofosbuvir / velpatasvir / voxilaprevir (see section 4.5).
Relevant UK clinical guidance on COCs should also be consulted.
Co - Cyprindiol is not for use in men.
4.4 Special warnings and precautions for use
Medical Examination
Assessment of women prior to starting oral contraceptives (and at regular intervals thereafter) should include a personal and family medical history of each woman. Physical examination should be guided by this and by the contraindications (section 4.3) and warnings (section 4.4) for this product. The frequency and nature of these assessments should be based upon relevant guidelines and should be adapted to the individual woman, but should include measurement of blood pressure and, if judged appropriate by the clinician, breast, abdominal and pelvic examination including cervical cytology.
Exclude the likelihood of pregnancy before starting treatment.
Undiagnosed vaginal bleeding that is suspicious for underlying conditions should be investigated.
Warnings:
Co - Cyprindiol is composed of the progestogen cyproterone acetate and the oestrogen ethinylestradiol and is administered for 21 days of a monthly cycle. It has a similar composition to that of a combined oral contraceptive (COC).
Duration of Use
Time to relief of symptoms is at least three months. The need to continue treatment should be evaluated periodically by the treating physician (see section 4.2).
| Women should be advised that |
Co - Cyprindiol does not protect against HIV
| infections (AIDS) and other sexually transmitted diseases. |
Conditions which require strict medical supervision
If any of the conditions/risk factors mentioned below is present, the benefits of the use of Co - Cyprindiol should be weighed against the possible risks for each individual woman and discussed with the woman before she decides to start using Co
Cyprindiol. In the event of aggravation, exacerbation or first appearance of any of these conditions or risk factors, the woman should contact her physician. The physician should then decide on whether the use of Co - Cyprindiol should be discontinued.
- Diabetes mellitus, with mild vascular disease or mild nephropathy, retinopathy or neuropathy
- Hypertension that is adequately controlled, i.e. systolic >140 to159 mm Hg or diastolic > 90 to 94mmHg (see also Section 4.4 'Reasons for stopping Co - Cyprindiol immediately'
- porphyria
- clinical depression
- obesity
- migraine
- cardiovascular diseases
- chloasma
Patients with a history of depression or any condition mentioned above should be monitored during treatment with Co - Cyprindiol.
Depressed mood and depression are well-known undesirable effects of hormonal contraceptive use (see section 4.8). Depression can be serious and is a well-known risk factor for suicidal behaviour and suicide. Women should be advised to contact their physician in case of mood changes and depressive symptoms, including shortly after initiating the treatment.
Reasons for stopping Co - Cyprindiol immediately:
| When stopping oral contraception non-hormonal contraception should be used to | |
| ensure contraceptive protection is maintained, if needed. | |
- 1. Occurrence for the first time, or exacerbation of migraines, headaches or unusually frequent or severe headaches
- 2. Sudden disturbances of vision or hearing or other perceptual disorders.
- 3. First signs of thrombophlebitis or thromboembolic symptoms (e.g. unusual pains in or
swelling of the leg(s), stabbing pains on breathing or coughing for no apparent reason). Pain and tightness in the chest.
- 4. At least four weeks before an elective major operation (e.g. abdominal, orthopaedic), any surgery to the legs, medical treatment for varicose veins or prolonged immobilisation, e.g. after accidents or surgery. Co - Cyprindiol should not be restarted until 2 weeks after full ambulation. In case of emergency surgery, thrombotic prophylaxis is usually indicated e.g. subcutaneous heparin.
- 5. Onset of jaundice, hepatitis or itching of the whole body.
- 6. Significant rise in blood pressure.
- 7. Onset of severe depression.
- 8. Severe upper abdominal pain or liver enlargement.
- 9. Clear exacerbation of conditions known to be capable of deteriorating during oral contraception or pregnancy (see section 4.4 'Conditions which deteriorate in pregnancy or during previous COC use' under 'Other conditions'.
- 10. Pregnancy is a reason for stopping immediately (see section 4.6)
Circulatory disorders
The use of Co-Cyprindiol carries an increased risk of venous thromboembolism (VTE) compared with no use. The excess risk of VTE is highest during the first year a woman starts Co-Cyprindiol or when restarting or switching after a pill-free interval of at least a month. Venous thromboembolism can be fatal in 1-2% of cases.
Epidemiological studies have shown that the incidence of VTE is 1.5 to 2 times higher in users of Co-Cyprindiol than in users of levonorgestrel-containing combined oral contraceptives (COCs) and may be similar to the risk for desogestrel / gestodene / drospirenone-containing COCs.
The user group of Co-Cyprindiol is likely to include patients that may have an inherently increased cardiovascular risk such as that associated with polycystic ovarian syndrome.
Epidemiological studies have also associated the use of hormonal contraceptive with an increased risk for arterial (myocardial infarction, transient ischaemic attack) thromboembolism.
Extremely rarely, thrombosis has been reported to occur in other blood vessels, e.g. hepatic, mesenteric, renal, cerebral or retinal veins and arteries, in hormonal contraceptive users.
Symptoms of venous or arterial thrombosis or of a cerebrovascular accident can include: unusual unilateral leg pain and / or swelling; sudden severe pain in the chest, whether or not it radiates to the left arm; sudden breathlessness; sudden onset of coughing; any unusual, severe, prolonged headache; sudden partial or complete loss of vision; diplopia; slurred speech or aphasia; vertigo; collapse with or without focal seizure; weakness or very marked numbness suddenly affecting one side or one part of the body; motor disturbances; ‘acute’ abdomen
The risk of venous thromboembolic events increases with:
- increasing age;
- smoking (with heavier smoking and increasing age the risk further increases, especially in women over 35 years of age. Women over 35 years of age should be strongly advised not to smoke if they wish to use Co-Cyprindiol);
- a positive family history (i.e. venous thromboembolism ever in a sibling or parent at a relatively early age). If a hereditary predisposition is suspected, the woman should be referred to a specialist for advice before deciding about any hormonal contraceptive use;
- prolonged immobilisation, major surgery, any surgery to the legs, or major trauma. In these situations it is advisable to discontinue use (in the case of elective surgery at least four weeks in advance) and not to resume until two weeks after complete remobilisation. Antithrombotic treatment should be considered if the use of Co-Cyprindiol has not been discontinued in advance.
- obesity (body mass index over 30 kg/m2).
There is no consensus about the possible role of varicose veins and superficial thrombophlebitis in venous thromboembolism.
The risk of arterial thromboembolic complications or of a cerebrovascular accident increases with:
- increasing age;
- smoking (with heavier smoking and increasing age the risk further increases, especially in women over 35 years of age. Women over 35 years of age should be strongly advised
not to smoke if they wish to use Co-Cyprindiol);
- dyslipoproteinemia;
- obesity (body mass index over 30 kg/m2);
- hypertension;
- migraine;
- valvular heart disease;
- atrial fibrillation;
- a positive family history (arterial thrombosis ever in a sibling or parent at a relatively early age). If a hereditary predisposition is suspected, the woman should be referred to a specialist for advice before deciding about any hormonal contraceptive use.
Other medical conditions, which have been associated with adverse circulatory events, include diabetes mellitus, systemic lupus erythematosus, hemolytic uraemic syndrome, chronic inflammatory bowel disease (e.g. Crohn's disease or ulcerative colitis) and sickle cell disease.
The increased risk of thromboembolism in the puerperium must be considered (for information on ‘Pregnancy and lactation’ see section 4.6).
An increase in frequency or severity of migraine during use of Co-Cyprindiol (which may be prodromal of a cerebrovascular event) may be a reason for immediate discontinuation of Co-Cyprindiol.
Women using Co-Cyprindiol should be specifically pointed out to contact their physician in case of possible symptoms of thrombosis. In case of suspected or confirmed thrombosis, Co-Cyprindiol use should be discontinued. Adequate contraception should be initiated because of the teratogenicity of anti-coagulant therapy (coumarins).
- Other factors affecting circulatory events
The user group of Co-Cyprindiol as a treatment for acne or moderately severe hirsutism is likely to include patients that may have an inherently increased cardiovascular risk such as that associated with polycystic ovarian syndrome. Biochemical factors that may be indicative of hereditary or acquired predisposition for venous or arterial thrombosis include Activated Protein C (APC) resistance, hyperhomocysteinaemia, antithrombin-III deficiency, protein C deficiency, protein S deficiency, antiphospholipid antibodies (anticardiolipin antibodies, lupus anticoagulant)
When considering risk/benefit, the physician should take into account that adequate treatment of a condition may reduce the associated risk of thrombosis and that the risk associated with pregnancy is higher than that associated with COC or Co-Cyprindiol use.
Tumours
Like many other steroids, Co-Cyprindiol, when given in very high doses and for the majority of the animal's life-span, has been found to cause an increase in the incidence of tumours, including carcinoma, in the liver of rats. The relevance of this finding to humans is unknown.
Numerous epidemiological studies have been reported on the risks of ovarian, endometrial, cervical and breast cancer in women using combined oral contraceptives. The evidence is clear that high dose combined oral contraceptives offer substantial protection against both ovarian and endometrial cancer. However, it is not clear whether low dose COCs or Co-Cyprindiol confer protective effects to the same level.
- Breast cancer
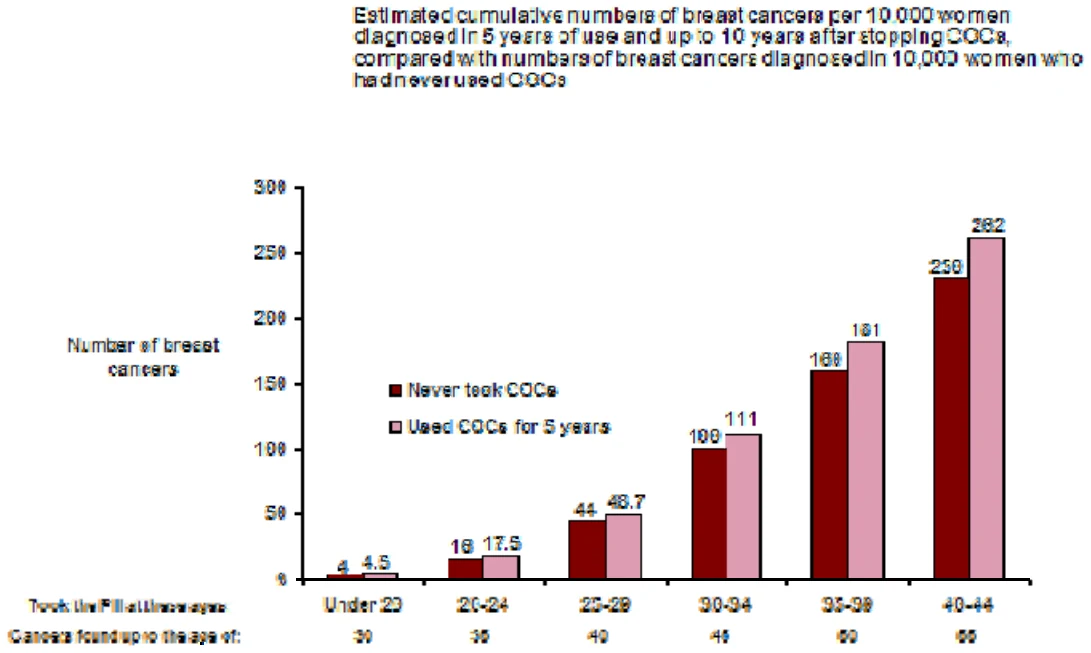
A meta-analysis from 54 epidemiological studies reported that there is a slightly increased relative risk (RR = 1.24) of having breast cancer diagnosed in women who are currently using combined oral contraceptives (COCs). The observed pattern of increased risk may be due to an earlier diagnosis of breast cancer in COC users, the biological effects of COCs or a combination of both. The additional breast cancers diagnosed in current users of COCs or in women who have used COCs in the last ten years are more likely to be localised to the breast than those in women who never used COCs.
Breast cancer is rare among women under 40 years of age whether or not they take COCs. Whilst this background risk increases with age, the excess number of breast cancer diagnoses in current and recent COC users is small in relation to the overall risk of breast cancer (see bar chart).
The most important risk factor for breast cancer in COC users is the age women discontinue the COC; the older the age at stopping, the more breast cancers are diagnosed. Duration of use is less important and the excess risk gradually disappears during the course of the 10 years after stopping COC use such that by 10 years there appears to be no excess.
The possible increase in risk of breast cancer should be discussed with the user and weighed against the benefits of COCs taking into account the evidence that they offer substantial protection against the risk of developing certain other cancers (e.g. ovarian and endometrial cancer).
- Cervical Cancer
The most important risk factor for cervical cancer is persistent HPV infection. Some epidemiological studies have indicated that long-term use of COCs may further contribute to this increased risk but there continues to be controversy about the extent to which this finding is attributable to confounding effects, e.g., cervical screening and sexual behaviour including use of barrier contraceptives.
- Liver Cancer
In rare cases benign and in even rarer cases malignant liver tumours leading in isolated cases to life-threatening intra-abdominal haemorrhage have been observed after the use of hormonal substances such as those contained in Co-Cyprindiol. If severe upper abdominal complaints, liver enlargement or signs of intra-abdominal haemorrhage occur, a liver tumour should be included in the differential diagnosis.
- Meningioma
The occurrence of meningiomas (single and multiple) has been reported in association with use of cyproterone acetate, especially at high doses of 25mg and above and for prolonged time (see section 5.1). If a patient is diagnosed with meningioma, any cyproterone containing treatment, including Co-Cyprindiol, must be stopped, as a precautionary measure.
Other conditions
The possibility cannot be ruled out that certain chronic diseases may occasionally deteriorate during the use of Co-Cyprindiol.
- Known hyperlipidaemias
Women with hypertriglyceridemia, or a family history thereof, may be at an increased risk of pancreatitis when using COCs or Co-Cyprindiol.
Women with hyperlipidaemias are at an increased risk of arterial disease (see section 4.4 'Circulatory disorders'). However routine screening of women on COCs or Co-Cyprindiol is not appropriate.
- Blood pressure
Hypertension is a risk factor for stroke and myocardial infarction (see section 4.4 'Arterial thromboembolic-related conditions'). Although small increases in blood pressure have been reported in many women taking COCs or oestrogen/progestogen combinations like Co-Cyprindiol, clinically relevant increases are rare. However, if sustained hypertension develops during the use of Co-Cyprindiol, antihypertensive treatment should normally be instigated at a level of 160/100 mm Hg in uncomplicated patients or at 140/90 mm Hg in those with target organ damage, established cardiovascular disease, diabetes or with increased cardiovascular risk factors. Decisions about the continued use of Co-Cyprindiol, should be made at lower BP levels, and alternative contraception may be advised.
- Conditions which deteriorate with pregnancy or during previous COC or Co-Cyprindiol use:
The following conditions have been reported to occur or deteriorate with both pregnancy and use of a COC or oestrogen/progestogen combinations like Co-Cyprindiol. Consideration should be given to stopping Co-Cyprindiol if any of the following occur during use:
- jaundice and/or pruritus related to cholestasis
- COCs or Co-Cyprindiol may increase the risk of gallstone formation and may worsen existing disease
- systemic lupus erythematosus
- herpes gestationis
- otosclerosis-related hearing loss
- sickle cell anaemia
- renal dysfunction
- hereditary angioedema
- epilepsy
- any other condition an individual woman has experienced worsening of during pregnancy or previous use of COCs or Co-Cyprindiol.
- Angioedema
Exogenous oestrogens may induce or exacerbate symptoms of hereditary and acquired angioedema.
|
| Acute or chronic disturbances of liver function may necessitate the discontinuation of |
| COC or Co-Cyprindiol use until markers of liver function return to normal. |
|
| Insulin-dependent diabetics without vascular disease can use Co-Cyprindiol. |
| However it should be remembered that all diabetics are at an increased risk of arterial |
| disease and this should be considered when prescribing COCs or Co-Cyprindiol. |
| Diabetics with existing vascular disease are contraindicated from using Co- |
| Cyprindiol (see section 4.3 Contraindications). |
| Although COCs or oestrogen/progestogen combinations like Co-Cyprindiol may have |
| an effect on peripheral insulin resistance and glucose tolerance, there is no evidence |
| for a need to alter the therapeutic regimen in diabetics using low-dose COCs |
| (containing < 0.05 mg ethinylestradiol). However, diabetic women should be |
| carefully observed while taking COCs or Co-Cyprindiol. |
|
| Chloasma may occasionally occur, especially in women with a history of chloasma |
| gravidarum. Women with a tendency to chloasma should avoid exposure to the sun or |
| ultraviolet radiation whilst taking Co – Cyprindiol |
|
| Reduction of menstrual flow: This is not abnormal and it is to be expected in some |
| patients. Indeed, it may be beneficial where heavy periods were previously |
| experienced. |
| Missed menstruation: Occasionally, withdrawal bleeding may not occur at all. If the |
| tablets have been taken correctly, pregnancy is unlikely. Should bleeding fail to occur |
| during the tablet-free interval the possibility of pregnancy must be excluded before |
| the next pack is started. |
| Intermenstrual bleeding: Irregular bleeding (spotting or breakthrough bleeding) may |
| occur especially during the first months of use. Therefore, the evaluation of any |
| irregular bleeding is only meaningful after an adaptation interval of about three |
| cycles. If bleeding irregularities persist or occur after previously regular cycles, then |
| non-hormonal causes should be considered and adequate diagnostic measures are |
| indicated to exclude malignancy or pregnancy. This may include curettage. |
| Some women may experience amenorrhoea or oligomenorrhoea after discontinuation |
| of Co-Cyprindiol, especially when these conditions existed prior to use. Women |
| should be informed of this possibility. |
|
| Each tablet of this medicinal product contains 30.965 mg lactose and 19.371 mg |
| sucrose per tablet. Patients with rare hereditary problems of galactose intolerance, |
| total lactase deficiency, fructose intolerance or glucose-galactose malabsorption or |
| sucrase-isomaltase should not take this medicine. |
4.5 Interaction with other medicinal products and other forms of interaction
Note: The prescribing information of concomitant medications should be consulted to identify potential interactions.
Enzyme inducers
Interactions can occur with drugs that induce microsomal enzymes (especially cytochrome P450 3A4) which can result in increased clearance of sex hormones and which may lead to breakthrough bleeding and/or contraceptive failure.
Enzyme induction can already be observed after a few days of treatment. Maximal enzyme induction is generally seen within a few weeks. After the cessation of drug therapy enzyme induction may be sustained for about 4 weeks.
Women receiving short courses of enzyme inducers and broad spectrum antibiotics should take additional, non-hormonal (except rhythm or temperature method) contraceptive precautions during the time of concurrent medication and for 7 days afterwards. If these 7 days over run the end of a pack, the next pack should he started without a break. In this situation, a withdrawal bleed should not be expected until the end of the second pack. If the patient does not have a withdrawal bleed during the tablet-free interval following the end of the second pack, the possibility of pregnancy must be ruled out before resuming with the next pack.
For women receiving long-term therapy with enzyme inducers, another method of contraception should be used.
The following have been shown to have clinically important interactions with Co-Cyprindiol:
Anticonvulsants: barbiturates (including phenobarbitone), primidone, phenytoin, carbamazepine, oxcarbazepine, topiramate.
Antibiotics/antifungals: griseofulvin, rifampicin.
Herbal remedies: St John's wort (Hypericum perforatum).
Antiretroviral agents:ritonavir, nelfinavir, nevirapine.
Note: There are other antiretroviral agents that may increase plasma concentration of sex hormones.
Substances decreasing the clearance of CHC (enzyme inhibitors)
The clinical relevance of potential interactions with enzyme inhibitors remains unknown.
Concomitant administration of strong CYP3A4 inhibitors can increase plasma concentrations of the oestrogen or the progestin or both.
Etoricoxib doses of 60 to 120 mg/day have been shown to increase plasma concentrations of ethinylestradiol 1.4 to 1.6-fold, respectively when taken concomitantly with a combined hormonal contraceptive containing 0.035 mg ethinylestradiol.
Effects of oestrogen/progestogen combinations on other medicinal products
Oral contraceptives and oestrogen/progestogen combinations like Co-Cyprindiol may affect the metabolism of certain other drugs. Accordingly, plasma and tissue concentrations may either increase (e.g. cyclosporin) or decrease (e.g. lamotrigine).
Pharmacodynamic interactions
During clinical trials with patients treated for hepatitis C virus infections (HCV) with the medicinal products containing ombitasvir / paritaprevir / ritonavir and dasabuvir with or without ribavirin, transaminase (ALT) elevations higher than 5 times the upper limit of normal (ULN) occurred significantly more frequently in women using ethinylestradiol-containing medications such as combined hormonal contraceptives (CHCs). Additionally, also in patients treated with glecaprevir/pibrentasvir or sofosbuvir / velpatasvir / voxilaprevir, ALT elevations were observed in women using ethinylestradiol-containing medications such as CHCs (see section 4.3).
Therefore, Co-Cyprindiol -users must switch to an alternative method of contraception (e.g., progestagen-only contraception or non-hormonal methods) prior to starting therapy with these combination drug regimens. Co-Cyprindiol can be restarted 2 weeks following completion of treatment with these combination drug regimens.
Clinical data suggest that ethinylestradiol is inhibiting the clearance of CYP1A2 substrates leading to a weak (e.g. theophylline) or moderate (e.g. tizanidine) increase in their plasma concentration.
Other forms of interactions
Laboratory tests
The use of oral contraceptives may influence the results of certain laboratory tests including biochemical parameters of liver, thyroid, adrenal and renal function, plasma levels of carrier proteins and lipid/lipoprotein fractions, parameters of carbohydrate metabolism and parameters of coagulation and fibrinolysis. Laboratory staff should therefore be informed about oral contraceptive use when laboratory tests are requested.
4.6 Fertility, pregnancy and lactation
Pregnancy is an absolute contraindication for treatment with Co - Cyprindiol and must be excluded before such treatment is begun. If pregnancy occurs during treatment with Co - Cyprindiol, further intake must be stopped.
Animal studies have revealed that feminisation of male foetuses may occur if cyproterone acetate is administered during the phase of embryogenesis when differentiation of the external genitalia occurs. Although these findings are not necessarily relevant to man,
| the possibility must be considered that administration of |
Co - Cyprindiol
| to women after the 45th day of pregnancy could cause feminisation | |
| of male foetuse | |
s . It follows from this that pregnancy is an absolute contraindication for treatment with Co - Cyprindiol Coated Tablets, and must be excluded before treatment is begun.
| The use of |
Co - Cyprindiol during lactation may lead to a reduction in the volume of
| milk produced and to a change in its composition. Minute amounts of the active | ||||||
| substances are excreted with the milk. These amounts may affect the child | ||||||
| particularly in the first 6 weeks post-partum. Mothers who are breast-feeding should | ||||||
| be advised not to take | ||||||
Co - Cyprindiol
| until the nursing mother has weaned her child | |||||
| off breast milk. | |||||
4.7 Effects on ability to drive and use machines
None known.
4.8 Undesirable effects
Summary of safety profile
The most commonly reported adverse reactions with Co - Cyprindiol are nausea, abdominal pain, increased weight, headache, depressed mood, altered mood, breast pain, breast tenderness. They occur in ≥ 1 % of users.
There is an increased risk of thromboembolism for all women who use Co - Cyprindiol (see section 4.4).
Tabulated list of adverse events
System Organ Class | Adverse events reported in clinical trials | Adverse events reported post marketing | ||
Common (≥ 1/100 to <1/10) | Uncommon (≥ 1/1000 to <1/100) | Rare (≥1/10,000 to < 1/1000) | ||
| Eye disorders | contact lens intolerance | |||
| Gastrointestinal disorders | nausea, abdominal pain | vomiting, diarrhea | ||
| Immune system disorders | hypersensitivity | exacerbation of symptoms of hereditary and acquired angioedema | ||
| Investigations | weight increased | weight decreased | ||
Metabolism and nutrition disorders | fluid retention | hypertriglyceridem ia | ||
| Nervous system disorders | headache | migraine | exacerbation of chorea | |
| Gastrointestinal disorders | Crohn's disease, ulcerative colitis | |||
| Hepatobiliary disorders | liver function disturbances | |||
| Psychiatric disorders | depressed mood, mood altered | libido decreased | libido increased | |
Reproductive system and breast disorders | breast pain, breast tenderness | breast hypertrophy | vaginal discharge, breast discharge | reduced menstrual flow, spotting, breakthrough bleeding and missed withdrawal bleeding, post pill amenorrhoea |
Skin and subcutaneous tissue disorders | rash, urticaria | erythema nodosum, erythema multiforme | chloasma | |
| Vascular Disorders | Thromboembolism | increase in blood pressure | ||
Description of selected adverse reactions
Post-marketing reports of severe depression (including very rare reports of suicidal ideation or behaviour) in patients using Co - Cyprindiol have been received. However, a causal relationship between clinical depression and Co - Cyprindiol has not been established.
An increased risk of arterial and venous thrombotic and thrombo-embolic events, including myocardial infarction, stroke, transient ischemic attacks, venous thrombosis and pulmonary embolism has been observed in women using CHCs, which are discussed in more detail in section 4.4.
The following serious adverse events have been reported in women using Co - Cyprindiol, which are discussed in section 4.4 Special warning and precautions for use:
- Venous thromboembolic disorders
- Arterial thromboembolic disorders
- Hypertension;
- Liver tumours;
- Occurrence or deterioration of conditions for which association with COC use is not conclusive: Crohn's disease, ulcerative colitis, epilepsy, uterine myoma, porphyria, systemic lupus erythematosus, herpes gestationis, Sydenham's chorea, haemolytic uremic syndrome, cholestatic jaundice;
- Chloasma;
- Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal. The frequency of diagnosis of breast cancer is very slightly increased among COC users. As breast cancer is rare in women under 40 years of age the excess number is small in relation to the overall risk of breast cancer. Causation with COC use is unknown. For further information, see sections 4.3 and 4.4.
Interactions
Breakthrough bleeding and/or contraceptive failure may result from interactions of other drugs (enzyme inducers) with oral contraceptives (see section 4.5).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Overdose may cause nausea, vomiting and, in females, withdrawal bleeding.
| Withdrawal bleeding may even occur in girls before their menarche, if they | |
| accidentally take the medicinal product. | |
There arc no specific antidotes and further treatment should be symptomatic.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
| Pharmacotherapeutic group: Sex hormones and modulators of the genital system, | |
| antiandrogens and oestrogens. | |
ATC code: G03HBOI
Co - Cyprindiol blocks androgen-receptors. It also reduces androgen synthesis both by a negative feedback effect on the hypothalamo-pituitiary-ovarian systems and by the inhibition of androgen-synthesising enzymes.
Although Co - Cyprindiol also acts as an oral contraceptive, it is not recommended in women solely for contraception, but should be reserved for those women requiring treatment for the androgen-dependent skin conditions described.
Meningioma
Based on results from a French epidemiological cohort study, a cumulative dose-dependent association between cyproterone acetate and meningioma has been observed. This study was based on data from the French Health insurance (CNAM) and included a population of 253,777 women using 50 - 100 mg cyproterone tablets. The incidence of meningioma treated with surgery or radiotherapy was compared between women exposed to high-dose cyproterone acetate (cumulative dose ≥3 g) and women who were slightly exposed to cyproterone acetate (cumulative dose <3 g). A cumulative dose-response relationship was demonstrated.
Cumulative dose of cyproterone acetate | Incidence rate (in patient- years) | HRadj (95% CI) a |
| Slightly exposed (<3 g) | 4.5/100,000 | Ref. |
| Exposed to ≥3 g | 23.8/100,000 | 6.6 [4.0-11.1] |
| 12 to 36 g | 26/100,000 | 6.4 [3.6-11.5] |
| 36 to 60g | 54.4/100,000 | 11.3 [5.8-22.2] |
| more than 60 g | 129.1/100,000 | 21.7 [10.8-43.5] |
a Adjusted based on age as a time-dependent variable and oestrogen at inclusion
A cumulative dose of 12g for example can correspond with one year of treatment with 50 mg/day for 20 days each month.
5.2 Pharmacokinetic properties
Cyproterone acetate:
Following oral administration cyproterone acetate is completely absorbed over a wide dose range. The ingestion of 2mg cyproterone in combination with 0.035mg of ethinylestradiol gave a maximum serum level of 15ng cyproterone acetate/ml at 1.6 hours. Thereafter drug serum levels decrease in two disposition phases characterised by half-lives of 0.8 hours and 2.3 days. The total clearance of cyproterone acetate from serum was determined to be 3.6 ml/min/kg. Cyproterone acetate is metabolised by varions pathways including hydroxylations and conjugations. The main metabolite in human plasma is the 15β-hydroxy derivative.
Some of the dose was excreted unchanged with the bile fluid. Most is excreted in the form of metabolites at a urinary to biliary ratio of 3:7. The renal and biliary excretion was determined to proceed with half-life of 1.9 days. Metabolites from plasma were eliminated at a similar rate (half-life of 1.7 days). Cyproterone acetate is almost exclusively bound to plasma albumin only about 3.5 - 4.0% of total drug levels are present unbound. Because protein binding is nonspecific, changes in sex hormone binding globulin (SHBG) levels do not affect cyproterone acetate pharmacokinetics.
According to the long half-life of the terminal disposition phase from plasma (serum) and the daily intake, cyproterone acetate accumulates during one treatment cycle. Mean maximum drug serum levels increased from 15ng/ml (day I) to 21ng/ml and 24ng/ml at the end of the treatment cycles I and 3 respectively. The area under the concentration versus time profile increased 2.2 fold (end of cycle I) and 2.4 fold (end of cycle 3). Steady state conditions were reached after about 16 days. During long term treatment cyproterone acetate accumulates over treatment cycles by a factor of
2.
The absolute bioavailability of cyproterone acetate is almost complete (88% of dose). The relative bioavailability of cyproterone acetate (in combination with 0.035mg of ethinylestradiol) was 109% when compared to an aqueous microcrystalline suspension.
Ethinylestradiol:
Orally administered ethinylestradiol is rapidly and completely absorbed. Following ingestion of 0.035mg of ethinylestradiol in combination with 2mg of cyproterone, maximum drug serum levels of about 80pg/ml are reached at 1.7 hours. Thereafter ethinylestradiol plasma levels decrease in two phases characterised by half-lives of 1 - 2 hours and about 20 hours. For analytical reasons these parameters can only be calculated for higher dosages.
For ethinylestradiol an apparent volume of distribution of about 5 l/kg and a metabolic clearance rate from plasma of about 5 ml/min/kg were determined.
Ethinylestradiol is highly, but non-specifically bound to serum albumin only 2% of the drug levels are present unbound. During absorption and first liver passage ethinylestradiol is metabolised resulting in a reduced absolute and variable oral bioavailability. Unchanged drug is not excreted. Ethinylestradiol metabolites are excreted at a urinary to biliary ratio of 4:6 with a half-life of about I day.
According to the half-life of the terminal disposition phase from plasma and the daily ingestion, steady state plasma levels are reached after 3 - 4 days and are higher by 30
- 40% as compared to a single dose. The relative bioavailability (reference: aqueous microcrystalline suspension) of ethinylestradiol was almost complete.
The systemic bioavailability of ethinylestradiol might be influenced in both directions by other drugs. There is, however, no interaction with high doses of vitamin C.
Ethinylestradiol induces the hepatic synthesis of SHBG and corticosteroid binding globulin (CBC) during continuous use. The extent of SHBG induction, however, is
| dependent upon the chemical structure and dose of the co-administered progestin. | |||||
| During treatment with | Co - Cyprindiol | SHBG concentrations in serum increased from | |||
| about 100nmol/l to 300nmol/l and the serum concentrations of CBG were increased | |||||
| from about 50μg/ml to 95μg/ml. | |||||
| In vitro, ethinylestradiol is a reversible inhibitor of CYP2C19, CYP1A1 and CYP1A2 | |
| as well as a mechanism based inhibitor of CYP3A4/5, CYP2C8 and CYP2J2. | |
5.3 Preclinical safety data
There are no preclinical safety data which could be of relevance to the prescriber and which are not already included in other relevant sections of the SPC.
6. PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Lactose monohydrate, maize starch, povidone K25, talcum, magnesium stearate, sucrose, calcium carbonate, polyethylene glycol 6000, Povidone K90 titanium dioxide (E 171), glycerol 85%, montan glycol wax, iron oxide pigment.
6.2 Incompatibilities
Not applicable
6.3 Shelf life
36 months
6.4 Special precautions for storage
Store in the original package
6.5 Nature and contents of container
PVC blister (250µm) and aluminium foil (20µm) packs or PVC/PVDC blister (40 gsm) and aluminium foil (20µm) each containing 21 tablets. Each carton contains either 1 or 3 blister strips.
6.6. Instructions for use and handling
Keep out of sight and reach of children.
7 MARKETING AUTHORISATION HOLDER
Strandhaven Limited
T/A Somex Pharma
High Road
Ilford Essex
IG3 8BS
United Kingdom
8. MARKETING AUTHORISATION NUMBER
PL 15764/0011
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
28/08/2025
10 DATE OF REVISION OF THE TEXT
21/04/2026