

Summary of Product Characteristics (SmPC) - Camcevi 21 mg prolonged-release suspension for injection
1 NAME OF THE MEDICINAL PRODUCT
CAMCEVI® 21mg prolonged-release suspension for injection
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each pre-filled syringe with prolonged-release suspension for injection contains leuprorelin mesilate equivalent to 21mg leuprorelin (in about 0.25 mL deliverable volume).
For the full list of excipients, see section 6.1.
3 PHARMACEUTICAL FORM
Prolonged-release suspension for injection.
Pre-filled syringe with off-white to pale yellow viscous and opalescent suspension.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
CAMCEVI is indicated for
(i) Metastatic prostate cancer.
(ii) Locally advanced prostate cancer, as an alternative to surgical castration.
(iii) As an adjuvant treatment to radiotherapy in patients with high-risk localised or locally advanced prostate cancer.
(iv) As an adjuvant treatment to radical prostatectomy in patients with locally advanced prostate cancer at high risk of disease progression.
(v) As neo-adjuvant treatment prior to radiotherapy in patients with high-risk localised or locally advanced prostate cancer.
4.2 Posology and method of administration
Posology
Adult prostate cancer patients
CAMCEVI should be administered under the direction of a healthcare professional having available the appropriate expertise for monitoring the response to treatment.
CAMCEVI is administered as a single subcutaneous injection every three months. The injected suspension forms a solid medicinal product delivery depot and provides continuous release of leuprorelin over a three-month period.
As a rule, therapy of advanced prostate cancer with leuprorelin entails long-term treatment and therapy should not be discontinued when remission or improvement occurs.
Leuprorelin may be used as neoadjuvant or adjuvant therapy in combination with radiotherapy in high-risk localised and locally advanced prostate cancer.
Response to leuprorelin should be monitored by clinical parameters and by measuring prostate specific antigen (PSA) serum levels. Clinical studies have shown that testosterone levels increased during the first 4 days of treatment in the majority of non-orchiectomised patients. They then decreased and reached castrate levels by 2-4 weeks. Once attained, castrate levels were maintained as long as drug therapy continued (<1% of testosterone breakthroughs). If a patient’s response appears to be sub-optimal, then it would be advisable to confirm that serum testosterone levels have reached or are remaining at castrate levels. Transient increases in acid phosphatase levels sometimes occur early in the treatment period but usually return to normal or near normal values by the 4th week of treatment.
In patients treated with GnRH analogues for prostate cancer, treatment is usually continued upon development of castrate-resistant prostate cancer. Reference should be made to relevant guidelines.
Special populations
Renal/hepatic impairment
No clinical studies were performed in patients having either renal or hepatic impairment.
Paediatric population
The safety and efficacy of leuprorelin in children aged 0 to 18 years have not been established (see also section 4.3). No data are available.
Method of administration
CAMCEVI should be administered subcutaneously only by healthcare professionals who are familiar with these procedures. For instructions on administration of the medicinal product, see section 6.6.
Intra-arterial or intravenous injection, respectively, must be strictly avoided.
As with other medicinal products administered by subcutaneous injection, the injection site should be varied periodically.
4.3 Contraindications
CAMCEVI is contraindicated in women and paediatric patients.
Hypersensitivity to leuprorelin, any of the excipients or to other synthetic gonadotrophin releasing hormone (Gn-RH) analogues or Gn-RH derivatives.
Patients who previously underwent orchiectomy (as with other GnRH agonists, leuprorelin does not result in further decrease of serum testosterone in case of surgical castration).
As sole treatment in prostate cancer patients with spinal cord compression or evidence of spinal metastases (see also section 4.4).
4.4 Special warnings and precautions for use
Androgen deprivation therapy may prolong the QT interval
In patients with a history of or risk factors for QT prolongation and in patients receiving concomitant medicinal products that might prolong the QT interval (see section 4.5) physicians should assess the benefit/risk ratio including the potential for Torsade de pointes prior to initiating leuprorelin. Periodic monitoring of electrocardiograms and electrolytes should be considered.
Cardiovascular diseases
Increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with use of GnRH agonists in men. The risk appears low based on the reported odds ratios, and should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Patients receiving GnRH agonists should be monitored for symptoms and signs suggestive of development of cardiovascular disease and be managed according to current clinical practice.
Transient testosterone flare
Leuprorelin, like other GnRH agonists, causes a transient increase in serum concentrations of testosterone, dihydrotestosterone and acid phosphatase during the first week of treatment. Patients may experience worsening of symptoms or onset of new symptoms, including bone pain, neuropathy, haematuria, or ureteral or bladder outlet obstruction (see section 4.8). These symptoms usually subside on continuation of therapy.
Additional administration of an appropriate antiandrogen should be considered beginning 3 days prior to leuprorelin therapy and continuing for the first two to three weeks of treatment. This has been reported to prevent the sequelae of an initial rise in serum testosterone.
Following surgical castration, leuprorelin does not lead to a further decrease in serum testosterone levels in male patients.
Bone density
Decreased bone density has been reported in the medical literature in men who have had orchiectomy or who have been treated with GnRH agonists (see section 4.8).
Antiandrogen therapy significantly increases the risk for fractures owing to osteoporosis. Only limited data is available on this issue. Fractures owing to osteoporosis were observed in 5% of patients following 22 months of pharmacological androgen deprivation therapy and in 4% of patients following 5 to 10 years of treatment. The risk for fractures owing to osteoporosis is generally higher than the risk for pathological fractures.
Apart from long lasting testosterone deficiency, increased age, smoking and consumption of alcoholic beverages, obesity and insufficient exercise may have an influence on the development of osteoporosis.
Pituitary apoplexy
During post-marketing surveillance, rare cases of pituitary apoplexy (a clinical syndrome secondary to infarction of the pituitary gland) have been reported after the administration of GnRH agonists, with a majority occurring within 2 weeks of the first dose, and some within the first hour. In these cases, pituitary apoplexy was presented as sudden headache, vomiting, visual changes, ophthalmoplegia, altered mental status, and sometimes cardiovascular collapse. Immediate medical attention is required.
Hyperglycaemia and diabetes
Hyperglycaemia and an increased risk of developing diabetes have been reported in men receiving GnRH agonists. Hyperglycaemia may represent development of diabetes mellitus or worsening of glycaemic control in patients with diabetes. Blood glucose and/or glycosylated haemoglobin (HbA1c) should be monitored periodically in patients receiving a GnRH agonist and patients should be managed with current practice for treatment of hyperglycaemia or diabetes. Metabolic changes associated with GnRH agonist may also include fatty liver disease.
Seizure
Postmarketing reports of seizures have been observed in patients treated with leuprorelin. These events have been reported in those with or without a history of epilepsy, seizure disorders or risk disorders for seizures.
Idiopathic intracranial hypertension
Idiopathic intracranial hypertension (pseudotumor cerebri) has been reported in patients receiving leuprorelin. Patients should be warned for signs and symptoms of idiopathic intracranial hypertension, including severe or recurrent headache, vision disturbances and tinnitus. If idiopathic intracranial hypertension occurs, discontinuation of leuprorelin should be considered.
Severe cutaneous adverse reactions
Severe cutaneous adverse reactions (SCARs) including Stevens-Johnson syndrome (SJS), and Toxic epidermal necrolysis (TEN) which can be life-threatening or fatal, have been reported in association with leuprorelin treatment. At the time of prescription patients should be advised of the signs and symptoms and monitored closely for severe skin reactions. If signs and symptoms suggestive of these reactions appear, leuprorelin should be withdrawn immediately and an alternative treatment considered (as appropriate).
Other events
Cases of ureteral obstruction and spinal cord compression, which may contribute to paralysis with or without fatal complications, have been reported with GnRH agonists. If spinal cord compression or renal impairment develops, standard treatment of these complications should be instituted.
Patients with vertebral and/or brain metastases as well as patients with urinary tract obstruction should be closely monitored during the first few weeks of therapy.
Depression
There is an increased risk of incident depression (which may be severe) in patients undergoing treatment with GnRH agonists, such as leuprorelin. Patients should be informed and monitored accordingly and treated as appropriate if symptoms occur.
4.5 Interaction with other medicinal products and other forms of interaction
No interaction studies have been performed.
Since androgen deprivation treatment may prolong the QT interval, the concomitant use of leuprorelin with medicinal products known to prolong the QT interval or medicinal products able to induce Torsade de pointes such as class IA (e.g. quinidine, disopyramide) or class III (e.g. amiodarone, sotalol, dofetilide, ibutilide) antiarrhythmic medicinal products, methadone, moxifloxacin, antipsychotics, etc. should be carefully evaluated (see section 4.4).
4.6 Fertility, pregnancy and lactation
CAMCEVI is contraindicated in women.
Based on findings in animals and mechanism of action, leuprorelin may impair fertility in males of reproductive potential (see section 5.3).
4.7 Effects on ability to drive and use machines
Leuprorelin-containing medicinal products can have minor influence on the ability to drive and use machines. The administration of this medicinal product can cause fatigue, dizziness and visual disturbances (see section 4.8). Patients should be advised not to drive or operate machinery if these adverse reactions occur.
4.8 Undesirable effects
Summary of the safety profile
Adverse reactions seen with leuprorelin-containing medicinal products are mainly subject to the specific pharmacological action of leuprorelin, namely increases and decreases in certain hormone levels. The most commonly reported adverse reactions are hot flushes, nausea, malaise and fatigue and transient local irritation at the site of injection. Mild or moderate hot flushes occur in approximately 58% of patients.
Tabulated list of adverse reactions
The following table lists adverse reactions with leuprorelin based on experience from clinical trials as well as from post-marketing experience. Adverse reactions are grouped by MedDRA System Organ Classes and frequency classification. Frequencies are defined as: very common (≥1/10); common (≥1/100 to <1/10); uncommon (≥1/1,000 to <1/100); rare (≥1/10,000 to <1/1,000); very rare (<1/10,000); not known (cannot be estimated from the available data).
Table 1: Undesirable effects reported for leuprorelin-containing medicinal products for injection
| SOC | Very common | Common | Uncommon | Rare | Very rare | Not known | ||||||||||||||||||
| Infections and infestations | nasopharyngitis | urinary tract | ||||||||||||||||||||||
| infection, local | ||||||||||||||||||||||||
| skin infection | ||||||||||||||||||||||||
Blood and lymphatic system disorders | anaemia (reported | |||||||||||||||||||||||
| in medicinal | ||||||||||||||||||||||||
| products of this | ||||||||||||||||||||||||
| class), | ||||||||||||||||||||||||
| thrombocytopaenia, | ||||||||||||||||||||||||
| leucopenia | ||||||||||||||||||||||||
| Immune system disorders | hypersensitivity | |||||||||||||||||||||||
| reactions | ||||||||||||||||||||||||
| (including rash, | ||||||||||||||||||||||||
| pruritus, urticaria, | ||||||||||||||||||||||||
| wheezing, fever, | ||||||||||||||||||||||||
| chills and | ||||||||||||||||||||||||
| anaphylactic | ||||||||||||||||||||||||
| reactions) | ||||||||||||||||||||||||
Metabolism and nutrition disorders | weight fluctuation | decreased appetite | worsening of glycaemic control in diabetes mellitus, hepatic steatosis | Metabolic | ||||||||||||||||||||
| syndrome | ||||||||||||||||||||||||
| (including | ||||||||||||||||||||||||
| hypertension, | ||||||||||||||||||||||||
| dyslipidaemia, | ||||||||||||||||||||||||
| insulin resistance, | ||||||||||||||||||||||||
| abnormal glucose | ||||||||||||||||||||||||
| tolerance) | ||||||||||||||||||||||||
| Psychiatric disorders | insomnia, | mood changes (short term use)**, abnormal dreams | ||||||||||||||||||||||
| depression (see | ||||||||||||||||||||||||
| Section 4.4), mood | ||||||||||||||||||||||||
| changes (long-term | ||||||||||||||||||||||||
| use)** | ||||||||||||||||||||||||
| Nervous system disorders | headache (occasionally severe) | dizziness, paraesthesia, taste disturbance, smell disturbance, vertigo | abnormal voluntary movements | pituitary apoplexy has been reported following initial administration in patients with pituitary adenoma, pituitary haemorrhage | paralysis (see Section 4.4), seizure, idiopathic intracranial hypertension (pseudotumor cerebri) (see section 4.4) | |||||||||||||||||||
| Eye disorders | visual impairment | |||||||||||||||||||||||
| Cardiac disorders | myocardial infarction | palpitations, QT | ||||||||||||||||||||||
| prolongation (see | ||||||||||||||||||||||||
| Sections 4.4 and | ||||||||||||||||||||||||
| 4.5) | |||||||||||||||||
| Vascular disorders | hot flush | syncope, collapse | pulmonary | ||||||||||||||
| embolism, | |||||||||||||||||
| hypertension, | |||||||||||||||||
| hypotension (see | |||||||||||||||||
| Sections 4.4 and | |||||||||||||||||
| 4.5) | |||||||||||||||||
| Gastrointestinal disorders | nausea, gastroenteritis/ colitis | diarrhoea, | flatulence, eructation | ||||||||||||||
| vomiting, dry | |||||||||||||||||
| mouth, | |||||||||||||||||
| dyspepsia | |||||||||||||||||
| Hepatobiliary disorders | hepatic function | jaundice | |||||||||||||||
| abnormal, hepatic | |||||||||||||||||
| function test | |||||||||||||||||
| abnormal (usually | |||||||||||||||||
| transient) | |||||||||||||||||
Skin and subcutaneous tissue disorders | hyperhydrosis, echhymoses, erythema | alopecia, skin eruption | Stevens-Johnson | ||||||||||||||
| syndrome/Toxic | |||||||||||||||||
| Epidermal | |||||||||||||||||
| Necrolysis | |||||||||||||||||
| (SJS/TEN) (see | |||||||||||||||||
| section 4.4), Toxic | |||||||||||||||||
| Skin Eruption, | |||||||||||||||||
| Erythema | |||||||||||||||||
| Multiforme | |||||||||||||||||
Musculoskeletal, connective tissue and bone disorders | muscle weakness, bone pain | arthralgia, rigors | myalgia, weakness of lower extremities, back pain, muscle cramps | spinal fracture, | |||||||||||||
| reduction in bone | |||||||||||||||||
| mineral density, | |||||||||||||||||
| osteoporosis | |||||||||||||||||
| (including spinal | |||||||||||||||||
| fracture, see | |||||||||||||||||
| Section 4.4) | |||||||||||||||||
| Respiratory, | Interstitial lung disease | ||||||||||||||||
| thoracic and | |||||||||||||||||
| mediastinal | |||||||||||||||||
| disorders | |||||||||||||||||
| Renal and urinary disorders | urinary | bladder spasm, haematuria, aggravated urinary frequency | urinary tract obstruction | ||||||||||||||
| infrequency, | |||||||||||||||||
| difficulty in | |||||||||||||||||
| micturition, | |||||||||||||||||
| dysuria, nocturia, | |||||||||||||||||
| oliguria | |||||||||||||||||
| Reproductive system and breast disorders | Libido | gynaecomastia, testicular pain, reduced penis size | |||||||||||||||
| decreased, | |||||||||||||||||
| erectile | |||||||||||||||||
| dysfunction, | |||||||||||||||||
| testicular | |||||||||||||||||
| atrophy | |||||||||||||||||
General disorders and administration site conditions | Fatigue, | oedema peripheral | pyrexia | ||||||||||||||
| injection site | |||||||||||||||||
| reaction, e.g., | |||||||||||||||||
| induration, | |||||||||||||||||
| erythema, pain, | |||||||||||||||||
| abscesses, | |||||||||||||||||
| swelling, | |||||||||||||||||
| nodules, ulcers | |||||||||||||||||
| and necrosis | |||||||||||||||||
| Investigations | increased creatinine | increased ALT, | |||||||||||||||
| phosphokinase, | increased | ||||||||||||||||
| prolonged | triglycerides, | ||||||||||||||||
| coagulation time | prolonged PT |
** mood changes (long term use: frequency of 'common' and short term use: frequency of 'uncommon')
Description of selected adverse reactions
In cases where a "tumour flare" occurs after leuprorelin therapy, an exacerbation may occur in any symptoms or signs due to disease. Adverse events, which may occur particularly at the beginning of treatment include urinary tract obstruction (as urinary symptoms). In patients with spinal cord compression, bone pain, weakness of the lower extremities and paraesthesia (as neurologic symptom) may also occur (see section 4.4). These symptoms subside on continuation of therapy.
Clinical experience on local skin tolerability with leuprorelin
Local skin tolerability of leuprorelin was assessed in the main study FP01C-17-001 per four aspects: itchiness, erythema, burning, and stinging. Of the 144 subjects receiving subcutaneous injections of leuprorelin, most subjects showed no to mild skin irritation after the injection. Generally, the reported localised events were mild and resolved.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
No case of overdose has been reported.
In animal studies, doses of up to 500 times the recommended human dose resulted in dyspnoea, decreased activity and local irritation at the injection site. In cases of overdose, the patients should be monitored closely and management should be symptomatic and supportive.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Gonadotropin-Releasing Hormone Analogues
ATC code: L02AE02
CAMCEVI contains leuprorelin mesilate, a synthetic nonapeptide analogue of naturally occurring gonadotrophin releasing hormone (GnRH) which possesses greater potency than the natural hormone. Leuprorelin mesilate is a peptide and therefore unrelated to the steroids. Chronic administration results in an inhibition of gonadotrophin production and subsequent suppression of testicular steroid secretion. This effect is reversible on discontinuation of therapy.
Administration of leuprorelin mesilate results in an initial increase in circulating levels of gonadotrophins which leads to a transient increase in gonadal steroid levels in men. Continued administration of leuprorelin mesilate results in a decrease of gonadotrophin and sex steroid levels. In men serum testosterone levels, initially raised in response to early luteinising hormone (LH) release, fall to castrate levels in about 2-4 weeks.
Leuprorelin mesilate is inactive when given orally.
Following the first dose of CAMCEVI, mean serum testosterone concentrations transiently increased, then fell to below castrate threshold levels (≤ 50 ng/dL) within 3-4 weeks, and were maintained below castrate threshold with 3-monthly administration of the medicinal product (Figure 1 below). Long-term studies on leuprorelin have shown that continuation of therapy maintains testosterone below the castrate level for up to seven years, and presumably indefinitely.
In an open, prospective clinical trial involving 205 patients receiving 3.75mg leuprorelin acetate on a monthly basis as treatment for metastatic prostate cancer, the long-term efficacy and safety of leuprorelin acetate was assessed. Testosterone levels were maintained below the castrate threshold over the 63-month follow up period. Median survival time exceeded 42.5 months for those receiving monotherapy and 30.9 months for those receiving leuprorelin acetate in combination with anti-androgens (this difference relating to baseline differences between groups).
In a meta-analysis involving primarily patients with metastatic disease, no statistically significant difference in survival was found for patients treated with GnRH analogues compared with patients treated with orchidectomy.
In another randomised, open-label, multi-centre comparative trial, leuprorelin acetate in combination with flutamide has been shown to significantly improve disease-free survival and overall survival when used as an adjuvant therapy to radiotherapy in 88 patients with high-risk localised (T1-T2 and PSA of at least 10ng/ml or a Gleason score of at least 7), or locally advanced (T3-T4) prostate cancer. The optimum duration of adjuvant therapy has not been established. This US study used a higher dose of leuprorelin acetate (7.5mg/month) which is therapeutically equivalent to the European licensed dose.
The use of a GnRH agonist may be considered after prostatectomy in selected patients considered at high risk of disease progression. There are no disease-free survival data or survival data with leuprorelin acetate in this setting.
Neoadjuvant leuprorelin acetate prior to radiotherapy has been shown to reduce prostate volume.
Clinical experience on efficacy with CAMCEVI
The multicentre, single-arm, open label, 24-week phase 3 study of leuprorelin included 144 male patients with high-risk localised and locally advanced prostate cancer in need for androgen deprivation therapy. The efficacy of the medicinal product (two doses administered 12 weeks apart) was evaluated by the percentage of subjects with serum testosterone concentrations suppressed to castrate threshold levels, the effect on serum LH levels as measure for testosterone level control, and the effect on serum PSA levels. The percentage of patients with serum testosterone levels below the castrate threshold (≤ 50ng/dL) by day 28 was 98.6% (141 out of 143 subjects; intent-to-treat) and 98.5% (130 out of 132 subjects; per protocol), respectively (Figure 1).
Figure 1: Mean serum testosterone concentration over time with CAMCEVI 21mg (n=132; per protocol population) 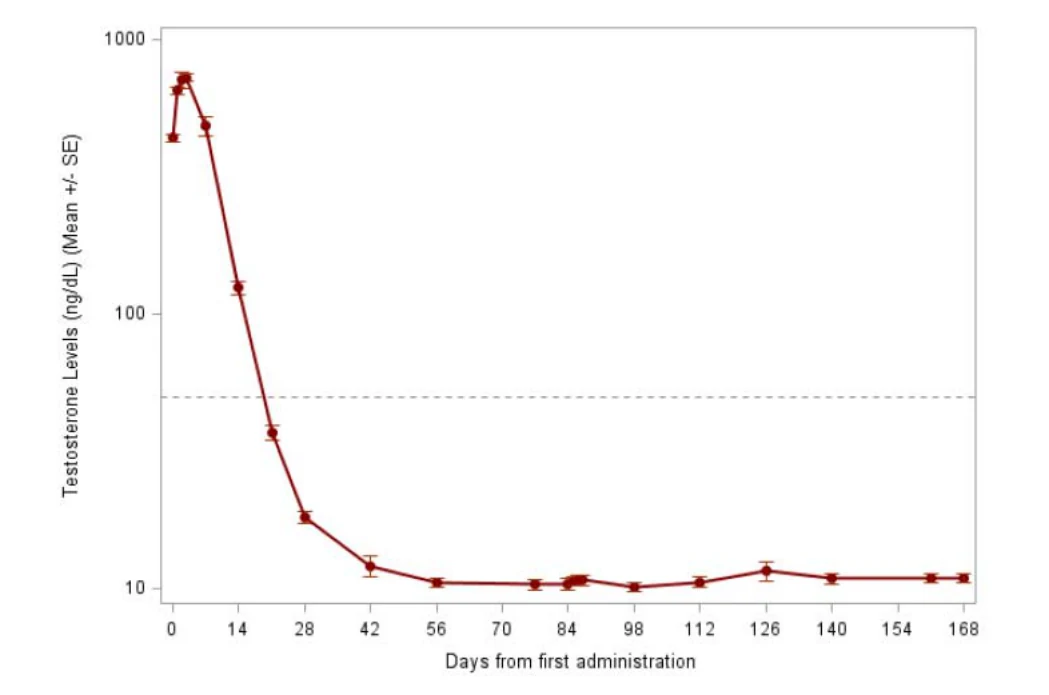
Dotted line indicates the castrate level (50 ng/dL) of serum testosterone.
Mean serum LH levels were significantly reduced after the first injection, and this effect remained until the end of the study (decrease versus baseline by 97% [day 168]).
Tumour size was not directly measured in this study, but an indirect beneficial tumour response can be presumed for leuprorelin as shown by a significant (96.7%) reduction in mean PSA levels over time after injection of the medicinal product (mean of 35.9ng/mL at baseline decreased to a mean minimum of 1.2ng/mL [per-protocol population] at Day 168.
Paediatric population
CAMCEVI is contraindicated in the paediatric population.
5.2 Pharmacokinetic properties
Absorption
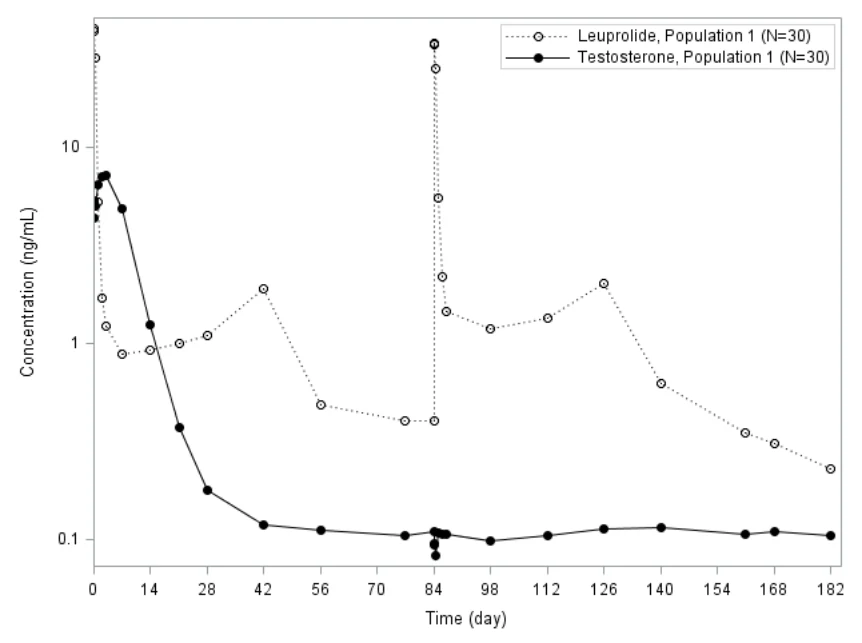
Following the first and the second doses of CAMCEVI, an initial rapid increase of serum leuprorelin concentration was observed, followed by a rapid decline over the first 3 days post-dose: after an initial “burst” phase characterised by mean serum leuprorelin concentrations of 43.4 and 37.8ng/mL after approximately 2.0 and 2.0 hours post dosing, respectively, mean serum leuprorelin levels maintained relatively constant over each 12-week dosing interval, with leuprorelin being continuously released by the third day after dosing with steady serum concentrations ("plateau" phase) through the 12-week (approximately 3-month) dosing interval (mean concentration: 1.22 and 1.44ng/mL). There is no indication of significant accumulation with repeated leuprorelin dosing at 12-week intervals.
The initial acute increase of leuprorelin concentrations after CAMCEVI is followed by a rapid decline to steady state levels.
The pharmacokinetics/pharmacodynamics (as per serum testosterone level) profiles of leuprorelin versus serum testosterone level observed after initial injection of CAMCEVI (first dose) and at 12 weeks (second dose) is shown in Figure 2 (study FP01C-17-001).
Figure 2: Pharmacokinetic/pharmacodynamic response to CAMCEVI 21mg
Distribution
The mean steady-state volume of distribution of leuprorelin following intravenous bolus administration to healthy male volunteers was 27 litres. In vitro binding to human plasma proteins ranged from 43% to 49%.
Metabolism
No metabolism study was conducted with leuprorelin.
Elimination
In healthy male volunteers, a 1mg bolus of leuprorelin administered intravenously revealed that the mean systemic clearance was 8.34 L/h, with a terminal elimination half- life of approximately 3 hours based on a two-compartment model.
No excretion studies have been conducted with leuprorelin.
5.3 Preclinical safety data
Preclinical studies with leuprorelin revealed effects on the reproductive system, which were expected from the known pharmacological properties. These effects were shown to be reversible after discontinuation of the treatment and an appropriate period of regeneration. Leuprorelin did not show teratogenicity. Embryotoxicity/lethality was observed in rabbits, in line with the pharmacological effects of leuprorelin on the reproductive system.
Consistent with the GnRH agonistic effects of leuprorelin hyperplasia and adenoma were observed in the anterior pituitary of rats.
Carcinogenicity studies were performed in rats and mice over 24 months. In rats, a dose-related increase in pituitary apoplexy was observed after subcutaneous administration at doses of 0.6 to 4mg/kg/day. No such effect was observed in mice.
Leuprorelin was not mutagenic in a set of in vitro and in vivo assays.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Poly(D,L-lactide-co-glycolide)
N-methyl-2-pyrrolidone
6.2 Incompatibilities
Not applicable.
6.3 Shelf life
30 months
6.4 Special precautions for storage
Store in a refrigerator (2°C – 8°C).
Store in the original package in order to protect from light. Once outside the refrigerator this product may be stored in its original packaging at room temperature (below 25°C) for up to eight weeks, discard if not used within eight weeks.
6.5 Nature and contents of container
One pack contains 1 pre-filled syringe (cyclic olefin copolymer, closed with a bromobutyl elastomeric grey tip cap, plunger and finger grip) and 1 sterile safety needle (18 gauge, 5/8 inch).
6.6 Special precautions for disposal
Follow the instructions as directed to ensure proper preparation of CAMCEVI prior to administration.
Important: Prior to use allow CAMCEVI to reach room temperature (15 °C to 25 °C). The use of gloves is recommended during administration.
CAMCEVI contains:
- One blister containing one sterile pre-filled syringe
- One sterile safety needle.
Assembled pre-filled syringe: 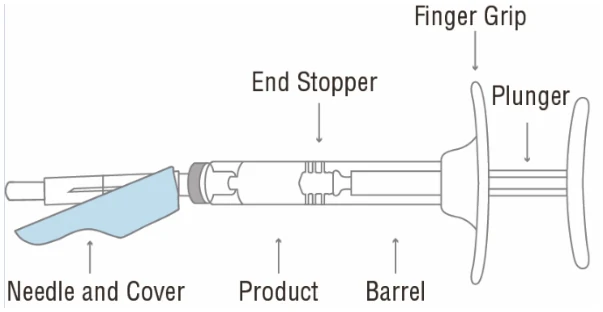
Step 1 - Prepare the medicinal product:
Allow to reach room temperature and inspect contents
- Remove CAMCEVI from refrigerator.
- Prior to use allow CAMCEVI to reach
room temperature (15 °C to 25 °C). This 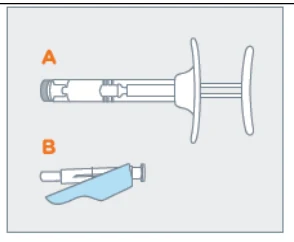
takes approximately 15 to 20 minutes.
- On a flat, clean and dry surface open carton and remove the blister container and the sachet. Remove the pre-filled CAMCEVI syringe (A) from the blister container. Remove the safety needle (B) from the sachet. Examine all contents of the package. Do not use if any component is damaged.
- Check the expiry date on the syringe. Do not use if the expiry date has passed.
- Visually inspect the medicine prior to use. The pre-filled syringe should contain off-white to pale yellow viscous and opalescent suspension. Do not use if foreign particles are noticed inside the syringe barrel.
Step 2 - Syringe assembly:
Attach the needle
Remove the grey cap from the syringe
(A).
- Attach the needle (B) to the end of the
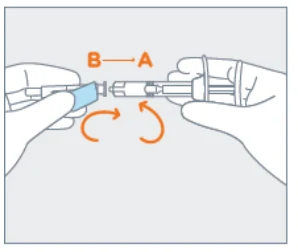
syringe (A) by pushing and turning clockwise with approximately a three-quarter turn until the needle is secure. Do not overtighten. Discard pre-filled CAMCEVI syringe if over-twist causes syringe or needle breakage.
Step 3 - Administration procedure:
Prepare the injection site
- Choose an injection site on the upper- or mid-abdominal area with sufficient soft or loose subcutaneous tissue that has not recently been used. The injection site should be varied periodically.
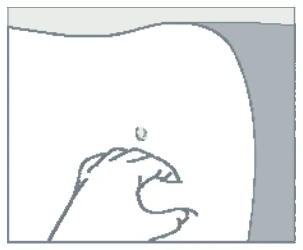
- Clean the injection site with an alcohol swab. Do NOT inject in areas with brawny or fibrous subcutaneous tissue or locations that can be rubbed or compressed (i.e., with a belt or clothing waistband).
Pull the needle cap from the needle (B).
Grab and bunch the skin around the
Administer treatment 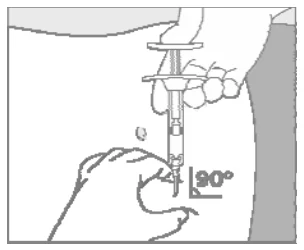
injection site with one hand. Insert the needle at a 90° angle, then release the bunched skin.
Inject the full contents of the syringe with a slow and steady push, then withdraw the needle at the same 90° angle used for insertion.
Intra-arterial or intravenous injection have to be strictly avoided.
Step 4 - Discard needle and pre-filled syringe
Needle Protection
| Thumb activation | Surface activation |
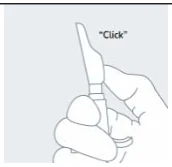
- Immediately following the withdrawal of the needle, activate the safety shield using a finger/thumb or flat surface and push until it completely covers the needle tip and locks into place.
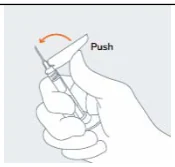
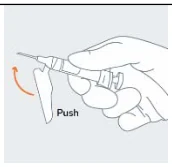
An audible and tactile
“click” verifies a locked position, Check to confirm the safety sheath is fully engaged. After use, place the used syringe with needle protected in a suitable sharps container.
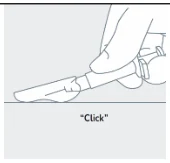
Any unused medicinal product or waste material should be disposed of in
accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Accord Healthcare Limited
Sage House
319 Pinner Road
North Harrow
Middlesex
HA1 4HF
United Kingdom
8 MARKETING AUTHORISATION NUMBER(S)
PL 20075/1580
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
26/06/2026
10 DATE OF REVISION OF THE TEXT
07/10/2026