

Summary of Product Characteristics (SmPC) - Boostrix suspension for injection in PFS, Diphtheria Tetanus and Pertussis (Acellular Component) vaccine
1. NAME OF THE MEDICINAL PRODUCT
Boostrix suspension for injection in pre-filled syringe
Diphtheria, tetanus and pertussis (acellular, component) vaccine (adsorbed, reduced antigen(s) content)
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
1 dose (0.5 ml) contains:
Diphtheria toxoid1 not less than 2 International Units (IU) (2.5 Lf)
Tetanus toxoid1 not less than 20 International Units (IU) (5 Lf)
Bordetella pertussis antigens
Pertussis toxoid1 8 micrograms
Filamentous Haemagglutinin1 8 micrograms
Pertactin1 2.5 micrograms
1 adsorbed on aluminium hydroxide, hydrated (Al(OH)3) 0.3 milligrams Al3+ and aluminium phosphate (AlPO4) 0.2 milligrams Al3+
The vaccine may contain traces of formaldehyde which is used during the manufacturing process (see section 4.3).
For the full list of excipients, see section 6.1.
3. PHARMACEUTICAL FORM
Suspension for injection in pre-filled syringe.
Boostrix is a turbid white suspension.
4 CLINICAL PARTICULARS
4.1 THERAPEUTIC INDICATIONS
Boostrix is indicated for booster vaccination against diphtheria, tetanus and pertussis of individuals from the age of four years onwards (see section 4.2).
Boostrix is also indicated for passive protection against pertussis in early infancy following maternal immunisation during pregnancy (see sections 4.2, 4.6 and 5.1).
The administration of Boostrix should be based on official recommendations.
4.2 POSOLOGY AND METHOD OF ADMINISTRATION
Posology
A single 0.5 ml dose of the vaccine is recommended.
Boostrix may be administered from the age of four years onwards.
Boostrix should be administered in accordance with official recommendations and/or local practice regarding the use of vaccines with reduced content of diphtheria, tetanus and pertussis antigens.
Boostrix can be administered to pregnant women during the second or the third trimester in accordance with official recommendations (see sections 4.1, 4.6 and 5.1).
Boostrix may also be administered to adolescents and adults with unknown vaccination status or incomplete vaccination against diphtheria, tetanus and pertussis as part of an immunisation series against diphtheria, tetanus and pertussis. Based on data in adults, two additional doses of a diphtheria and tetanus containing vaccine are recommended one and six months after the first dose to maximize the vaccine response against diphtheria and tetanus (see section 5.1).
Boostrix can be used in the management of tetanus prone injuries in persons who have previously received a primary vaccination series of tetanus toxoid vaccine and for whom a booster against diphtheria and pertussis is indicated. Tetanus immunoglobulin should be administered concomitantly in accordance with official recommendations.
Repeat vaccination against diphtheria, tetanus and pertussis should be performed at intervals as per official recommendations (generally 10 years).
Paediatric population
The safety and efficacy of Boostrix in children below 4 years of age have not been established.
Method of administration
Boostrix is for deep intramuscular injection preferably in the deltoid region (see section 4.4).
4.3 CONTRAINDICATIONS
Hypersensitivity to the active substances or to any of the excipients listed in section 6.1 or formaldehyde.
Hypersensitivity after previous administration of diphtheria, tetanus or pertussis vaccines.
Boostrix is contraindicated if the subject has experienced an encephalopathy of unknown aetiology, occurring within 7 days following previous vaccination with pertussis-containing vaccine. In these circumstances, pertussis vaccination should be discontinued and the vaccination course should be continued with diphtheria and tetanus vaccines.
Boostrix should not be administered to subjects who have experienced transient thrombocytopenia or neurological complications (for convulsions or hypotonic-hyporesponsive episodes, see section 4.4) following an earlier immunisation against diphtheria and/or tetanus.
As with other vaccines, administration of Boostrix should be postponed in subjects suffering from acute severe febrile illness. The presence of a minor infection is not a contraindication.
4.4 SPECIAL WARNINGS AND PRECAUTIONS FOR USE
Vaccination should be preceded by a review of the medical history (especially with regard to previous vaccination and possible occurrence of undesirable events).
If any of the following events are known to have occurred in temporal relation to receipt of pertussis-containing vaccine, the decision to give doses of pertussis-containing vaccines should be carefully considered:
- Temperature of ≥ 40.0°C within 48 hours of vaccination, not due to another identifiable cause.
- Collapse or shock-like state (hypotonic-hyporesponsiveness episode) within 48 hours of vaccination.
- Persistent, inconsolable crying lasting ≥ 3 hours, occurring within 48 hours of vaccination.
- Convulsions with or without fever, occurring within 3 days of vaccination. There may be circumstances, such as a high incidence of pertussis, when the potential benefits outweigh possible risks.
As for any vaccination, the risk-benefit of immunising with Boostrix or deferring this vaccination should be weighed carefully in a child suffering from a new onset or progression of a severe neurological disorder.
As with all injectable vaccines, appropriate medical treatment and supervision should always be readily available in case of a rare anaphylactic reaction following the administration of the vaccine.
Boostrix should be administered with caution to subjects with thrombocytopenia (see section 4.3) or a bleeding disorder since bleeding may occur following an intramuscular administration to these subjects. If in accordance with official recommendations, the vaccine may be administered subcutaneously to these subjects. With both routes of administration, firm pressure should be applied to the injection site (without rubbing) for at least two minutes.
Boostrix should in no circumstances be administered intravascularly.
A history or a family history of convulsions and a family history of an adverse event following DTP vaccination do not constitute contraindications.
Human Immunodeficiency Virus (HIV) infection is not considered as a contraindication. The expected immunological response may not be obtained after vaccination of immunosuppressed patients.
Syncope (fainting) can occur following, or even before, any vaccination especially in adolescents as a psychogenic response to the needle injection. This can be accompanied by several neurological signs such as transient visual disturbance, paraesthesia and tonic-clonic limb movements during recovery. It is important that procedures are in place to avoid injury from faints.
As with any vaccine, a protective immune response may not be elicited in all vaccinees.
Excipients
This medicine contains less than 1 mmol sodium (23 mg) per dose, that is to say essentially ‘sodium-free’.
Traceability
In order to improve the traceability of biological medicinal products, the name and the batch number of the administered product should be clearly recorded.
4.5 INTERACTION WITH OTHER MEDICINAL PRODUCTS AND OTHER
FORMS OF INTERACTION
Use with other vaccines or immunoglobulins
Boostrix may be administered concomitantly with human papilloma virus vaccine with no clinically relevant interference with antibody response to any of the components of either vaccine.
Boostrix can be given concomitantly with meningococcal serogroups A, C, W-135 and Y (MenACWY) conjugate vaccines. Clinical studies in subjects aged 9 to 25 years demonstrated that the immune responses to the tetanus, diphtheria and meningococcal antigens were unaffected. Lower geometric mean concentrations (GMCs) were observed for the pertussis antigens; however, these data do not suggest clinically relevant interference.
Boostrix can be given concomitantly with unadjuvanted inactivated seasonal influenza vaccines. When Boostrix was co-administered with a trivalent inactivated influenza vaccine in subjects aged between 19 and 64 years, clinical data demonstrated that the immune responses to the tetanus, diphtheria, pertussis toxoid (PT) and influenza antigens were unaffected. Lower GMCs were observed for the pertussis filamentous haemagglutinin (FHA) and pertactin (PRN) antigens; however, these data do not suggest clinically relevant interference. No differences were observed in a predefined exploratory cohort when the vaccines were given concomitantly or separately to subjects aged 65 years and older.
Boostrix can be given concomitantly with non-live herpes zoster vaccine. Clinical data in subjects aged 50 years and older demonstrated that the immune responses to the tetanus, diphtheria, PT, FHA and herpes zoster antigens were unaffected. Lower GMCs were observed for the PRN antigen; however, these data do not suggest clinically relevant interference.
Concomitant administration of Boostrix with other vaccines or with immunoglobulins has not been studied.
It is unlikely that co-administration with other inactivated vaccines or with immunoglobulins will result in clinically relevant interference with the immune responses.
According to generally accepted vaccine practices and recommendations, if concomitant administration of Boostrix with other vaccines or immunoglobulins is considered necessary, the products should be given at separate sites.
Use with immunosuppressive treatment
As with other vaccines, patients receiving immunosuppressive therapy may not achieve an adequate response.
4.6 FERTILITY, PREGNANCY AND LACTATION
Pregnancy
Boostrix can be used during the second or third trimester of pregnancy in accordance with official recommendations.
For data relating to the prevention of pertussis disease in infants born to women vaccinated during pregnancy, see section 5.1.
Safety data from a randomised controlled clinical trial (341 pregnancy outcomes) and from a prospective observational study (793 pregnancy outcomes) where Boostrix was administered to pregnant women during the third trimester have shown no vaccine related adverse effect on pregnancy or on the health of the foetus/newborn child.
Safety data from prospective clinical studies on the use of Boostrix or Boostrix-IPV during the first and second trimester of pregnancy are not available.
Data from passive surveillance where pregnant women were exposed to Boostrix or to Boostrix-IPV (dTpa-IPV vaccine) in the 3rd and 2nd trimester have shown no vaccine related adverse effect on pregnancy or on the health of the foetus/newborn child.
As with other inactivated vaccines, it is not expected that vaccination with Boostrix harms the foetus at any trimester of pregnancy.
Animal studies do not indicate direct or indirect harmful effects with respect to pregnancy, embryonal/foetal development, parturition or post-natal development (see section 5.3).
Breastfeeding
The effect of administration of Boostrix during lactation has not been assessed. Nevertheless, as Boostrix contains toxoids or inactivated antigens, no risk to the breastfed infant should be expected. The benefits versus the risk of administering Boostrix to breastfeeding women should carefully be evaluated by the healthcare providers.
Fertility
No human data from prospective clinical studies are available. Animal studies do not indicate direct or indirect harmful effects with respect to female fertility (see section 5.3).
4.7 Effects on ability to drive and use machines
The vaccine is unlikely to produce an effect on the ability to drive and use machines.
4.8 UNDESIRABLE EFFECTS
Summary of the safety profile
The safety profile presented below is based on data from clinical trials where Boostrix was administered to 839 children (from 4 to 8 years of age) and 1931 adults, adolescents and children (from 10 to 76 years of age) (Table 1).
The most common events occurring after Boostrix administration in both groups were local injection site reactions (pain, redness and swelling) reported by 23.7 – 80.6% of subjects in each trial. These usually had their onset within the first 48 hours after vaccination. All resolved without sequelae.
Tabulated list of adverse reactions
Adverse reactions reported are listed according to the following frequency: Very common: (≥1/10)
Common: (≥ 1/100 to < 1/10)
Uncommon: (≥ 1/1,000 to < 1/100)
Rare: (≥ 1/10,000 to < 1/1,000)
Very rare: (< 1/10,000)
- Clinical trials
Table 1: Adverse reactions reported in clinical trials with Boostrix
| System Organ Class | Frequency | Adverse reactions | |
Subjects aged 4 - 8 years (N=839) | Subjects aged 10 - 76 years (N = 1931) | ||
| Infections and infestations | Uncommon | upper respiratory tract infection | upper respiratory tract infection, pharyngitis |
| Blood and lymphatic system disorders | Uncommon | lymphadenopathy | |
| Metabolism and nutrition disorders | Common | anorexia | |
| Psychiatric disorders | Very common | irritability | |
| Nervous system disorders | Very common | somnolence | headache |
| Common | headache | dizziness | |
| Uncommon | disturbances in attention | syncope | |
| Eye disorders | Uncommon | conjunctivitis | |
| Respiratory, thoracic and mediastinal disorders | Uncommon | cough | |
| Gastrointestinal disorders | Common | diarrhoea, vomiting, gastrointestinal disorders | nausea, gastrointestinal disorders |
| Uncommon | diarrhoea, vomiting | ||
| Skin and subcutaneous tissue disorders | Uncommon | rash | hyperhidrosis, pruritus, rash |
| Musculoskeletal and connective tissue disorders | Uncommon | arthralgia, myalgia, joint stiffness, musculoskeletal stiffness | |
| General disorders and administration site conditions | Very common | injection site reactions (such as redness and/or swelling), injection site pain, fatigue ≥ | injection site reactions (such as redness and/or swelling), malaise, fatigue, injection site pain |
| Common | pyrexia (fever 37.5°C including fever > 39.0°C), extensive swelling of vaccinated limb (sometimes involving the adjacent joint) | pyrexia (fever ≥ 37.5°C), injection site reactions (such as injection site mass and injection site abscess sterile) | |
| Uncommon | other injection site reactions (such as induration), pain | pyrexia (fever > 39.0°C), influenza like illness, pain |
Reactogenicity after repeat dose
Data on 146 subjects suggest that there might be a small increase in local reactogenicity (pain, redness, swelling) with repeated vaccination according to a 0, 1, 6 months schedule in adults (> 40 years of age).
Data suggest that in subjects primed with DTP in childhood a second booster dose might give an increase of local reactogenicity.
- Post-marketing surveillance
Because these events were reported spontaneously, it is not possible to reliably estimate their frequency.
Table 2: Adverse reactions reported with Boostrix during post-marketing surveillance
| System Organ Class | Frequency | Adverse reactions |
| Immune system disorders | unknown | allergic reactions, including anaphylactic and anaphylactoid reactions |
| Nervous system disorders | unknown | hypotonic-hyporesponsiveness episodes, convulsions (with or without fever) |
| Skin and subcutaneous tissue disorders | unknown | urticaria, angioedema |
| General disorders and administration site conditions | unknown | asthenia |
Following administration of tetanus toxoid containing vaccines, there have been very rare reports of adverse reactions on the central or peripheral nervous systems, including ascending paralysis or even respiratory paralysis (e.g. Guillain-Barré syndrome).
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme at www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Cases of overdose have been reported during post-marketing surveillance. Adverse events following overdosage, when reported, were similar to those reported with normal vaccine administration.
5 PHARMACOLOGICAL PROPERTIES
5.1 PHARMACODYNAMIC PROPERTIES
Pharmacotherapeutic group: Bacterial vaccines, pertussis vaccines, ATC code: J07AJ52
Immune response
Approximately one month following booster vaccination with Boostrix, the following seroprotection / seropositivity rates were observed (Table 3).
Table 3: Immune response in children, adolescents and adults
| Antigen | Response(1) | Adults and adolescents from the age of 10 years onwards ATP(2) N=1694 (% vaccinees) | Children from the age of 4 years onwards ATP(2) N=415 (% vaccinees) |
| Diphtheria | ≥ 0.1 IU/ml | 97.2% | 99.8% |
| Tetanus | ≥ 0.1 IU/ml | 99.0% | 100.0% |
Pertussis:
| ≥ 5 EL.U/ml | 97.8% 99.9% 99.4% | 99.0% 100.0% 99.8% |
(1)Response: where, at the specified time point, a concentration of antibodies against diphtheria and tetanus ≥ 0.1 IU/ml was considered as seroprotection and a concentration of antibodies against pertussis ≥ 5 EL.U/ml was considered as seropositivity.
(2)ATP: According to protocol – includes all eligible subjects, who had received a single booster dose of Boostrix, for whom immunogenicity data was available for at least one antigen at the specified time-point. N: the minimum number of subjects with available data for each antigen
In adolescents and adults, comparative trials have demonstrated that one month post-vaccination, diphtheria antibody titres are similar to adult-type Td vaccines with the same antigen content as Boostrix; lower tetanus antibody titres were seen as compared to adult-type Td vaccines.
As with other adult-type Td vaccines, Boostrix induces higher titres of both anti-D and anti-T antibodies in children and adolescents as compared to adults.
Persistence of the immune response
Three to 3.5 years, 5 to 6 years and 10 years following a first vaccination with Boostrix, the following seroprotection/seropositivity rates were observed in subjects vaccinated according to protocol (ATP1) (Table 4).
Table 4: Persistence of immune response in children, adolescents and adults
Adults and adolescents from the age of 10 years onwards (% vaccinees) | Children from the age of 4 years onwards (% vaccinees) | ||||
Antigen
| Response(2) | |||||
| 3-3.5 years persistence | 5 years persistence | 10 years persistence | 3-3.5 years persistence | 5 to 6 years persistence | |
Adult(3) (N=309) Adole-scent(3) (N=261) | Adult(3) (N=232) Adole-scent(3) (N=250) | Adult(3) (N=158) Adole-scent(3) (N=74) | (N=118) | (N=68) | |
Diphtheria
≥ 0.1 IU/ml ≥ 0.016 IU/ml(4) | 71.2% 91.6% 97.4% 100% | 84.1% 86.8% 94.4% 99.2% | 64.6% 82.4% 89.9% 98.6% | 97.5 % 100 % | 94.2 % Not determined |
Tetanus
| ≥ 0.1 IU/ml | 94.8% 100% | 96.2% 100% | 95.0% 97.3% | 98.4 % | 98.5 % |
Pertussis
Pertussis toxoid Filamentous haemagglutinin Pertactin
| ≥ 5 EL.U/ml | 90.6% 100% 94.8% 81.6% 100% 99.2% | 89.5% 100% 95.0% 76.8% 100% 98.1% | 85.6% 99.4% 95.0% 61.3% 100% 96.0% | 58.7 % 100 % 99.2 % | 51.5 % 100 % 100 % |
(1)ATP: According to protocol – includes all eligible subjects, who had received a single booster dose of Boostrix, for whom immunogenicity data was available for at least one antigen at the specified time-point.
(2)Response: Where, at the specified time point, a concentration of antibodies against diphtheria and tetanus ≥ 0.1 IU/ml was considered as seroprotection and a concentration of antibodies against pertussis ≥ 5 EL.U/ml was considered as seropositivity.
(3)The terms ‘adult’ and ‘adolescent’ reflect the ages at which subjects received their first vaccination with Boostrix. (4)Percentage of subjects with antibody concentrations associated with protection against disease (≥ 0.1 IU/ml by ELISA assay or ≥ 0.016 IU/ml by an in-vitro Vero-cell neutralisation assay).
N = the minimum number of subjects with available data for each antigen
Efficacy in protecting against pertussis
The pertussis antigens contained in Boostrix are an integral part of the paediatric acellular pertussis combination vaccine (Infanrix), for which efficacy after primary vaccination has been demonstrated in a household contact efficacy study. The antibody titres to all three pertussis components following vaccination with Boostrix are higher than those observed during the household contact efficacy trial. Based on these comparisons, Boostrix would provide protection against pertussis, however the degree and duration of protection afforded by the vaccine are undetermined.
Passive protection against pertussis in infants (below 3 months of age) born to mothers vaccinated during pregnancy
In a randomised, cross-over, placebo-controlled study, higher pertussis antibody concentrations were demonstrated at delivery in the cord blood of babies born to mothers vaccinated with Boostrix (dTpa group; N=291) versus placebo (control group; N=292) at 27-36 weeks of pregnancy. The cord blood geometric mean concentrations of antibodies against the pertussis antigens PT, FHA and PRN were 46.9, 366.1 and 301.8 IU/ml in the dTpa group, and 5.5, 22.7 and 14.6 IU/ml in the control group. This corresponds to antibody titres that are 8, 16 and 21 times higher in the cord blood of babies born to vaccinated mothers versus controls. These antibody titres may provide passive protection against pertussis as shown by observational effectiveness studies.
Immunogenicity in infants and toddlers born to mothers vaccinated during pregnancy
The immunogenicity of Infanrix hexa (diphtheria, tetanus, pertussis, hepatitis B, inactivated poliovirus, Haemophilus influenzae type b conjugate vaccine) in infants and toddlers born to healthy mothers vaccinated with Boostrix at 27-36 weeks of pregnancy was evaluated in two clinical studies. Infanrix hexa was co-administered with a 13-valent pneumococcal conjugate vaccine to infants for primary vaccination (n=268); and to the same infants/toddlers from 11 to 18 months as booster dose (n=229).
Post-primary and post-booster vaccination, immunological data did not show clinically relevant interference of maternal vaccination with Boostrix on the infant’s and toddler’s responses to diphtheria, tetanus, hepatitis B, inactivated poliovirus, Haemophilus influenzae type b or pneumococcal antigens.
Lower antibody concentrations against pertussis antigens post-primary (PT, FHA and PRN) and post-booster (PT, FHA) vaccination were observed in infants and toddlers born to mothers vaccinated with Boostrix during pregnancy. The fold-increases of anti-pertussis antibody concentrations from the pre-booster to the 1-month post-booster time point were in the same range for infants and toddlers born to mothers vaccinated with Boostrix or with placebo, demonstrating effective priming of the immune system. In the absence of correlates of protection for pertussis, the clinical relevance of these observations remains to be fully understood. However, current epidemiological data on pertussis disease following the implementation of dTpa maternal immunisation do not suggest any clinical relevance of this immune interference.
Effectiveness in the protection against pertussis disease in infants born to women vaccinated during pregnancy
Boostrix or Boostrix-IPV vaccine effectiveness (VE) was evaluated in three observational studies, in UK, Spain and Australia. The vaccine was used during the third trimester of pregnancy to protect infants below 3 months of age against pertussis disease, as part of a maternal vaccination programme.
Details of each study design and results are provided in Table 5.
Table 5: VE against pertussis disease for infants below 3 months of age born to mothers vaccinated during the third trimester of pregnancy with Boostrix/Boostrix-IPV:
| Study location | Vaccine | Study design | Vaccination Effectiveness |
| UK | Boostrix- IPV | Retrospective, screening method | 88% (95% CI: 79, 93) |
| Spain | Boostrix | Prospective, matched case-control | 90.9% (95% CI: 56.6, 98.1) |
| Australia | Boostrix | Prospective, matched case-control | 69% (95% CI: 13, 89) |
CI: confidence interval
If maternal vaccination occurs within two weeks before delivery, vaccine effectiveness in the infant may be lower than the figures in the table.
Immune response after a repeat dose of Boostrix
The immunogenicity of Boostrix, administered 10 years after a previous booster dose with reduced-antigen content diphtheria, tetanus and acellular pertussis vaccine(s) has been evaluated. One month post vaccination, > 99 % of subjects were seroprotected against diphtheria and tetanus and seropositive against pertussis.
Immune response in subjects without prior or with unknown vaccination history
After administration of one dose of Boostrix to 83 adolescents aged from 11 to 18 years, without previous pertussis vaccination and no vaccination against diphtheria and tetanus in the previous 5 years, all subjects were seroprotected against tetanus and diphtheria. The seropositivity rate after one dose varied between 87% and 100% for the different pertussis antigens.
After administration of one dose of Boostrix to 139 adults ≥ 40 years of age that had not received any diphtheria and tetanus containing vaccine in the past 20 years, more than 98.5% of adults were seropositive for all three pertussis antigens and 81.5% and 93.4% were seroprotected against diphtheria and tetanus respectively. After administration of two additional doses one and six months after the first dose, the seropositivity rate was 100% for all three pertussis antigens and the seroprotection rates for diphtheria and tetanus reached 99.3% and 100% respectively.
Immune response and safety profile in subjects on active treatment for obstructive airway diseases
The safety and immunogenicity of Boostrix have been evaluated in a descriptive meta-analysis study combining data from 222 subjects ≥ 18 years of age vaccinated with Boostrix while on active treatment for obstructive airway disease such as asthma or Chronic Obstructive Pulmonary Disease (COPD). One month after Boostrix vaccination, the immune responses against diphtheria and tetanus antigens in terms of seroprotective rates (≥ 0.1 IU/mL) were respectively 89.0% and 97.2%, and against pertussis in terms of booster responses these were 78.3 %, 96.1 % and 92.2 % against pertussis toxoid [PT], filamentous haemagglutinin [FHA] and pertactin [PRN], respectively. These results are consistent with the responses obtained in the general adult population and with a similar safety profile.
5.2 Pharmacokinetic properties
Evaluation of pharmacokinetic properties is not required for vaccines.
5.3 Preclinical safety data
Reproductive toxicology
Fertility
Non-clinical data obtained with Boostrix reveal no specific hazard for humans based on conventional studies of female fertility in rats and rabbits.
Pregnancy
Non-clinical data obtained with Boostrix reveal no specific hazard for humans based on conventional studies of embryo-foetal development in rats and rabbits, and also of parturition and postnatal toxicity in rats (up to the end of the lactation period).
Animal toxicology and/or pharmacology
Preclinical data reveal no special hazard for humans based on conventional studies of safety and of toxicity.
6 PHARMACEUTICAL PARTICULARS
6.1 LIST OF EXCIPIENTS
Sodium chloride
Water for injections
For adjuvants, see section 2.
6.2 Incompatibilities
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products
6.3 SHELF LIFE
4 years.
6.4 SPECIAL PRECAUTIONS FOR STORAGE
Store in a refrigerator (2°C – 8°C).
Stability data indicate that Boostrix is stable at temperatures up to 37°C for 7 days. At the end of this period Boostrix should be used or discarded. These data are intended to guide healthcare professionals in case of temporary temperature excursion only.
Do not freeze.
Store in the original package in order to protect from light.
6.5 NATURE AND CONTENTS OF CONTAINER
0.5 ml of suspension in a pre-filled syringe (type I glass) with a plunger stopper (butyl rubber) and with a rubber tip cap.
Pack sizes of 1 and 10, with or without needles.
The tip cap and the rubber plunger stopper of the pre-filled syringe are made with synthetic rubber.
Not all pack sizes may be marketed.
6.6 SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Prior to use, the vaccine should be at room temperature, and well shaken in order to obtain a homogeneous turbid white suspension. Prior to administration, the vaccine should be visually inspected for any foreign particulate matter and/or variation of physical aspect. In the event of either being observed, do not administer the vaccine.
Instructions for the pre-filled syringe
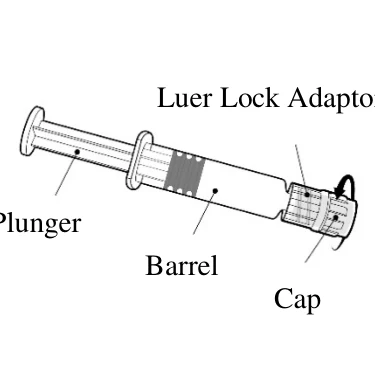
Hold the syringe by the barrel, not by the plunger.
Unscrew the syringe cap by twisting it anticlockwise. 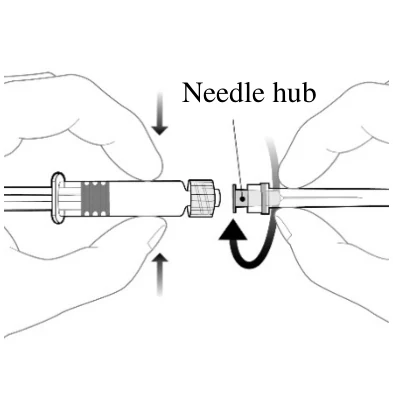
To attach the needle, connect the hub to the Luer Lock Adaptor and rotate a quarter turn clockwise until you feel it lock.
Do not pull the syringe plunger out of the barrel. If it happens, do not administer the vaccine.
Disposal:
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
SmithKline Beecham Ltd
79 New Oxford Street
London
WC1A 1DG
United Kingdom
Trading as: GlaxoSmithKline UK
8. MARKETING AUTHORISATION NUMBER(S)
PL 10592/0162
9. DATE OF FIRST AUTHORISATION/RENEWAL OF THE AUTHORISATION
Date of first authorisation: 2 August 2005
Date of last renewal: 23 December 2009
Plunger
Barrel
Cap
Luer Lock Adaptor
Needle hub
10 DATE OF REVISION OF THE TEXT
22/01/2025