


Summary of Product Characteristics (SmPC) - Austedo 24 mg prolonged-release tablets
1 NAME OF THE MEDICINAL PRODUCT
Austedo 24 mg Prolonged-release Tablets
2 QUALITATIVE AND QUANTITATIVE COMPOSITION
Each prolonged-release tablet contains 24 mg of deutetrabenazine.
Excipient with known effect
Each prolonged-release tablet contains 0.94 mg of allura red AC.
For the full list of excipients, see section 6.1
3 PHARMACEUTICAL FORM
Prolonged-release tablet
The tablets are round, purple, film-coated, with a diameter of approximately 9 mm and “Q24” printed in black ink on one side.
4 CLINICAL PARTICULARS
4.1 Therapeutic indications
Austedo is indicated for the treatment of moderate to severe tardive dyskinesia in adults.
4.2 Posology and method of administration
The initiation and titration of Austedo treatment should be supervised by a physician with experience in drug-induced movement disorders.
Posology
Austedo dosing should be determined individually for each patient, based on adequate reduction of tardive dyskinesia symptoms and tolerability.
Therapy should be initiated at 12 mg once daily for one week. The dose should then be increased to 24 mg once daily for another week. After the second week, it is recommended that the dose be titrated at weekly intervals in increments of 6 mg once daily, based on reduction of tardive dyskinesia symptoms and tolerability. The efficacious dose range is considered to be 24 mg to 48 mg. The maximum recommended daily dose is 48 mg.
In patients receiving strong CYP2D6 inhibitors or who are poor CYP2D6 metabolisers, the daily dose of deutetrabenazine should not exceed 36 mg (see sections 4.5 and 5.2).
A decision to continue treatment with deutetrabenazine should be taken on an individual patient basis. Treatment can be continued for as long as a therapeutic benefit is observed, and the patient tolerates treatment.
Treatment with deutetrabenazine can be discontinued without the need for tapering off.
Missed doses
If a patient misses doses for less than one week, treatment can be resumed at the current dose. If the patient misses doses for more than one week, Austedo therapy should be restarted at 12 mg once daily.
Special populations
Elderly
There is limited data available on the use of deutetrabenazine in patients ≥
65 years of age. Based on the results of population pharmacokinetic analysis, no dose adjustment is required (see section 5.2).
Hepatic impairment
The use of deutetrabenazine in patients with hepatic impairment is contraindicated (see sections 4.3 and 5.2).
Renal impairment
No dose adjustment is necessary in patients with renal impairment (see section 5.2).
Paediatric population
There is no relevant use of Austedo in the paediatric population for the indication of tardive dyskinesia.
Method of administration
For oral use.
The prolonged-release tablets can be taken with or without food. To preserve the prolonged-release properties, the tablets must be swallowed whole with water, not chewed, crushed or divided.
The active substance is contained within a non-absorbable shell designed to release the active substance at a controlled rate. The tablet shell is eliminated from the body. Patients should be advised that they may occasionally notice in their stool something that looks like a tablet.
4.3 Contraindications
Hypersensitivity to the active substance or to any of the excipients listed in section 6.1.
Hepatic impairment (see section 4.2).
Concomitant treatment with reserpine (see section 4.5).
Concomitant treatment with monoamine oxidase inhibitors (MAOIs) (see section 4.5).
Concomitant treatment with other vesicular monoamine transporter 2 (VMAT2) inhibitors (see section 4.5).
4.4 Special warnings and precautions for use
Depression
Deutetrabenazine may cause depression or worsen pre-existing depression (see section 4.8). Patients should be closely monitored for the emergence of such adverse reactions. Patients and their caregivers should be informed of the risks and instructed to report any concerns to their doctor immediately. If depression does not resolve, discontinuing treatment with deutetrabenazine should be considered.
QTc prolongation
Deutetrabenazine may prolong the QTc interval, but the degree of QTc prolongation is not clinically significant when deutetrabenazine is administered within the recommended dose range (see section 5.1). Deutetrabenazine should be used with caution in combination with other medicinal products that prolong the QTc interval (see section 4.5) and in patients with congenital long QT syndrome, bradycardia, hypokalaemia, hypomagnesaemia or a history of cardiac arrhythmias.
Neuroleptic malignant syndrome (NMS)
There is a potential risk of NMS associated with medicinal products that reduce dopaminergic transmission (see section 4.5). Main symptoms of NMS are mental changes, rigidity, hyperthermia, autonomic dysfunction and elevated creatinine phosphokinase levels. If NMS is suspected, deutetrabenazine should be discontinued immediately and appropriate symptomatic treatment should be initiated.
Akathisia, agitation and restlessness
Deutetrabenazine may increase the risk of akathisia, agitation, and restlessness in patients with tardive dyskinesia (see section 4.8). Patients receiving deutetrabenazine should be monitored for signs and symptoms of restlessness and agitation, as these may be indicators of developing akathisia. If a patient develops akathisia during treatment with deutetrabenazine, the dose should be reduced; some patients may require discontinuation of therapy.
Somnolence
Somnolence is a very common dose-limiting adverse reaction of deutetrabenazine (see section 4.8) and, therefore, patients should be advised to exercise caution when driving or operating machines (see section 4.7). Due to possible additive effects, caution should also be advised when patients are taking other sedating products or alcohol in combination with deutetrabenazine (see section 4.5).
Parkinsonism
Deutetrabenazine may cause parkinsonism in patients with tardive dyskinesia (see section 4.8). If a patient develops parkinsonism, the deutetrabenazine dose should be reduced and discontinuation of treatment should be considered if the event does not resolve.
Binding to melanin-containing tissues
Since deutetrabenazine or its metabolites bind to melanin-containing tissues (e.g. skin and eye), it could accumulate in these tissues over time. This raises the possibility that deutetrabenazine may cause toxicity in these tissues after extended use. The clinical relevance of deutetrabenazine’s binding to melanin-containing tissues is unknown.
Excipients
This medicinal product contains less than 1 mmol sodium (23 mg) per prolonged-release tablet, i.e. is essentially ‘sodium-free’.
This medicinal product contains sunset yellow FCF and/or allura red AC which may cause allergic reactions (see section 2).
4.5 Interaction with other medicinal products and other forms of interaction
Reserpine
Deutetrabenazine and reserpine must not be used concomitantly (see section 4.3). Reserpine binds irreversibly to VMAT2 and the duration of its effect is several days. At least 20 days must elapse after stopping reserpine before starting deutetrabenazine. Prescribers should wait for dyskinesia to re-emerge before administering deutetrabenazine to help reduce the risk of overdose and major depletion of serotonin and noradrenaline in the central nervous system.
Monoamine Oxidase Inhibitors (MAOIs)
Deutetrabenazine must not be used in combination with an MAOI (e.g. moclobemide, tranylcypromine, isocarboxazid, selegiline, rasagiline, safinamide, linezolid) (see section 4.3). At least 14 days must elapse after stopping an MAOI before starting deutetrabenazine.
Other VMAT2 inhibitors
Deutetrabenazine must not be used in patients currently taking other VMAT2 inhibitors (e.g. tetrabenazine) (see section 4.3). Deutetrabenazine can be started the day after the discontinuation of tetrabenazine at a dose which is approximately half the tetrabenazine daily dose.
Medicinal products known to reduce dopaminergic transmission
The risk of parkinsonism, NMS, and akathisia may be increased by concomitant use of medicinal products that reduce dopaminergic transmission (e.g. haloperidol, chlorpromazine, metoclopramide, ziprasidone, promazine), therefore caution is recommended (see section 4.4).
Medicinal products known to prolong the QTc interval
Deutetrabenazine may prolong the QTc interval. Deutetrabenazine should be used with caution in combination with other medicinal products that prolong the QTc interval (see section 4.4). Examples of medicinal products that prolong the QTc interval include: antiarrhythmics class IA (e.g. quinidine, disopyramide) and class III (e.g. amiodarone, sotalol), antipsychotics (e.g. phenothiazine derivatives, pimozide, haloperidol, droperidol, ziprasidone), tricyclic antidepressants (e.g. amitriptyline), selective serotonin reuptake inhibitors (e.g. citalopram, escitalopram), antimicrobials (e.g. fluoroquinolones, triazole derivative (e.g. voriconazole), erythromycin IV, pentamidine, antimalarial medicinal products), and antihistamines (e.g. hydroxyzine, mizolastine).
Alcohol or other sedating products
Concomitant use of alcohol or other sedating products is not recommended, as these may have additive effects and worsen sedation and somnolence (see section 4.4). Examples of sedating products include benzodiazepines (e.g. midazolam, diazepam, lorazepam), antidepressants (e.g. mirtazapine, amitriptyline, trazodone), antipsychotics (e.g. promethazine, chlorprothixene), opioids (e.g. oxycodone, buprenorphine), antihistamines (e.g. diphenhydramine, dimenhydrinate), and centrally acting antihypertensives (e.g. clonidine, moxonidine).
Strong CYP2D6 inhibitors
Concomitant use of strong CYP2D6 inhibitors, such as quinidine (antiarrhythmic and antimalarial medicinal product), and paroxetine, fluoxetine, and bupropion (antidepressants), has been shown to increase the systemic exposure to the active dihydro-metabolites of deutetrabenazine. In the presence of a strong CYP2D6 inhibitor (paroxetine), systemic exposure of the individual active metabolites increased 1.9-fold for deuterated α
-dihydrotetrabenazine [HTBZ] and 6.5-fold for deuterated β
-HTBZ resulting in an overall 3-fold increase in the active metabolites, deuterated total (α
+ β
)-HTBZ (see section 5.2). A reduction in the dose of deutetrabenazine may be necessary when adding a strong CYP2D6 inhibitor in patients maintained on a stable dose of deutetrabenazine. The daily dose of deutetrabenazine should not exceed 36 mg in patients taking strong CYP2D6 inhibitors (see section 4.2).
Levodopa and other dopaminergic medicinal products
Levodopa and other dopaminergic medicinal products (e.g. pramipexole, ropinirole) may reduce the effect of deutetrabenazine. Caution should be applied if deutetrabenazine is used with levodopa and other dopaminergic medicinal products.
4.6 Fertility, pregnancy and lactation
Pregnancy
There is a limited amount of data from the use of deutetrabenazine in pregnant women.
Animal studies are insufficient with respect to reproductive toxicity (see section 5.3).
Austedo is not recommended during pregnancy and in women of childbearing potential not using contraception.
Breast-feeding
It is unknown whether deutetrabenazine or its metabolites are excreted in human milk. A risk to the newborns/infants cannot be excluded. A decision must be made whether to discontinue breast-feeding or to discontinue/abstain from Austedo therapy taking into account the benefit of breast-feeding for the child and the benefit of therapy for the woman.
Fertility
The effect of deutetrabenazine on fertility in humans and animals has not been evaluated. Oral administration of deutetrabenazine to female rats resulted in oestrous cycle disruption (see section 5.3). In animal studies with tetrabenazine, female cycle lengths were increased and a delay in fertility was observed.
4.7 Effects on ability to drive and use machines
Deutetrabenazine has moderate influence on the ability to drive and use machines. Deutetrabenazine may cause somnolence, therefore patients being treated with deutetrabenazine should be advised to refrain from driving or operating hazardous machinery, until they are on a maintenance dose and know how the medicinal product affects them (see section 4.4).
4.8 Undesirable effects
Summary of the safety profile
Most commonly reported adverse reactions associated with deutetrabenazine were somnolence (11%), diarrhoea, dry mouth, and fatigue (each 9%). Somnolence may occur more frequently at the beginning of treatment and decrease with treatment continuation.
The most serious adverse reactions were depression and dysthymic disorder (2%).
Tabulated list of adverse reactions
Adverse reactions from clinical studies and post-marketing reports are presented according to MedDRA system organ classification. Within each frequency grouping, adverse reactions are presented in the order of decreasing seriousness. Frequency categories are based on the following convention: very common (≥
1/10), common (≥
1/100 to < 1/10), uncommon (≥
1/1 000 to < 1/100), rare (≥
1/10 000 to < 1/1 000) and not known (cannot be estimated from the available data).
The following adverse reactions have been identified for deutetrabenazine (see Table 1).
Table 1: List of adverse reactions
| System Organ Class | Frequency | Adverse Reaction |
| Infections and infestations | Common | Urinary tract infection |
| Nasopharyngitis |
| Psychiatric disorders | Common | Depression* |
| Dysthymic disorder* | ||
| Anxiety | ||
| Insomnia | ||
| Agitation** | ||
| Restlessness** | ||
| Nervous system disorders | Very common | Somnolence |
| Common | Akathisia** | |
| Uncommon | Parkinsonism | |
| Gastrointestinal disorders | Common | Diarrhoea |
| Constipation | ||
| Dry mouth | ||
| General disorders and administration site conditions | Common | Fatigue |
| Injury, poisoning and procedural complications | Common | Contusion |
* Preferred terms depression and dysthymic disorder were grouped for frequency calculation.
** Preferred terms agitation, restlessness and akathisia were grouped for frequency calculation.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the Yellow Card Scheme Website: www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple App Store.
4.9 Overdose
Experience with doses higher than the recommended maximum daily dose of 48 mg is limited. Isolated cases of deutetrabenazine overdose (up to 240 mg per day) have been derived from post-marketing reports and literature. The most frequently observed symptoms were: somnolence, increase in movements, fatigue, agitation and restlessness, insomnia, and suicidal ideation. One additional case reported in the literature included a patient taking 720 mg who experienced toxic encephalopathy, dyskinesia, and psychomotor hyperactivity.
In case of symptoms suggestive for overdose, it is recommended that the patient is monitored for any signs or symptoms of adverse events and given appropriate symptomatic treatment if necessary. The possible involvement of multiple medicinal products should always be considered.
No specific antidote is known. Forced diuresis and dialysis are unlikely to be of benefit.
5 PHARMACOLOGICAL PROPERTIES
5.1 Pharmacodynamic properties
Pharmacotherapeutic group: Other nervous system drugs, ATC code: N07XX16.
Mechanism of action
Deutetrabenazine and the major circulating metabolites (deuterated α
-HTBZ and deuterated β
-HTBZ), are reversible inhibitors of VMAT2, resulting in decreased uptake of monoamines into synaptic vesicles and depletion of monoamine stores in dopaminergic regions (e.g. striatum and cortex) of the brain (see section 5.2 “Distribution”). While the precise mechanism of action by which deutetrabenazine exerts its effects in the treatment of tardive dyskinesia is unknown, it is believed to be related to its effect as a depletor of monoamines (such as dopamine, serotonin, norepinephrine, and histamine) from nerve terminals.
Pharmacodynamic effects
Cardiac electrophysiology
At the maximum recommended dose, deutetrabenazine does not prolong the QTc interval to any clinically relevant extent. An exposure-response analysis on QTc prolongation from a study conducted in extensive, intermediate and poor CYP2D6 metabolisers, showed that a clinically relevant effect can be excluded at exposures following daily doses of 24 and 48 mg of deutetrabenazine.
Clinical efficacy and safety
The efficacy of deutetrabenazine was assessed in two 12-week, randomised, double-blind, placebo-controlled trials in adult patients with tardive dyskinesia presenting with symptoms that were bothersome to the patient or caused functional impairment (n=335). These studies included patients who had moderate or severe abnormal movements based on Item 8 of the Abnormal Involuntary Movement Scale (AIMS) and a total motor AIMS score of ≥
6 (based on Items 1 through 7). Enrolled patients had a history of using a dopamine receptor antagonist (DRA, e.g. antipsychotics, metoclopramide) for at least 3 months (or 1 month in patients 60 years of age and older), were psychiatrically stable and had no change in psychoactive medications for at least 30 days (45 days for antidepressants). Background comorbid illnesses included schizophrenia/schizoaffective disorder (n=207, 62%), mood disorder (n=112, 33%), other (neurological, psychiatric and gastrointestinal conditions; n=15, 4%), and missing (n=1, <1%). With respect to concurrent DRA use, 75.5% of the patients were on a stable DRA dose, while 24.5% were not receiving a DRA at baseline. The primary efficacy endpoint in the trials was the total motor AIMS score (the sum of Items 1 to 7 with score range from 0 to 28).
Fixed-dose study (AIM-TD - Study 1)
Study 1 was a 12-week, double-blind, placebo-controlled, fixed-dose trial in adult patients with tardive dyskinesia. A total of 222 patients were randomised into one of four arms: 12 mg deutetrabenazine per day, 24 mg deutetrabenazine per day, 36 mg deutetrabenazine per day, or placebo administered orally. The study included a 4-week dose escalation period and an 8-week maintenance period. The dose of deutetrabenazine was started at 12 mg per day and increased at weekly intervals in 6 mg per day increments to the targeted fixed doses of 12 mg, 24 mg or 36 mg deutetrabenazine per day. Demographics and baseline disease characteristics were comparable between the study arms. Patients had a mean age of 57 years (range: 21 to 81 years), 24% were 65 years of age and older, 48% were male, and 79% were Caucasian.
Deutetrabenazine showed a statistically significant and clinically meaningful improvement in the AIMS total score from baseline compared to placebo for the 24 mg and 36 mg arms (see Table 2). The effect occurred from as early as week 2 and was sustained over the treatment period (see Figure 1).
Table 2: Improvement in AIMS total score in Study 1
| Efficacy endpoint | Placebo (n=58) | Deutetrabenazine 12 mg/day (n=60) | Deutetrabenazine 24 mg/day (n=49) | Deutetrabenazine 36 mg/day (n=55) |
| AIMS total score | ||||
| Mean baseline score (SD) | 9.5 (2.71) | 9.6 (2.40) | 9.4 (2.93) | 10.1 (3.21) |
| LS Mean change from baseline (SE) | -1.4 (0.41) | -2.1 (0.42) | -3.2 (0.45) | -3.3 (0.42) |
| Treatment effect (95% CI) | -0.7 (-1.84, 0.42) | -1.8 (-3.00, -0.63) | -1.9 (-3.09, -0.79) | |
| p-value | 0.001* | |||
LS Mean = Least-squares mean; SD = Standard deviation; SE = Standard error; CI = 2-sided 95% confidence interval
* Multiplicity-adjusted p-value for difference from placebo, statistically significant
Figure 1: Mean change from baseline in AIMS total score in Study 1 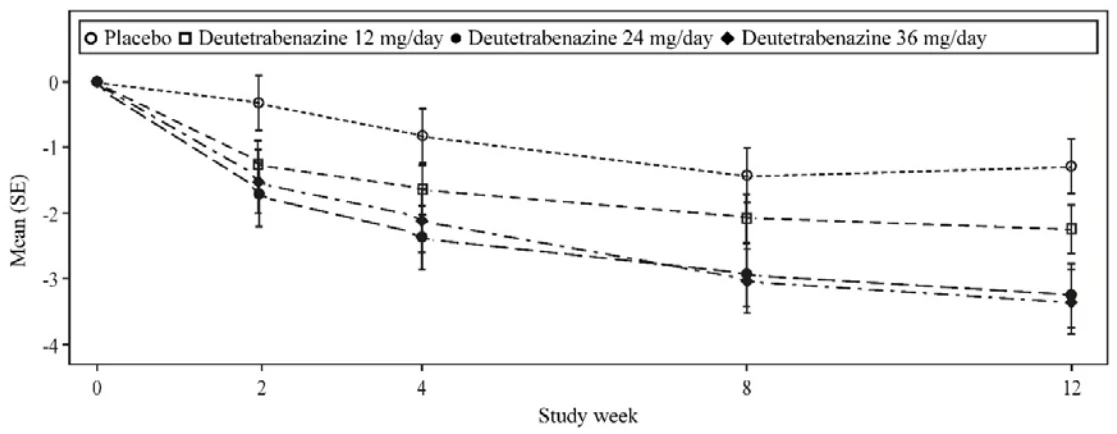
Flexible-dose study (ARM-TD - Study 2)
Study 2 was a 12-week, double-blind placebo-controlled, flexible-dose trial in adults with tardive dyskinesia. A total of 113 patients received daily doses of placebo or deutetrabenazine, starting at 12 mg per day with increases allowed at weekly intervals in 6 mg per day increments until adequate dyskinesia control was achieved, a clinically significant adverse reaction occurred, or the maximum daily dose of 48 mg deutetrabenazine per day was reached. The study included a 6-week dose titration period and a 6-week maintenance period. Patients had a mean age of 55 years (range: 25 to 75 years), 14% were 65 years of age and older, 48% were male, and 70% were Caucasian.
The average dose of deutetrabenazine at the end of treatment was 38.3 mg per day. Deutetrabenazine showed a statistically significant and clinically meaningful improvement in the AIMS total score from baseline compared to placebo (see Table 3).
Table 3: Improvement in AIMS total score in Study 2
| Efficacy endpoint | Placebo (n=57) | Deutetrabenazine 12 mg/day – 48 mg/day (n=56) |
| AIMS total score | ||
| Mean baseline score (SD) | 9.6 (3.78) | 9.7 (4.14) |
| LS Mean change from baseline (SE) | -1.6 (0.46) | -3.0 (0.45) |
| Treatment effect (95% CI) | -1.4 (-2.6, -0.2) | |
| p-value | 0.0188* | |
LS Mean = Least-squares mean; SD = Standard deviation; SE = Standard error; CI = 2-sided 95% confidence interval
* Multiplicity-adjusted p value for difference from placebo, statistically significant
Paediatric population
The Licencing Authority has waived the obligation to submit the results of studies with deutetrabenazine in all subsets of the paediatric population in treatment of tardive dyskinesia (see section 4.2 for information on paediatric use).
5.2 Pharmacokinetic properties
After oral dosing deutetrabenazine undergoes rapid and extensive hepatic metabolism to its active metabolites deuterated α
-HTBZ and deuterated β
-HTBZ resulting in low plasma concentrations of deutetrabenazine compared to that of the active metabolites.
Absorption
Following oral administration of deutetrabenazine, the extent of absorption is at least 80%.
Peak plasma concentrations of deutetrabenazine and its active metabolites (deuterated α
-HTBZ and deuterated β
-HTBZ) are reached within 3 hours after repeated dosing, followed by sustained plateaus for several hours allowing for a 24-hour dosing interval. Absorption is not influenced by food intake.
Distribution
The protein binding of deutetrabenazine, deuterated α
-HTBZ and deuterated β
-HTBZ in human plasma is 82%, 57%, and 49% respectively, with no preferential binding of total radioactivity to the cellular components of human blood after 14C-deutetrabenazine administration.
Single oral dose of either 14C-deutetrabenazine or 14C-tetrabenazine to rats in a quantitative whole-body autoradiography study resulted in similar blood to brain ratios. Results of PET-scan studies in humans showed that following intravenous injection of 11C-tetrabenazine or α
-HTBZ, radioactivity is rapidly distributed to the brain, with the highest binding in the striatum and lowest binding in the cortex. No human PET-scan studies have been performed with deutetrabenazine.
Based on population pharmacokinetic modelling, after oral administration, the apparent volumes of distribution (Vc/F) for deutetrabenazine, deuterated α
-HTBZ, and deuterated β
-HTBZ is 13 700 L, 490 L, and 860 L, respectively.
Biotransformation
In vitro studies using human liver microsomes demonstrate that deutetrabenazine is extensively biotransformed, mainly by carbonyl reductase, to its major active metabolites, deuterated α
-HTBZ and deuterated β
-HTBZ, which are subsequently metabolised primarily by CYP2D6, with minor contributions of CYP1A2 and CYP3A4/5, to form several minor metabolites.
Deutetrabenazine and its active metabolites did not inhibit or induce any CYP enzymes that were studied in vitro at clinically relevant concentrations.
Elimination
In a mass balance study in six healthy subjects, 75% to 86% of the deutetrabenazine dose was excreted in the urine, and faecal recovery accounted for 8% to 11% of the dose. Urinary excretion of deuterated α
-HTBZ and deuterated β
-HTBZ each accounted for less than 10% of the administered dose. Sulphate and glucuronide conjugates of deuterated α
-HTBZ and deuterated β
-HTBZ, as well as products of oxidative metabolism, accounted for the majority of metabolites in the urine.
Based on population pharmacokinetic modelling, after oral administration, for deutetrabenazine, deuterated α
-HTBZ and deuterated β
-HTBZ, the apparent clearance values (CL/F) are 11,750 L/h, 67 L/h, and 260 L/h; the half-lives are 11.4 h, 11 h, and 8.2 h.
Deutetrabenazine and its active metabolites are not substrates or inhibitors of the human transporters, predominantly located in the liver, intestines, central nervous system (CNS) and kidney, that were studied in vitro at clinically relevant concentrations.
Linearity/non-linearity
Dose proportionality was observed in the dose range of 12 mg to 48 mg.
Special populations
Based on population pharmacokinetic analyses there is no apparent effect of gender, race, and age (18-64 years) on the pharmacokinetics of deuterated α
-HTBZ and deuterated β
-HTBZ.
Limited pharmacokinetic data are available for patients 65-74 years of age (approx. 9% of the patients) and 75-84 years of age (approx. 1% of the patients). No data are available for those over 85 years of age. Therefore, no definitive pharmacokinetic conclusions can be made for patients over 65 years of age.
The majority of patients had a body weight of 50 kg to <120 kg, and only a limited number of patients with a body weight of <50 kg or ≥
120 kg were included in clinical trials. Population pharmacokinetic analyses predict higher exposures of deuterated α
-HTBZ and deuterated β
-HTBZ in patients with lower body weights and lower exposures in patients with higher body weights, however, body weight was not correlated to individual response as measured by change in AIMS total score at week 12 of treatment.
Renal impairment
No clinical studies have been conducted to assess the effect of renal impairment on the pharmacokinetics of deuterated α
-HTBZ and deuterated β
-HTBZ. Based on population pharmacokinetic analyses, the effect of renal impairment on the pharmacokinetic exposures of deuterated total (α
+β
)-HTBZ is negligible. As the major route of elimination of the active metabolites is non-renal, it is unlikely that patients with any degree of renal impairment will be exposed to excessive concentrations of deutetrabenazine and its active metabolites.
Hepatic impairment
The effect of hepatic impairment on the pharmacokinetics of deutetrabenazine and its active metabolites has not been studied. Since deutetrabenazine is extensively metabolised in the liver and due to the potential increase in systemic exposure the use of deutetrabenazine in patients with hepatic impairment is contraindicated (see section 4.3).
Poor CYP2D6 metabolisers
Although the pharmacokinetics of deutetrabenazine and its metabolites have not been systematically evaluated in patients who do not express the drug-metabolising enzyme CYP2D6, data in healthy subjects who are poor CYP2D6 metabolisers shows that the exposure to deuterated α
-HTBZ and deuterated β
-HTBZ would be increased similarly to taking strong CYP2D6 inhibitors (maximum exposure increased 2-fold and total exposure approximately 4-fold) (see sections 4.2 and 4.5).
5.3 Preclinical safety data
After 4 weeks of dosing (interim necropsy) in a 3-month toxicology study of deutetrabenazine in rats, observations of oestrus cycle arrest at the pro-oestrus (pre-ovulatory) phase and mammary hyperplasia in females at exposures similar to those expected in patients were likely physiological consequences of reduced CNS dopamine with attendant disinhibition of prolactin. CNS-related observations in this study, including intermittent tremors, partial eye closure, changes in activity, and twitching ears, that were observed at clinically relevant doses, with subclinical exposure to some major metabolites, were likely associated with depletion of monoamine neurotransmitter stores. Male rats from the 3-month study, at deutetrabenazine exposures slightly below clinical exposure levels, showed adverse effect of decreased body weight gains.
Non-rodent toxicology studies of deutetrabenazine were not conducted. However, observations in a toxicology study of another VMAT2 inhibitor (tetrabenazine) that was orally administered to dogs for 9 months revealed CNS-related pharmacological effects similar to rats, including hypoactivity, lethargy, strabismus, or closed eyes at doses associated with major human metabolite exposures below clinical exposure levels.
Deutetrabenazine and its major active metabolites, deuterated α
-HTBZ and deuterated β
-HTBZ, were not genotoxic in a standard battery of in vitro assays, and deutetrabenazine treatment resulted in a negative response for the induction of bone marrow micronuclei in mice.
Carcinogenicity studies of deutetrabenazine were not conducted.
Deutetrabenazine had no effect on embryofoetal development when administered to pregnant rats at doses up to 30 mg/kg/day corresponding to exposure levels (AUC) 119-fold higher than in patients at the maximum recommended dose. Exposure levels (AUC) to deuterated α
-HTBZ were comparable and deuterated β
-HTBZ metabolites were slightly lower than the metabolite levels in humans at the maximum recommended dose.
No embryofoetal development studies in a non-rodent species, or fertility and pre- and post-natal development studies in a rodent species were conducted with deutetrabenazine.
Tetrabenazine had no effects on embryofoetal development when administered to pregnant rabbits during the period of organogenesis at oral doses up to 60 mg/kg/day.
When tetrabenazine was orally administered to pregnant rats (5, 15, and 30 mg/kg/day) from the beginning of organogenesis through the lactation period, an increase in stillbirths and offspring postnatal mortality was observed at 15 and 30 mg/kg/day and delayed pup maturation was observed at all doses. A no-effect dose for pre- and postnatal developmental toxicity in rats was not identified.
6 PHARMACEUTICAL PARTICULARS
6.1 List of excipients
Tablet core
Butylhydroxyanisole (E 320)
Butylhydroxytoluene (E 321)
Macrogol high-molecular-mass 200K
Macrogol high-molecular-mass 5000K
Hypromellose 2910
Sodium chloride
Allura red AC (E 129)
Magnesium stearate
Cellulose acetate
Macrogol 3350
Hydroxypropylcellulose
Film-coating
Poly(vinyl alcohol)
Titanium dioxide (E 171)
Macrogol 3350
Talc
Indigo carmine (E 132)
Allura red AC (E 129)
Printing ink
Shellac
Iron oxide black (E 172)
Propylene glycol
6.2 Incompatibilities
Not applicable.
6.3 Shelf life
3 years
6.4 Special precautions for storage
This medicinal product does not require any special storage conditions.
6.5 Nature and contents of container
PVC/PCTFE/PVC-Aluminium blisters
Packs of 28 and 84 prolonged-release tablets.
Not all pack sizes may be marketed.
6.6 Special precautions for disposal
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
7 MARKETING AUTHORISATION HOLDER
Teva UK Limited,
Ridings Point,
Whistler Drive,
Castleford,
WF10 5HX,
United Kingdom
8 MARKETING AUTHORISATION NUMBER(S)
PL 00289/2638
9 DATE OF FIRST AUTHORISATION/RENEWAL OF THE
AUTHORISATION
30/01/2026
10 DATE OF REVISION OF THE TEXT
30/01/2026